


Form HHS-520 at a glance
What it is: HHS-520: Department of Health and Human Services request for approval of outside activity under the Standards of Ethical Conduct Regulation and the HHS Supplemental Ethics Regulation (5 CFR 2635.803, 5 CFR 5501.106(d)).
Who signs: The employee signs and dates under EMPLOYEE SIGNATURE DATE.
Disclosure of this information is mandatory for employees seeking prior authorization from an agency designee to pursue outside employment or activities pursuant to Sections 2635.803 and 5501.106(d) of Title 5 of the Code of Federal Regulations.
A filled-in Form HHS-520 example: an employee fills in page 1
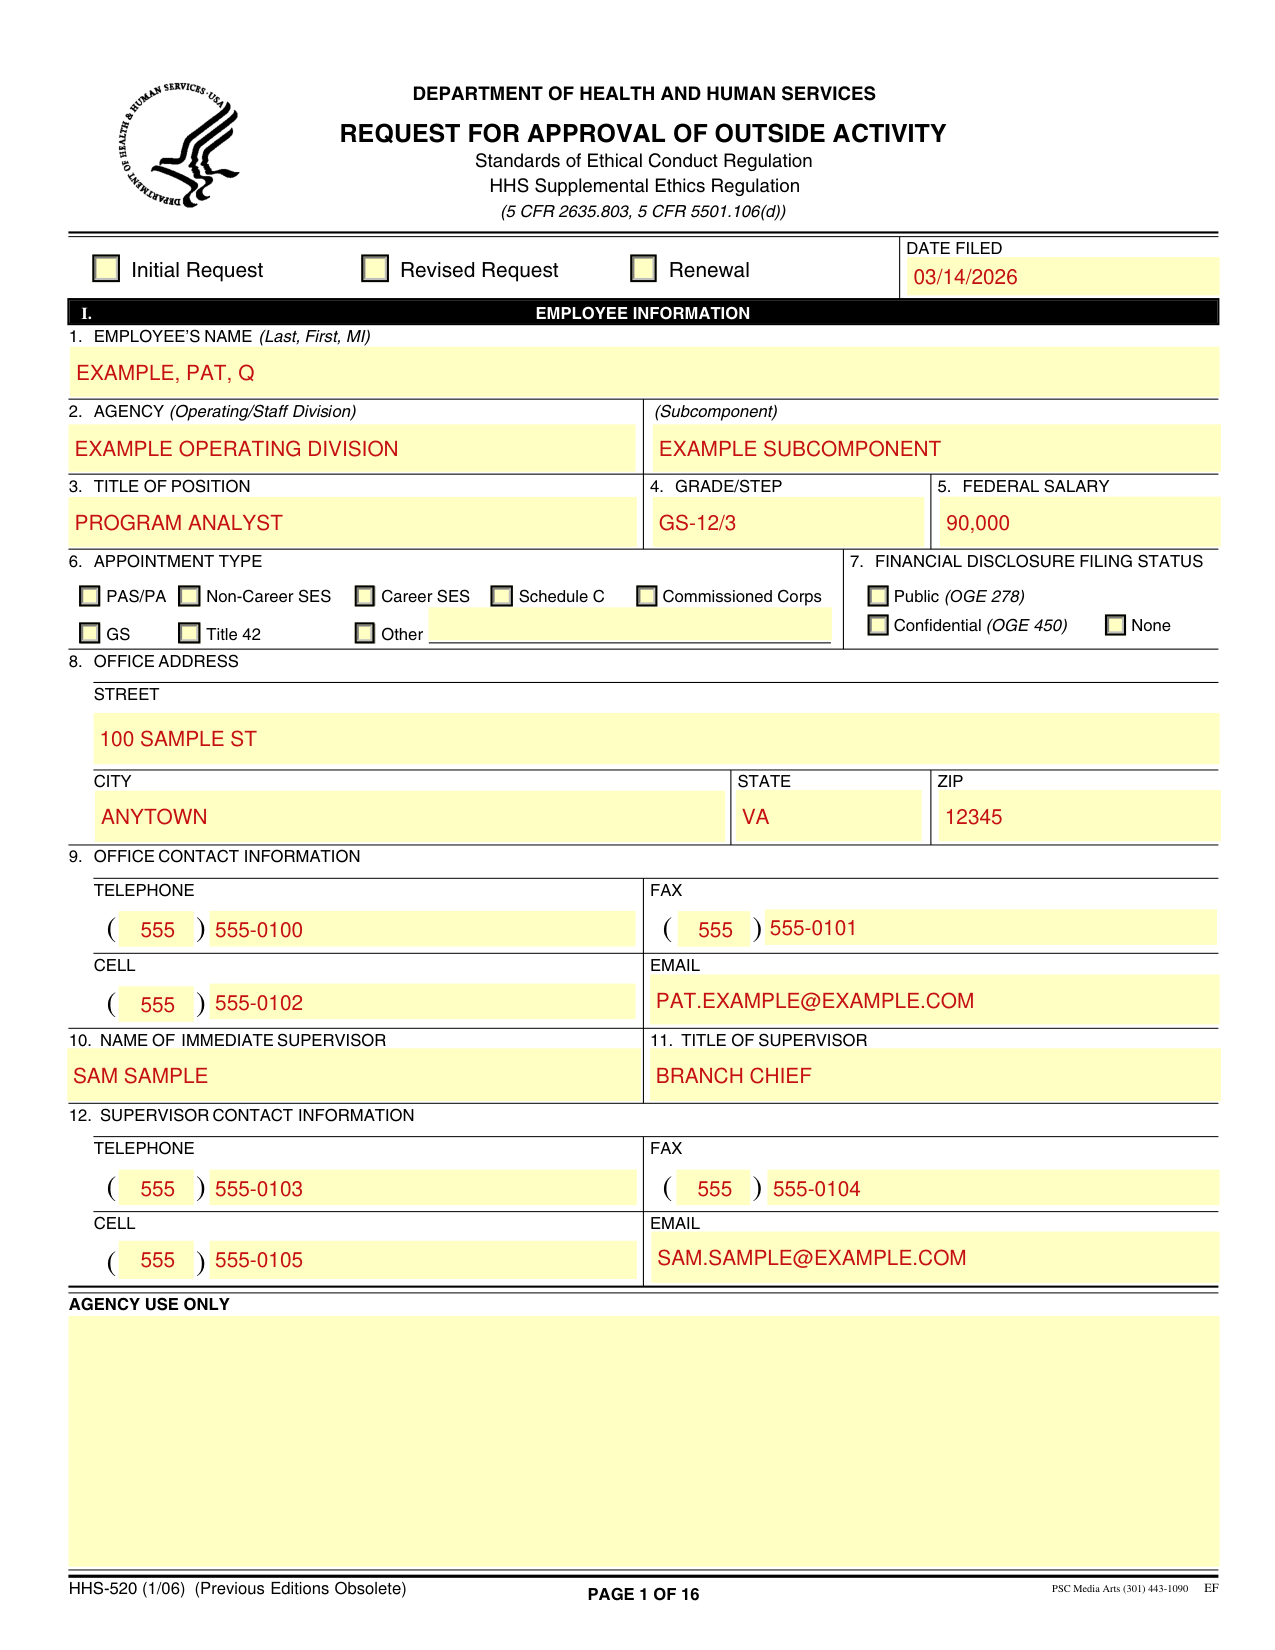
How to fill out Form HHS-520, box by box
Employee information
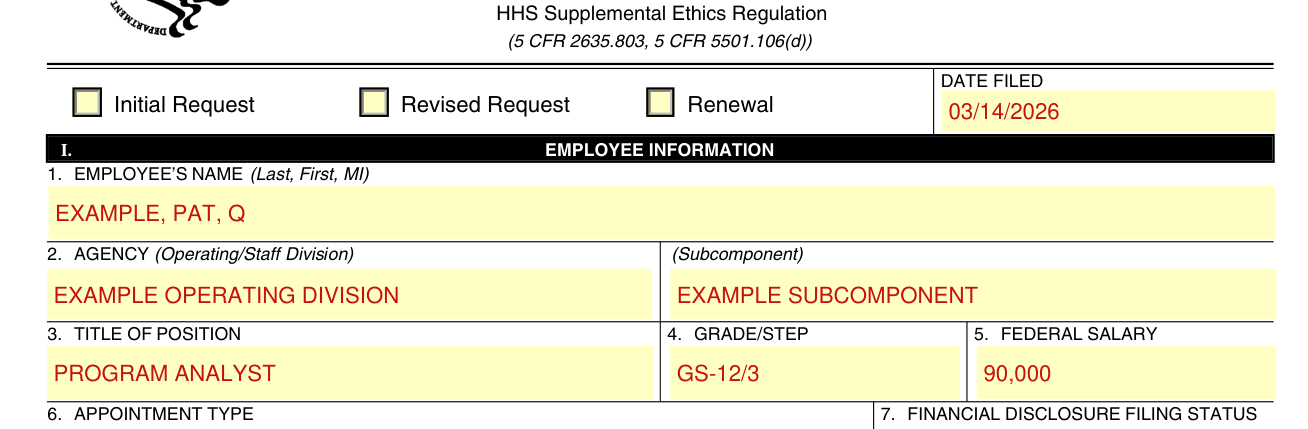
Under DATE FILED, Initial Request, Revised Request or Renewal.
Enter in box 1 the EMPLOYEE'S NAME (Last, First, MI).
Enter in box 2 the AGENCY (Operating/Staff Division) and (Subcomponent).
Enter in box 3 the TITLE OF POSITION and in box 4 the GRADE/STEP.
Enter in box 5 the FEDERAL SALARY.
In box 6, APPOINTMENT TYPE, PAS/PA, Career SES, Non-Career SES, Schedule C, Commissioned Corps, GS, Title 42 or Other.
In box 7, FINANCIAL DISCLOSURE FILING STATUS, None, Confidential (OGE 450) or Public (OGE 278).
Office address and contact information
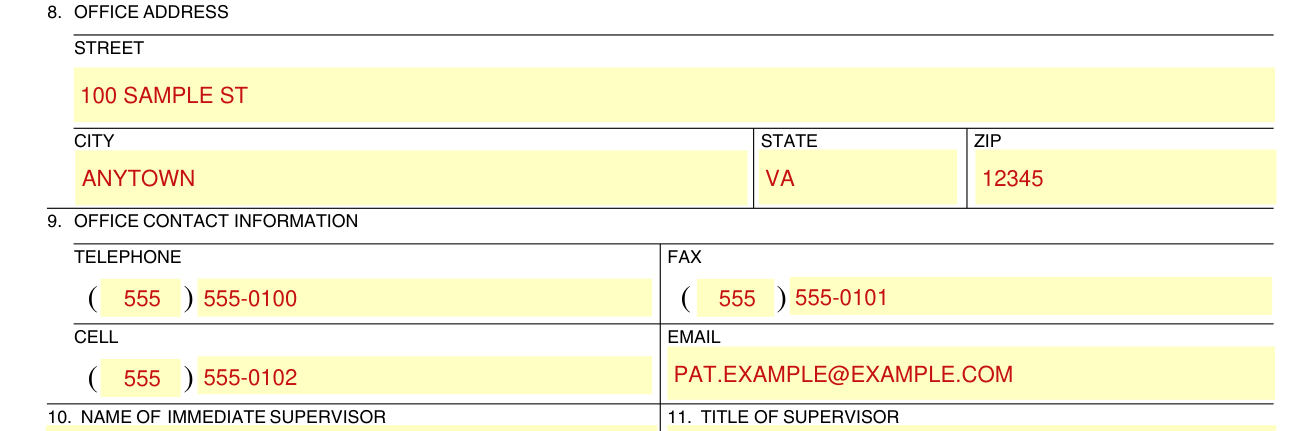
In box 8, OFFICE ADDRESS, enter the STREET, CITY, STATE and ZIP.
In box 9, OFFICE CONTACT INFORMATION, and in box 12, SUPERVISOR CONTACT INFORMATION, enter the TELEPHONE, FAX, CELL and EMAIL.
Immediate supervisor
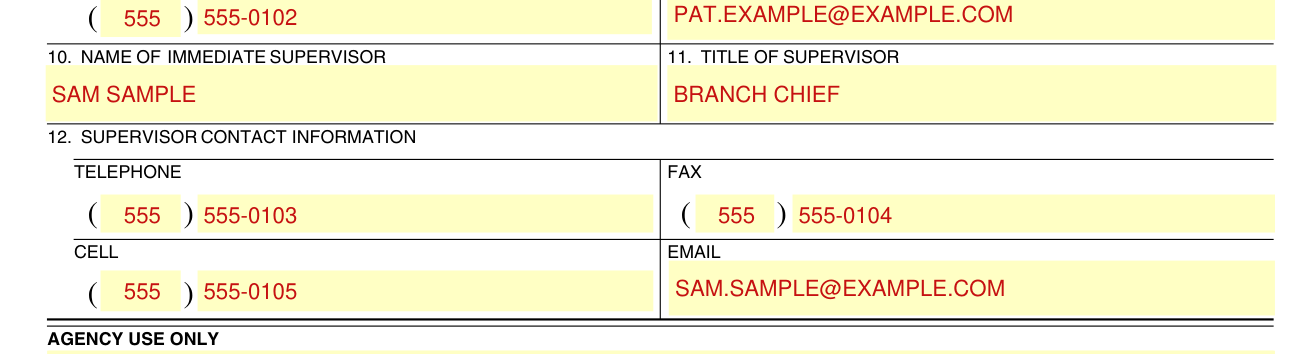
Enter in box 10 the NAME OF IMMEDIATE SUPERVISOR and in box 11 the TITLE OF SUPERVISOR.
More rules for Form HHS-520
If your request for prior approval is granted, the approval is effective for a period not to exceed one year from the date of approval.
Failure to provide all or part of the requested information may result in denial of the request for approval of the outside employment or activity.
An employee cannot undertake an outside activity that conflicts with the employee's official duties. An activity conflicts with official duties: (a) if it is prohibited by statute or regulation; or (b) if, under the standards in 5 CFR 2635.402 and 2635.502, it would require the employee's recusal from matters so central or critical to the performance of his or her official duties that the employee's ability to perform the duties of his or her position would be materially impaired.
For example, if you want to lobby Federal agencies on behalf of a non-profit organization that employs you, prior approval will be denied because a criminal statute prohibits such representational activities.
Approval of an outside activity does not release you from a continuing legal obligation to disqualify yourself from official assignments affecting your outside employer or the entity to which you are providing personal services.
STAPLE ATTACHMENTS TO THIS PAGE 14 List each attachment in the space provided and append copies.
ADDITIONAL SPACE Identify the part and item number to which the additional information refers.
Outside Activity Information and Official Duty Information
Nature of Outside Activity
Indicate the type of activity for which you request prior approval, and describe fully the specific duties or services to be performed: Professional or Consultative Activities, Teaching, Speaking, Writing or Editing, Board Service, Expert Witness or Other (Describe).
For activities involving teaching, speaking, or writing, provide a syllabus, outline, summary, synopsis, draft, or similar description of the content and subject matter involved in the course, speech, or written product (including, if available, a copy of the text of any speech) and the proposed text of any disclaimer that indicates that the views expressed do not necessarily represent the views of the agency or the United States. Check the applicable boxes indicating that these materials are attached. If you are unable to provide this information, or will be delayed in submitting the attachments, please explain in Explain.
Outside Employer or Other Entity
Identify the outside employer or other person for whom or organization for which the proposed activity will be performed or conducted. Give the name and title of a contact person. In Items 3 and 4, provide address and contact information for the outside entity.
For the Outside Entity Address, enter the STREET, CITY and STATE and ZIP; for Contact information, enter the TELEPHONE, FAX, CELL and EMAIL.
Location and Travel
Indicate the location where the activity or services will be performed.
Indicate whether travel is involved, and if so, whether the transportation, lodging, meals, or per diem will be at your own expense or provided by the outside entity in kind or through reimbursement. Describe arrangements and provide estimated costs of items to be furnished or reimbursed by the outside entity.
Time
If you wish to continue an activity beyond the one year approval period, you must renew your request no later than thirty days prior to the expiration of the period authorized.
Provide details with respect to the duration, frequency, and timing of the activity.
In a. Period Covered, enter From (mm/dd/yy) and To (mm/dd/yy); in b. Estimated Total Time Devoted to the Proposed Activity, enter the Hours per Day, Days per Week and Weeks per Year.
Will work be performed entirely outside of usual working hours? (If "no," estimate the number of hours or days that you will be absent from work and indicate the type of leave to be requested.)
Compensation
Indicate whether the activity is compensated, and if so, answer the questions.
In a. Method or Basis of Compensation, check all boxes that apply: Fee, Honorarium, Retainer, Salary, Advance, Stock Options, Royalty, Stock, Non-Travel Related Expenses (describe) or Other (specify).
Indicate the total amount of compensation to be received for the proposed activity for the period covered by this request. Do not include the amount of any travel expenses to be provided by the outside entity that were reported in Part II, Item 6.
If any compensation will be received from a payor other than the entity to which personal services will be provided, identify the payor and explain.
Indicate whether any compensation is derived from an HHS grant, contract, cooperative agreement, or other source of HHS funding or if the services to be performed are related to an activity funded by HHS, regardless of the specific source of the compensation. If "yes," describe.
For activities involving the provision of consultative or professional services, indicate whether the client, employer, or other person on whose behalf the services are performed is receiving, or intends to seek, an HHS grant, contract, cooperative agreement, or other funding relationship. If "yes," describe.
Record of Prior Compensation from Same Source
Identify the source, activity, amount and date of any compensation received, or due for services performed, within the last six calendar years and the current year through the date this request is submitted, from the person for whom or the organization with which the current work or activity will be done (including any amount received or due from an agent, affiliate, parent, subsidiary, or predecessor of the proposed payor). This information must be provided as to any outside activity performed for the person or organization that is the subject of this request for approval. Include any prior activity that is the same or similar to the present request, as well as any unrelated activity involving the same source.
Official Duty Information
Describe the principal duties and responsibilities of your current position. You may attach a copy of your position description in lieu of providing the description unless you currently have significant duties or assignments that are not reflected in that document.
Describe any official duties that relate in any way to the proposed activity. If none, explain why.
In performing your official duties, explain how your actions or the matters upon which you may be called upon to work could affect the interests of the person for whom or the organization for which the proposed activity will be performed. If the exercise of your official duties would not have such an effect, explain why.
Describe any official duty assignments or other interactions you have had that involve the person for whom or the organization for which the proposed activity will be performed and indicate when such assignments or interactions occurred. If none, explain.
Certification
Under CERTIFICATION, the undersigned employee certifies that the notices in Part VIII have been read and understood and that the statements made and information provided on this form are true, complete, and correct to the best of the individual's knowledge.
Common questions about Form HHS-520
Who signs it?
The employee signs and dates under EMPLOYEE SIGNATURE DATE.
Is there a penalty?
Knowing and willful falsification of information required to be reported may subject the employee to criminal prosecution.
Sources
[1] Form HHS-520 (1/06), Request for Approval of Outside Activity, U.S. Department of Health and Human Services (the Official source link on this page).