


Form IHS-810 at a glance
What it is: The Indian Health Service of the Department of Health and Human Services prints this form as the Authorization for Use or Disclosure of Protected Health Information.
Who signs: The patient or personal representative signs and dates (mm/dd/yyyy); a personal representative states the relationship to the patient. Specific provisions regarding the use or disclosure of substance use disorder records: By signing you state: I understand that my substance use disorder records are protected under federal law, including the federal regulations governing the confidentiality of substance use disorder patient records, 42 CFR Part 2, the Health Insurance Portability and Accountability Act Privacy Rule [45 CFR Part 164], and the Privacy Act of 1974 [5 USC 552a], and cannot be disclosed without my written consent unless otherwise provided for by the regulations. I understand that if I am authorizing the disclosure of my substance use disorder records to a Health Information Exchange pursuant to a general designation, I have the right to receive a list of all such disclosures made from the Health Insurance Exchange.
A filled-in Form IHS-810 example: a patient sends records to her doctor

How to fill out Form IHS-810, box by box
I. AUTHORIZATION

Section I, print your name or the name of patient whose information is to be released.
I, (Name of Patient), hereby voluntarily authorize the disclosure of information from my health record.
II. THE INFORMATION IS TO BE DISCLOSED BY
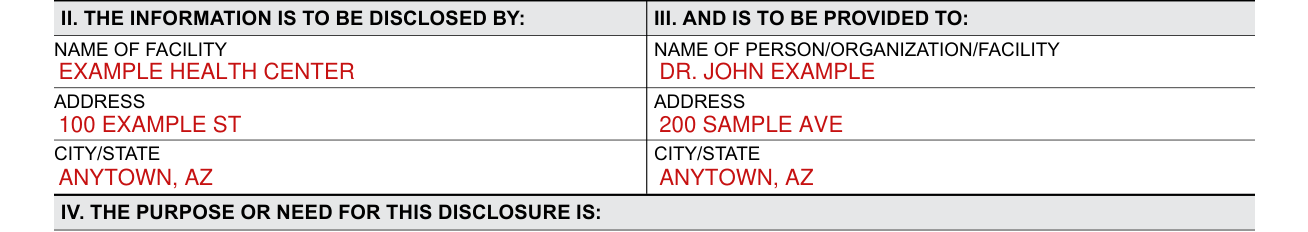
II. THE INFORMATION IS TO BE DISCLOSED BY: NAME OF FACILITY, ADDRESS and CITY/STATE.
Section II, print the name and address of the facility releasing the information.
III. AND IS TO BE PROVIDED TO
Section III, provide the name of the person, facility, and address that will receive the information.
If the information is being disclosed to prevent multiple enrollments in a withdrawal management or maintenance treatment program, please provide the name of each central registry, withdrawal management, and maintenance treatment program to which disclosure may be made OR state “any withdrawal management or maintenance treatment program within 200 miles of [IHS Facility permitted to make the disclosure]”.
IV. THE PURPOSE OR NEED FOR THIS DISCLOSURE IS

Under IV. THE PURPOSE OR NEED FOR THIS DISCLOSURE IS, the boxes are Treatment, Payment or Other Healthcare Operations, Attorney, School, Other (Specify), Personal Use, Disability, Research and Health Information Exchange (IHS/Other).
Section IV, state the reason why the information is needed, e.g., disability claim, continuing medical care, legal, research-related projects, etc.
For an Health Information Exchange (HIE) other than IHS, please provide the name of the HIE, as well as the name or general designation of the HIE participants who may access your records (e.g., a specific provider(s) or “my current and future treating providers”).
V. THE INFORMATION TO BE DISCLOSED FROM MY HEALTH RECORD
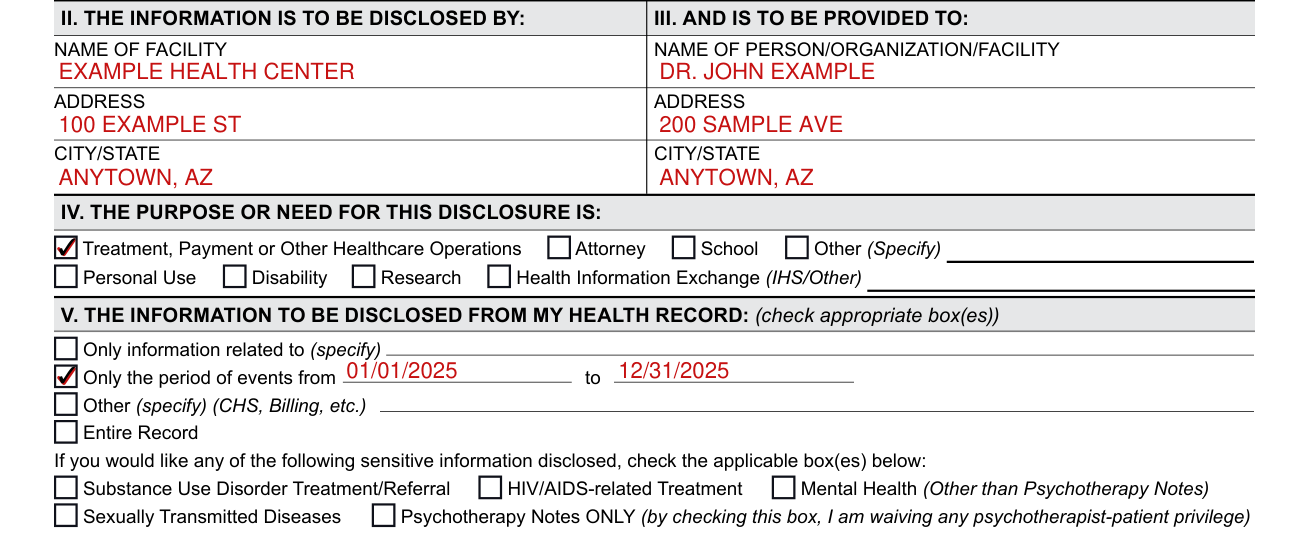
Section V, check the appropriate box as applicable.
Only information related to - specify diagnosis, injury, operations, special therapies, etc.
Only the period of events from - specify date range, e.g., Jan. 1, 2002, to Feb. 1, 2002.
Other (specify) - e.g., Purchased Referred Care (PRC), Billing, Employee Health.
Entire Record - complete record including, if authorized, the sensitive information (alcohol and drug abuse treatment/referral, sexually transmitted diseases, HIV/AIDS-related treatment, and mental health other than psychotherapy notes).
In order to release sensitive information regarding alcohol/drug abuse treatment/referral, HIV/AIDS-related treatment, sexually transmitted diseases, mental health (other than psychotherapy notes), the appropriate box or boxes must be checked by the patient.
Psychotherapy Notes ONLY - in order to authorize the use or disclosure of psychotherapy notes (which are separate from progress notes and contain the therapist's impressions and the content of psychotherapy conversations), only this box should be checked on this form.
Authorizations for the use or disclosure of other health record information may not be made in conjunction with authorizations pertaining to psychotherapy notes.
If this box is checked with other boxes, another authorization will be required to authorize the use or disclosure of psychotherapy notes only.
VI. AUTHORIZATION

Section VI, if a different expiration date or event is desired, please specify.
When you opt-in to share information through the HIE, an expiration date must be entered; it is recommended that a date five (5) years into the future be entered to provide for continuity of care.
If authorizing the release of records for court-ordered substance use disorder treatment, the expiration date/event must be no later than the final disposition of the criminal proceeding.
Section VI, Please sign (or mark) and date.
Signature of Witness (If signature of patient is a thumbprint or mark) and Date (mm/dd/yyyy).
I understand that I may revoke this authorization in writing submitted at any time to the Health Information Management Department, except to the extent that action has been taken in reliance on this authorization. If this authorization has not been revoked, it will terminate one year from the date of my signature unless a different expiration date or expiration event is stated.
The information is to be released for the purpose stated in IV and may not be used by the recipient for any other purpose. Any person who knowingly and willfully requests or obtains any record concerning an individual from a Federal agency under false pretenses shall be guilty of a misdemeanor (5 USC 552a(i)(3)).
PATIENT IDENTIFICATION
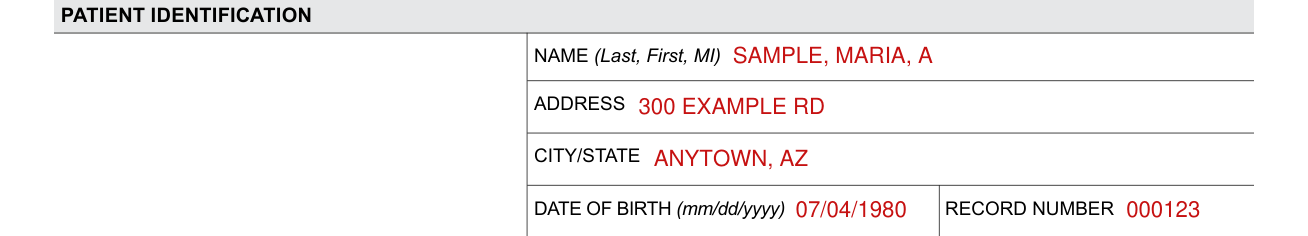
Under PATIENT IDENTIFICATION, enter the NAME (Last, First, MI), ADDRESS, CITY/STATE, DATE OF BIRTH (mm/dd/yyyy) and RECORD NUMBER.
More rules for Form IHS-810
Complete all sections, date, and sign.
Print legibly in all fields using dark permanent ink.
I understand that IHS will not condition treatment or eligibility for care on my providing this authorization.
A copy of the completed IHS-810 form will be given to you.
The time required to complete this information collection is estimated to average less than 10 minutes per response, including the time to review instructions, search existing data resources, gather the data needed, to review and complete the information collection.
Sources
[1] Form IHS-810 (05/24), Authorization for Use or Disclosure of Protected Health Information, Indian Health Service (the Official source link on this page).