

Form L at a glance
What it is: Form L is the Physician Licensure Evaluation of the Texas Medical Board for the Verification of Postgraduate Training and Professional Evaluation.
Who signs: The applicant signs on page 1: I authorize the release of the information contained in this evaluation form to the Texas Medical Board. A physician who currently holds the position of Chief of Staff, Department Chairman, Medical Director, or Training Director must complete this evaluation.
A filled-in Form L example: a resident's applicant box

How to fill out Form L, box by box
Applicant and the evaluating hospital/institution
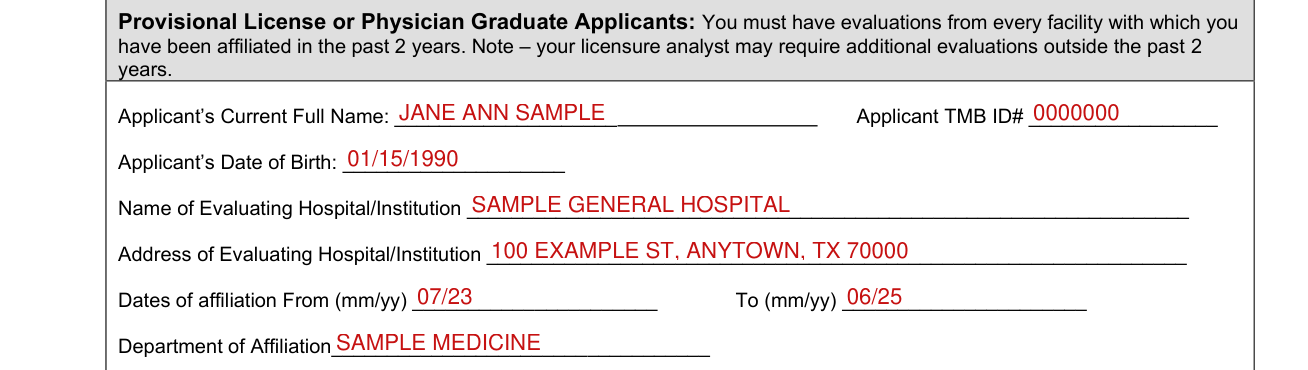
Applicant: Complete the information in this box. Enter Applicant's Current Full Name, Applicant TMB ID# and Applicant's Date of Birth.
Full, Admin, Conceded Eminence, or Physician-in-Training Applicants: You must have evaluations from every facility with which you have been affiliated in the past 5 years. Note - your licensure analyst may require additional evaluations outside the past 5 years.
Provisional License or Physician Graduate Applicants: You must have evaluations from every facility with which you have been affiliated in the past 2 years. Note - your licensure analyst may require additional evaluations outside the past 2 years.
Enter the Name of Evaluating Hospital/Institution, the Address of Evaluating Hospital/Institution, the Dates of affiliation From (mm/yy) and To (mm/yy) and the Department of Affiliation.
Your position at the time of affiliation

Mark your position at the time of affiliation: Intern, Resident, Fellow, Faculty, Staff or Other.
Applicant's Signature
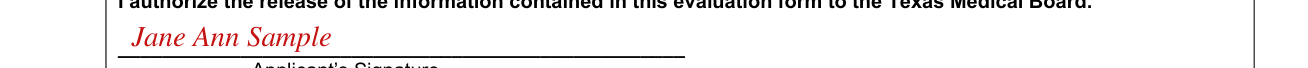
Sign on the Applicant's Signature line: I authorize the release of the information contained in this evaluation form to the Texas Medical Board.
Sending the evaluation
EVALUATING PHYSICIAN: This completed evaluation should be sent directly to the Texas Medical Board offices via mail, fax, or email.
By mail - Evaluating Physician: Place this form in an envelope of the hospital/institution that you represent, seal the envelope and place your signature over the outside sealed envelope flap. Send to: Texas Medical Board, MC-240, P.O. Box 2029, Austin, TX 78768-2029
By fax - Evaluator must submit the form along with an official hospital/institution coversheet to 888-550-7516. Fax submitted by the applicant and/or without the appropriate coversheet cannot be accepted.
By email - Evaluator must submit the form from an official practice/institution email address to screen-cic@tmb.texas.gov. Emails sent from the applicant cannot be accepted.
Letters of recommendation or standard institution verification forms will not be accepted in lieu of this form.
Verification of post graduate training
Verification of Post Graduate Training: Only post-graduate training completed at this institution should be evaluated in this section.
For each Post Graduate Training Program Participation, enter the Department, the PGY and Internship, Residency, Fellowship or Research, and From and To.
Credit received? Full, Partial or in progress. *For partial credit - how many months?
Report incomplete postgraduate years (PGY) separately from those that were successfully completed. If the postgraduate year is currently in progress, report the expected completion date in the “To” field.
Unusual circumstances
UNUSUAL CIRCUMSTANCES: (For training positions only) Yes or No 1. Did this individual ever take a leave of absence or break from training? Yes or No 2. Did this individual resign from training? Yes or No 3. Were any limitations or special requirements placed upon this individual for professionalism or behavioral issues? Yes or No 4. Did this individual ever receive a written warning or documented counseling about his/her behavior? Yes or No 5. Was this individual ever placed on probation for any reason? Yes or No 6. Is this individual currently under investigation? Yes or No 7. Were this individual's privileges or duties ever reduced, suspended, or revoked? Yes or No 8. Did this individual experience delayed promotion or delayed advancement to the next level? Yes or No 9. Was this individual informed his/her contract would not be renewed? Yes or No 10. Was this individual suspended, terminated, or dismissed from training? If you answered "yes" to any of the 10 questions, please provide any additional information you may have.
Verification of Professional History
1. This evaluation is based on Personal Knowledge or Review of Credential File. 2. Is this applicant related to you? Yes or No.
3. Do you consider the applicant: (a) Reliable? Yes or No (b) Ethical? Yes or No (c) Of good character? Yes or No
4. Please rate the applicant: Excellent, Good, Average or Poor on (a) Professional ability, (b) Attention to duties, (c) Breadth of education and (d) Interpersonal skills.
5. Has applicant, to your knowledge, ever been guilty of: (a) Fraud or dishonesty? Yes or No (b) Unprofessional conduct? Yes or No
To your knowledge, has the applicant ever
6. To your knowledge, has the applicant ever: (a) been warned, censured, reprimanded, disciplined, had admissions monitored or privileges limited or suspended? Yes or No (b) had disciplinary action taken against him/her by a licensing agency? Yes or No (c) been denied or surrendered a federal or state controlled substance permit? Yes or No (d) been arrested, fined, charged with or convicted of a crime, indicted, imprisoned or placed on probation? Yes or No (e) been a defendant in a legal action involving professional liability (malpractice) or had a professional liability claim paid in his/her behalf or paid such a claim him/herself? Yes or No (f) been placed on probation, asked to withdraw, or reprimanded? Yes or No (g) been terminated, resigned in lieu of termination or during investigation? Yes or No If you answered "yes" to any of Question 5 and/or 6, please provide any additional information you may have, including the names of other individuals who may have information concerning this applicant.
7. Provide dates of affiliation: Beginning month and year, Ending month and year.
Evaluating Physician's Name/Degree and signature
Enter the Evaluating Physician's Name/Degree, Title (Chief of Staff, Department Chair, Medical Director or Training Director), Phone, Fax, Address and Email Address, then Signature and Date.
More rules for Form L
All information on this Form L, (including attachments that you provide as the Evaluating Physician) regarding a licensure applicant is confidential pursuant to §164.007(c) of the Medical Practice Act. However, the Board must provide a copy of this Form L and attachments to an applicant when an application is referred to the Licensure Committee for licensure determination.
Training and non-training positions
You are in a training position
FOR TRAINING POSITIONS - Completion of the Verification of Post Graduate Training on page 2 and the Verification of Professional History on page 3 are required.
You are in a non-training position
FOR NON-TRAINING POSITIONS - Only completion of the Verification of Professional History on page 3 is required.
Sources
[1] Form L Physician Licensure Evaluation (Version 01.2026), Texas Medical Board (the Official source link on this page).
