

Form M13D at a glance
What it is: The Consumer Directed Personal Assistance Program Application is M-13d (E) 04/09/2018.
Who signs: The consumer, parent, legal guardian or designated representative signs under Signature, then enters Relationship to Consumer and Date. Note: If the consumer has skilled nursing tasks, a registered nurse must complete the attached certification.
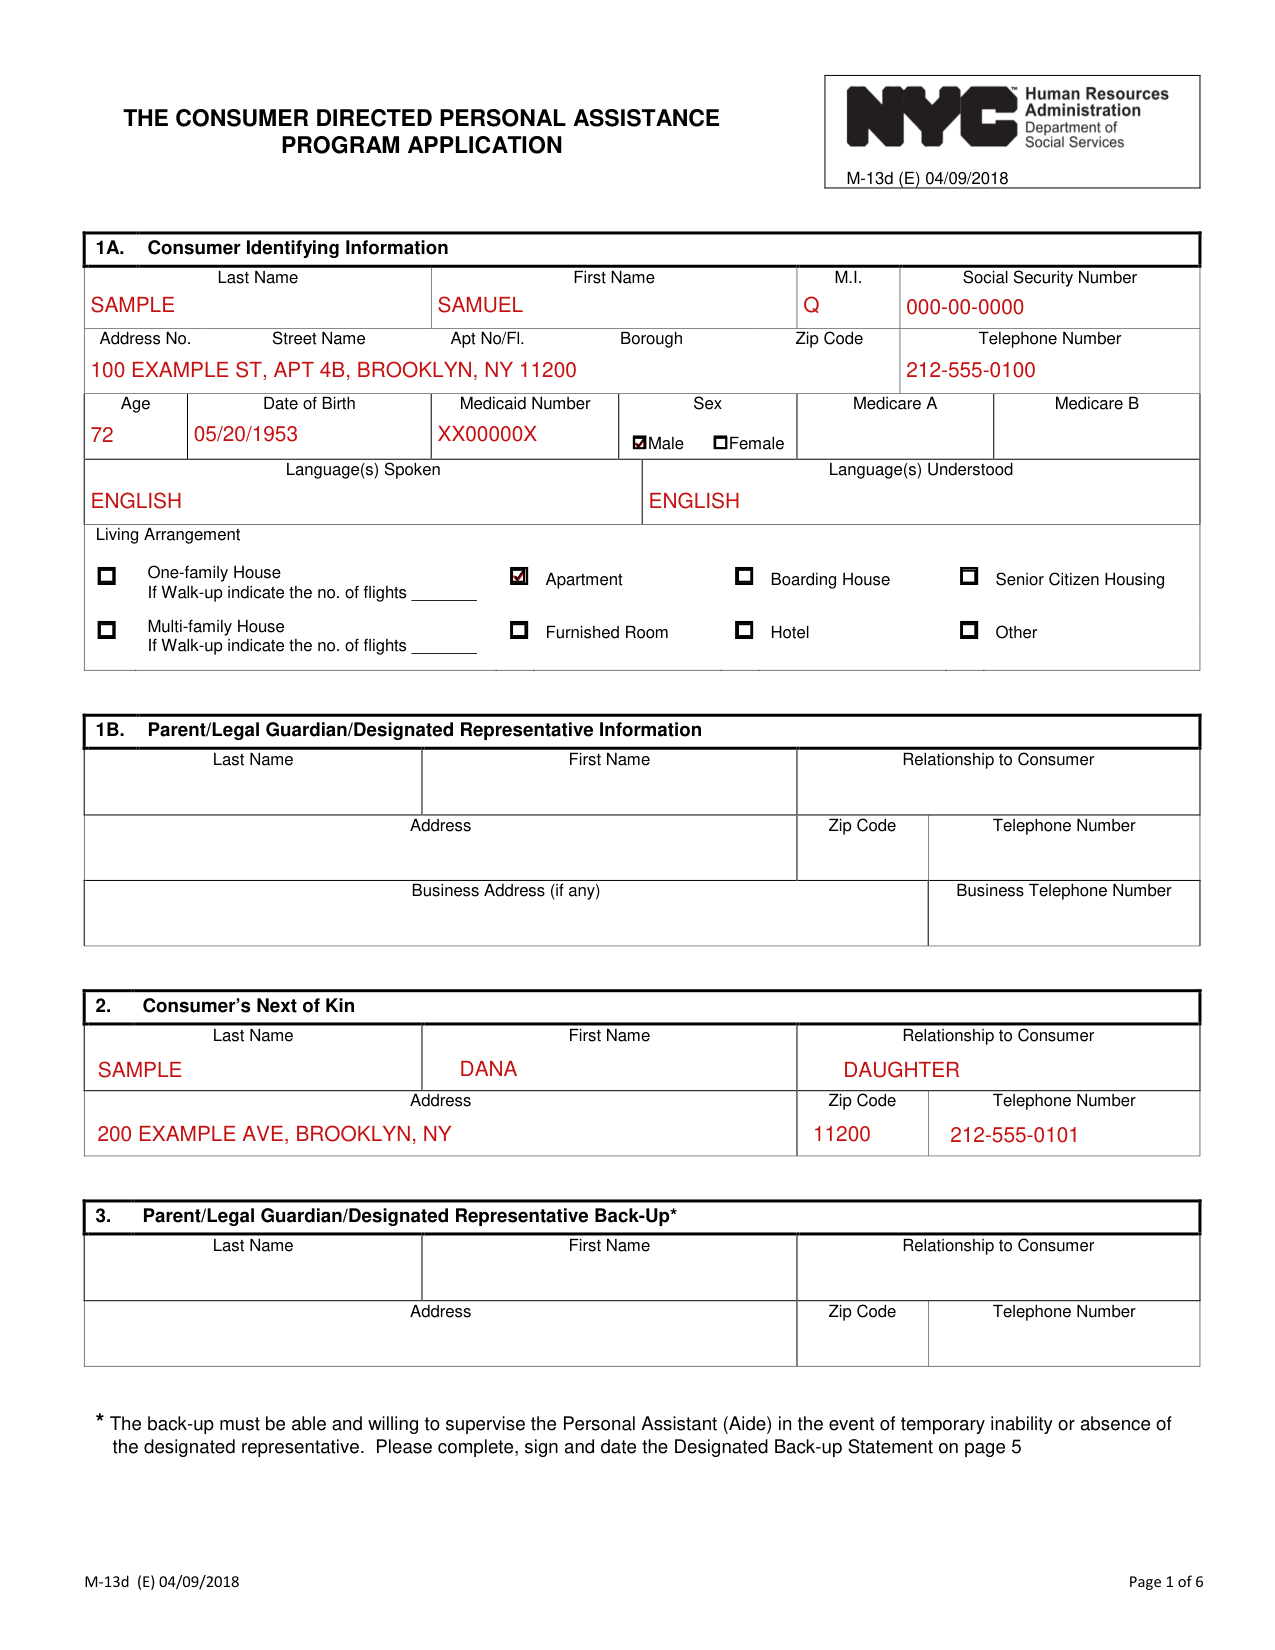
A filled-in Form M13D example: a consumer applies from an apartment
How to fill out Form M13D, box by box
1A. Consumer Identifying Information
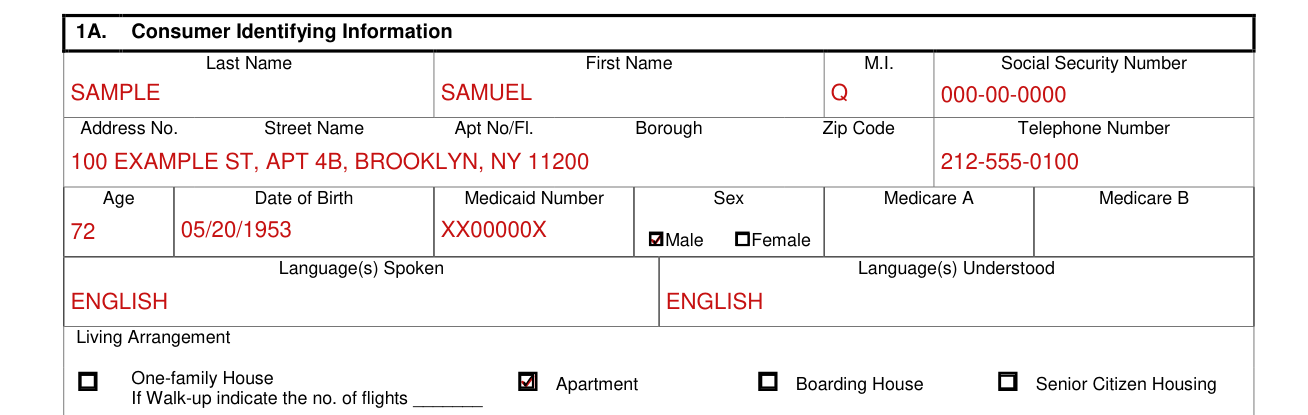
In 1A. Consumer Identifying Information, enter Last Name, First Name, M.I., Social Security Number, Address (No., Street Name, Apt No/Fl., Borough, Zip Code), Telephone Number, Age, Date of Birth, Medicaid Number, Medicare A, Medicare B, Language(s) Spoken and Language(s) Understood.
Mark Male or Female under Sex.
Living Arrangement

Under Living Arrangement, mark One-family House, Multi-family House, Apartment, Furnished Room, Boarding House, Hotel, Senior Citizen Housing or Other. If Walk-up indicate the no. of flights next to One-family House or Multi-family House.
1B. Parent/Legal Guardian/Designated Representative Information

In 1B. Parent/Legal Guardian/Designated Representative Information, enter Last Name, First Name, Relationship to Consumer, Address, Zip Code, Telephone Number, Business Address (if any) and Business Telephone Number.
2. Consumer's Next of Kin
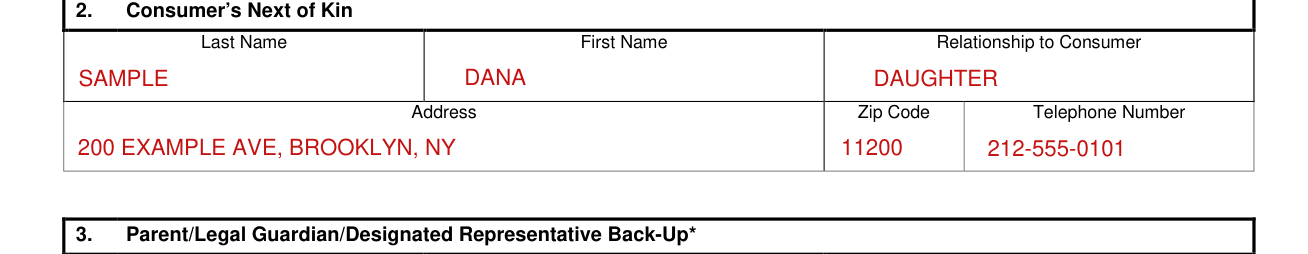
In 2. Consumer's Next of Kin, enter Last Name, First Name, Relationship to Consumer, Address, Zip Code and Telephone Number.
3. Parent/Legal Guardian/Designated Representative Back-Up*

In 3. Parent/Legal Guardian/Designated Representative Back-Up*, enter Last Name, First Name, Relationship to Consumer, Address, Zip Code and Telephone Number.
For 3. Parent/Legal Guardian/Designated Representative Back-Up*, * The back-up must be able and willing to supervise the Personal Assistant (Aide) in the event of temporary inability or absence of the designated representative. Please complete, sign and date the Designated Back-up Statement on page 5
The Designated Representative Back-Up must write a statement confirming that she or he is willing to direct and supervise the Personal Assistant (Aide) in the event of the temporary inability or absence of the Designated Representative. The Designated Representative Back-Up must sign and date the statement in the spaces provided.
4. Describe Consumer's Medical Condition and Personal Situation

In 4, Describe Consumer's Medical Condition and Personal Situation.
5. Screening and Recruitment Plan

In 5. Screening and Recruitment Plan: A. Describe how the consumer, legal guardian or designated representative will screen and recruit prospective personal assistants. B. Describe how the consumer, legal guardian, or designated representative will screen and recruit sufficient, additional personal assistants to serve as replacement workers when needed. C. Describe how the consumer, legal guardian or designated representative will arrange for emergency coverage to maintain continuity of service in the absence of the regularly assigned personal assistant. D. Explain how the consumer, legal guardian or designated representative will provide orientation to conditions of employment for new personal assistants. E. Describe how the consumer, legal guardian or designated representative plans to direct and monitor the personal assistant's job performance.
F. Describe how the designated representative will supervise the personal assistant when he/she is performing skilled nursing tasks. G. Describe how the consumer, legal guardian or designated representative will resolve all personal assistant complaints. H. Describe how the consumer, legal guardian or designated representative will train personal assistants to provide the needed services.
6. Consumer's Declaration

In 6. Consumer's Declaration, the consumer, parent, legal guardian or designated representative is willing to assume all of the required obligations in the Consumer Directed Personal Assistance Program.
The consumer, parent, legal guardian or designated representative signs under Signature, then enters Relationship to Consumer and Date.
Note: If the consumer has skilled nursing tasks, a registered nurse must complete the attached certification.
Registered Nurse's Certification
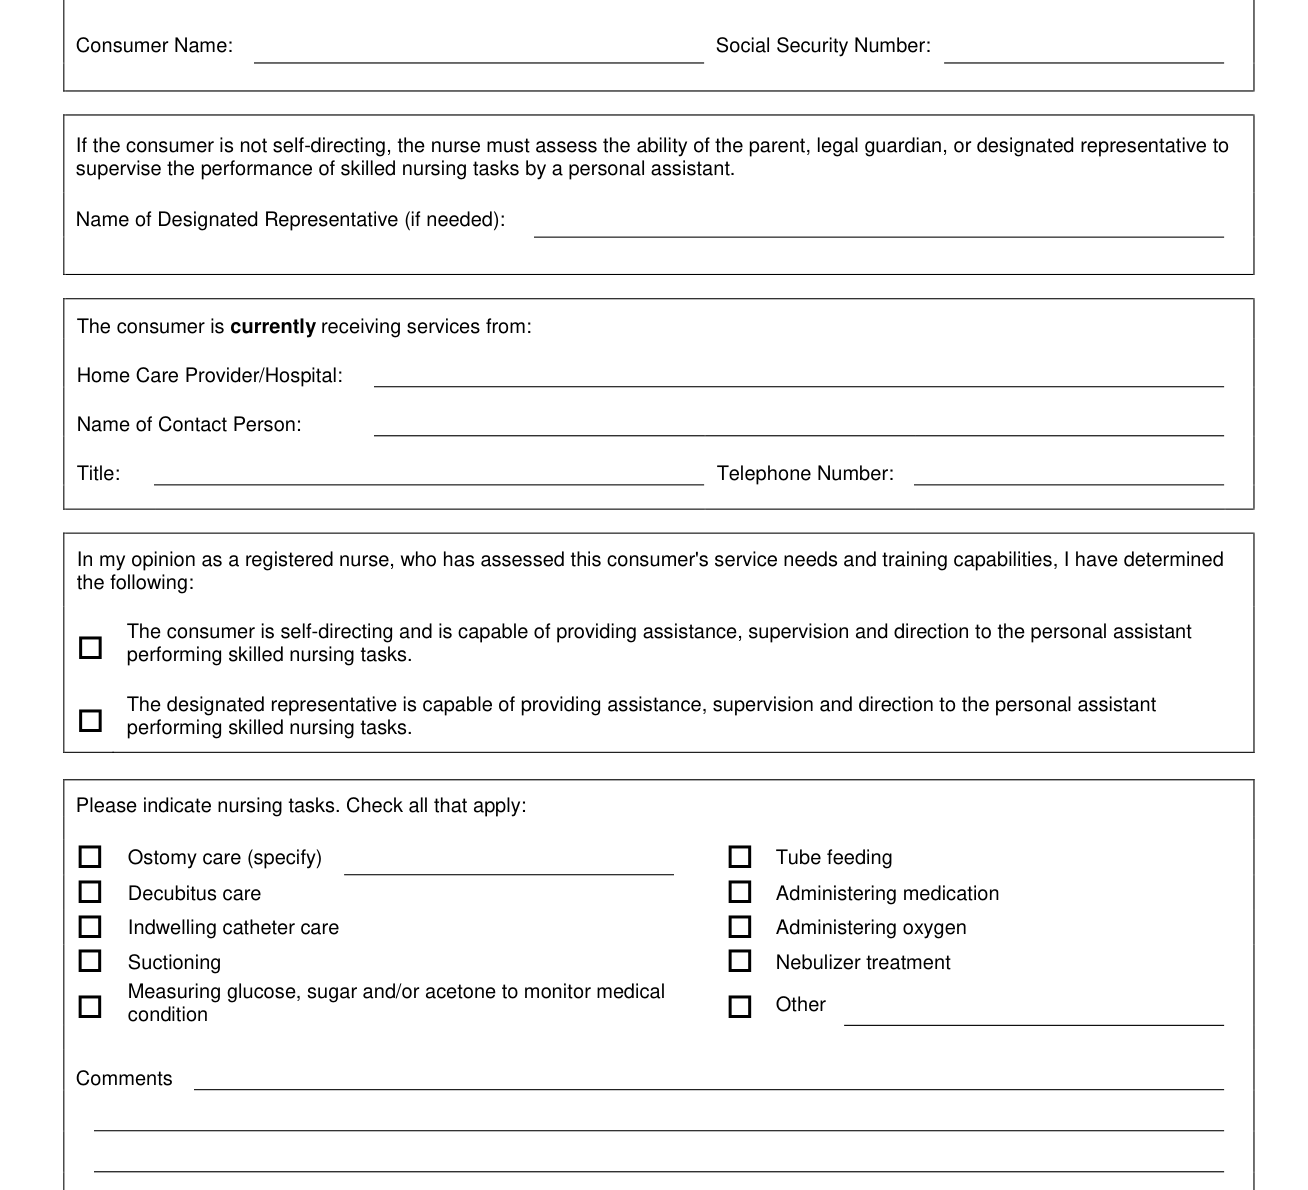
In the REGISTERED NURSE'S CERTIFICATION, enter Consumer Name and Social Security Number. If the consumer is not self-directing, the nurse must assess the ability of the parent, legal guardian, or designated representative to supervise the performance of skilled nursing tasks by a personal assistant. Enter Name of Designated Representative (if needed).
Under The consumer is currently receiving services from, enter Home Care Provider/Hospital, Name of Contact Person, Title and Telephone Number.
In my opinion as a registered nurse, who has assessed this consumer's service needs and training capabilities, I have determined the following: The consumer is self-directing and is capable of providing assistance, supervision and direction to the personal assistant performing skilled nursing tasks. The designated representative is capable of providing assistance, supervision and direction to the personal assistant performing skilled nursing tasks.
Please indicate nursing tasks. Check all that apply: Ostomy care (specify), Tube feeding, Decubitus care, Administering medication, Indwelling catheter care, Administering oxygen, Suctioning, Nebulizer treatment, Measuring glucose, sugar and/or acetone to monitor medical condition, Other. Enter Comments.
Enter the Nurse's Name, Agency, License Number and Telephone Number, and sign and date under Signature Date.
Sources
[1] Form M-13d (E) 04/09/2018, The Consumer Directed Personal Assistance Program Application, NYC Human Resources Administration (the Official source link on this page).