


Form Map 109 at a glance
What it is: Map 109 is the Plan of Care/Prior Authorization for Waiver Services of the Commonwealth of Kentucky Cabinet for Health and Family Services, Department for Medicaid Services.
Who signs: Certify that the information contained in this Plan of Care is accurate and that an informed choice was made when selecting the providers/employees to provide each service, with the Member/Guardian Signature, Case Manager/Support Broker Signature and Representative Signature (CDO), each with a Date. The Emergency Back-up Plan is CDO only.
A filled-in Form Map 109 example: a case manager completes an initial plan

How to fill out Form Map 109, box by box
Initial, 30 Day, Annual and Modification

Mark Initial, 30 Day, Annual or Modification.
Type of Waiver Program

Under Type of Waiver Program, mark SCL or HCB.
Mark MP, ABI, Traditional, CDO or Blended (CDO/Traditional).
Residential Status

Under Residential Status, mark In Home, Family Home Provider, Adult Foster Care Provider, Staffed Residence or Group Home.
Member, Guardian and Caregiver
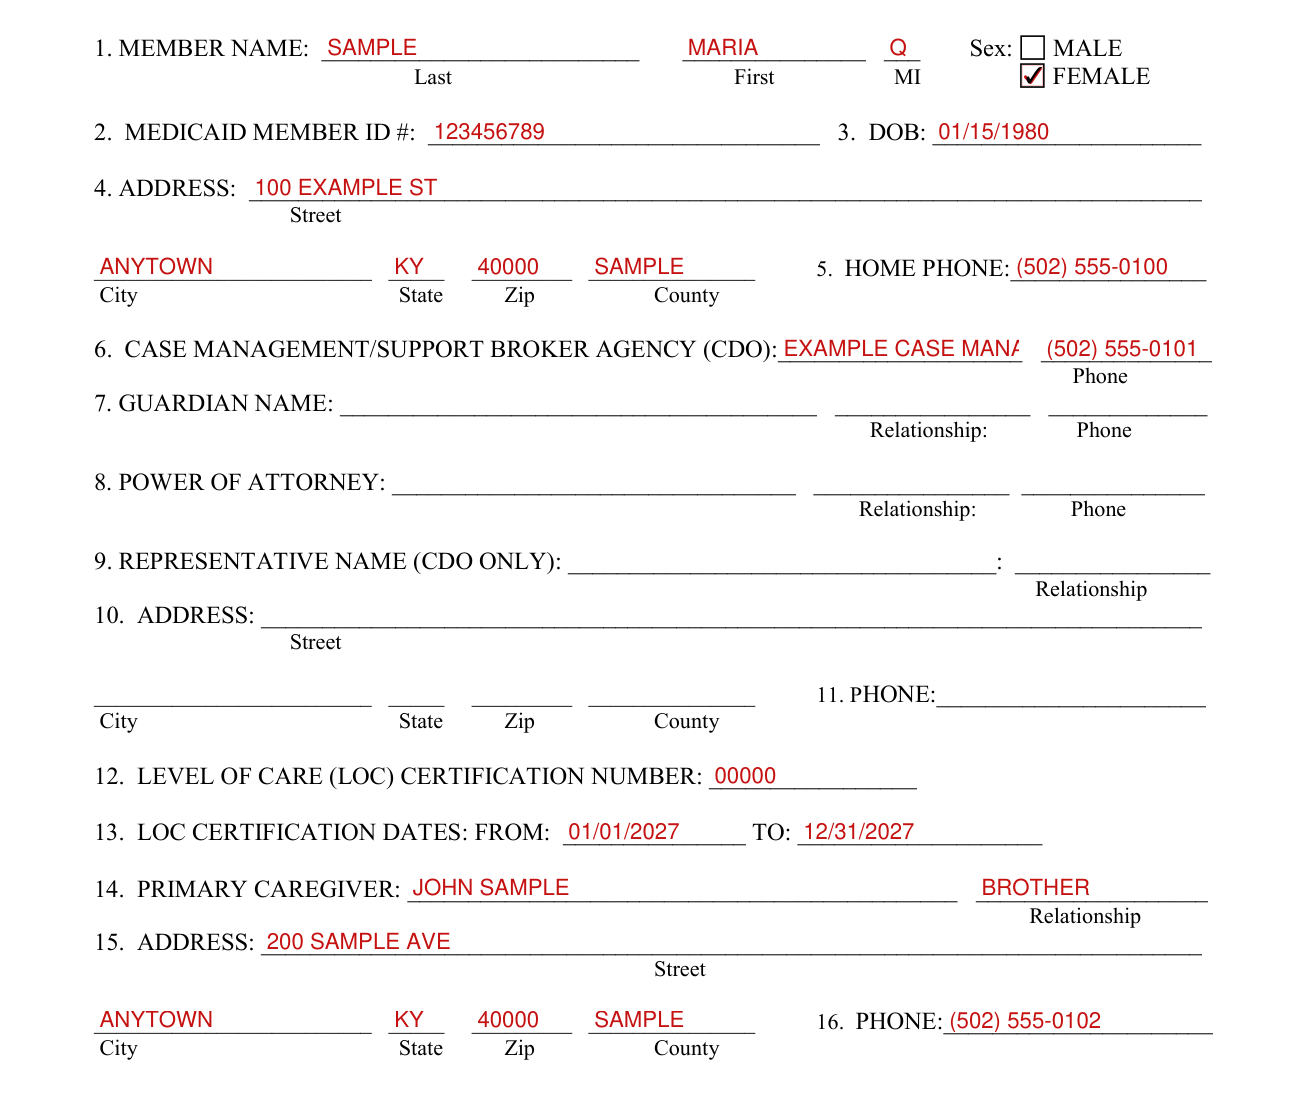
Enter the Member Name (Last, First, MI), Sex (MALE or FEMALE), Medicaid Member ID #, DOB, Address (Street, City, State, Zip, County) and Home Phone. Enter the Case Management/Support Broker Agency (CDO) and Phone. Enter the Guardian Name and the Power of Attorney, each with Relationship and Phone. Enter the Representative Name (CDO ONLY) with Relationship, Address (Street, City, State, Zip, County) and Phone. Enter the Level of Care (LOC) Certification Number and the LOC Certification Dates, FROM and TO. Enter the Primary Caregiver with Relationship, Address (Street, City, State, Zip, County) and Phone.
Identification of Needs/Outcomes/Services/Providers
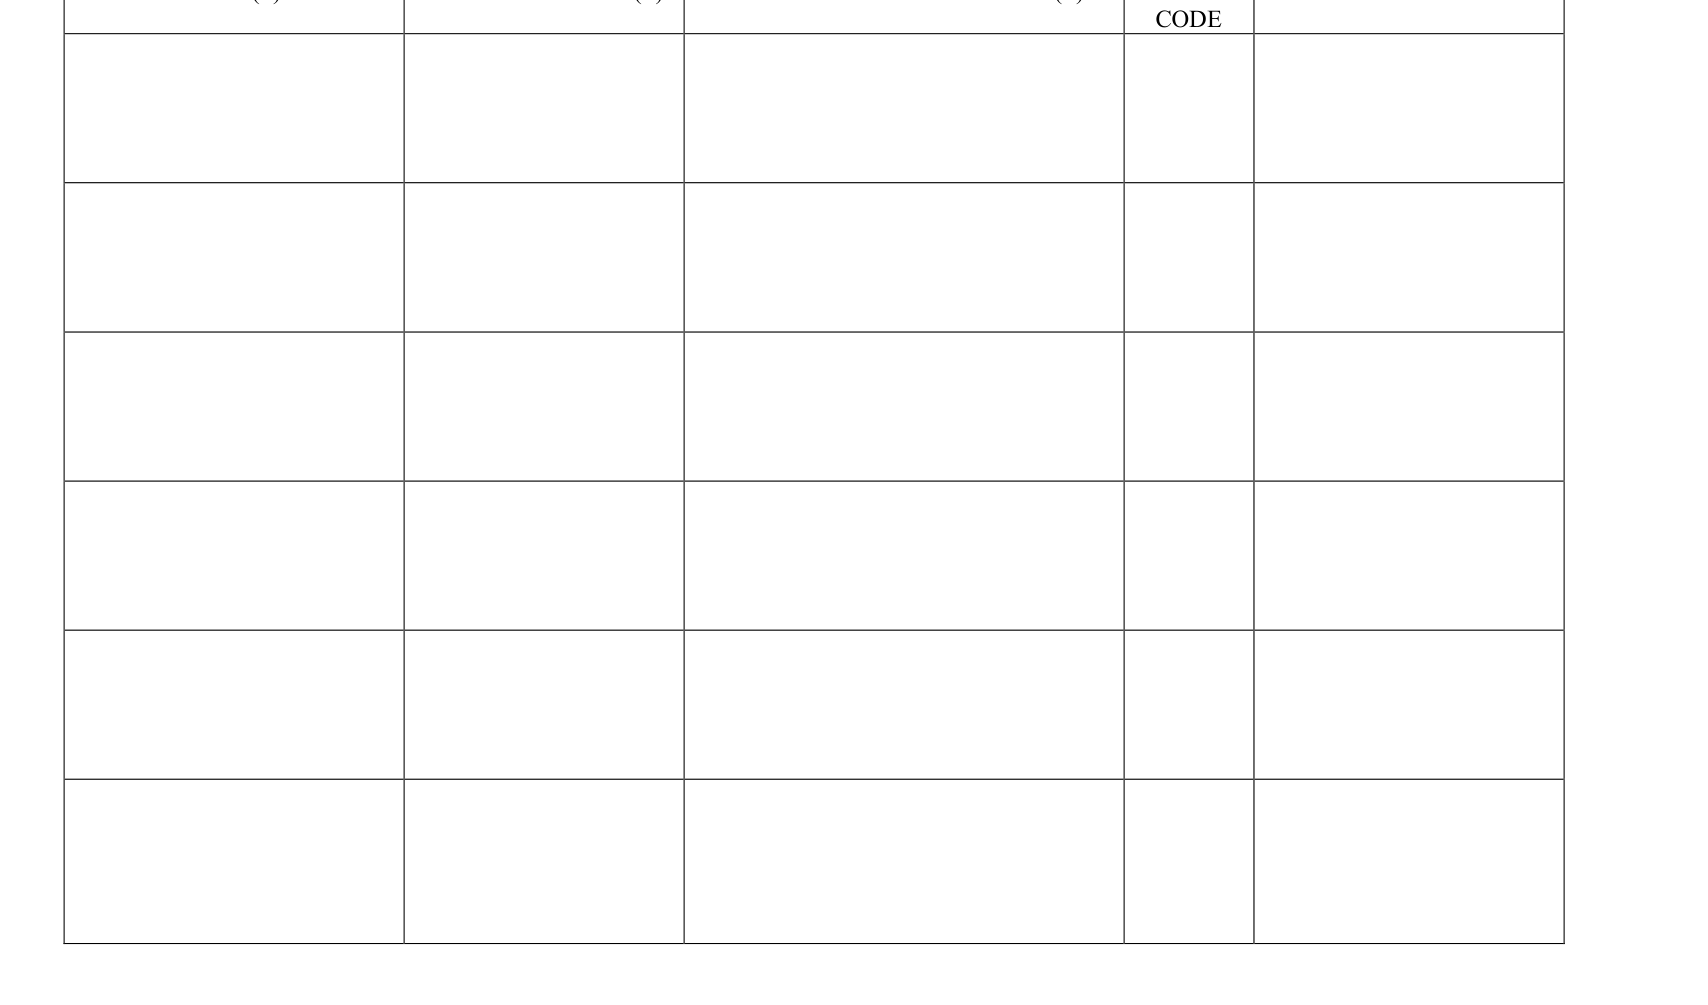
Under Identification of Needs/Outcomes/Services/Providers, enter NEED(S), OUTCOMES/GOAL(S), OBJECTIVES/INTERVENTION(S), SERVICE CODE and PROVIDER NAME/#.
Traditional Waiver Services
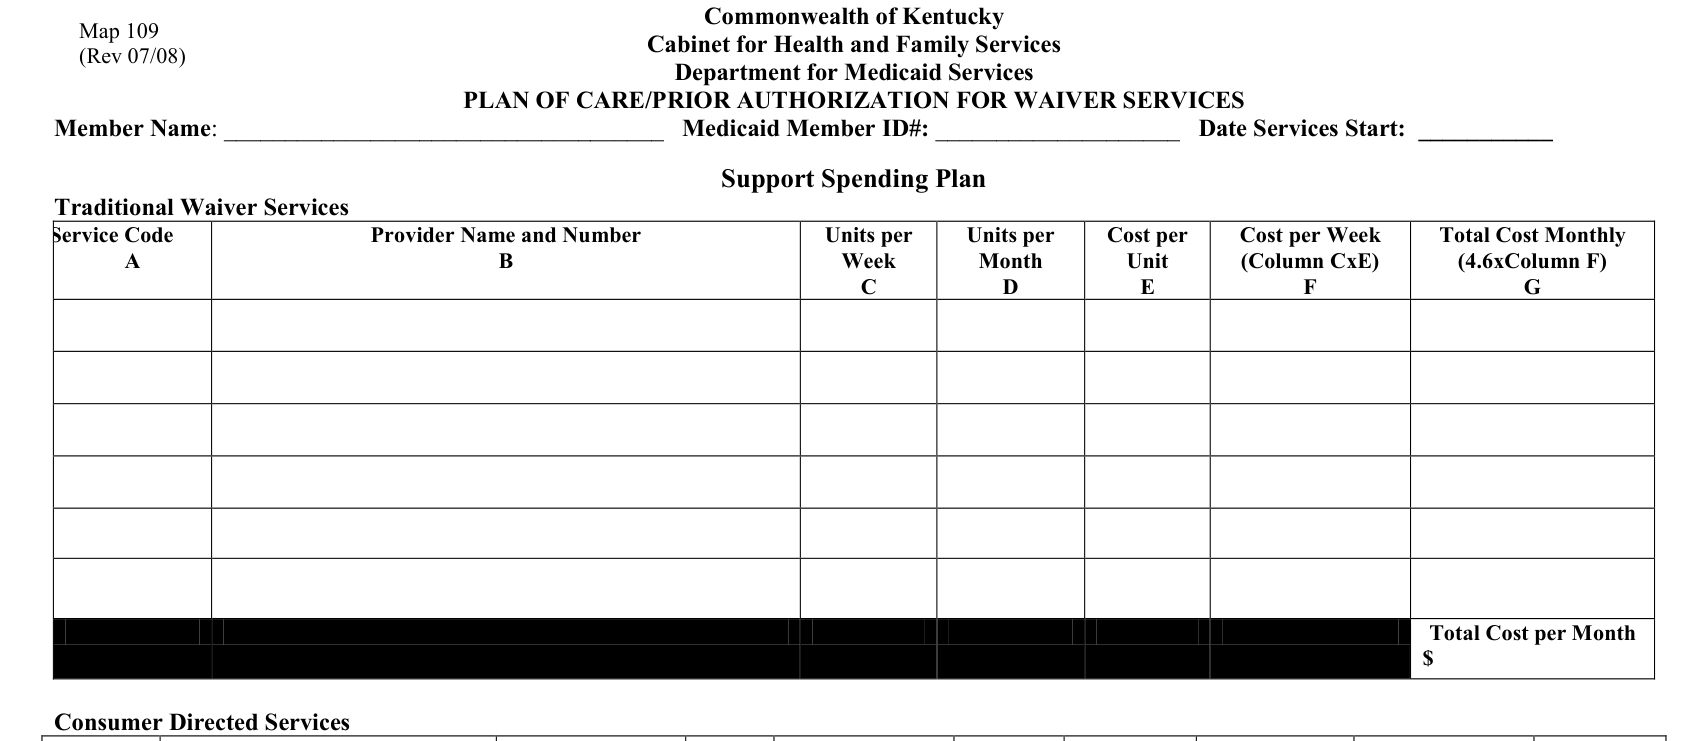
Enter the Date Services Start.
Under Traditional Waiver Services, enter the Service Code, Provider Name and Number, Units per Week, Units per Month, Cost per Unit, Cost per Week (Column CxE) and Total Cost Monthly (4.6xColumn F).
Enter the Total Cost per Month for Traditional Waiver Services.
Consumer Directed Services
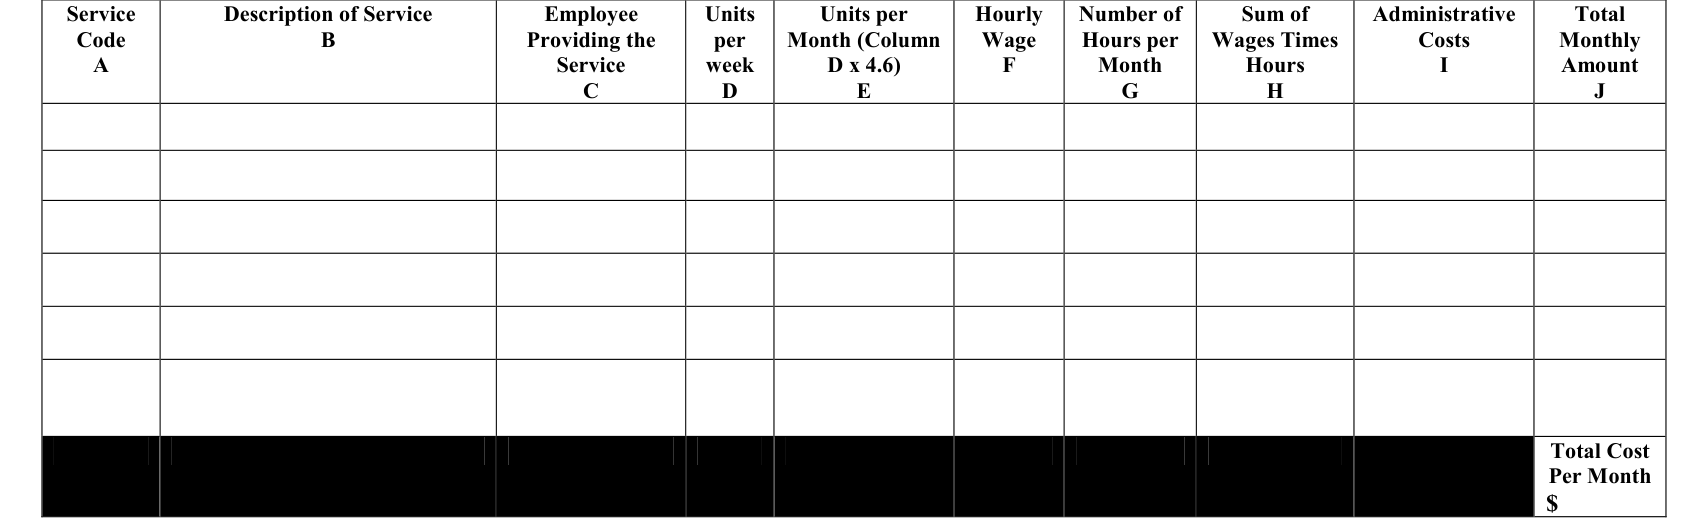
Under Consumer Directed Services, enter the Service Code, Description of Service, Employee Providing the Service, Units per week, Units per Month (Column D x 4.6), Hourly Wage, Number of Hours per Month, Sum of Wages Times Hours, Administrative Costs and Total Monthly Amount.
Enter the Total Cost Per Month for Consumer Directed Services.
Provider/Employee Name, Number, Address and Phone
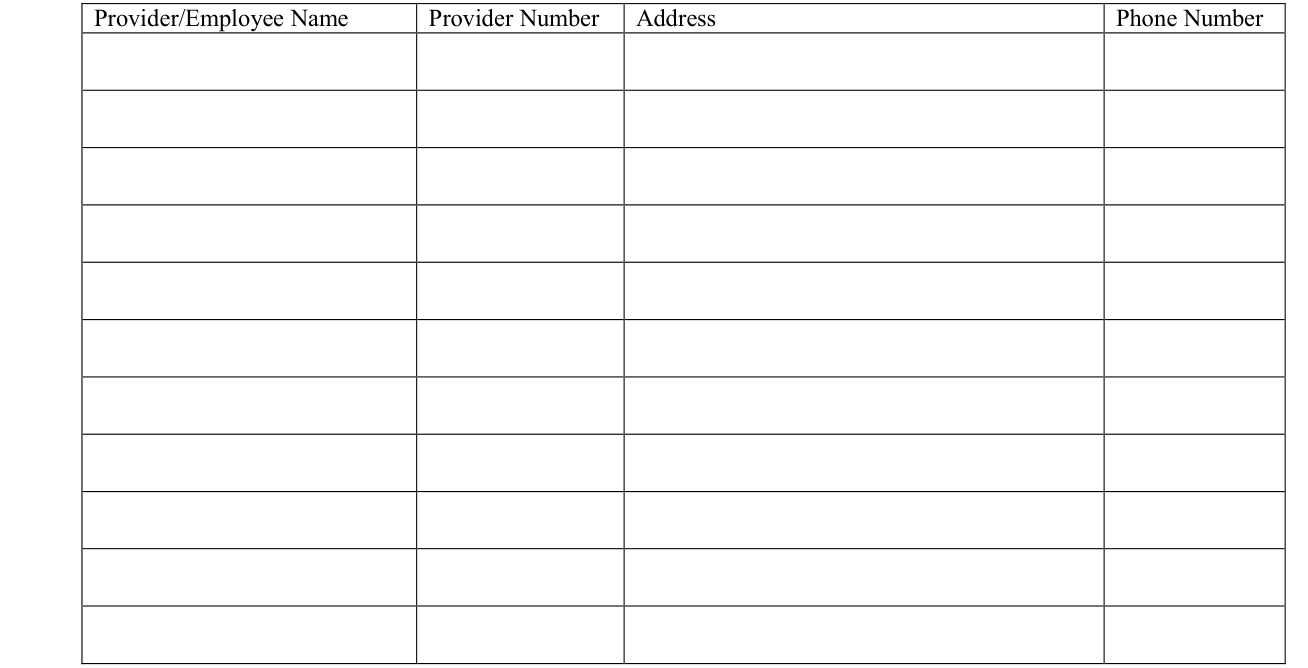
List each provider/employee name, address and telephone number: Provider/Employee Name, Provider Number, Address and Phone Number.
Clinical Summary

Write the Clinical Summary.
Signatures and Plan of Care/Support Spending Plan

Write the Emergency Back-up Plan (CDO only). Sign the Member/Guardian Signature, Case Manager/Support Broker Signature and Representative Signature (CDO), each with a Date. By signing you certify that the information contained in this Plan of Care is accurate and that an informed choice was made when selecting the providers/employees to provide each service. The QIO Signature/Title and Date go with Plan of Care/Support Spending Plan Approved or Denied.
Sources
[1] Form Map 109 (Rev 07/08), Plan of Care/Prior Authorization for Waiver Services, Kentucky Cabinet for Health and Family Services (the Official source link on this page).