


MAP 14 at a glance
What it is: MAP 14 (10/21) is the AUTHORIZED REPRESENTATIVE form of the Commonwealth of Kentucky Cabinet for Health and Family Services, Department for Medicaid Services.
Who signs: For the applicant, enter the Printed Applicant/Member Name, Applicant/Member Signature, Applicant/Member Address, City, State, Zip, Phone Number and Date Signed.
A filled-in MAP 14 example: a daughter as authorized representative

How to fill out MAP 14, box by box
Permission

Check all that apply: Apply, Report Changes; Apply, Report Changes, Recertify; or Apply, Report Changes, Recertify and receive a copy of Notices.
Names

Print Your Name and the Authorized Representative's Name after I have asked. The authorization is to help me as I have chosen in the check all that apply boxes with Medicaid. This authorization is valid from the date of applicant's signature until the form is rescinded by the applicant.
The applicant

For the applicant, enter the Printed Applicant/Member Name, Applicant/Member Signature, Applicant/Member Address, City, State, Zip, Phone Number and Date Signed.
Witness, if signed by X

Witness (if signed by X).
The authorized representative
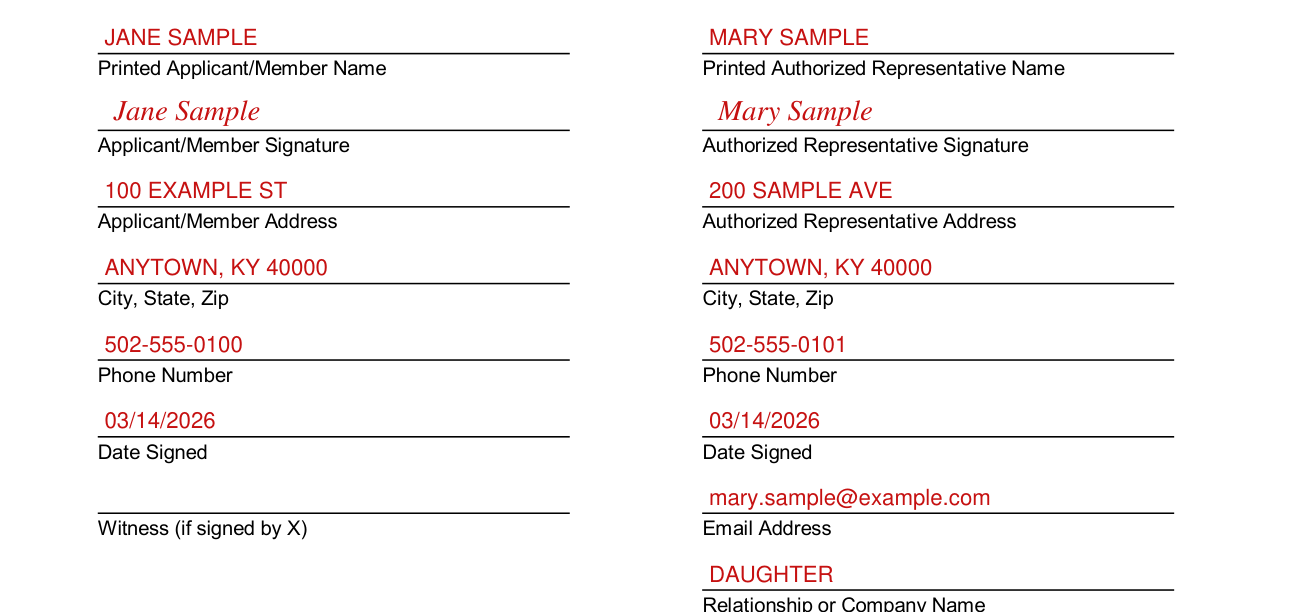
For the authorized representative, enter the Printed Authorized Representative Name, Authorized Representative Signature, Authorized Representative Address, City, State, Zip, Phone Number, Date Signed, Email Address and Relationship or Company Name.
More rules for MAP 14
If I or my authorized representative knowingly provides false information or withholds information, I may be subject to prosecution for fraud. Eligibility determinations may take up to 30 days from the date of application to be completed. All identification cards and letters will be mailed to the address you choose. You will need to show your identification card to your medical providers so they can bill Medicaid for the services you received.
Common questions about MAP 14
What am I certifying when I sign?
The applicant or authorized representative must provide complete and truthful information to have Medicaid eligibility determined or redetermined. The authorized representative is responsible for fulfilling all responsibilities designated in the check all that apply boxes as well as agreeing to maintain the confidentiality of any information regarding the applicant or member provided by the agency.
Sources
[1] MAP 14 (10/21), Authorized Representative, Commonwealth of Kentucky Cabinet for Health and Family Services, Department for Medicaid Services (the Official source link on this page).