

Form IM-1SSL at a glance
What it is: Missouri Department of Social Services Family Support Division Application for Health Coverage & Help Paying Costs. Use this application to see what coverage choices you qualify for
Who signs: Signature of applicant. The person who filled out step 1 should sign this application.
Use this application to apply for anyone in your family. Apply even if you or your child(ren) already have health coverage. You could be eligible for lower-cost or free coverage. Families that include immigrants can apply. You can apply for your child even if you are not eligible for coverage. Applying will not affect your immigration status or chances of becoming a permanent resident or citizen. If someone is helping you fill out this application, you may need to complete Appendix C. If you are applying for your unmarried domestic partner, both of you will need to complete Appendix C.
What to bring and attach to Form IM-1SSL
Social Security Numbers (or document numbers for any legal immigrants who need insurance). Employer and income information for everyone in your family (for example, from paystubs, W-2 forms, or wage and tax statements). Policy numbers for any current health insurance. Information about any job-related health insurance available to your family.
A filled-in Form IM-1SSL example: an adult starts a family health coverage application

How to fill out Form IM-1SSL, box by box
Did you obtain this application from a

Did you obtain this application from a: Missouri Public School, Licensed Child Care Provider, Other
Legal Name and Home address

1. Legal Name (First Name, Middle name, Last Name, & Suffix) 2. Home address (Write HOMELESS if you are currently without a home address) Apartment or suite number City State ZIP code County
Mailing address and Safe at Home

3. Check here if your mailing address is different than your home address.
4. Check here if the mailing address provided is a Safe at Home address. Safe at Home authorization code
5. Mailing Address 6. Apartment or suite number 7. City 8. State 9. ZIP Code 10. County of residence
Phone numbers, Email address and preferred contact
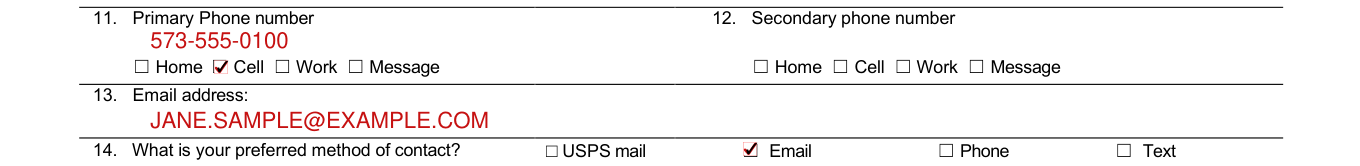
11. Primary Phone number 12. Secondary phone number 13. Email address: 14. What is your preferred method of contact? USPS mail, Email, Phone, Text
Preferred language and how well you speak English

15. What is your preferred language (if not English)? 16. How well do you speak English? Very Well, Well, Not Well, No Spoken Proficiency, Prefer not to answer
Use my tax returns to renew my eligibility automatically

I agree to allow the Family Support Division to use income data, including information from tax returns. The Family Support Division will send me a notice, let me make any changes, and I can opt out at any time. Yes, use my tax returns to renew my eligibility automatically for the next: 5 years (the maximum number of years allowed), 4 years, 3 years, 2 years, 1 year. Do not use information from tax returns to renew my coverage.
If your situation is different
You may also need to fill out the Aged, Blind, and Disabled Supplement (IM-1ABDS)
Use this application for all MO HealthNet programs. You may also need to fill out the Aged, Blind, and Disabled Supplement (IM-1ABDS) if you are over 65, blind, disabled, or living in a nursing home or long-term care facility.
Complete Step 2 for each person in your family
Complete Step 2 for each person in your family. Start with yourself! Then add other adults and children.
For adults who need coverage: Include these people even if they aren't applying for health coverage for themselves: Any spouse they live with. Any child under age 21 they live with, including stepchildren. Any other person on the same federal income tax return (including any children over age 21 who are claimed on a parent's tax return).
For children under age 21 who need coverage: Include these people even if they aren't applying for health coverage themselves: Any parent (or stepparent) they live with. Any sibling they live with. Any child they live with, including stepchildren. Any spouse they live with. Any other person on the same federal income tax return.
Please complete pages 5 and 6 for additional household members, make copies if necessary.
American Indian or Alaska Native, or medical bills for the 3 months prior to this application
8. Check here if you are an American Indian or Alaska Native and fill out Appendix D.
9. Check here if you want help paying for medical bills for the 3 months prior to this application and fill out Appendix A. APPENDIX A For faster service: Complete this form ONLY for persons who are requesting health coverage for the 3 months prior to this application.
Federal income tax return and health coverage from this month forward
Do you plan to file a federal income tax return NEXT YEAR? (You can still apply for health insurance even if you do not file a federal income tax return.) Yes. If yes, answer questions a-c. No. If no, skip to question c.
Are you requesting health coverage from this month forward? YES. If yes, answer all the questions. NO. If no, SKIP to the next page.
Employed, self-employed or not employed
Employed - If you are currently employed, start with question 23. Self-employed - Skip to question 33. Not employed - Skip to question 34.
Yearly income: Complete only if income changes from month to month. If you do not expect changes to monthly income, skip to the next person.
Anyone listed on this application is offered health coverage from a job
Is anyone listed on this application offered health coverage from a job? Check yes even if the coverage is from someone else's job, such as a parent or spouse. Yes, you will also need to complete Appendix B. No, continue to Step 4.
You would like to name someone to act on your behalf
Use this form if you would like to name someone to help you apply for MO HealthNet coverage and/or act on your behalf if you get coverage. Return the completed form to FSD within 90 days of the date(s) you and your authorized representative sign and date the form.
Common questions about Form IM-1SSL
Who signs it?
Signature of applicant. The person who filled out step 1 should sign this application. If you are an authorized representative, you may sign here, as long as you have provided the information required in Appendix C.
Where do I file it?
STEP 6: Send your completed application. Upload your document: Visit mydssupload.mo.gov to upload a copy of your document. Mail to: Family Support Division PO BOX 2700 Jefferson City, MO 65102 Fax to: (573) 526-9400
Is there a penalty?
I know that I may be subject to penalties under federal law if I provide false or untrue information.
What am I certifying when I sign?
I am signing this application under penalty of perjury which means I have provided true answers to all the questions on this form to the best of my knowledge.
Sources
[1] Form IM-1SSL (9/2026), Application for Health Coverage & Help Paying Costs, Missouri Department of Social Services Family Support Division (the Official source link on this page).
