

Form 2575-034 at a glance
What it is: Form 2575-034 is the PRIOR AUTHORIZATION REQUEST.
Who signs: Box 31: Provider signature and date; check Provider Manual to determine if this field is required. Section 5 - Prescribing/Performing Practitioner: This section must be completed for services which require a prescription such as durable medical equipment, physical therapy, services prescribed by a physician/practitioner that require PA, or when the provider in Section IV is a clinic or group practice.
A filled-in Form 2575-034 example: a doctor's office requests prior authorization
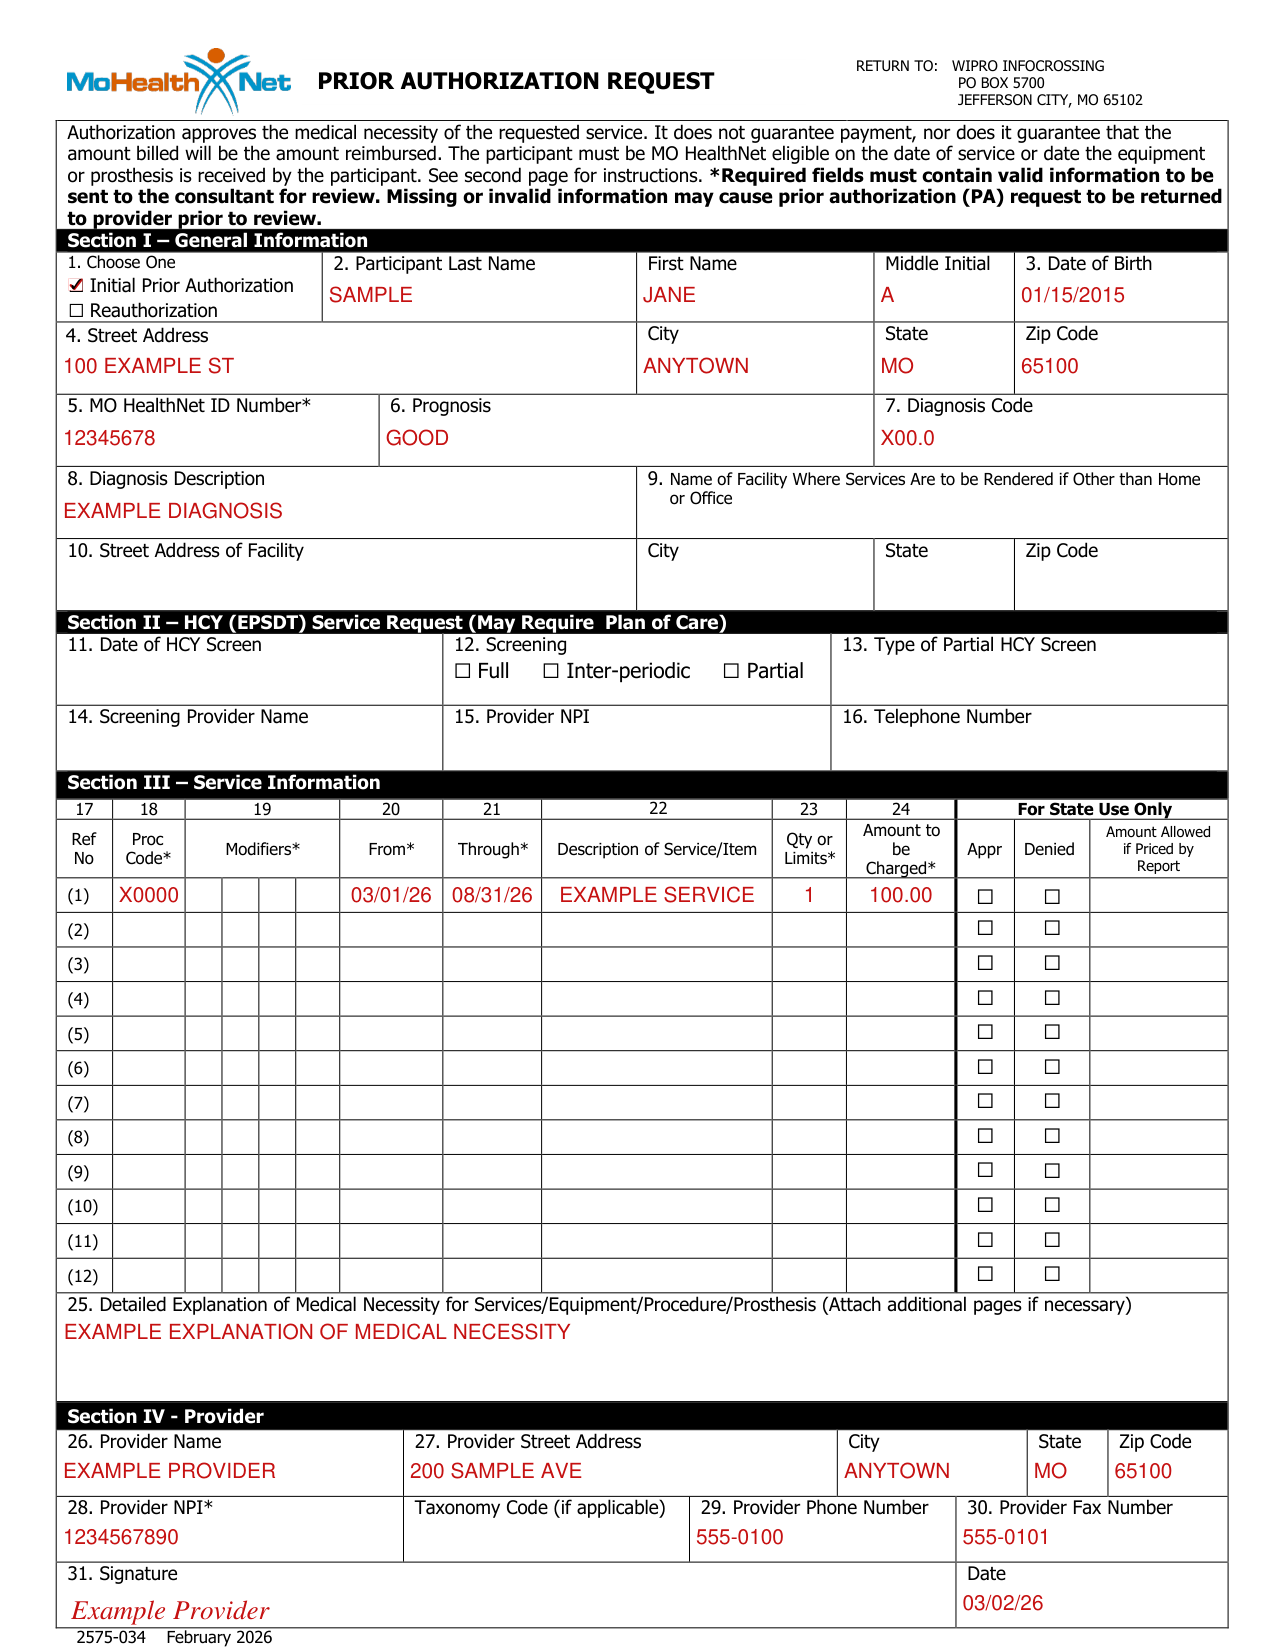
How to fill out Form 2575-034, box by box
Type of authorization for services requested

Type of authorization for services requested (box 1). Authorization approves the medical necessity of the requested service. It does not guarantee payment, nor does it guarantee that the amount billed will be the amount reimbursed. The participant must be MO HealthNet eligible on the date of service or date the equipment or prosthesis is received by the participant. See second page for instructions. *Required fields must contain valid information to be sent to the consultant for review. Missing or invalid information may cause prior authorization (PA) request to be returned to provider prior to review. Section 1 - General Information 1. Choose One: Initial Prior Authorization or Reauthorization.
Participant: name, date of birth, address and MO HealthNet ID Number
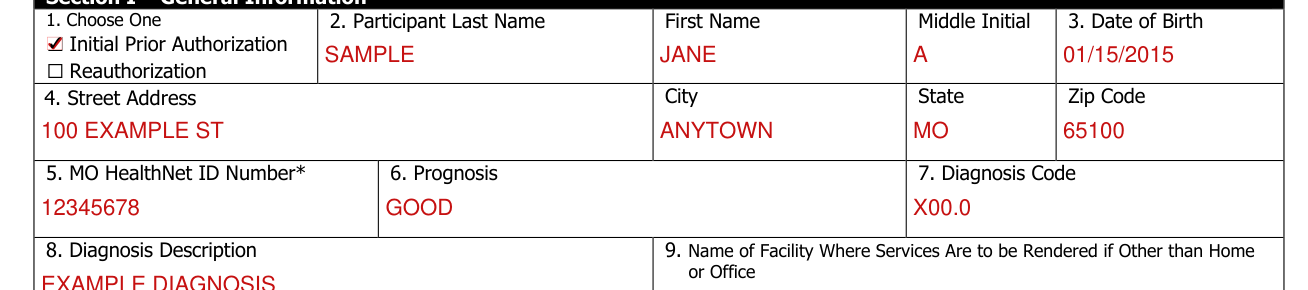
Enter the Participant Last Name, First Name and Middle Initial as it appears on MO HealthNet ID Card, and the Date of Birth.
Enter the participant Street Address, City, State and Zip Code.
Box 5*: Must include valid 8-digit MO HealthNet ID Number. Fields marked * are Required fields: missing or invalid information will cause prior authorization (PA) request to be returned prior to review.
Prognosis, diagnosis code and diagnosis description
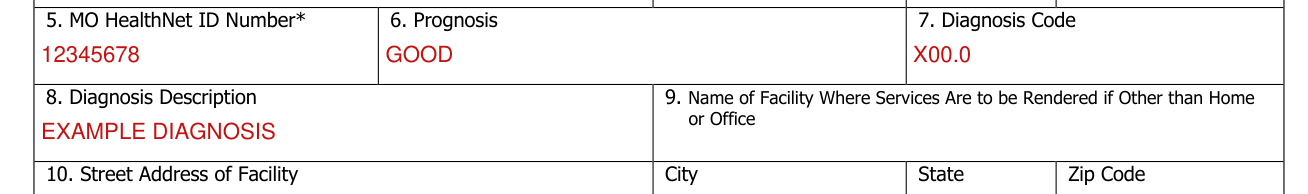
Enter the participant prognosis.
Enter the Diagnosis Code(s).
Enter the Diagnosis Description: all diagnosis appropriate to services being requested.
Name of Facility Where Services Are to be Rendered if Other than Home or Office
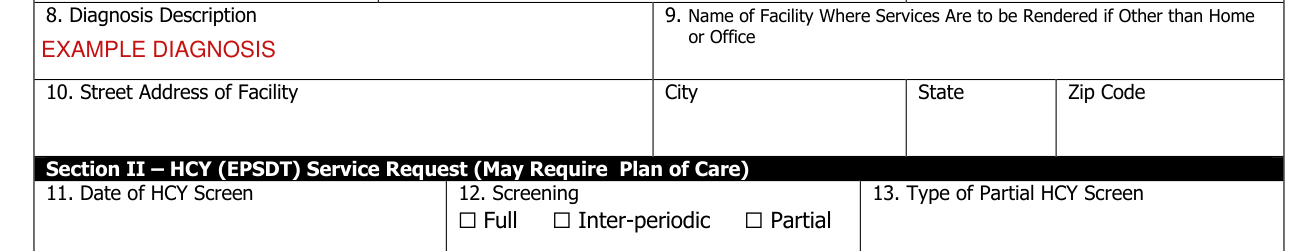
If service is to be provided other than home or office, enter the name of facility where services are to be rendered.
If service is to be provided other than home or office, enter the Street Address of Facility, City, State and Zip Code where services are to be rendered.
Section 2: HCY (EPSDT) Service Request
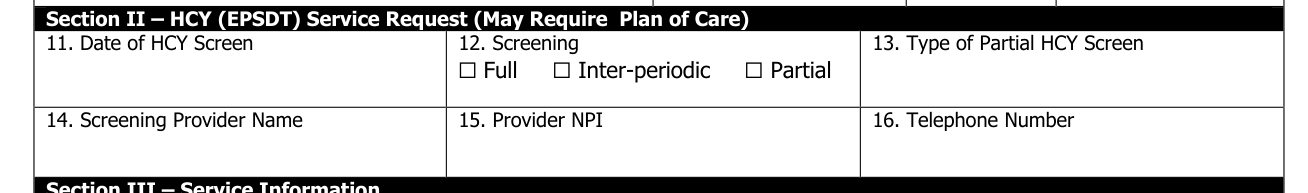
Section 2 - Healthy Children and Youth (HCY) Service Request: Plan of Care may be required, see Provider Manual.
Enter the date HCY Screen was done.
Check Full, Inter-Periodic or Partial Screen.
Enter the type of partial HCY Screen performed (e.g., Vision, Hearing).
Enter the provider's name who performed screening.
Enter the provider's NPI who performed screening.
Enter the provider's telephone number.
Section 3: Service Information

Ref No 17 identifies each separate line on the request.
Proc Code (box 18)*: must include valid procedure code(s) for services being requested (when applicable).
Modifiers (box 19)*: must include valid modifier(s) for services being requested (when applicable).
From (box 20)*: must include From date services will begin if authorization approved (mm/dd/yy).
Through (box 21)*: must include Through date services will terminate is approved (mm/dd/yy).
Description of Service/Item (box 22): specific description of service/item being requested.
Qty or Limits (box 23)*: must include quantity or units of service/item being requested with procedure codes with set reimbursement.
Amount to be Charged (box 24)*: amount to be charged for the service must be present with procedure codes that are manually priced.
25: Detailed Explanation of Medical Necessity

In box 25, enter the Detailed Explanation of Medical Necessity for Services/Equipment/Procedure/Prosthesis: the detailed explanation of medical necessity of the service/equipment/procedure/prosthesis, etc. Attach additional pages if necessary.
Do not use another PA form.
Section 4: Provider
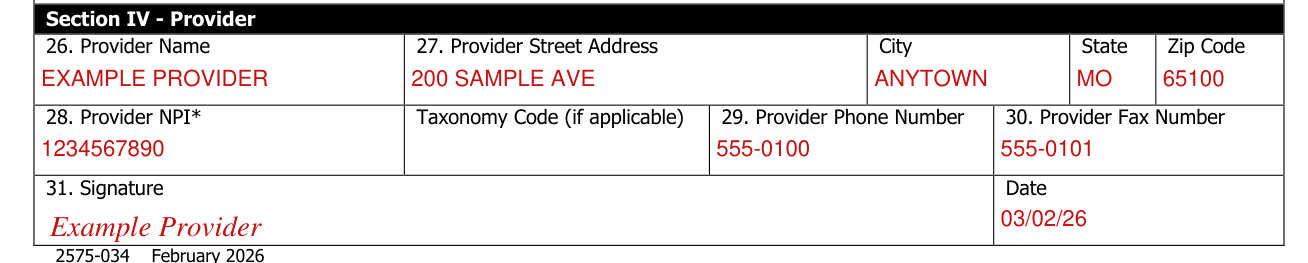
Enter the Providers Name making the request; if clinic/group, also complete section V.
Enter the complete mailing address: Provider Street Address, City, State and Zip Code.
Provider NPI (box 28)*: must include providers NPI, and taxonomy code (if applicable).
Enter the Provider Phone Number.
Enter the Provider Fax Number.
Section 5: Prescribing/Performing Practitioner
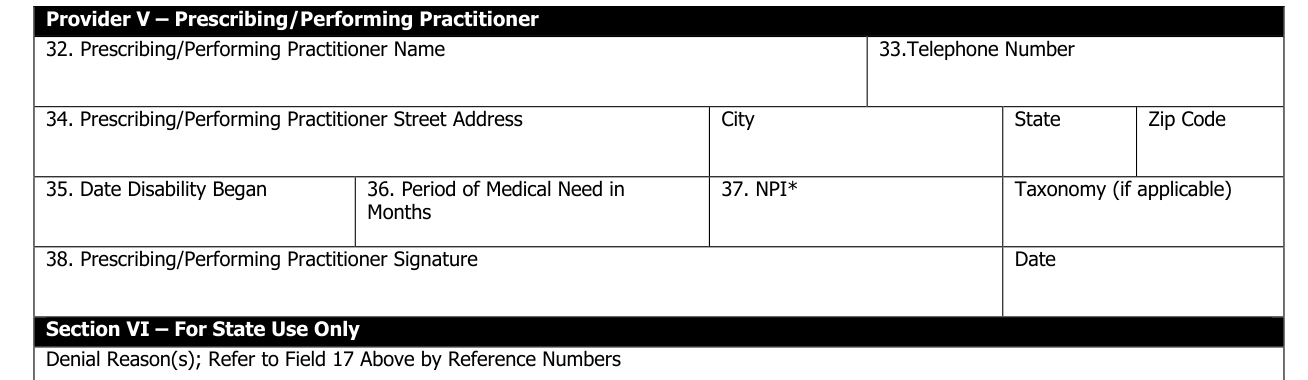
Enter the name of prescribing/performing practitioner.
Enter the prescribing/performing practitioner telephone number.
Enter the prescribing/performing practitioner address: Street Address, City, State and Zip Code.
Date disability began: for example, if it originated at birth, enter date of birth.
Enter the estimated number of months for the need as the Period of Medical Need in Months.
NPI (box 37)*: must include provider's NPI, and taxonomy code (if applicable).
Sign the prescribing/performing practitioner signature line; signature stamps are not acceptable.
More rules for Form 2575-034
Section 6 - For State Use Only: Section 3 will indicate approval or denial for each line and the consultant will indicate allowed amount if procedure requires manual pricing.
Review Provider Manual for additional instructions.
Common questions about Form 2575-034
Where do I file it?
Return the PRIOR AUTHORIZATION REQUEST to WIPRO INFOCROSSING, PO BOX 5700, JEFFERSON CITY, MO 65102.
Sources
[1] Form 2575-034 (February 2026), Prior Authorization Request, Missouri Department of Social Services (the Official source link on this page).
