


Form MV-80U.1 at a glance
What it is: Form MV-80U.1, the Physician's Statement for Medical Review Unit, is to report medical, physical, mental or a combination of such conditions to the Medical Review Unit.
Who signs: Complete the information and have your physician/physician assistant/nurse practitioner complete the statement on page 2.
A filled-in Form MV-80U.1 example: a driver reports a condition on page 1

How to fill out Form MV-80U.1, box by box
Your name, date of birth and sex

Print or type your Last Name, First Name, M.I. and Date of Birth (Month/Day/Year).
Under Sex, mark M, F or X.
Your address, Client ID and telephone

Enter your Mailing Address (Number and Street), City, State and Zip Code.
Enter your Client ID No. (Driver License No.), any other names that you have used (if applicable) and your Daytime Telephone Number (Area Code).
Your conditions and who treats you
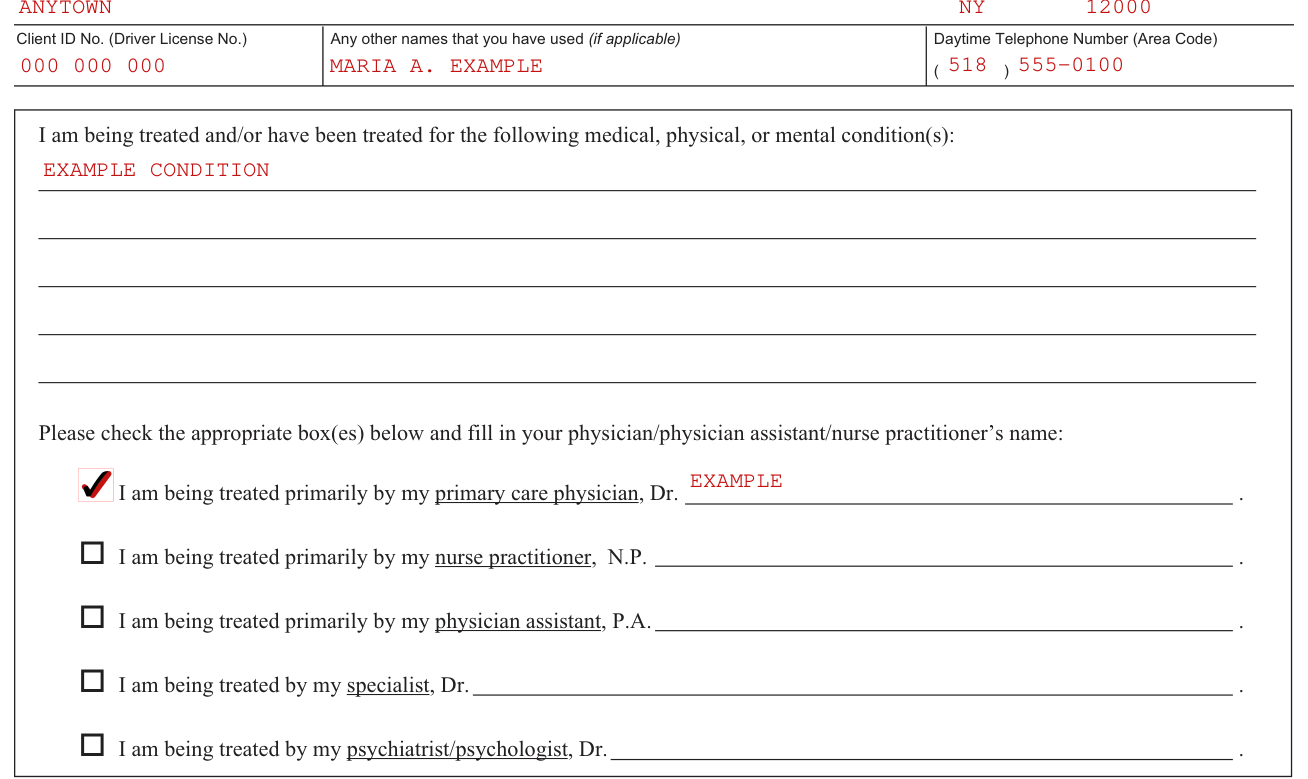
Write the condition(s) under I am being treated and/or have been treated for the following medical, physical, or mental condition(s).
Check the appropriate box(es) and fill in your physician/physician assistant/nurse practitioner's name: I am being treated primarily by my primary care physician, Dr.; I am being treated primarily by my nurse practitioner, N.P.; I am being treated primarily by my physician assistant, P.A.; I am being treated by my specialist, Dr.; or I am being treated by my psychiatrist/psychologist, Dr.
Returning the form and the 120 days
The information provided must be based on a current examination performed by your physician/physician assistant/nurse practitioner within the last 120 days from the date this statement is submitted.
Have your physician/physician assistant/nurse practitioner complete page 2, and then return this form to: Medical Review Unit, Driver Improvement Bureau, NYS Department of Motor Vehicles, 6 Empire State Plaza, Albany, NY 12228.
Page 2: examination date and condition
Physician/Physician Assistant/Nurse Practitioner: Please attach a sample of your letterhead or a voided prescription blank.
Examination Date (must be within 120 days from the date this form is submitted). Condition patient is being treated for: Epilepsy/convulsive disorder, Dementia/senility/Alzheimer's, Stroke, Other (please specify), Syncope/fainting/dizziness or a condition that causes unconsciousness, Diabetes, Head trauma/tumor, Mental disorder, Sleep disorder, Heart condition, or Neurological or neuromuscular disease.
Page 2: episodes and accidents
Enter the Symptoms, severity, and frequency of condition, and the Date of the last episode/incident associated with this condition.
Have any episode(s)/incident(s) associated with this condition caused any loss of consciousness, awareness, and/or body control? YES or NO. If YES, list the dates of the episode(s)/incident(s).
Give a brief description regarding any factors that may have caused/contributed to the episode(s)/incident(s).
To the best of your knowledge have any of the patient's episode(s)/incident(s) resulted in a motor vehicle accident(s) and/or incident(s)? YES or NO. If YES, please give details and the dates of the episode(s)/incident(s) and related accident(s).
Page 2: tests, treatment and sleep disorder
List the Tests conducted (e.g., EEG, EKG, MRI, sleep study, serum levels, etc.) and the Current treatment, medication and dosage, and /or therapy.
MUST be answered if the patient has a sleep disorder: (a) Date first diagnosed with the sleep disorder; (b) Is patient receiving treatment? Type of treatment and Date treatment began; (c) Is patient compliant with the treatment?
Page 2: the physician's opinion and signature
In my medical opinion, at this time (please check one). The patient's condition may affect the safe operation of a motor vehicle, and the patient should be evaluated by the Department of Motor Vehicles. The patient's condition prevents the safe operation of a motor vehicle and driving privileges should be suspended. The patient's condition will not interfere with the safe operation of a motor vehicle.
Please provide further detail in the space provided or in an attached statement on your letterhead.
Enter the Physician/Physician Assistant/Nurse Practitioner's Name (Please print in full), Certificate or license number and state where licensed, Mailing Address (include number and street), Telephone Number (area code), City, State and Zip Code.
Primary care physician, Neurologist, Psychiatrist/Psychologist, Physician/Physician Assistant/Nurse Practitioner, Endocrinologist, or Other. Physician/Physician Assistant/Nurse Practitioner's Signature and Date (Month/Day/Year).
More rules for Form MV-80U.1
Information provided by emergency care personnel is NOT acceptable. After review of the completed statement you may be requested to provide additional information from either the physician/physician assistant/nurse practitioner who provided the information or from a qualified specialist.
Sources
[1] Form MV-80U.1 (4/25), Physician's Statement for Medical Review Unit, New York State Department of Motor Vehicles (the Official source link on this page).