

Form NF-6 at a glance
What it is: Employer's Wage Verification Report under the New York Motor Vehicle No-Fault Insurance Law.
Who signs: Enter PRINT NAME, TITLE, PHONE NO., SIGNATURE, FEDERAL EMPLOYER I.D. NO. and DATE.
A filled-in Form NF-6 example: an employer verifies a cashier's wages

How to fill out Form NF-6, box by box
Boxes 1 and 2, occupation and dates of employment

In Box 1, enter the employee's occupation.
In Box 2, enter the dates of employment: FROM and THROUGH.
Box 3, earnings and hours
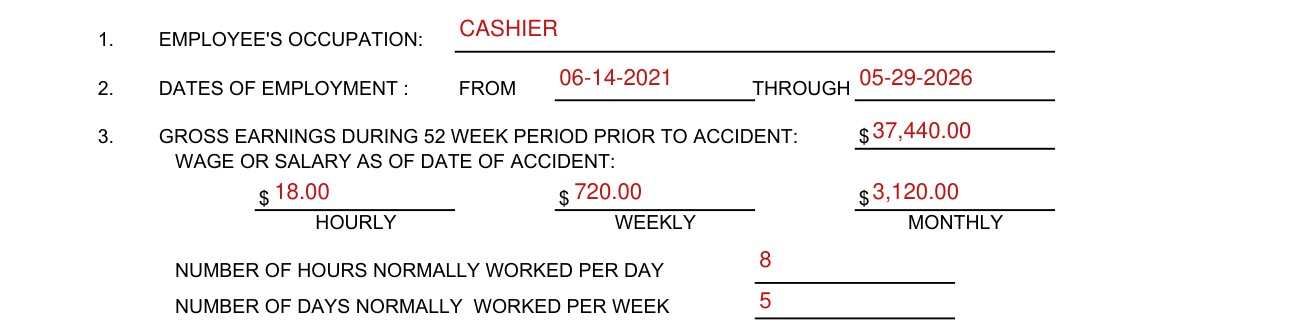
In Box 3, enter the gross earnings during the 52 week period prior to accident, and the wage or salary as of date of accident: hourly, weekly or monthly.
Enter the number of hours normally worked per day.
Enter the number of days normally worked per week.
Box 4, dates absent

In Box 4, enter the first day absent from work and the date returned to work.
Box 5, workers' compensation benefits

In Box 5, enter YES, NO or UNDETERMINED: has the employee received, is the employee receiving or is the employee entitled to receive benefits under any workers' compensation law as a result of this accident?
Enter the WORKER'S COMPENSATION INSURER, ADDRESS and POLICY NUMBER.
Box 6, state disability benefits

In Box 6, enter YES, NO or UNDETERMINED: has the employee received, is the employee receiving or is the employee entitled to receive New York State disability benefits as a result of this accident?
Enter YES or NO: is the employee required to pay for DBL coverage through payroll deduction?
Enter the NYS DISABILITY INSURER, ADDRESS and POLICY NUMBER.
Boxes 7 to 11, payment by the employer

In Box 7, enter YES or NO: was or will the employee be paid by the employer for this absence from work?
If the answer to Question 7 is "YES", answer Questions 8, 9, 10 and 11.
In Box 8, enter how much was or will the employee be paid, weekly or monthly.
In Box 9, enter YES or NO: will the employee be required to reimburse you any of the above amount?
In Box 10, enter YES or NO: will the employee lose accumulated leave credits as a result of the foregoing payment?
In Box 11, enter YES or NO: will the employee's eligibility for future wage benefits be affected by payments indicated in Question 8 above?
Print name, title, phone, signature, employer I.D. and date
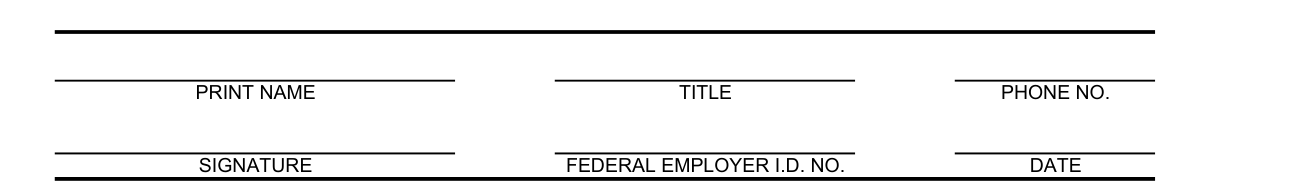
Enter PRINT NAME, TITLE, PHONE NO., SIGNATURE, FEDERAL EMPLOYER I.D. NO. and DATE.
More rules for Form NF-6
Provide the answers to the questions on the form to assist in determining the benefits that may be due the applicant, who has applied for benefits under the New York Comprehensive Motor Vehicle Insurance Reparations Act (No-Fault Law) as a result of injuries sustained in a motor vehicle accident.
When the form is complete
The form is complete
Complete and submit this form to the claims representative as soon as possible; the completed form must be submitted to the insurer no later than 90 days after work loss was first incurred.
Common questions about Form NF-6
Is there a penalty?
Any person who knowingly and with intent to defraud any insurance company or other person files a statement of claim containing any materially false information commits a fraudulent insurance act, which is a crime, and shall also be subject to a civil penalty not to exceed five thousand dollars and the value of the subject motor vehicle or stated claim for each violation. (checked November 11, 2026)
Sources
[1] NYS Form NF-6 (Rev 1/2004), Employer's Wage Verification Report, New York State Department of Financial Services (the Official source link on this page).
