Ga Form Wc 6 PDF Details

The Ga WC 6 form serves a critical role within the Georgia State Board of Workers' Compensation framework, providing a structured means for calculating an injured employee's average weekly wage. This document facilitates a fair assessment of benefits by requiring detailed wage information from both the employer and a comparable role within the same employment, should the employee not have a sufficient employment history. Key sections include identifying information for the employee, employer, and insurer or self-insurer, in addition to a comprehensive schedule for recording thirteen weeks of gross earnings leading up to the incident. This form not only assists in determining the financial compensation due to the employee but also underscores the state's commitment to protecting workers' rights through meticulous record-keeping and transparency. Instructions for completion are straightforward, with emphasis on the accuracy and honesty of the information provided, underlining the serious legal implications of falsifying documents. This wage statement is an invaluable tool, ensuring that workers are compensated in alignment with their earnings, thereby providing a semblance of security during their recovery period.

QuestionAnswer
Form NameGa Form Wc 6
Form Length1 pages
Fillable?Yes
Fillable fields186
Avg. time to fill out37 min 27 sec
Other namesgeorgia wage statement, wage state statement online, wc6, ga form wc

How to Fill Out Form WC-6

Form WC-6 at a glance

What it is: WC-6 Wage Statement of the Georgia State Board of Workers' Compensation.

A filled-in Form WC-6 example: an injured employee's thirteen weeks of wages
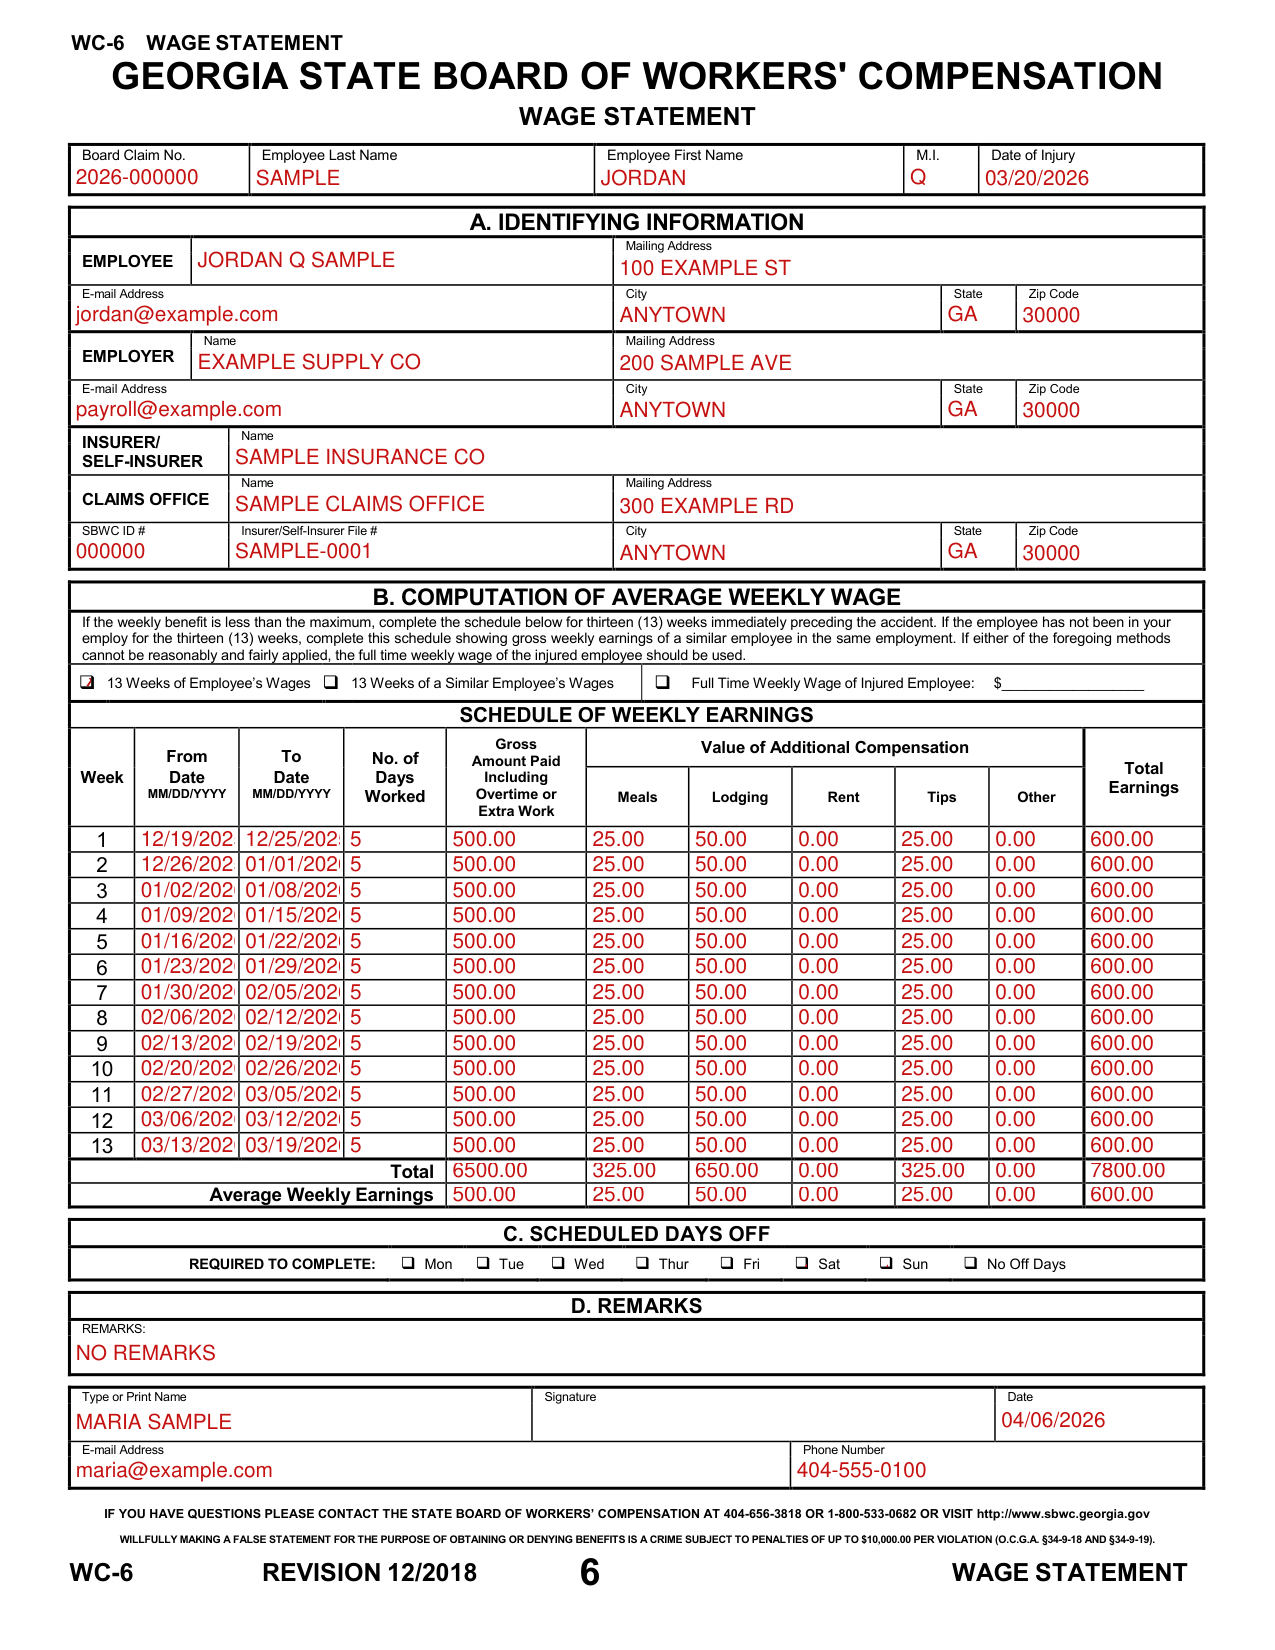
Form WC-6 example filled out, example: an injured employee's thirteen weeks of wages
Maria Sample completes the WC-6 Wage Statement for an injured employee. The schedule covers thirteen weeks of the employee's wages, with Saturday and Sunday as days off. The picture shows one employee; its names and figures are sample values. The thirteen weeks are used, so Full Time Weekly Wage stays empty. Each week has five days worked, 500.00 gross and 100.00 of additional compensation, so 600.00 total earnings.

How to fill out Form WC-6, box by box

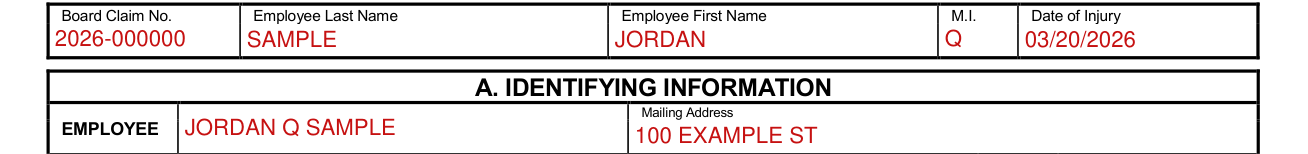
Board claim number, employee name and date of injury
Form WC-6 example filled out, board claim number, employee name and date of injury

Enter the Board Claim No., Employee Last Name, Employee First Name, M.I. and Date of Injury.

Employee

Form WC-6 example filled out, employee

Under A. IDENTIFYING INFORMATION, for the EMPLOYEE enter the Mailing Address, E-mail Address, City, State and Zip Code.

Employer

Form WC-6 example filled out, employer

For the EMPLOYER enter the Name, Mailing Address, E-mail Address, City, State and Zip Code.

Insurer/ Self-Insurer and Claims Office

Form WC-6 example filled out, insurer/ Self-Insurer and Claims Office

For the INSURER/ SELF-INSURER and the CLAIMS OFFICE enter the Name, Mailing Address, SBWC ID #, Insurer/Self-Insurer File #, City, State and Zip Code.

Computation of average weekly wage: the method

Form WC-6 example filled out, computation of average weekly wage: the method

B. COMPUTATION OF AVERAGE WEEKLY WAGE: If the weekly benefit is less than the maximum, complete the schedule for thirteen (13) weeks immediately preceding the accident. If the employee has not been in your employ for the thirteen (13) weeks, complete the schedule showing gross weekly earnings of a similar employee in the same employment. If either foregoing method (13 Weeks of Employee's Wages or 13 Weeks of a Similar Employee's Wages) cannot be reasonably and fairly applied, the full time weekly wage of the injured employee should be used.

13 Weeks of Employee's Wages, 13 Weeks of a Similar Employee's Wages and Full Time Weekly Wage of Injured Employee: $.

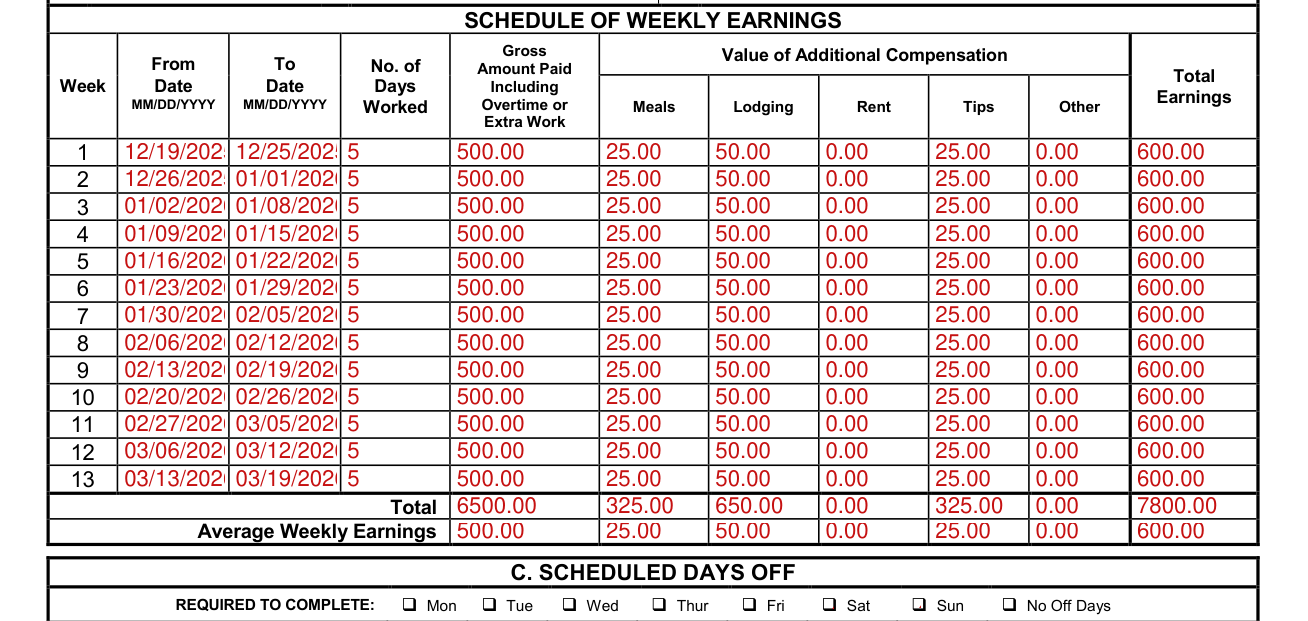
Schedule of weekly earnings
Form WC-6 example filled out, schedule of weekly earnings

In the SCHEDULE OF WEEKLY EARNINGS enter, for each Week, the From and To Date MM/DD/YYYY, the No. of Days Worked, the Gross Amount Paid Including Overtime or Extra Work, the Value of Additional Compensation (Meals, Lodging, Rent, Tips, Other) and the Total Earnings.

Week 1, 2, 3, 4, 5, 6, 7, 8, 9, 10, 11, 12 and 13, then Total and Average Weekly Earnings.

Scheduled days off required to complete

Form WC-6 example filled out, scheduled days off required to complete

Under C. SCHEDULED DAYS OFF REQUIRED TO COMPLETE: Mon, Tue, Wed, Thur, Fri, Sat, Sun or No Off Days.

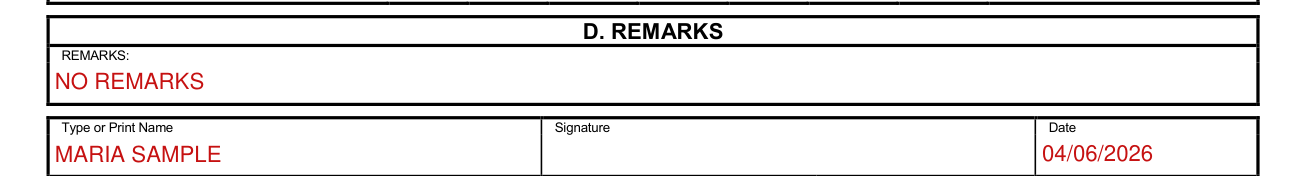
Remarks
Form WC-6 example filled out, remarks

Under D. REMARKS, enter the REMARKS.

Type or Print Name, Signature and Date

Form WC-6 example filled out, type or Print Name, Signature and Date

Enter Type or Print Name, Signature, Date, E-mail Address and Phone Number.

More rules for Form WC-6

If you have questions, contact the State Board of Workers' Compensation at 404-656-3818 or 1-800-533-0682 or visit http://www.sbwc.georgia.gov

Common questions about Form WC-6

Is there a penalty?

Willfully making a false statement for the purpose of obtaining or denying benefits is a crime subject to penalties of up to $10,000.00 per violation (checked November 2, 2026).

Sources

[1] Form WC-6 (12/2018), Wage Statement, Georgia State Board of Workers' Compensation (the Official source link on this page).

Please rate Ga Form Wc 6

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .