
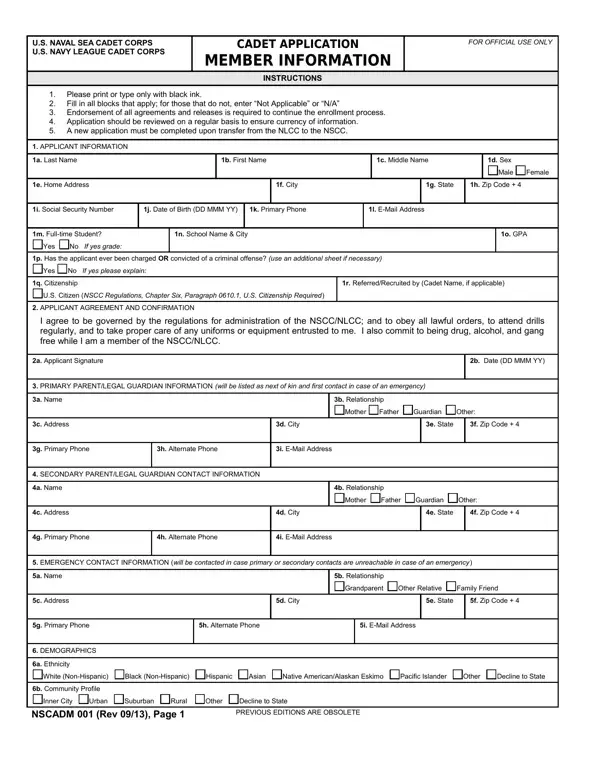

NSCADM 001 Cadet Application at a glance
What it is: This is the Cadet Application of the U.S. Naval Sea Cadet Corps and U.S. Navy League Cadet Corps: Member Information.
Who signs: Sign at 2a. Applicant Signature, 8a. Signature of Parent/Legal Guardian, 9d. Parent/Guardian Signature and 10b. Signature; the witness box 9g. Signature of Witness is signed by the Unit CO or Designated Officer, and 9b. Signature (MD, DO, NP, PA) by an MD, DO, NP or PA.
A filled-in NSCADM 001 Cadet Application example: a cadet applicant fills out page 1
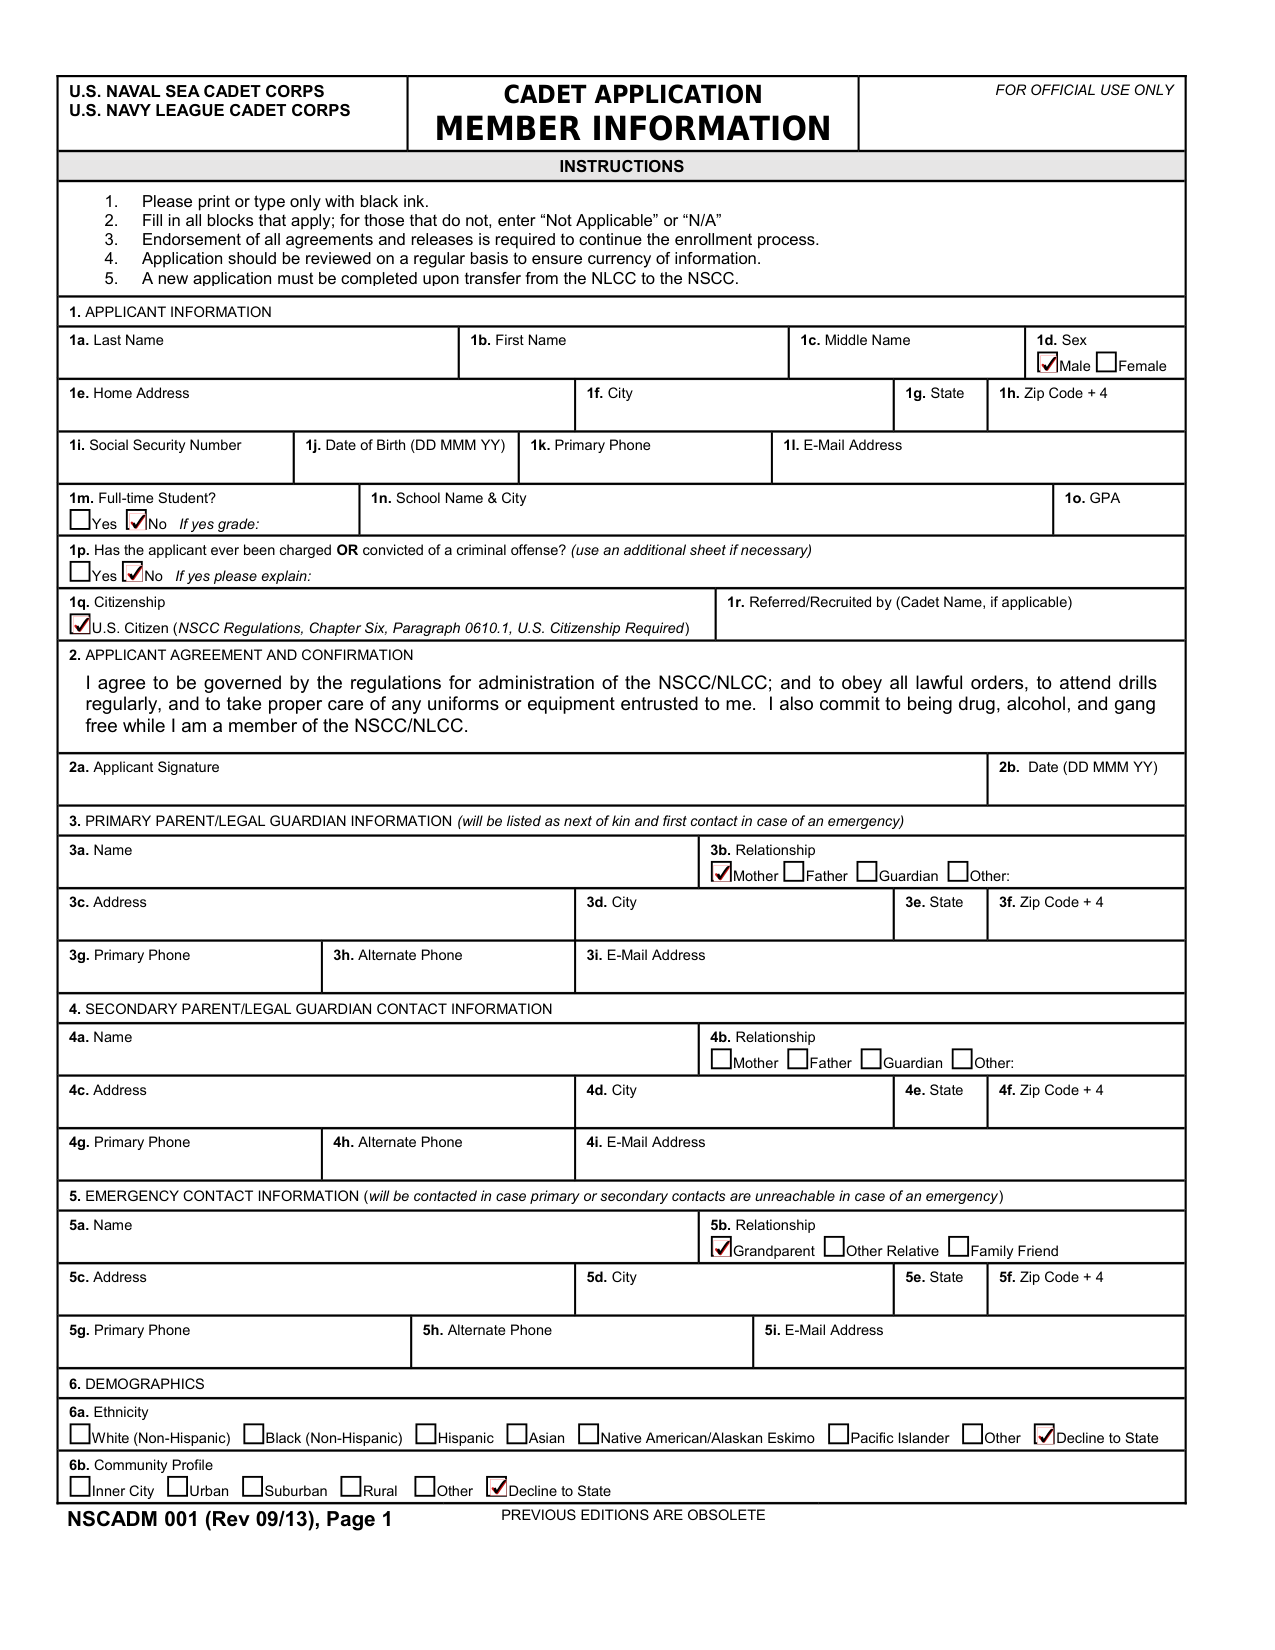
How to fill out NSCADM 001 Cadet Application, box by box
1d. Sex
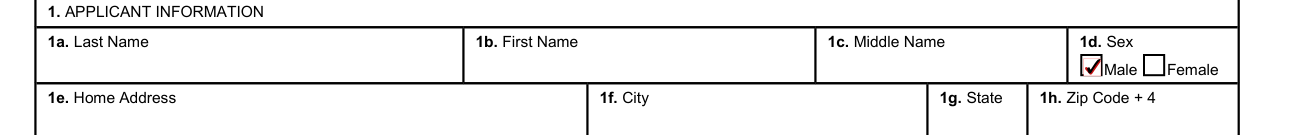
Under 1d. Sex, mark Male or Female.
1m. Full-time Student?

Under 1m. Full-time Student?, mark Yes or No; if yes, enter the grade.
1p. Charged OR convicted of a criminal offense

1p. Has the applicant ever been charged OR convicted of a criminal offense? Mark Yes or No; if yes please explain (use an additional sheet if necessary).
1q. Citizenship

Under 1q. Citizenship, mark U.S. Citizen (NSCC Regulations, Chapter Six, Paragraph 0610.1, U.S. Citizenship Required).
3b. Relationship

3. PRIMARY PARENT/LEGAL GUARDIAN INFORMATION will be listed as next of kin and first contact in case of an emergency. Mark Mother, Father, Guardian or Other in 3b. Relationship.
Enter 3a. Name, 3c. Address, 3d. City, 3e. State, 3f. Zip Code + 4, 3g. Primary Phone, 3h. Alternate Phone and 3i. E-Mail Address.
4b. Relationship

4. SECONDARY PARENT/LEGAL GUARDIAN CONTACT INFORMATION: in 4b. Relationship, mark Mother, Father, Guardian or Other.
5b. Relationship

5. EMERGENCY CONTACT INFORMATION will be contacted in case primary or secondary contacts are unreachable in case of an emergency. In 5b. Relationship, mark Grandparent, Other Relative or Family Friend.
6a. Ethnicity

Under 6a. Ethnicity, mark White (Non-Hispanic), Black (Non-Hispanic), Hispanic, Asian, Native American/Alaskan Eskimo, Pacific Islander, Other or Decline to State.
6b. Community Profile

Under 6b. Community Profile, mark Inner City, Urban, Suburban, Rural, Other or Decline to State.
4. MEDICAL HISTORY

Under 4. MEDICAL HISTORY, mark each item “YES” or “NO”; every item marked YES must be fully explained in block 9: explain treatment to return cadet to medically fit for NSCC.
If taking medications at time of enrollment, list in Block 9.
Proof of immunization for polio, measles, mumps, rubella, hepatitis B, pertussis and tetanus plus diphtheria and Menactra vaccine for Meningitis must be attached.
6. ALLERGIES
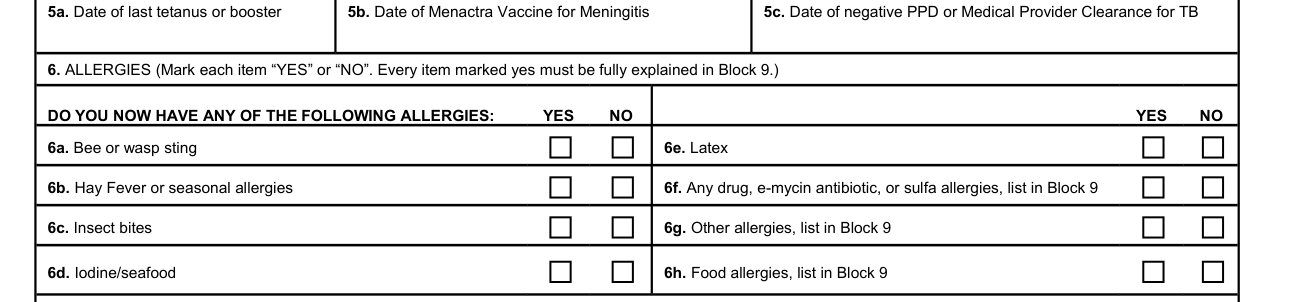
Under 6. ALLERGIES, mark each item “YES” or “NO”. Every item marked yes must be fully explained in Block 9.
If I do not want my child to be administered over the counter medications, or certain medications concurrent with other medications, I must specify those medications or write, “Do not medicate my child with any over the counter medications” in Block 9.
8. MEDICAL PROVIDER ENDORSEMENT
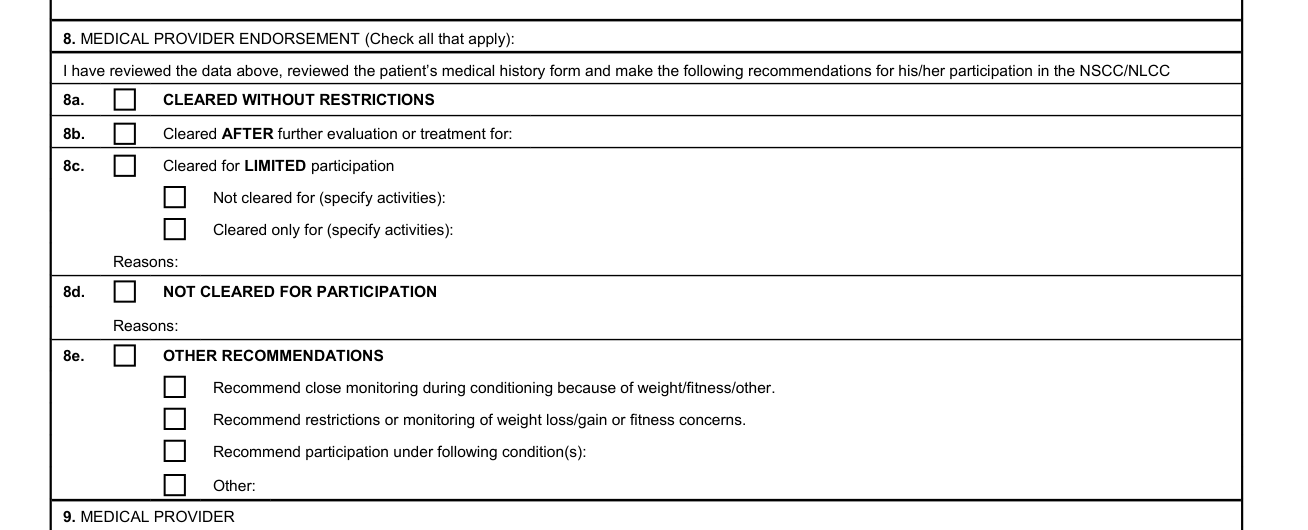
Under 8. MEDICAL PROVIDER ENDORSEMENT, check all that apply: 8a. CLEARED WITHOUT RESTRICTIONS, Cleared AFTER further evaluation or treatment for, 8c. Cleared for LIMITED participation, 8d. NOT CLEARED FOR PARTICIPATION or 8e. OTHER RECOMMENDATIONS.
More rules for NSCADM 001 Cadet Application
Print or type only with black ink. Fill in all blocks that apply; for those that do not, enter “Not Applicable” or “N/A”.
Endorsement of all agreements and releases is required to continue the enrollment process.
A new application must be completed upon transfer from the NLCC to the NSCC.
In 1. APPLICANT INFORMATION, enter 1a. Last Name, 1b. First Name, 1c. Middle Name, 1e. Home Address, 1f. City, 1g. State, 1h. Zip Code + 4, 1i. Social Security Number, 1j. Date of Birth (DD MMM YY), 1k. Primary Phone and 1l. E-Mail Address.
Enter 1n. School Name & City and 1o. GPA.
Enter 1r. Referred/Recruited by (Cadet Name, if applicable).
2. APPLICANT AGREEMENT AND CONFIRMATION: I agree to be governed by the regulations for administration of the NSCC/NLCC; and to obey all lawful orders, to attend drills regularly, and to take proper care of any uniforms or equipment entrusted to me. Sign at 2a. Applicant Signature and enter 2b. Date (DD MMM YY).
Sign 8a. Signature of Parent/Legal Guardian and enter 8b. Date (DD MMM YY).
Enter 9a. Cadet Full Name, 9b. Social Security Number and 9c. Parent/Guardian Name (Print or Type); sign 9d. Parent/Guardian Signature and enter 9e. Date (DD MMM YY); the witness enters 9f. Name of Witness (Unit CO or other Designated Officer - Print or Type) and signs 9g. Signature of Witness (Unit CO or Designated Officer).
Under 5. IMMUNIZATION RECORDS, attach copy of immunization record to this form: enter 5a. Date of last tetanus or booster, 5b. Date of Menactra Vaccine for Meningitis and 5c. Date of negative PPD or Medical Provider Clearance for TB.
10. AUTHORIZATION AND RELEASE: enter 10a. Parent/Guardian Name (Type or Print), sign 10b. Signature and enter 10c. Date (DD MMM YY).
After enrollment, use this form to screen cadets for continued medical fitness before sending to Orientation, Recruit, Advanced and/or other trainings.
A licensed medical provider must complete this examination.
Conditions that will or are likely to require treatment, particularly unresolved injuries and recurrent illnesses, must be listed.
4. LABORATORY FINDINGS are only required for those with a history of urinary tract infections or anemia; enter N/A if tests were not administered.
9. MEDICAL PROVIDER: enter 9a. Name of Medical Provider (Type or Print) or Medical Provider Stamp, sign 9b. Signature (MD, DO, NP, PA) and enter 9c. Date (DD MMM YY).
If the cadet is taking prescription medications, a qualified medical provider must endorse this document in Section 10, confirming the accuracy of the prescription information provided. Medical provider signature for OTC medications is NOT REQUIRED; parent signature is sufficient for OTC medications.
Medication must NOT have expired.
Under 4. PRESCRIPTION OR NON-PRESCRIPTION MEDICATION (Use additional documents if more than three medications are provided), enter 4a. Name of Medication, 4b. Strength, 4c. Total Quantity Required and 4d. Total Quantity Sent.
If Unit Commanding Officer determines accommodation is considered not reasonable, or cannot be made, Unit Commanding Officer must so state, with firm reasons and further forward to the Regional Director for review/comment and NHQ Representative for final determination.
Mark Approve or Disapprove in 8. REGIONAL DIRECTOR'S RECOMMENDATION and in 9. NHQ REPRESENTATIVE'S DECISION.
The adult leadership of the NSCC/NLCC is made up entirely of volunteers.
Mark Volunteer as a uniformed adult leader (must meet weight requirements), Volunteer as a non-uniformed adult leader, Join a Parent's Auxiliary Group, Assist with unit recruiting, Assist with unit fundraising, Assist with unit morale activities (outings, picnics, dances, etc.), Assist with unit administrative functions (copying, typing, etc.), Assist with unit supply (issue uniforms, maintaining inventory).
Common questions about NSCADM 001 Cadet Application
Who signs it?
Sign at 2a. Applicant Signature, 8a. Signature of Parent/Legal Guardian, 9d. Parent/Guardian Signature and 10b. Signature (10a. Parent/Guardian Name); the Unit CO or Designated Officer signs 9g. Signature of Witness, and an MD, DO, NP or PA signs 9b. Signature (MD, DO, NP, PA).
Are there fees?
Payment of enrollment fees will be required ANNUALLY, and payment of uniform fees may be required upon enrollment.
What am I certifying when I sign?
"I certify that, to the best of my knowledge, he/she is physically and mentally fit to take part in vigorous activities or if not, I have disclosed all physical/medical/disability limitations and he/she is not suffering from any communicable disease."
When is this form not the right one?
On the CADET APPLICATION REQUEST FOR ACCOMMODATION page, the INSTRUCTIONS say to complete this form ONLY when an accommodation is requested for a prospective cadet under the Americans with Disabilities Act. This form, used as a supplement to the Report of Medical History, is MANDATORY for all Cadets who are currently taking medication and will report to training with prescription and/or non-prescription (over the counter) medications.
Sources
[1] NSCADM 001 (Rev 09/13), Cadet Application, U.S. Naval Sea Cadet Corps and U.S. Navy League Cadet Corps (the served file) (the Official source link on this page).