
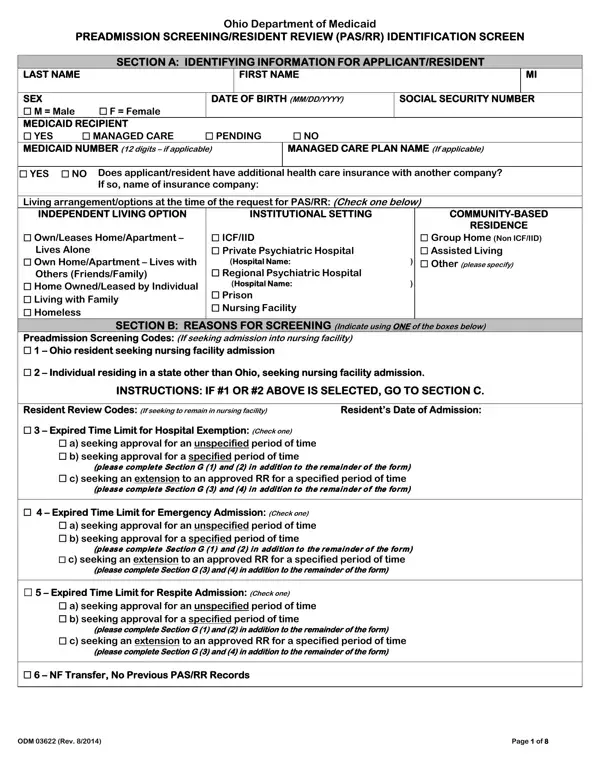
Form ODM 03622 at a glance
What it is: ODM 03622 is the Ohio Department of Medicaid Preadmission Screening and Resident Review (PASRR) Identification Screen.
Where and when to file: This form must be submitted electronically.
To process the screen, the submitter must provide his/her name and address and sign.
A filled-in Form ODM 03622 example: a preadmission screening for a person living at home
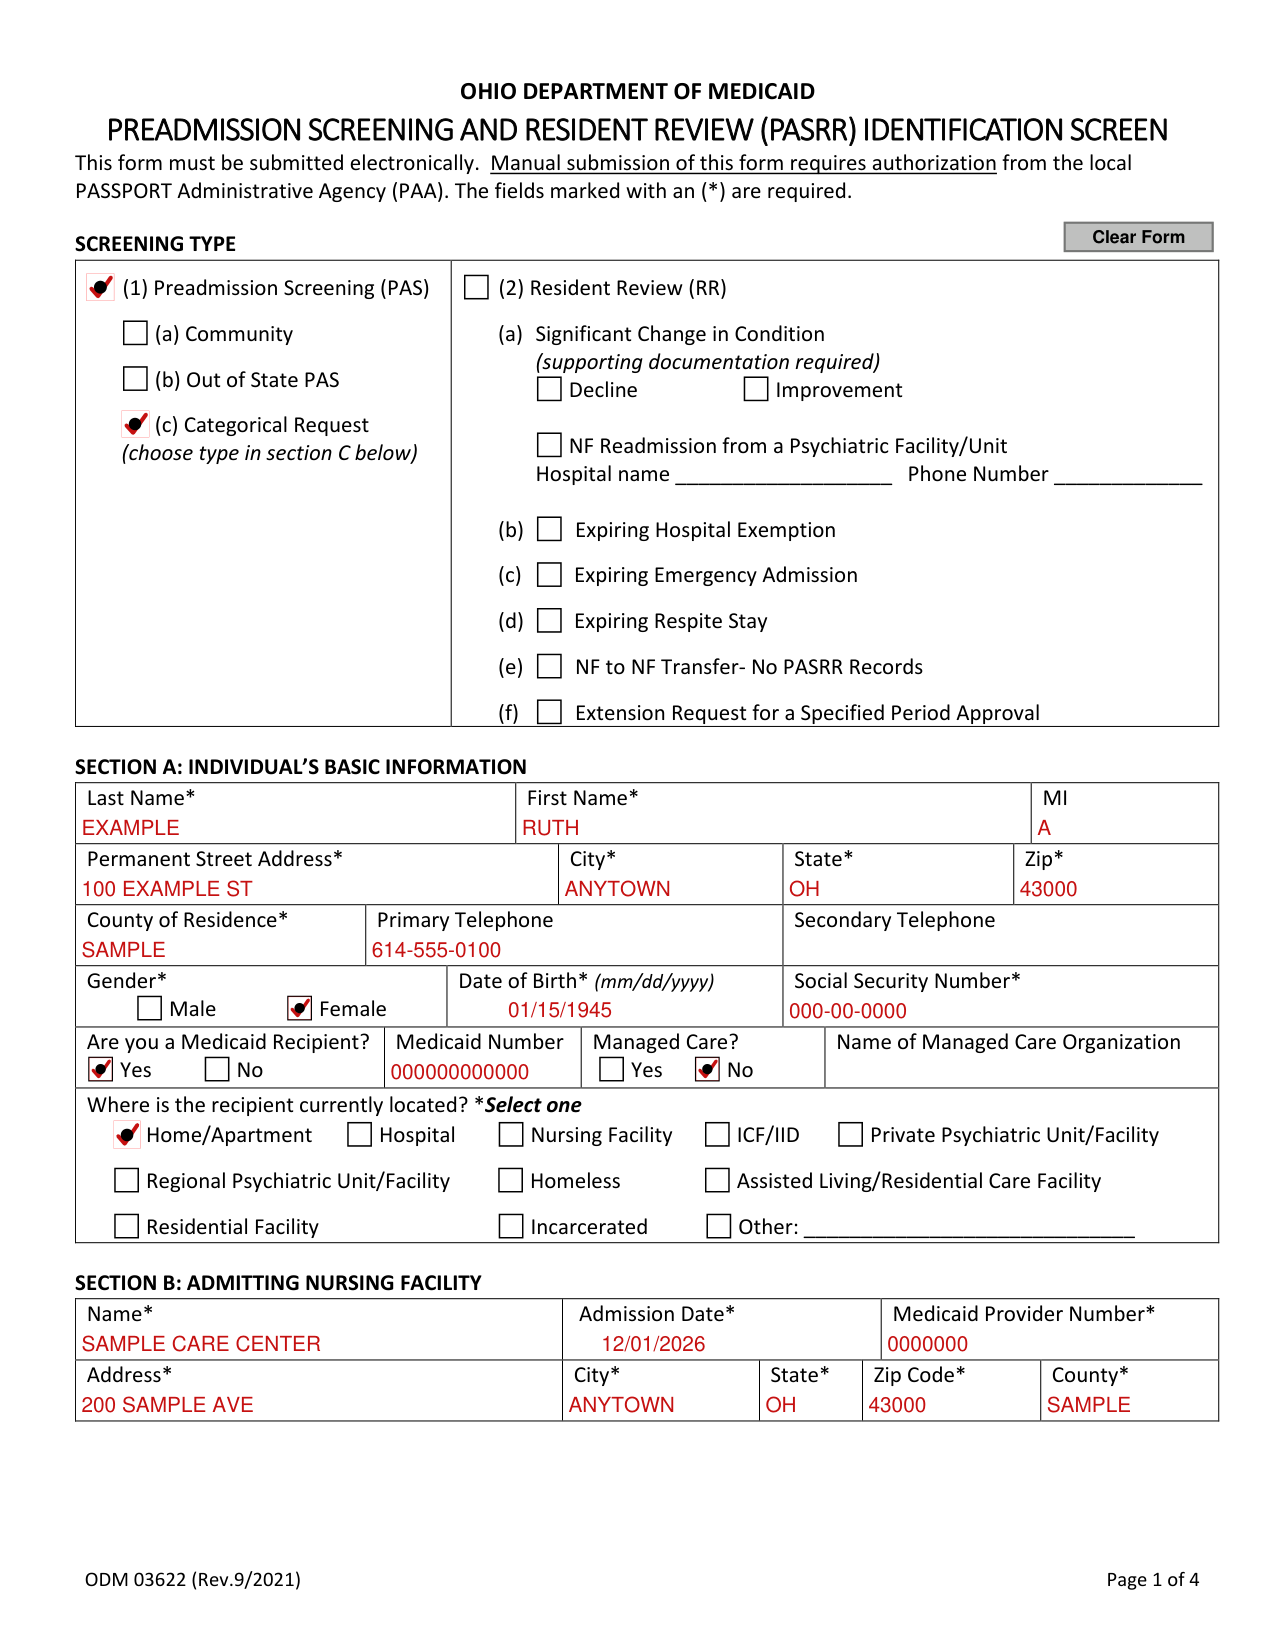
How to fill out Form ODM 03622, box by box
Screening type
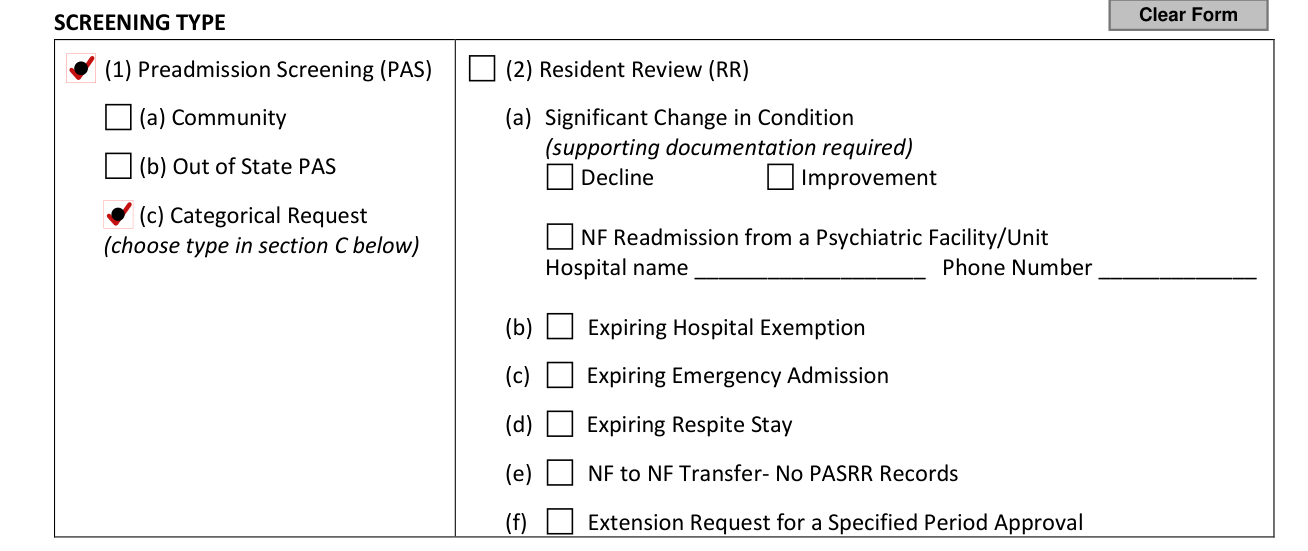
Under SCREENING TYPE, mark (1) Preadmission Screening (PAS) or (2) Resident Review (RR).
For (c) Categorical Request, choose the type in section C.
Section A: Individual's basic information
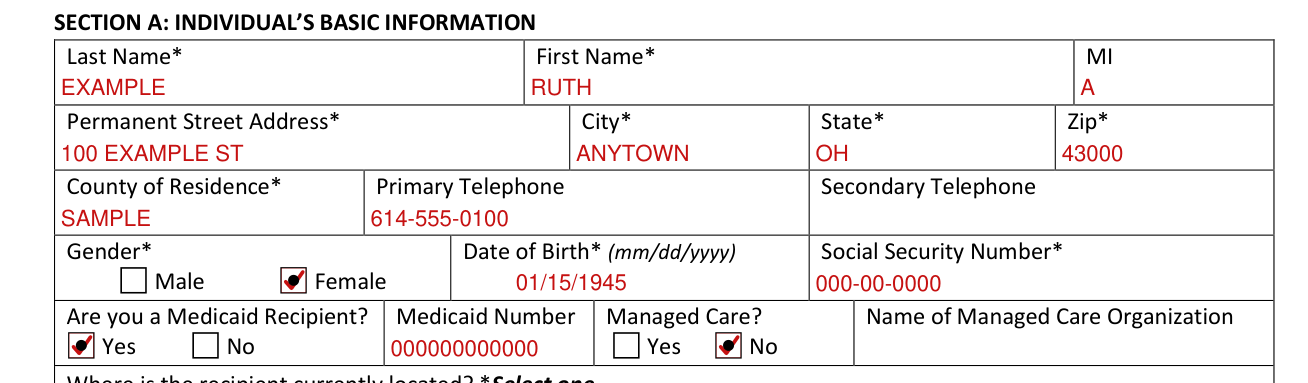
In SECTION A: INDIVIDUAL'S BASIC INFORMATION, fill in Last Name*, First Name* and MI.
Fill in Permanent Street Address*, City*, State* and Zip*, then County of Residence*, Primary Telephone and Secondary Telephone.
Mark Gender* as Male or Female. Fill in Date of Birth* as mm/dd/yyyy and the Social Security Number*.
Mark Are you a Medicaid Recipient? as Yes or No, fill in the Medicaid Number, mark Managed Care? as Yes or No and fill in the Name of Managed Care Organization.
Where is the recipient currently located?

For Where is the recipient currently located? *Select one: Home/Apartment, Hospital, Nursing Facility, ICF/IID, Private Psychiatric Unit/Facility, Regional Psychiatric Unit/Facility, Homeless, Assisted Living/Residential Care Facility, Residential Facility, Incarcerated or Other.
Section B: Admitting nursing facility
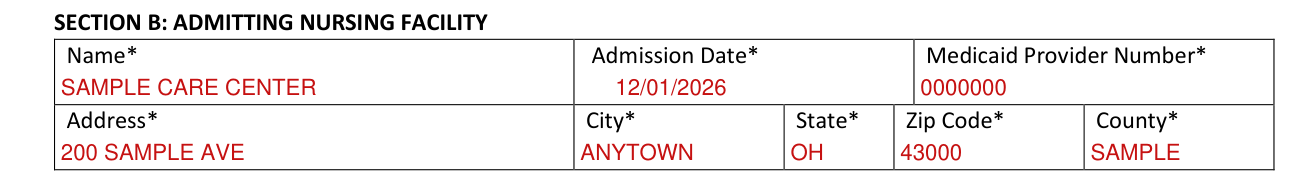
In SECTION B: ADMITTING NURSING FACILITY, fill in Name*, Admission Date*, Medicaid Provider Number*, Address*, City*, State*, Zip Code* and County*.
Section C: Categorical determination and extension requests
SECTION C: CATEGORICAL DETERMINATION AND EXTENSION REQUESTS requires supporting documentation. Choose only ONE option.
Categorical Determination (1) Emergency NF stay in situations requiring protective services as defined in OAC 5101:2-20-01 has a Time Limit = 7 days.
Categorical Determination (2) Respite NF stay to provide respite to in-home caregivers to whom the individual is expected to return has a Time Limit = 14 days.
For an Extension Request, fill in (1) Number of Days (up to 90 days) and (2) Reason for Extension Request? Describe.
Section D: Medical diagnosis
In SECTION D: MEDICAL DIAGNOSIS, mark (1) Does the individual have a diagnosis of dementia?* as No, Yes or Unknown.
If “Yes” or “Unknown”, please attach documentation related to symptoms, treatment, or a diagnosis of dementia.
Please list current diagnoses: * (if none, indicate none)
Section E: Indications of serious mental illness, 1) and 2)
All questions in Section E must be completed.
Mark 1) Does the individual have a diagnosis(es) of any of the mental disorders listed?* as No, Yes or Unknown. Check all that apply: Schizophrenia, Personality Disorder(s), Mood Disorder(s), Other Psychotic Disorder(s), Delusional Disorder(s), Another mental disorder that may lead to a chronic disability (If so, describe), Panic or other Severe Anxiety Disorder(s) and Somatic Symptom Disorder(s).
Mark 2) Does the individual have a diagnosis(es) of a substance use related disorder?* as No, Yes or Unknown. If Yes, specify diagnosis(es) and the Last reported usage.
Section E: Psychiatric services in the last TWO (2) years
For 3) Within the last TWO (2) years, has the individual utilized psychiatric services listed more than once DUE TO THE MENTAL DISORDER?* complete the information before responding. Indicate the number of times the individual utilized each service over the past 2 years: Ongoing case management from a mental health agency, Emergency mental health services, Inpatient psychiatric hospitalization, Partial hospitalization treatment program for psychiatric reasons and Admission to residential facility for mental health services provided by mental health agency.
If the total score is greater than 1 answer yes in question 3). Fill in the TOTAL.
Section E: Disruption in living arrangement and functional limitations
Mark 4) Within the last TWO (2) years, has the individual had a disruption in his/her usual living arrangement (i.e. arrest, eviction, inter or intra-agency transfer, non-hospital locked seclusion) DUE TO THE MENTAL DISORDER?* as No, Yes or Unknown.
Mark 5) Within the past SIX (6) months, has the individual experienced one or more of the following functional limitations on a continuing or intermittent basis DUE TO THE MENTAL DISORDER?* as No, Yes or Unknown. Check all that apply.
Check all that apply: Maintaining Personal Hygiene, Walking/Getting Around, Maintaining Adequate Diet, Maintaining Prescribed Medication Regimen, Performing Household Chores, Going Shopping, Using Available Transportation, Securing Necessary Support Services, Managing Available Funds, Verbalizing Needs, Dressing Self and Preparing/Obtaining Meals.
Section E: Indications of serious mental illness, 6) medications and the SMI indication
Mark 6) In the past SIX (6) months, has the individual been prescribed any psychotropic medications? * as No, Yes or Unknown. Check all that apply: Anti-psychotics, Anti-depressants, Anti-anxiety, Mood Stabilizers or Other (please specify).
The individual has indications of Serious Mental Illness (SMI) if any of the following are true: Answered yes OR unknown to AT LEAST two questions of E(1), E(3) through E(5) OR Is currently admitted in an inpatient psychiatric unit/facility. Mark Does the individual have indications of Serious Mental Illness? as No or Yes.
Section G: Legal guardian / power of attorney information
In SECTION G: LEGAL GUARDIAN / POWER OF ATTORNEY INFORMATION (supporting documentation required), mark 1) Does the individual have a court appointed legal guardian? and 2) Does the individual have a legal representative (e.g. Power of Attorney)? as No or Yes (If yes, fill in name and address.), with Last Name * and First Name *.
Fill in Street Address *, City*, State*, Zip Code*, Email (optional) and Phone Number*.
Section H: Attending physician information
In SECTION H: ATTENDING PHYSICIAN INFORMATION, fill in Last Name, First Name, Street Address, City, State, Zip Code and Phone Number.
Submitter information and certification
Fill in Last Name *, First Name *, Facility/Organization Name *, Email Address *, Street Address, City, State, Zip Code, County*, Telephone Number * and Fax Number *.
I understand this screening information may be relied upon for the payment of claims from Federal and State funds, and that any willful falsification or concealment of a material fact may be prosecuted under Federal and State laws.
By signing you certify that, to the best of your knowledge, the information is true, accurate and complete. This form must be signed and dated to be valid. Sign in Signature, and fill in the Date (mm/dd/yyyy), the Employer and the Title.
More rules for Form ODM 03622
Complete the form fully and with accuracy. Incomplete forms may be returned with a request for further information.
Manual submission of this form requires authorization from the local PASSPORT Administrative Agency (PAA).
Sources
[1] Form ODM 03622 (Rev.9/2021), Preadmission Screening and Resident Review (PASRR) Identification Screen, Ohio Department of Medicaid (the Official source link on this page).