

Form RG-007A at a glance
What it is: This is the South Carolina Department of Motor Vehicles RG-007A Application for Placard and/or License Plate for People Who Have a Disability.
On the RG-007A Application for Placard and/or License Plate for People Who Have a Disability, complete a separate application form for each person who has a disability.
Section 1 - Applicant's information: Provide the full legal name, street, and mailing address, including city, state, zip code, and the phone number of the person who has a disability. List the SC driver's license, beginner's permit, or identification card number of the person who has a disability (if applicable).
The signature of the person who has a disability or the legal guardian is required on the Signature of Applicant (Parent/Legal Guardian) line.
All applicants must complete Section 2, Transaction Type.
Section 3, the Physician's Statement, must be completed by a licensed Physician, an Advanced Practice Registered Nurse (APRN), or a Physician Assistant (PA), who must indicate the disability and length of disability. APRNs are nurse practitioners, certified nurse-midwives, clinical nurse specialists, and certified registered nurse anesthetists.
The vehicle owner must sign to certify that the vehicle is insured and will maintain insurance throughout the registration period.
A filled-in Form RG-007A example: a placard for a permanent disability
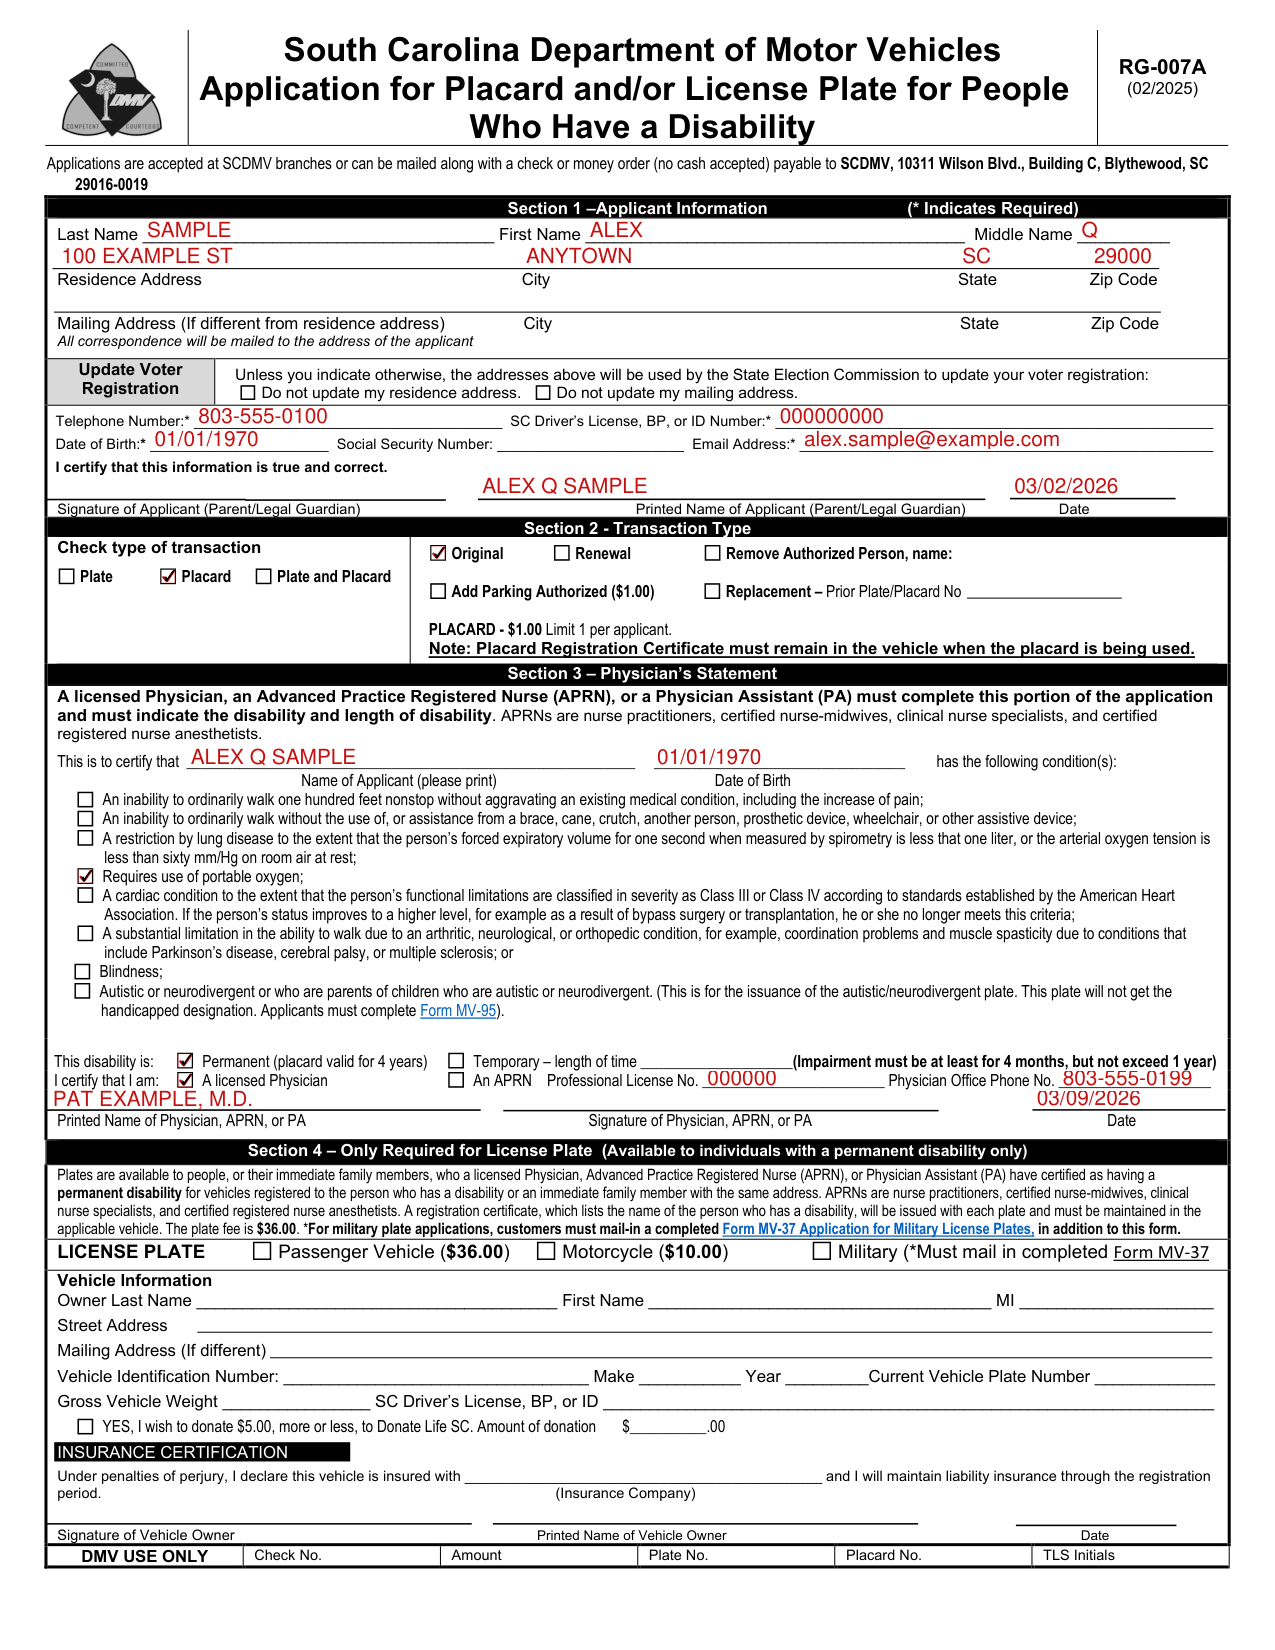
How to fill out Form RG-007A, box by box
Tap a group of boxes to open it, and a picture to see it full size.
Section 1: the applicant's name, addresses and voter registration
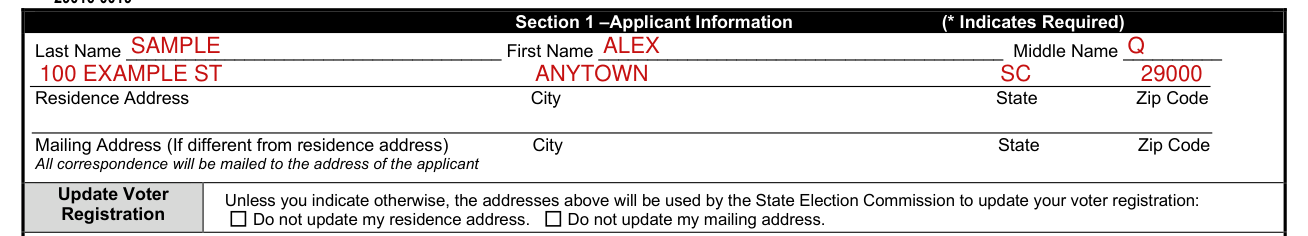
Enter the Last Name, First Name and Middle Name, then the Residence Address with City, State and Zip Code.
Enter a Mailing Address, with City, State and Zip Code, only if it is different from the residence address; all correspondence will be mailed to the address of the applicant.
Unless indicated otherwise, the addresses above will be used by the State Election Commission to update the voter registration; the two check boxes are Do not update my residence address and Do not update my mailing address.
The Update Voter Registration opt-out check boxes do not apply to business customers.
Section 1: telephone number, ID number, date of birth, email and signature

Enter the Telephone Number, the SC Driver's License, BP, or ID Number, the Date of Birth, the Social Security Number and the Email Address.
* Indicates Required: Telephone Number, SC Driver's License, BP, or ID Number, Date of Birth and Email Address. Social Security Number has no *.
I certify that this information is true and correct. Sign on the Signature of Applicant (Parent/Legal Guardian) line, then write the Printed Name of Applicant (Parent/Legal Guardian) and the Date.
Section 2: the type of transaction
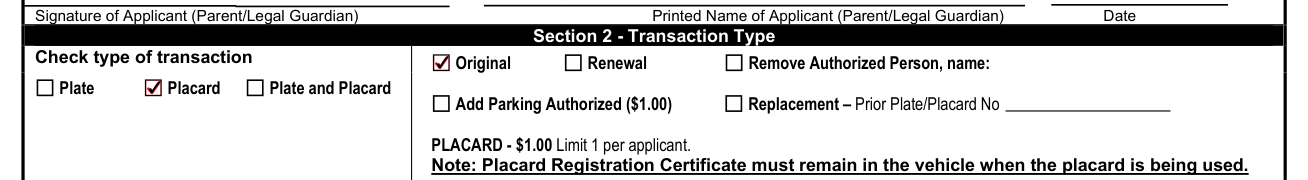
Check the type of transaction: Original, Renewal, Remove Authorized Person (with the name), Add Parking Authorized ($1.00) or Replacement (with the Prior Plate/Placard No). The form also prints the boxes Plate, Placard and Plate and Placard.
Check One. Plate: for customers who only want a plate; must complete all sections.
Placard: for customers who only want a placard; must complete sections 1-3.
Plate and Placard: for customers who want both plate and placard; must complete all sections.
Original: for first-time applicants.
Renewal: to renew placard or license plate.
Replacement: to replace a lost, stolen or destroyed plate, or placard and certificate.
Second page, Add Person who has a disability: to add the name of an individual who has a disability to the Registration Certificate ($1.00). Section 3 - Physician's Statement.
Placards are available to people who a licensed Physician, APRN, or PA have certified as having a disability.
First page: Note: Placard Registration Certificate must remain in the vehicle when the placard is being used. Second page: The placard fee is $1.00 and only one placard may be issued per applicant. A registration certificate will be issued with each placard and must remain with the person who has a disability when the placard is used.
Section 3: the conditions the physician, APRN, or PA certifies

This is to certify that Name of Applicant (please print), Date of Birth, has the following condition(s): An inability to ordinarily walk one hundred feet nonstop without aggravating an existing medical condition, including the increase of pain; An inability to ordinarily walk without the use of, or assistance from a brace, cane, crutch, another person, prosthetic device, wheelchair, or other assistive device; A restriction by lung disease to the extent that the person's forced expiratory volume for one second when measured by spirometry is less than one liter, or the arterial oxygen tension is less than sixty mm/Hg on room air at rest; Requires use of portable oxygen; A cardiac condition to the extent that the person's functional limitations are classified in severity as Class III or Class IV according to standards established by the American Heart Association. If the person's status improves to a higher level, for example as a result of bypass surgery or transplantation, he or she no longer meets this criteria; A substantial limitation in the ability to walk due to an arthritic, neurological, or orthopedic condition, for example, coordination problems and muscle spasticity due to conditions that include Parkinson's disease, cerebral palsy, or multiple sclerosis; or Blindness; Autistic or neurodivergent or who are parents of children who are autistic or neurodivergent. (This is for the issuance of the autistic/neurodivergent plate. This plate will not get the handicapped designation. Applicants must complete Form MV-95).
The physician, APRN, or PA must certify the applicant as having a disability by checking the qualifying conditions.
Section 3: Permanent or Temporary, license number, signature and date

The Physician, APRN, or PA must also indicate if the disability is permanent or temporary and state the length of the disability in the space provided. This disability is: Permanent (placard valid for 4 years). Temporary - length of time (Impairment must be at least for 4 months, but not exceed 1 year). I certify that I am: A licensed Physician or An APRN, Professional License No., Physician Office Phone No.
Write the Printed Name of Physician, APRN, or PA, sign on the Signature of Physician, APRN, or PA line and write the Date.
Section 4: the license plate (plate only)

Section 4 is only required for a license plate and is available to individuals with a permanent disability only; complete it only if applying for a license plate.
Plates are available to people, or their immediate family members, who a licensed Physician, Advanced Practice Registered Nurse (APRN), or Physician Assistant (PA) have certified as having a permanent disability for vehicles registered to the person who has a disability or an immediate family member with the same address. A registration certificate, which lists the name of the person who has a disability, will be issued with each plate and must be maintained in the applicable vehicle. The plate fee is $36.00. LICENSE PLATE: Passenger Vehicle ($36.00), Motorcycle ($10.00), Military (Must mail in completed Form MV-37).
If interested in applying for a military plate, you must mail-in a completed Application for Military License Plate (Form MV-37) in addition to RG-007A.
Section 4: the vehicle and its owner

Under Vehicle Information, enter the Owner Last Name, First Name and MI, the Street Address and the Mailing Address (If different).
Enter the Vehicle Identification Number, Make, Year, Current Vehicle Plate Number, Gross Vehicle Weight, and SC Driver's License, BP, or ID.
Gross Vehicle Weight (GVW) is for property carrying vehicles.
License plates may be issued to vehicles used to transport a certified person who has a disability if the vehicle is owned and titled in the name of the person who has a disability or his/her immediate family member who resides in the same household.
Section 4: Donate Life SC and the insurance certification
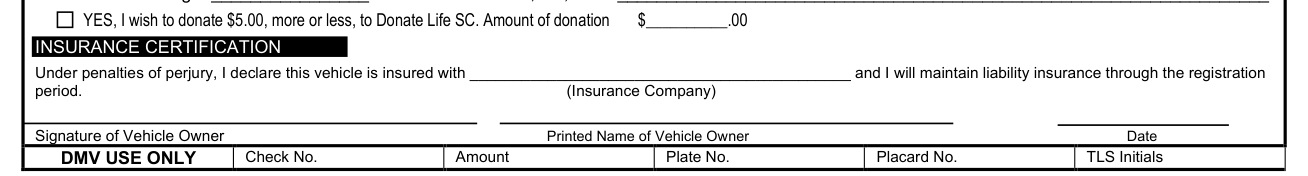
Indicate if you wish to donate to Donate Life SC: YES, I wish to donate $5.00, more or less, to Donate Life SC. If you would like to make a donation, indicate the amount in the space provided: Amount of donation.
INSURANCE CERTIFICATION: Under penalties of perjury, I declare this vehicle is insured with (Insurance Company) and I will maintain liability insurance through the registration period.
The name of the liability insurance company should be listed, not the agent.
Sign on the Signature of Vehicle Owner line, then write the Printed Name of Vehicle Owner and the Date. DMV USE ONLY: Check No., Amount, Plate No., Placard No., TLS Initials.
Common questions about Form RG-007A
Where do I file it?
First page: Applications are accepted at SCDMV branches or can be mailed along with a check or money order (no cash accepted) payable to SCDMV, 10311 Wilson Blvd., Building C, Blythewood, SC 29016-0019. Second page: Applications are accepted at an SCDMV branch or can be mailed to the following address along with a check or money order (no cash accepted) payable to the SCDMV: SC Department of Motor Vehicles PO Box 1498 Blythewood, SC 29016-0019.
Sources
[1] Form RG-007A (02/2025), Application for Placard and/or License Plate for People Who Have a Disability, South Carolina Department of Motor Vehicles (the Official source link on this page).
