
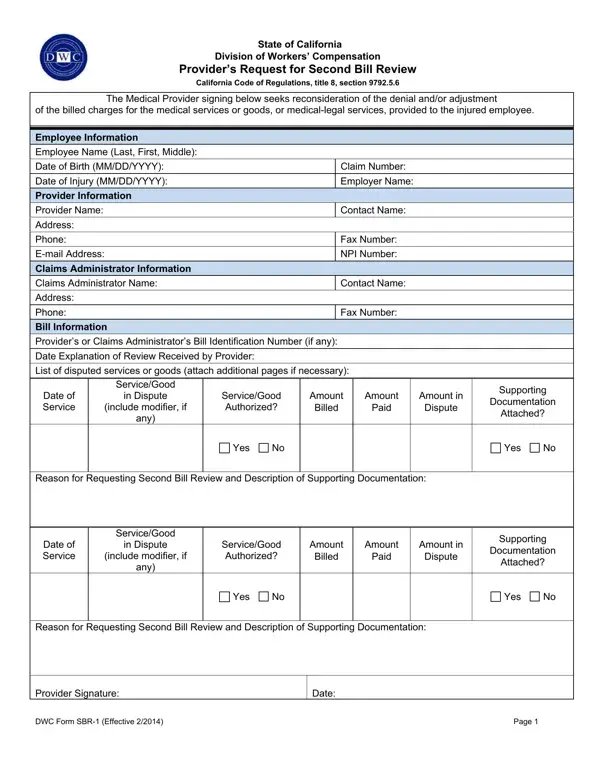
Form SBR-1 at a glance
What it is: The Provider's Request for Second Bill Review seeks reconsideration of the denial and/or adjustment of the billed charges for the medical services or goods, or medical-legal services, provided to the injured employee.
Where and when to file: The Request for Second Bill Review form can either be mailed or faxed to the claims administrator.
The Provider's Request for Second Bill Review (DWC Form SBR-1, Effective 2/2014) is used to initiate the second bill review process required by Labor Code sections 4603.2(e), for medical treatment services and goods, and by Labor Code section 4622, for medical-legal services, to dispute the amount of payment.
A medical provider who disputes the amount paid by a claims administrator on either a bill for medical treatment services or goods, or a bill for medical-legal expenses, must request a second review of the bill from the claims administrator.
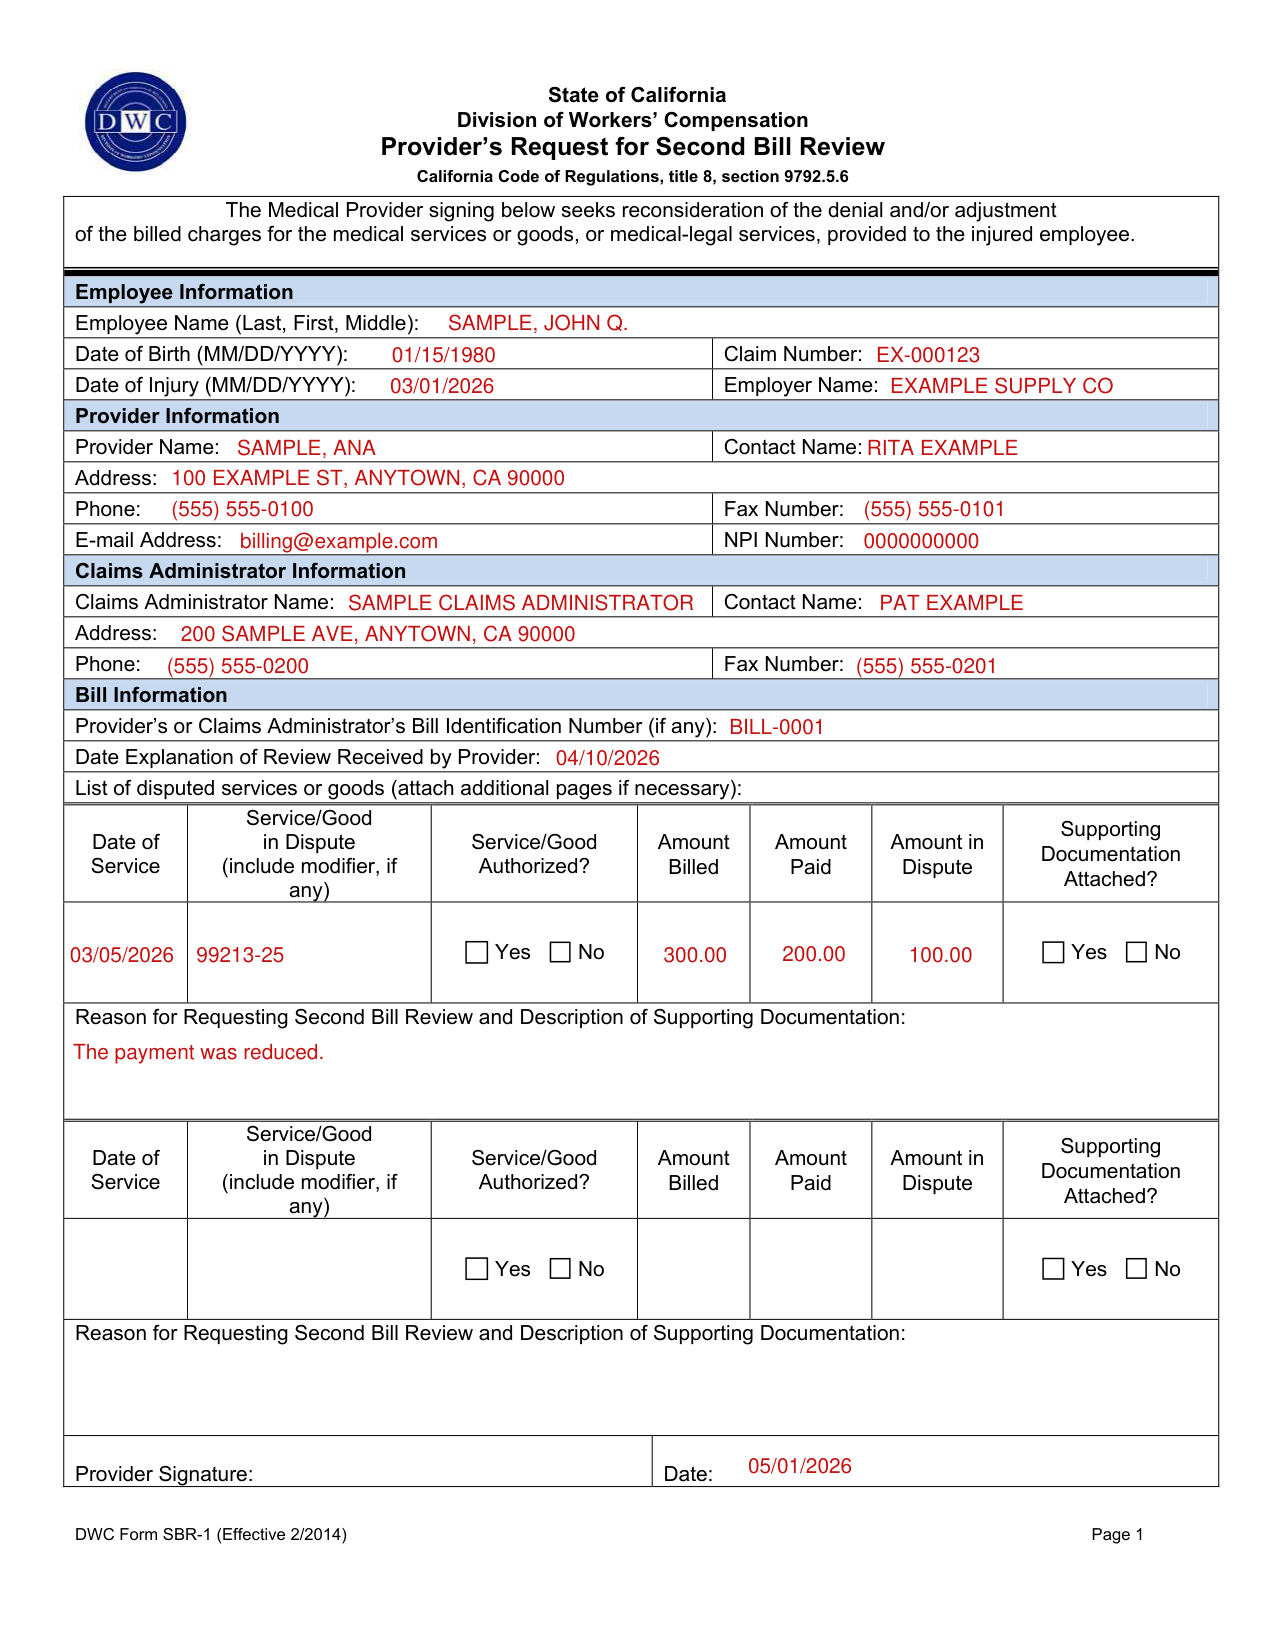
A filled-in Form SBR-1 example: a provider disputes one reduced payment
How to fill out Form SBR-1, box by box
Employee Information
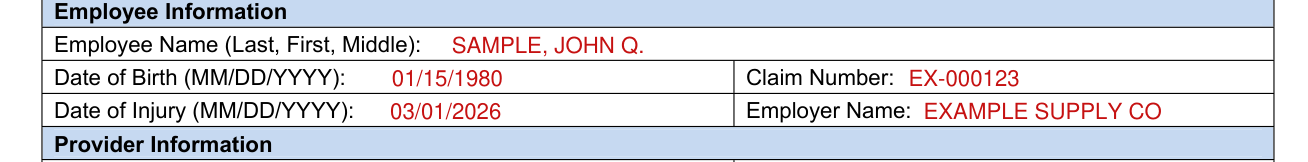
The requesting provider must complete all fields in the Employee Information, Provider Information, and Claims Administrator Information sections. Enter the Employee Name (Last, First, Middle), Date of Birth (MM/DD/YYYY), Claim Number, Date of Injury (MM/DD/YYYY) and Employer Name.
Provider Information
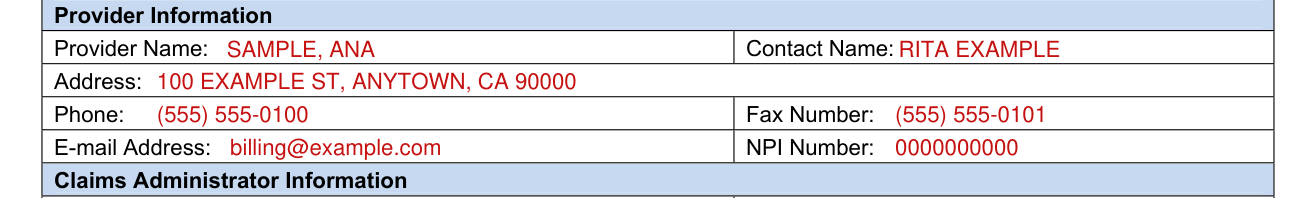
Enter the Provider Name, Contact Name, Address, Phone, Fax Number, E-mail Address and NPI Number.
Claims Administrator Information
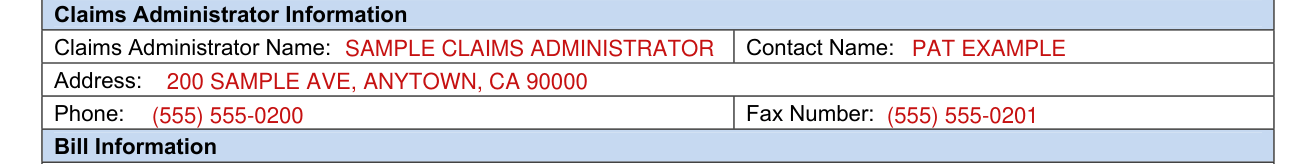
Enter the Claims Administrator Name, Contact Name, Address, Phone and Fax Number.
Bill Information
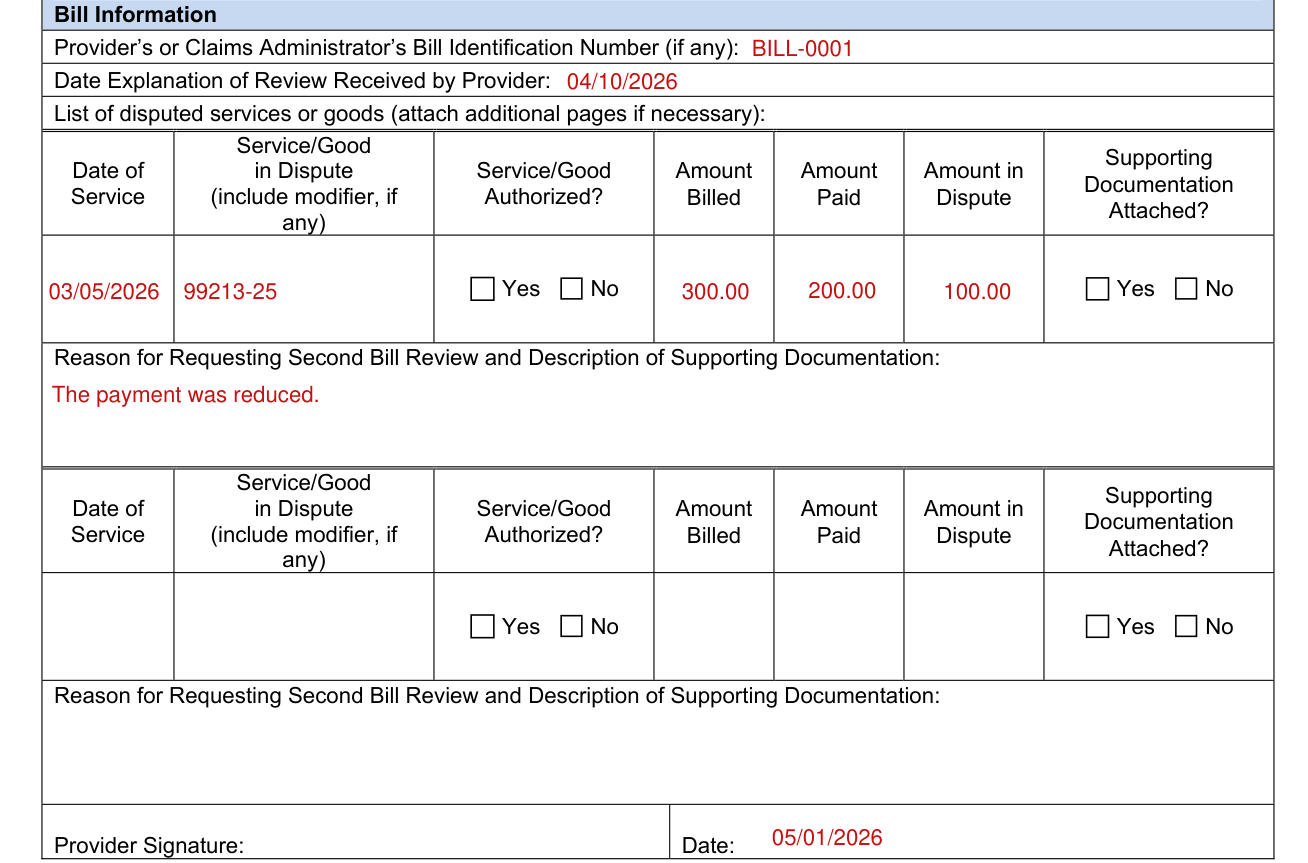
Complete all fields in this section for each disputed service or good, or medical-legal service.
Attach additional pages if necessary. Provide your or the claims administrator's bill identification number, if any. State the date when the explanation of review that either denied or reduced the amount billed was received. State the date of service. State the service or good for which payment is in dispute.
Include the code and modifier, if any. Indicate whether the billed service was authorized. State the amount billed, the amount paid, and the amount in dispute. State whether supporting documentation is attached. (For example, documents provided in response to a request by the claims administrator in the explanation of review.) State the reason for requesting the second bill review and describe the supporting documentation.
Provider signature and date

The Medical Provider signs on the Signature/Date line at the bottom of the form.
More rules for Form SBR-1
The second bill review process must be completed before a provider can seek independent bill review of a billing dispute.
To apply for a second review of a non-electronic medical treatment bill, you can use either this form or a modified standardized bill.
For medical-legal bills, the second review must be on this form.
Common questions about Form SBR-1
Is there a deadline?
When to Apply: A request for second bill review must be made within 90 days of service of the explanation of review that explained why the payment you sought in the initial bill was reduced or denied. If an issue that would preclude your right to receive compensation for the submitted bill is under consideration by the Workers' Compensation Appeal Board (WCAB), you have 90 days from the date of the service of the WCAB order that resolves the issue to request the second bill review.
Is there a penalty?
If the only dispute is the amount of payment and you do not timely request a second bill review, the bill will be considered satisfied and neither the claims administrator nor the employee shall be liable to you for any further payment.
Sources
[1] DWC Form SBR-1 (Effective 2/2014), Provider's Request for Second Bill Review, California Division of Workers' Compensation (the Official source link on this page).