

Form SSA-454-BK at a glance
What it is: The office that reviews your medical condition(s) will use the information you provide in Form SSA-454-BK, the Continuing Disability Review Report, to decide whether you are still disabled.
Where and when to file: Send or bring the completed report to your local field office, or the nearest U.S. embassy or consulate office.
When a question refers to "you" or "your" it refers to the person receiving disability benefits. If you are completing this report for someone else, provide information about them.
A filled-in Form SSA-454-BK example: a person fills out Section 1
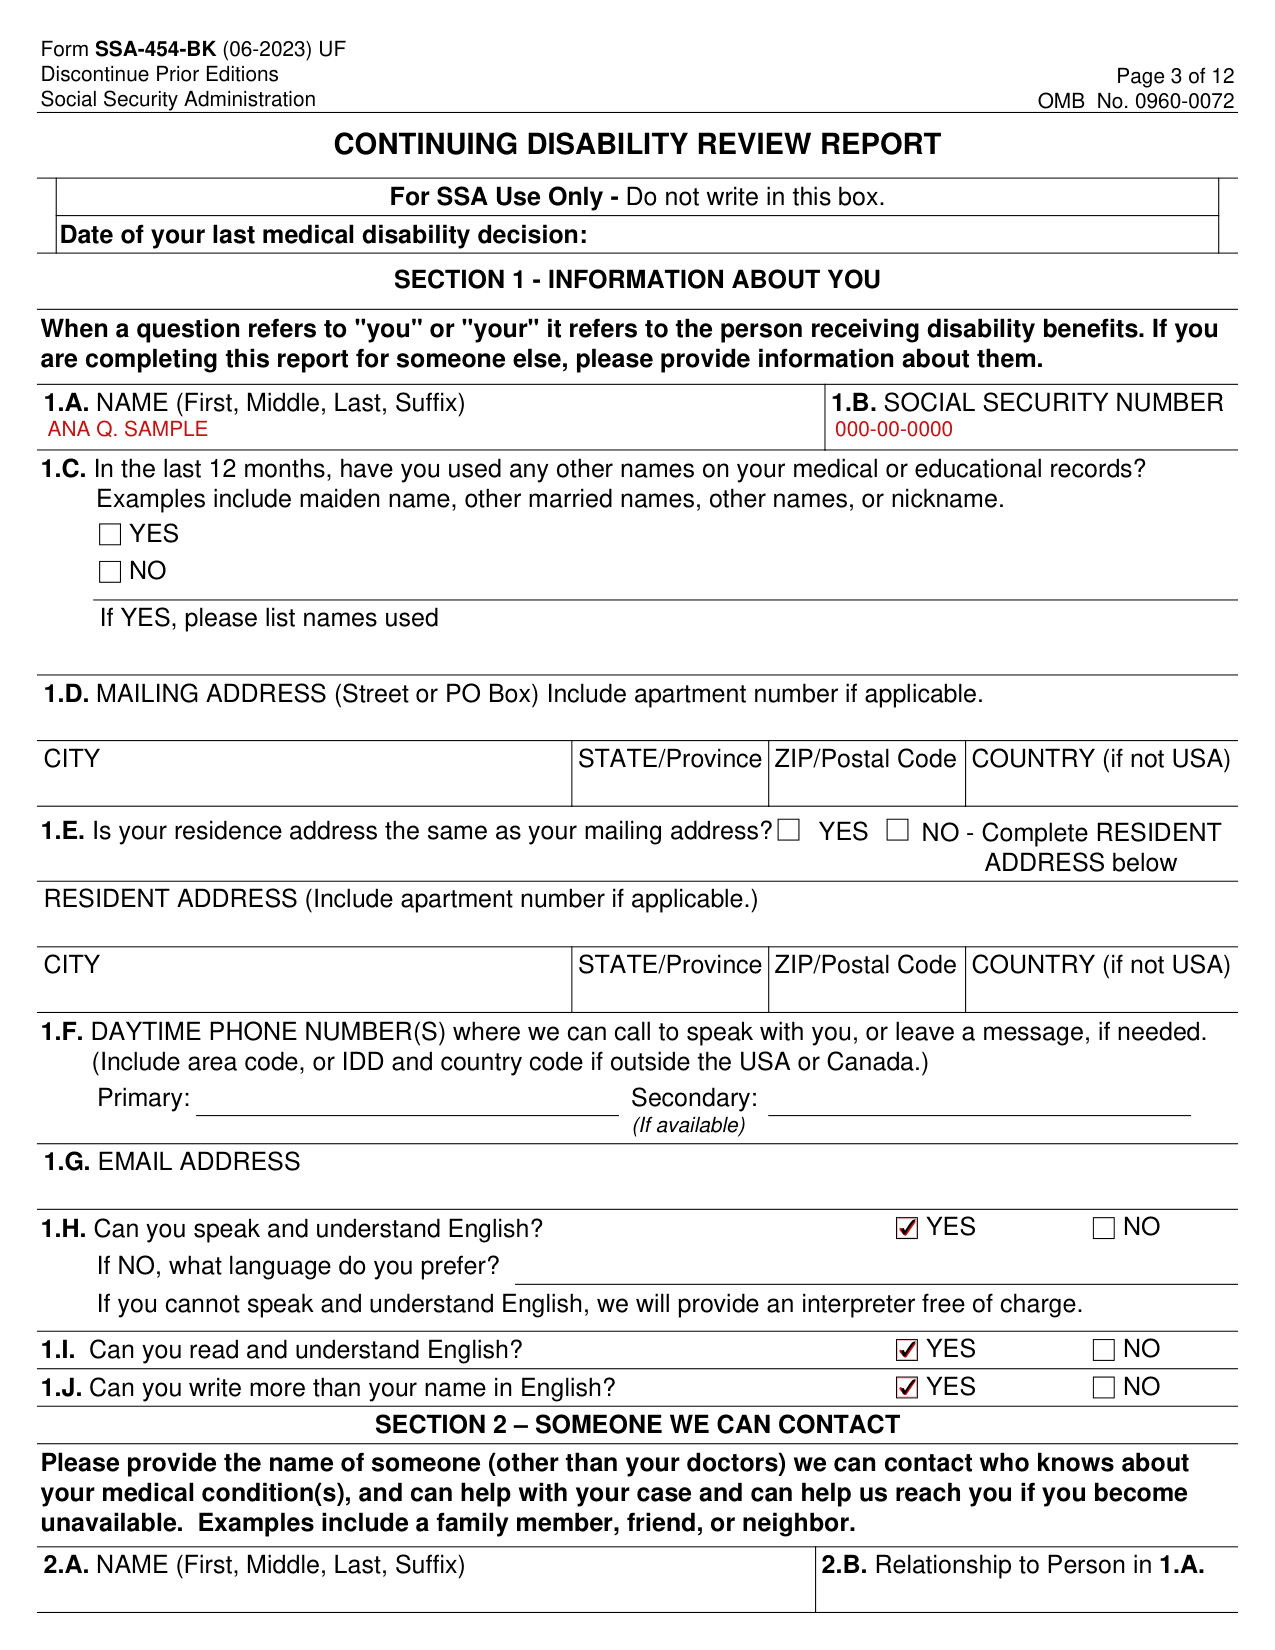
How to fill out Form SSA-454-BK, box by box
Section 1 - Information about you
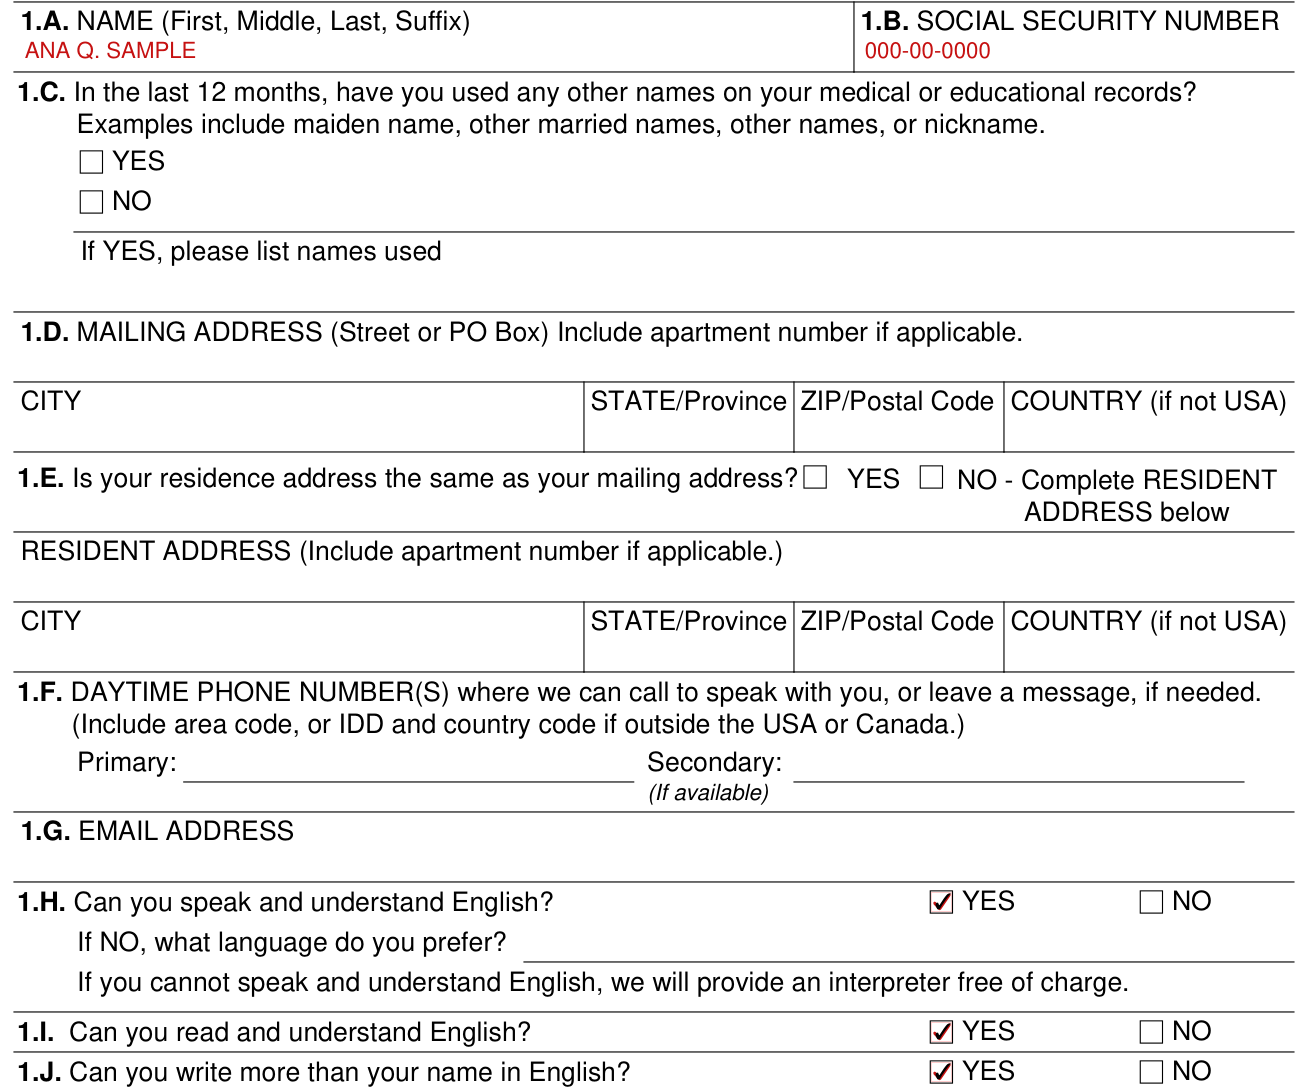
In SECTION 1 - INFORMATION ABOUT YOU, enter your name in 1.A. NAME (First, Middle, Last, Suffix) and your number in 1.B. SOCIAL SECURITY NUMBER.
1.C. In the last 12 months, have you used any other names on your medical or educational records? Examples include maiden name, other married names, other names, or nickname.
1.E. Is your residence address the same as your mailing address? Mark YES, or mark NO and complete the RESIDENT ADDRESS.
In 1.F. enter DAYTIME PHONE NUMBER(S) to speak with you, or leave a message, if needed. Include area code, or IDD and country code if outside the USA or Canada.
1.H. Can you speak and understand English? YES NO If NO, what language do you prefer?
1.I. Can you read and understand English? YES NO 1.J. Can you write more than your name in English? YES NO
Section 2 - Someone we can contact

Section 2: provide the name of someone (other than your doctors) who knows about your medical condition(s), and can help with your case and can help reach you if you become unavailable. Examples include a family member, friend, or neighbor.
Enter 2.A. NAME (First, Middle, Last, Suffix) and 2.B. Relationship to Person in 1.A.
Enter 2.C. MAILING ADDRESS (Street or PO Box). Include apartment number if applicable.
Enter 2.D. DAYTIME PHONE NUMBER, as described in 1.F.
2.E. Can this person speak and understand English? YES NO (If NO, what language is preferred?)
Section 3 - Medical information
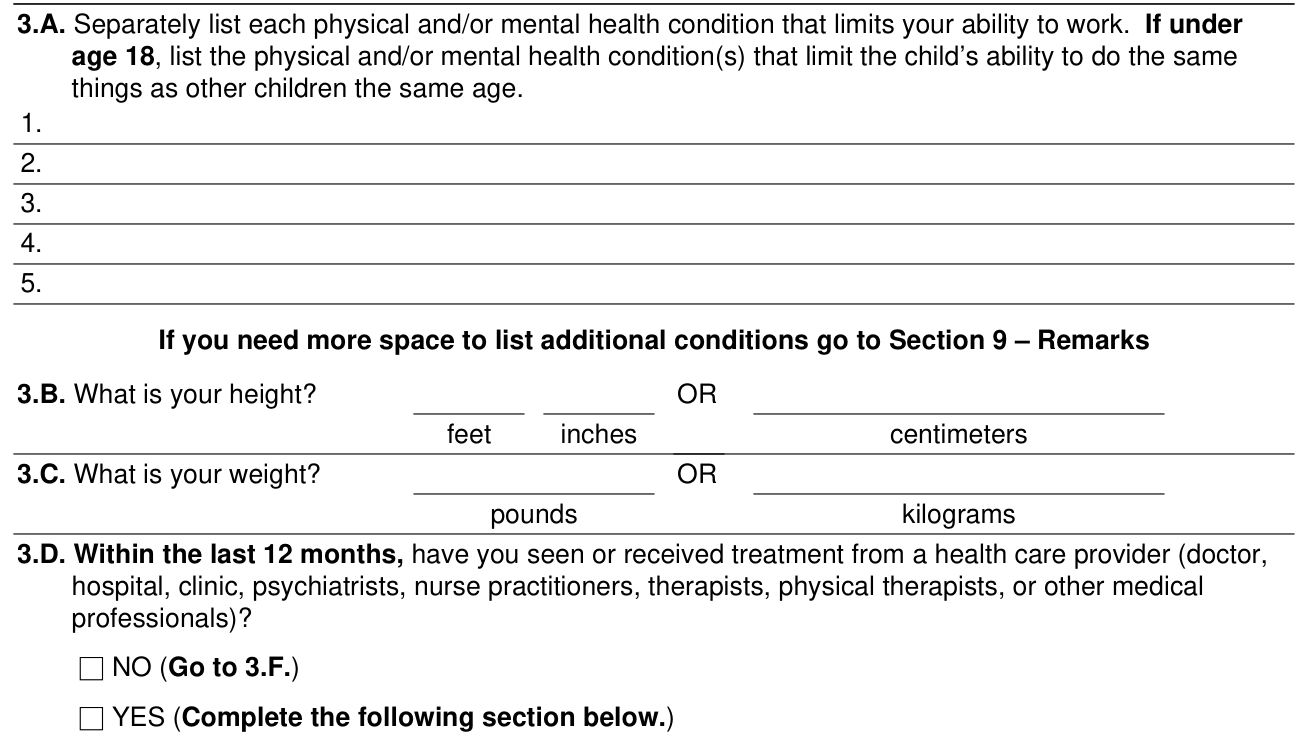
In SECTION 3 - MEDICAL INFORMATION, in 3.A. separately list each physical and/or mental health condition that limits your ability to work. If under age 18, list the physical and/or mental health condition(s) that limit the child's ability to do the same things as other children the same age.
3.B. What is your height? Enter feet inches OR centimeters. 3.C. What is your weight? Enter pounds OR kilograms.
3.D. Within the last 12 months, have you seen or received treatment from a health care provider? NO (Go to 3.F.). YES: fill in each provider.
3.E. Within the last 12 months, did any of the providers listed in 3.D. order any medical tests for you? Include tests already performed and those scheduled in the future. NO (Go to 3.F.). YES: fill in the TEST and the NAME OF HEALTHCARE PROVIDER OR FACILITY. If you need more space, use Section 9 - Remarks.
3.F. Within the last 12 months, have you taken or are you now taking any prescription or non-prescription medicines? Put any side-effects you may have in Section 9 - Remarks. NO (Go to 3.G.). YES: fill in the NAME OF MEDICINE.
3.G. Do you use an assistive device? Even if you do not always use an assistive device at home, if you always use it when outside your home, select "always." NO (Go to Section 3.H.). YES: fill in the DEVICE and its FREQUENCY OF USE.
3.H. Is the person receiving disability benefits listed in 1.A. under age 14? NO (Go to Section 4). YES (Go to Section 10).
Section 4 - Work information

Section 4 - Work information: Complete only if you are age 14 years old or older.
4.A. Since the date of your last medical disability decision have you worked? (See date on top of Page 3.) NO (Go to 4.B.). YES: mark No or Yes for Are you currently working?
Select all types of work you had since your last medical disability decision: Wages from employer, Self-employment.
4.B. Under age 18? NO (Go to Section 5). YES (Go to Section 10).
Section 5 - Support services
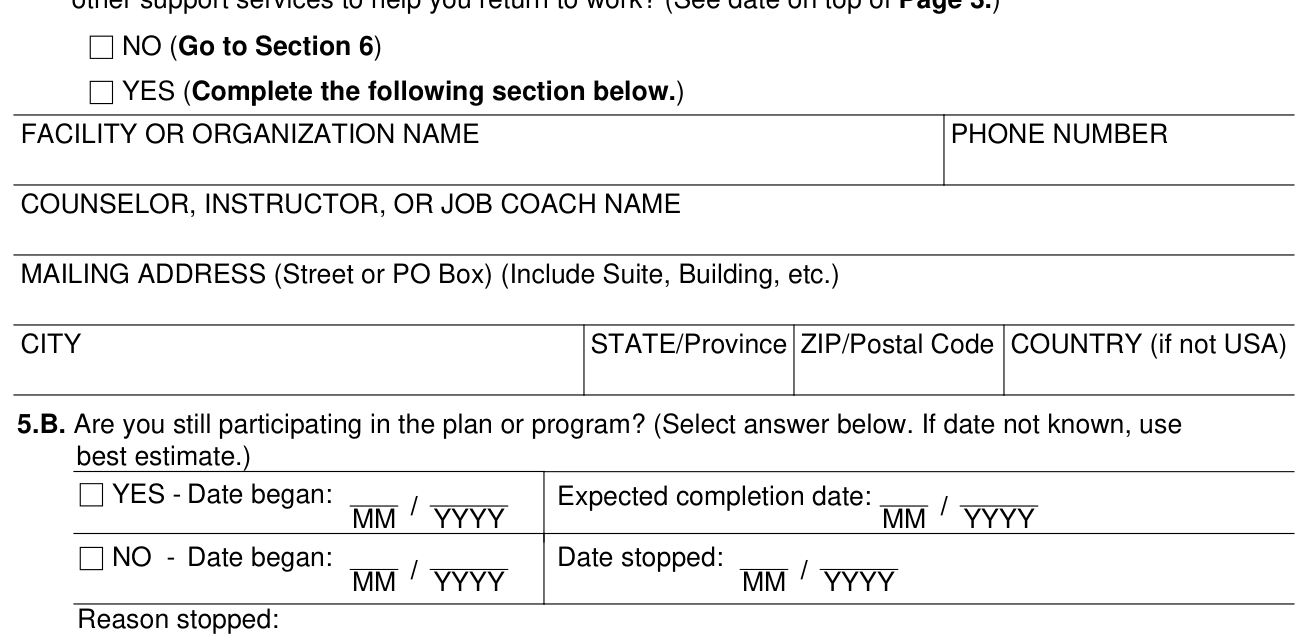
Section 5 - Support services: Complete only if you are age 18 years or older. Please provide the information about your participation in support services.
5.A. Since the date of your last medical disability decision, have you participated or are you participating in any vocational rehabilitation, employment services, or other support services to help you return to work? (See date on top of Page 3.) NO (Go to Section 6). YES: fill in the FACILITY OR ORGANIZATION NAME.
5.B. Are you still participating in the plan or program? YES: enter Date began and Expected completion date. NO: enter Date began, Date stopped and Reason stopped. If date not known, use best estimate.
5.C. What types of services, tests, or evaluation were provided? Select all that apply.
Section 6 - Other medical information

Section 6 - Other medical information: Complete only if you are age 18 years or older.
Provide the contact information for anyone else or any other organization that may have medical information about your physical or mental health condition(s) that you did not list in Questions 3.D. or 5.A.
6. Within the last 12 months, does anyone else (other than your medical providers) have your medical information or are you scheduled to see anyone else? NO (Go to Section 7). YES: fill in the lines.
Section 7 - Education, training, and literacy
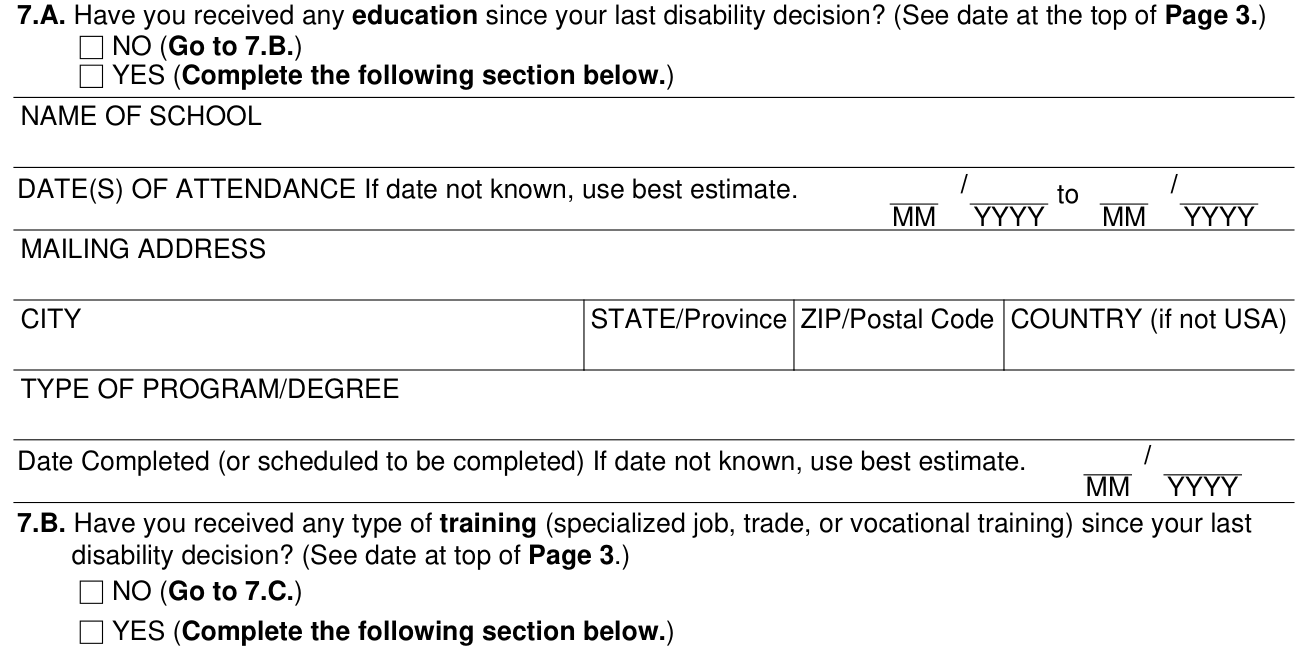
Section 7 - Education, training, and literacy: Complete only if you are age 18 years or older.
7.A. Have you received any education since your last disability decision? (See date at the top of Page 3.) NO (Go to 7.B.). YES: fill in the NAME OF SCHOOL.
7.B. Have you received any type of training (specialized job, trade, or vocational training) since your last disability decision? (See date at top of Page 3.) NO (Go to 7.C.). YES: fill in the NAME OF TRAINING FACILITY.
7.C. What written language do you use every day in most situations (at home, work, school, in community, etc.)?
7.D. READING - In the language you identified in 7.C., can you read a simple message, such as a shopping list or short simple notes? 7.E. WRITING - In the language you identified in 7.C., can you write a simple message, such as a shopping list or short simple notes? YES NO
Section 8 - Daily activities
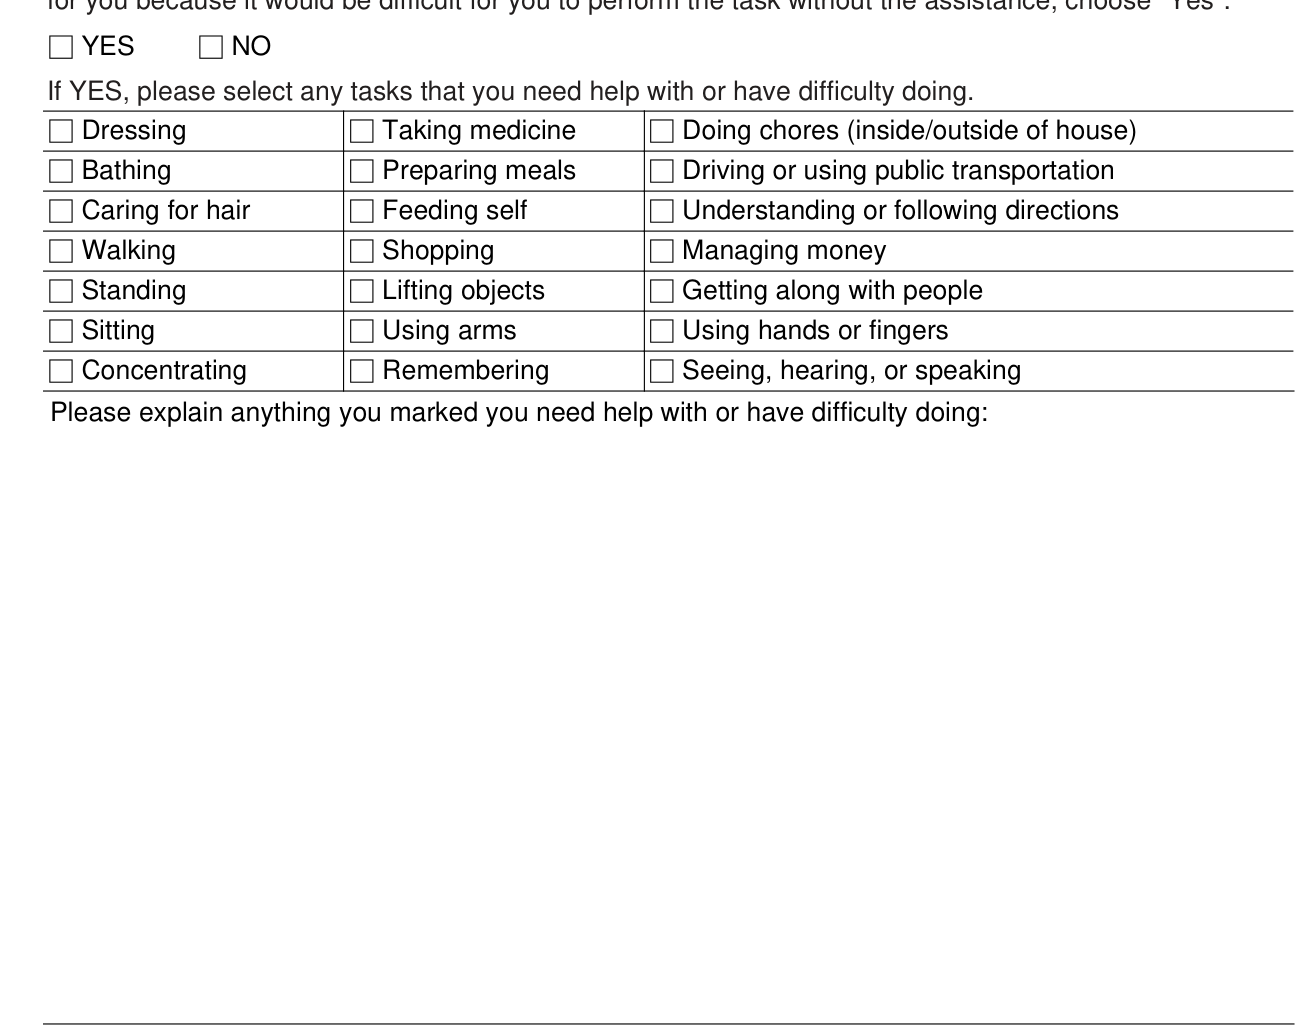
Section 8 - Daily activities: Complete only if you are age 18 years or older.
8. Do your medical conditions cause you to have difficulties doing any of the following? If other people or assistive devices help you perform a task or perform a task for you because it would be difficult for you to perform the task without the assistance, choose "Yes".
If YES, select any tasks that you need help with or have difficulty doing. Explain anything you marked you need help with or have difficulty doing.
Section 9 - Remarks

Section 9 - Remarks: Provide any additional information you did not give in earlier parts of this report. Be sure to note the name of the section (and question number) you are referring to.
Section 10 - Who is completing this report

Section 10 - Who is completing this report: enter the Date Report Completed (month, day, year). Who is completing this report? Mark The person listed in 1.A., The person listed in 2.A., or Someone else.
If Someone else, enter NAME (First, Middle Initial, Last), Relationship to Person in 1.A., DAYTIME PHONE NUMBER to reach you or leave a message, if needed, and MAILING ADDRESS (Street or PO Box). Include apartment number if applicable.
More rules for Form SSA-454-BK
If you cannot complete the report, you may contact the Social Security Administration at 1-800-772-1213 (TTY 1-800-325-0778).
YOU DO NOT NEED TO ASK DOCTORS OR HOSPITALS FOR ANY MEDICAL RECORDS.
ANSWER EVERY QUESTION, unless the report indicates otherwise. If you do not know an answer, or the answer is "none" or "does not apply," please write: "don't know," or "none," or "does not apply." If you need more space to answer any question, please use Section 9 - Remarks. Write the number of the question you are answering.
After completing this report, remove this sheet and keep it for your records.
Common questions about Form SSA-454-BK
Where do I file it?
Send or bring the completed report to your local field office, or the nearest U.S. embassy or consulate office.
Sources
[1] Form SSA-454-BK (06-2023), Continuing Disability Review Report, Social Security Administration (the Official source link on this page).
