


Form TDI-1E at a glance
What it is: Form TDI-1E (09/25) is the Rhode Island Department of Labor and Training's application for benefits for Temporary Disability Insurance (TDI).
Who signs: Sign with Your Signature, Social Security Number and Date.
What to bring and attach to Form TDI-1E
Documentation is required for court-appointed wards and for children over 18 who are incapacitated.
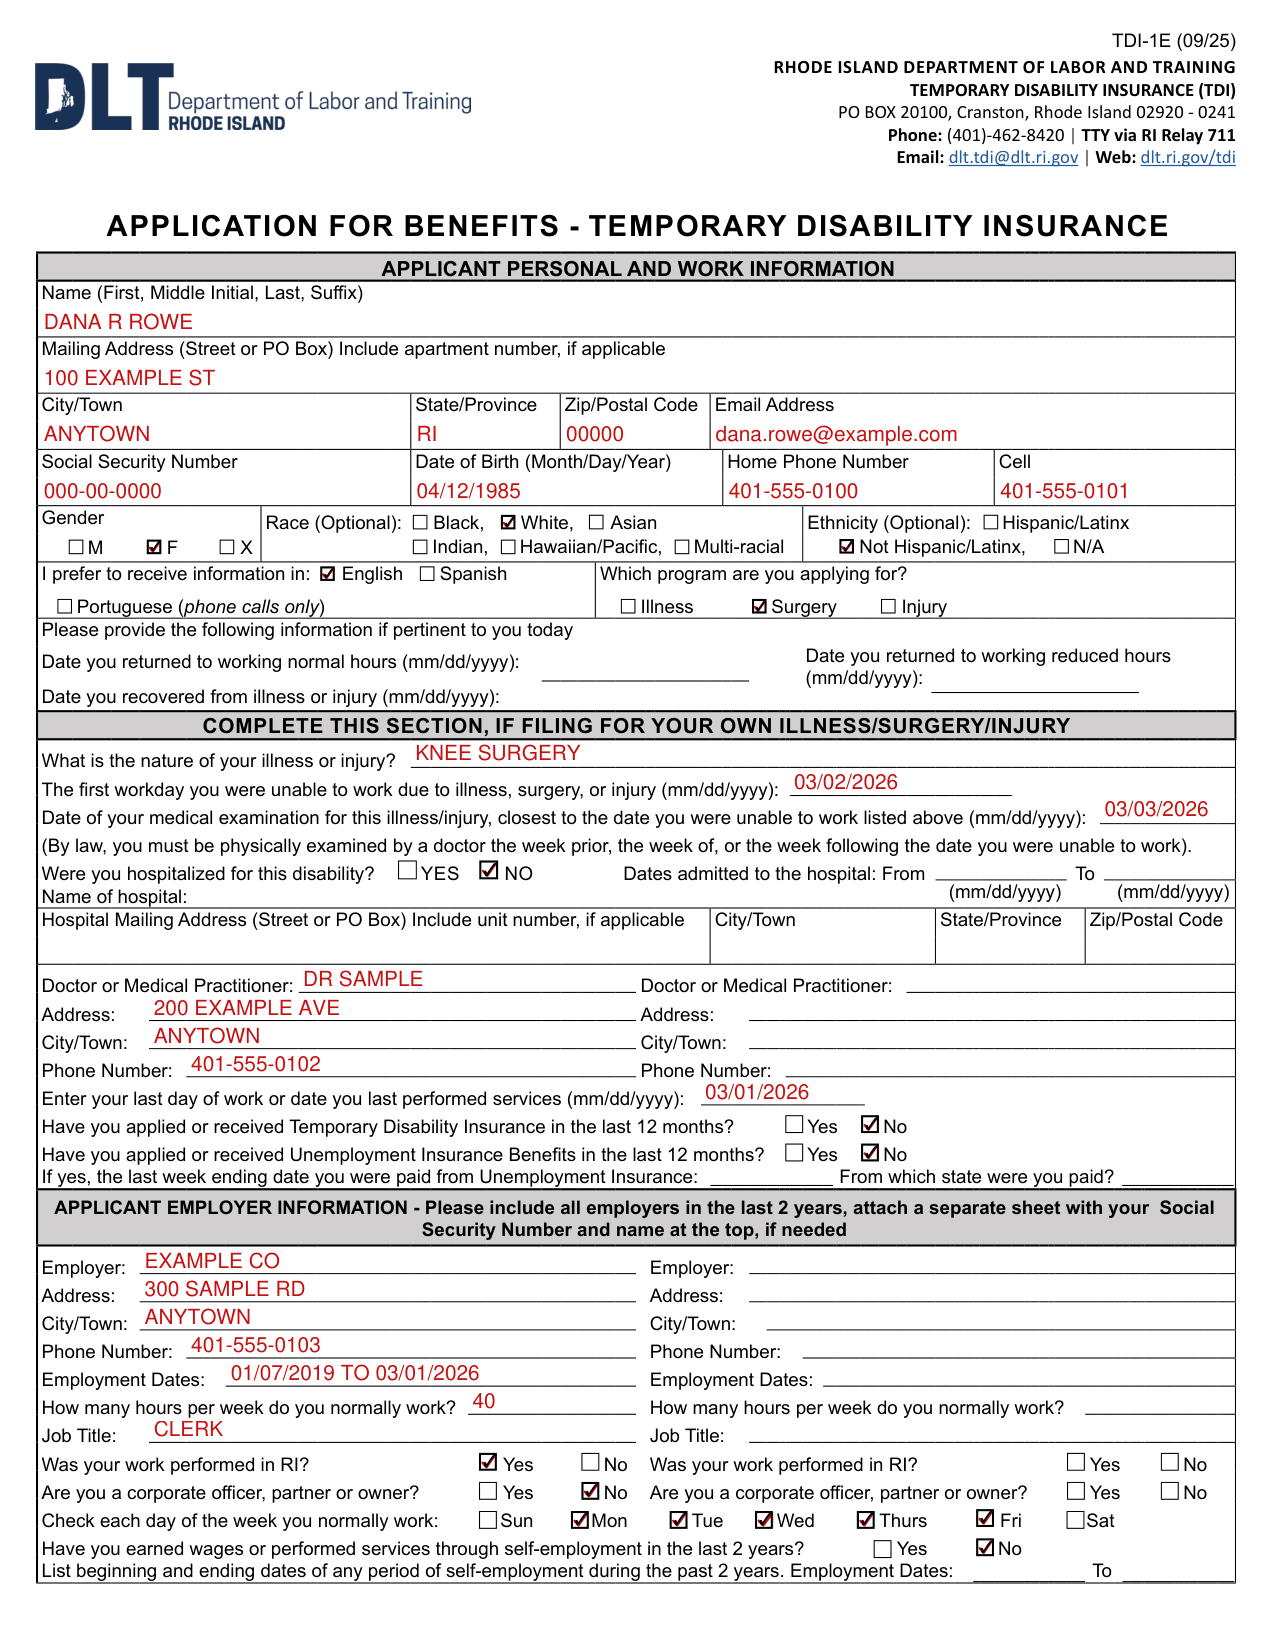
A filled-in Form TDI-1E example: a worker files after her own surgery
How to fill out Form TDI-1E, box by box
Applicant personal and work information

Under APPLICANT PERSONAL AND WORK INFORMATION, enter your Name (First, Middle Initial, Last, Suffix), Mailing Address (Street or PO Box) including the apartment number, if applicable, City/Town, State/Province, Zip/Postal Code, Email Address, Social Security Number, Date of Birth (Month/Day/Year), Home Phone Number and Cell.
Gender, race, ethnicity and program

Mark Gender as M, F or X. Mark Race (Optional) as Black, White, Asian, Indian, Hawaiian/Pacific or Multi-racial. Mark Ethnicity (Optional) as Hispanic/Latinx, Not Hispanic/Latinx or N/A. Mark I prefer to receive information in: English, Spanish or Portuguese (phone calls only). Under Which program are you applying for?, mark Illness, Surgery or Injury. Under Please provide the following information if pertinent to you today, enter the Date you returned to working reduced hours (mm/dd/yyyy) and the Date you returned to working normal hours (mm/dd/yyyy).
Enter the Date you recovered from illness or injury (mm/dd/yyyy).
Your own illness, surgery or injury
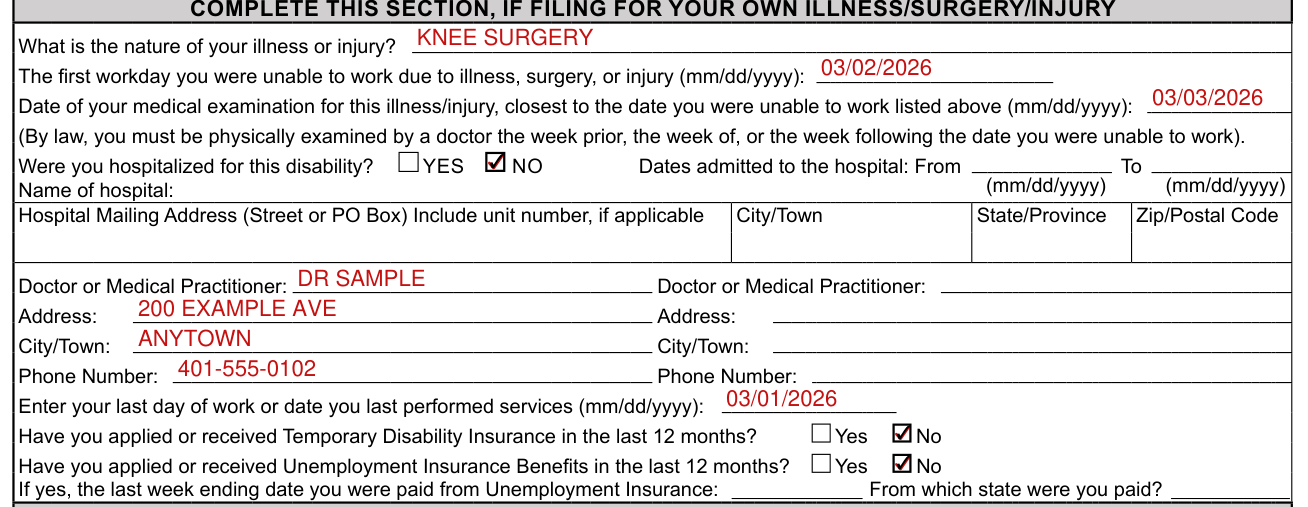
Complete the section marked COMPLETE THIS SECTION, IF FILING FOR YOUR OWN ILLNESS/SURGERY/INJURY if you are filing for your own illness, surgery or injury.
Enter the nature of your illness or injury and the first workday you were unable to work due to illness, surgery, or injury (mm/dd/yyyy).
By law, you must be physically examined by a doctor the week prior, the week of, or the week following the date you were unable to work; enter the date of your medical examination for this illness/injury, closest to the date you were unable to work (mm/dd/yyyy).
For Were you hospitalized for this disability? mark YES or NO, then enter Dates admitted to the hospital From and To (mm/dd/yyyy), Name of hospital and the Hospital Mailing Address (Street or PO Box) including the unit number, if applicable, City/Town, State/Province and Zip/Postal Code.
Enter the Doctor or Medical Practitioner with Address, City/Town and Phone Number.
Your last day of work and Unemployment Insurance

Enter your last day of work or date you last performed services (mm/dd/yyyy).
For Have you applied or received Temporary Disability Insurance in the last 12 months? mark Yes or No.
For Have you applied or received Unemployment Insurance Benefits in the last 12 months? mark Yes or No. If yes, enter the last week ending date you were paid from Unemployment Insurance and From which state were you paid?
Employer information
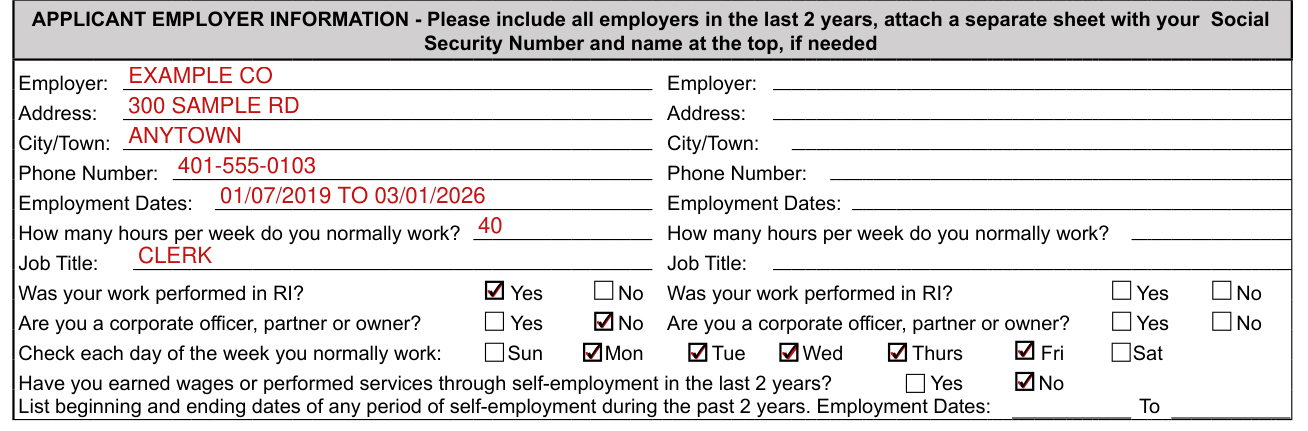
Under APPLICANT EMPLOYER INFORMATION, please include all employers in the last 2 years, and attach a separate sheet with your Social Security Number and name at the top, if needed.
For each employer, enter Employer, Address, City/Town, Phone Number, Employment Dates, How many hours per week do you normally work? and Job Title.
For Was your work performed in RI? mark Yes or No, and for Are you a corporate officer, partner or owner? mark Yes or No, then check each day of the week you normally work: Sun, Mon, Tue, Wed, Thurs, Fri or Sat.
For Have you earned wages or performed services through self-employment in the last 2 years? mark Yes or No, and list beginning and ending dates of any period of self-employment during the past 2 years.
Your dependents allowance
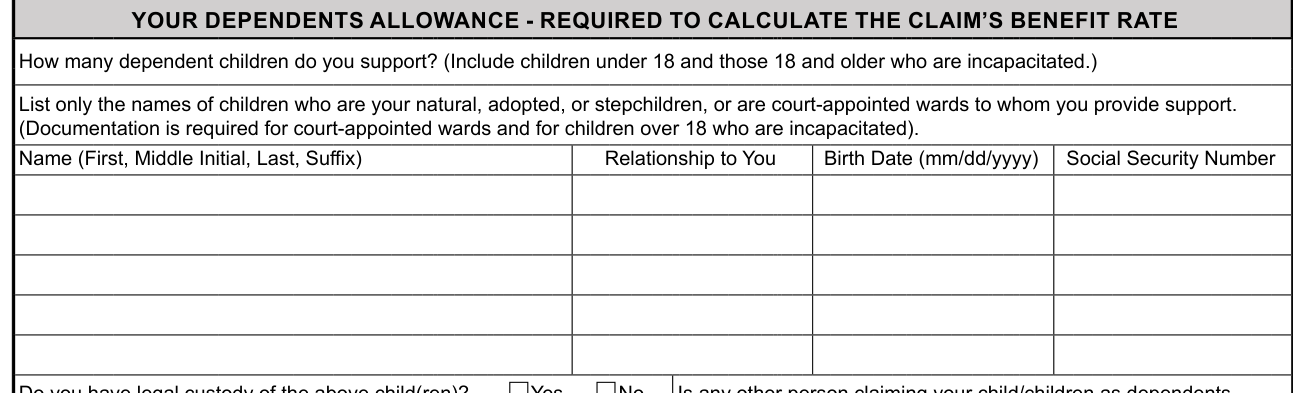
Under YOUR DEPENDENTS ALLOWANCE - REQUIRED TO CALCULATE THE CLAIM'S BENEFIT RATE, enter how many dependent children you support (include children under 18 and those 18 and older who are incapacitated).
List only the names of children who are your natural, adopted, or stepchildren, or are court-appointed wards to whom you provide support, with Name (First, Middle Initial, Last, Suffix), Relationship to You, Birth Date (mm/dd/yyyy) and Social Security Number.
Legal custody, children who live with you and incapacity
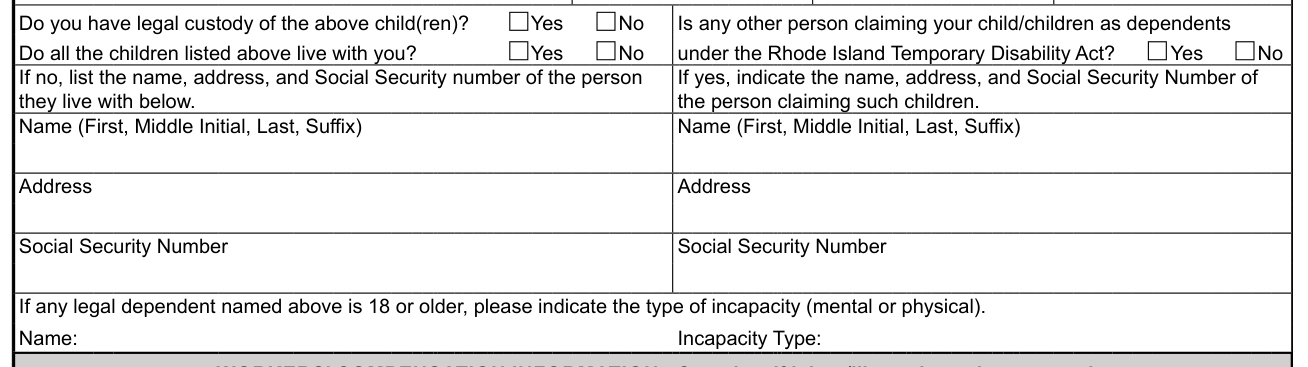
For Do you have legal custody of the child(ren)? mark Yes or No. For Do all the children listed under YOUR DEPENDENTS ALLOWANCE live with you? mark Yes or No. If no, list the name, address, and Social Security number of the person they live with.
For Is any other person claiming your child/children as dependents under the Rhode Island Temporary Disability Act? mark Yes or No. If yes, indicate the name, address, and Social Security Number of the person claiming such children.
If any legal dependent named under YOUR DEPENDENTS ALLOWANCE is 18 or older, please indicate the type of incapacity (mental or physical) with Name and Incapacity Type.
Workers' compensation information

Complete WORKERS' COMPENSATION INFORMATION if injury/illness is work connected, and mark Do you have a job-related illness or Workers' Compensation issue? Yes or No.
For Have you filed a Workers' Compensation claim for this disability or any other disability? mark Yes or No, then enter Date of injury or start of illness (mm/dd/yyyy), Name of company where injury occurred and Address, and mark Have you received any Workers' Compensation payments for this or any other disability? Yes or No. If yes, enter dates From and To and provide the contact information for your Workers' Compensation Company. If no, please explain why not. If you have a lawyer representing you in this matter, please provide his/her name and address: Lawyer Name, Address, City/Town, State and Zip.
Preferred benefit payment method

Under Select your preferred benefit payment method, mark Direct Deposit into my account (Complete the Direct Deposit Form) or Electronic Payment Card - EPC (Works like a debit card, fees may apply if not used properly).
Signature required

Sign with Your Signature, Social Security Number and Date.
Under SIGNATURE REQUIRED, you understand that to claim TDI benefits you are/were physically unable to work, including self-employment, during the period for which you are claiming benefits, and that the information you have provided on this application is true and complete.
You authorize your Qualified Healthcare Provider, hospital, or other health care provider to make available to TDI any medical information, including hospital records, which may be requested.
You are responsible to report to TDI the date that you return to work part-time or full-time to prevent any overpayment of benefits. You are responsible for costs/fees incurred by your QHP for providing medical records to TDI. By signing this acknowledgment, you indicate that you have been informed of the TDI Program requirements in SIGNATURE REQUIRED and understand them.
Sources
[1] Form TDI-1E (09/25), Application for Benefits - Temporary Disability Insurance, Rhode Island Department of Labor and Training (the Official source link on this page).