

Form UBEN 100 at a glance
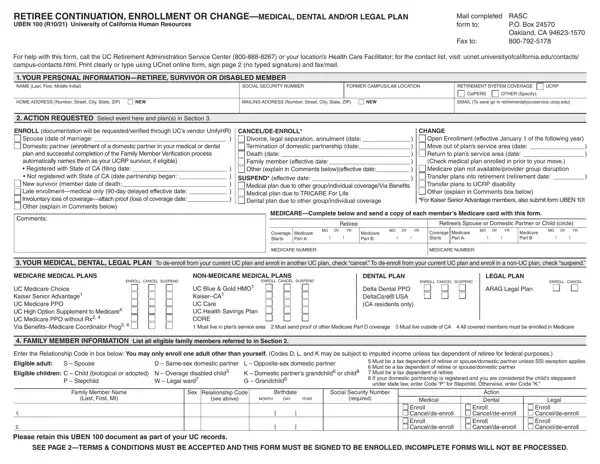
What it is: Retiree Continuation, Enrollment or Change for Medical, Dental and/or Legal Plan, UBEN 100, University of California Human Resources.
Where and when to file: If you have a newly eligible family member as a result of marriage or domestic partnership, birth, adoption, or placement for adoption, you must request enrollment within 31 days after the marriage or partnership, birth, adoption, or placement for adoption.
What to bring and attach to Form UBEN 100
MEDICARE: Complete and send a copy of each member's Medicare card with this form.
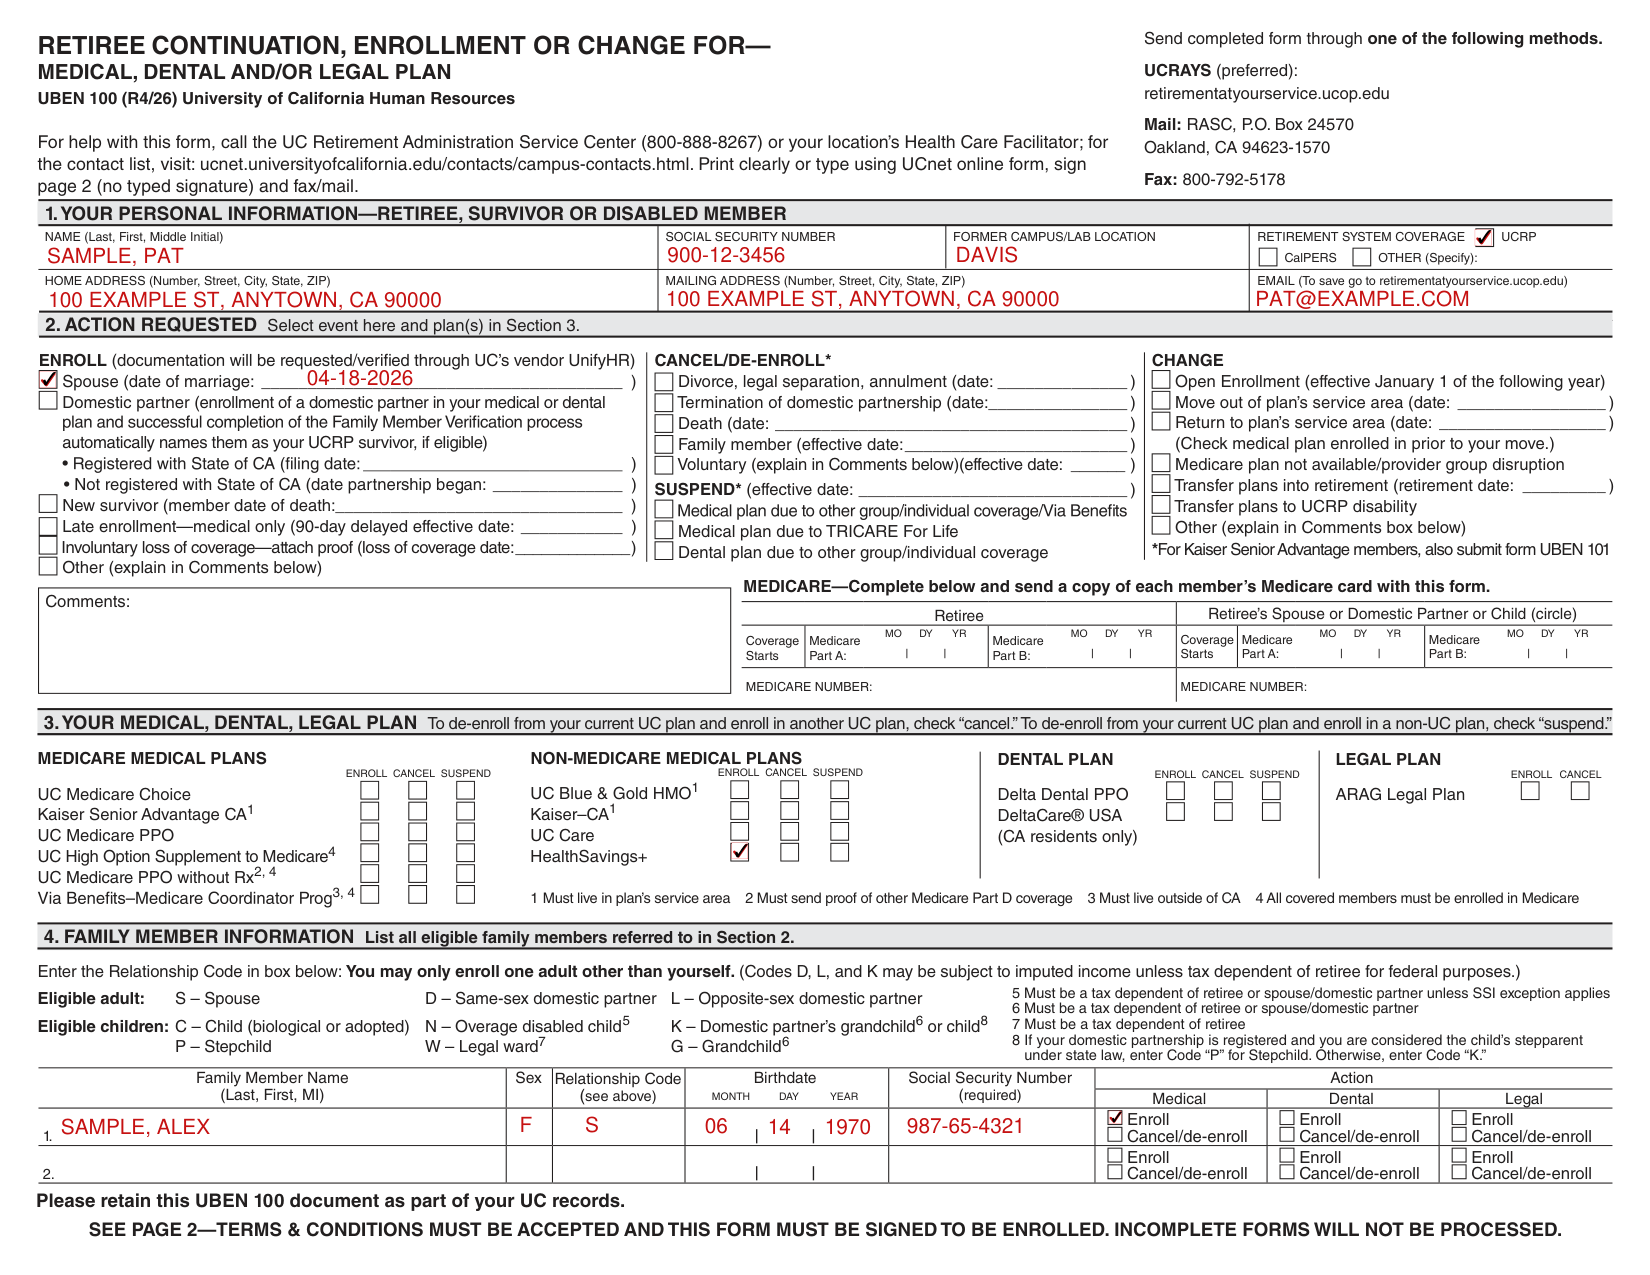
A filled-in Form UBEN 100 example: a retiree enrolls a new spouse
How to fill out Form UBEN 100, box by box
Your personal information

Under 1. Your Personal Information, enter Name (Last, First, Middle Initial), Social Security Number, Former Campus/Lab Location, Retirement System Coverage (UCRP, CalPERS, OTHER (Specify)), Home Address (Number, Street, City, State, ZIP), Mailing Address (Number, Street, City, State, ZIP) and Email.
Your Social Security number, and that of your enrolled family members, is required to verify your identity, and for legally required reporting purposes all in compliance with federal and state laws.
Action requested
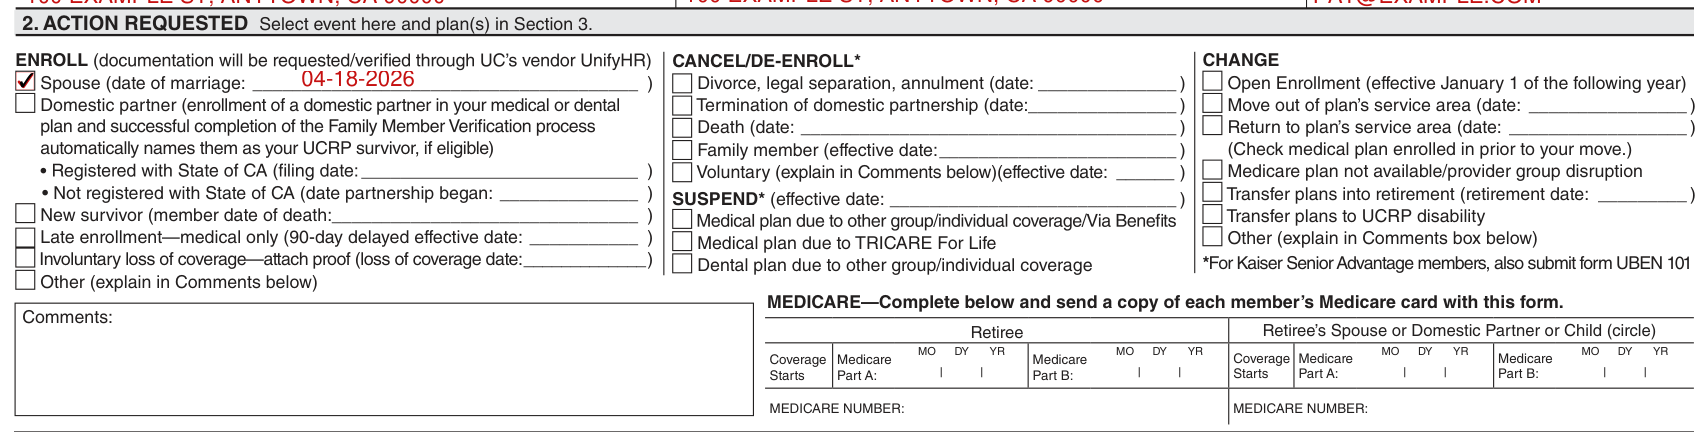
Under 2. ACTION REQUESTED, select the event here and the plan(s) in Section 3.
ENROLL: Spouse (date of marriage), or Domestic partner (enrollment of a domestic partner in your medical or dental automatically names them as your UCRP survivor, if eligible). Also under ENROLL: Not registered with State of CA (date partnership began), New survivor (member date of death), Late enrollment-medical only (90-day delayed effective date), Involuntary loss of coverage-attach proof (loss of coverage date), or Other (explain in Comments).
CANCEL/DE-ENROLL*: Divorce, legal separation, annulment (date), Termination of domestic partnership (date), Death (date), Family member (effective date), Voluntary (explain in Comments)(effective date), or SUSPEND* (effective date).
CHANGE: Move out of plan's service area (date), Return to plan's service area (date) (Check medical plan enrolled in prior to your move.), Medicare plan not available/provider group disruption, Transfer plans into retirement (retirement date), Transfer plans to UCRP disability, Other (explain in Comments box), or Open Enrollment (effective January 1 of the following year).
*For Kaiser Senior Advantage members, also submit form UBEN 101
Medicare

For the Retiree and the Retiree's Spouse or Domestic Partner or Child (circle), enter Coverage Starts for Medicare Part A and Medicare Part B as MO DY YR, and the MEDICARE NUMBER.
Your medical, dental, legal plan
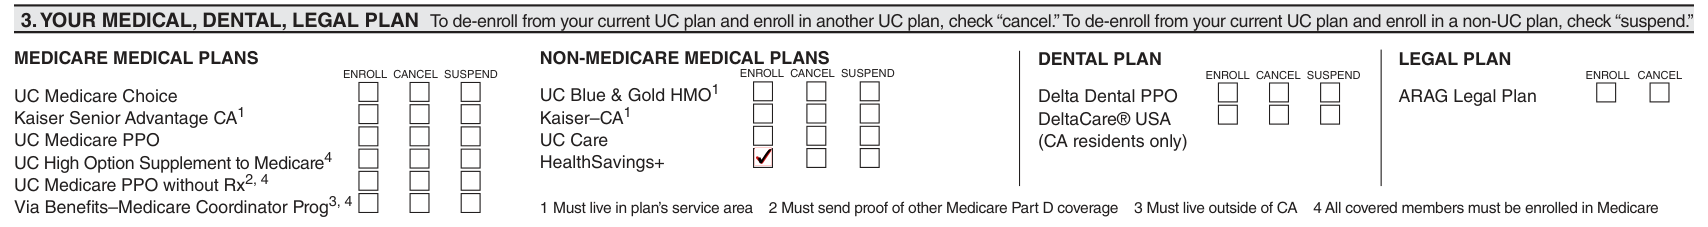
To de-enroll from your current UC plan and enroll in another UC plan, check “cancel.” To de-enroll from your current UC plan and enroll in a non-UC plan, check “suspend.”
Under MEDICARE MEDICAL PLANS or NON-MEDICARE MEDICAL PLANS, check ENROLL, CANCEL or SUSPEND.
Under DENTAL PLAN, check ENROLL, CANCEL or SUSPEND. Under LEGAL PLAN, check ENROLL or CANCEL.
1 Must live in plan's service area 2 Must send proof of other Medicare Part D coverage 3 Must live outside of CA 4 All covered members must be enrolled in Medicare
Family member information
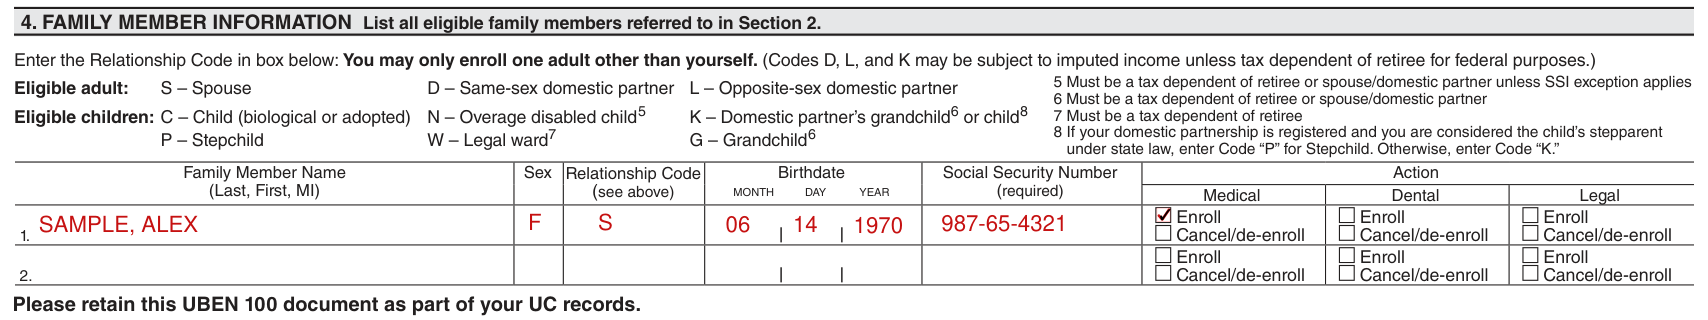
Under 4. FAMILY MEMBER INFORMATION, list all eligible family members referred to in Section 2. You may only enroll one adult other than yourself. (Codes D, L, and K may be subject to imputed income unless tax dependent of retiree for federal purposes.)
Eligible adult: S - Spouse, D - Same-sex domestic partner, L - Opposite-sex domestic partner. Eligible children: C - Child (biological or adopted), N - Overage disabled child5, K - Domestic partner's grandchild6 or child8, P - Stepchild, W - Legal ward7, G - Grandchild6.
5 Must be a tax dependent of retiree or spouse/domestic partner unless SSI exception applies. 6 Must be a tax dependent of retiree or spouse/domestic partner. 7 Must be a tax dependent of retiree. 8 If your domestic partnership is registered and you are considered the child's stepparent under state law, enter Code “P” for Stepchild. Otherwise, enter Code “K.”
For each family member, enter Family Member Name (Last, First, MI), Sex, Relationship Code, Birthdate MONTH DAY YEAR and Social Security Number (required), then check Enroll or Cancel/de-enroll under Action for Medical, Dental or Legal.
If you enroll individuals as your family members you must provide, upon request, documentation verifying that those individuals are eligible for coverage.
Arbitration terms for medical plans

This arbitration agreement applies to: UC Care, HealthSavings+, UC Blue & Gold HMO, UC High Option Supplement to Medicare, UC Medicare PPO, UC Medicare PPO without Prescription Drugs. By checking this box I am electronically signing and accepting the arbitration terms pertaining to all medical plans except Kaiser Foundation Health Plans and Optum Behavioral Health.
This arbitration agreement applies to only the Kaiser Foundation Health Plan. By checking this box and enrolling in a Kaiser Permanente CA health plan, I understand that this action will serve as my electronic signature of agreement to the Kaiser Foundation Health Plan arbitration agreement. If you do not wish to accept the arbitration agreement you must make a different non-Kaiser Health Plan selection.
Signature, date and daytime phone

SIGNATURE OF RETIREE, SURVIVOR OR DISABLED MEMBER (Electronic signatures, e.g., Adobe, DocuSign or Microsoft signatures, are acceptable; not typed.) Then enter DATE and DAYTIME PHONE.
SIGNATURE: I have read, understand and accept the “Participation Terms and Conditions” on this form. By signing you certify under penalty of perjury that the information you provided is true to the best of your knowledge.
More rules for Form UBEN 100
TERMS & CONDITIONS MUST BE ACCEPTED AND THIS FORM MUST BE SIGNED TO BE ENROLLED. INCOMPLETE FORMS WILL NOT BE PROCESSED.
If your enrolled family member loses eligibility for UC-sponsored coverage (for example because of divorce or loss of eligible child status) you must notify UC by de-enrolling that individual.
Making false statements about satisfying eligibility criteria, failing to timely notify UC of a family member's loss of eligibility, or failing to provide documentation when requested may lead to de-enrollment of the affected individuals.
Common questions about Form UBEN 100
Where do I file it?
Send the completed form through one of the following methods: UCRAYS (preferred): retirementatyourservice.ucop.edu Mail: RASC, P.O. Box 24570, Oakland, CA 94623-1570. Fax: 800-792-5178. For help with this form, call the UC Retirement Administration Service Center (800-888-8267) or your location's Health Care Facilitator. Print clearly or type using UCnet online form, sign page 2 (no typed signature) and fax/mail.
Is there a penalty?
You are also certifying under penalty of perjury that all the information you provide regarding the individuals you enroll is true to the best of your knowledge.
Where to get help with Form UBEN 100
To request special enrollment or obtain more information, retirees should call the UC Retirement Administration Service Center (800-888-8267).
Sources
[1] Form UBEN 100 (R4/26), Retiree Continuation, Enrollment or Change, University of California Human Resources (the Official source link on this page).