


Form WH-380-E at a glance
What it is: Form WH-380-E is the U.S. Department of Labor Wage and Hour Division Certification of Health Care Provider for Employee's Serious Health Condition under the Family and Medical Leave Act.
Who signs: The health care provider signs on the Signature of Health Care Provider line and writes the Date as mm/dd/yyyy.
Where and when to file: Do not send the completed form to the Department of Labor; return it to the patient.
The Family and Medical Leave Act (FMLA) provides that an employer may require an employee seeking FMLA protections because of a need for leave due to a serious health condition to submit a medical certification issued by the employee's health care provider. 29 U.S.C. §§ 2613, 2614(c)(3); 29 C.F.R. § 825.305. The employer must give the employee at least 15 calendar days to provide the certification. If the employee fails to provide complete and sufficient medical certification, his or her FMLA leave request may be denied. 29 C.F.R. § 825.313.
Your patient has requested leave under the FMLA. Please provide your contact information, complete all relevant parts of this Section, and sign the form. For FMLA purposes, a “serious health condition” means an illness, injury, impairment, or physical or mental condition that involves inpatient care or continuing treatment by a health care provider. For more information about the definitions of a serious health condition under the FMLA, see the chart on page 4.
A filled-in Form WH-380-E example: a doctor completes Part A for a patient with asthma

How to fill out Form WH-380-E, box by box
SECTION I - EMPLOYER
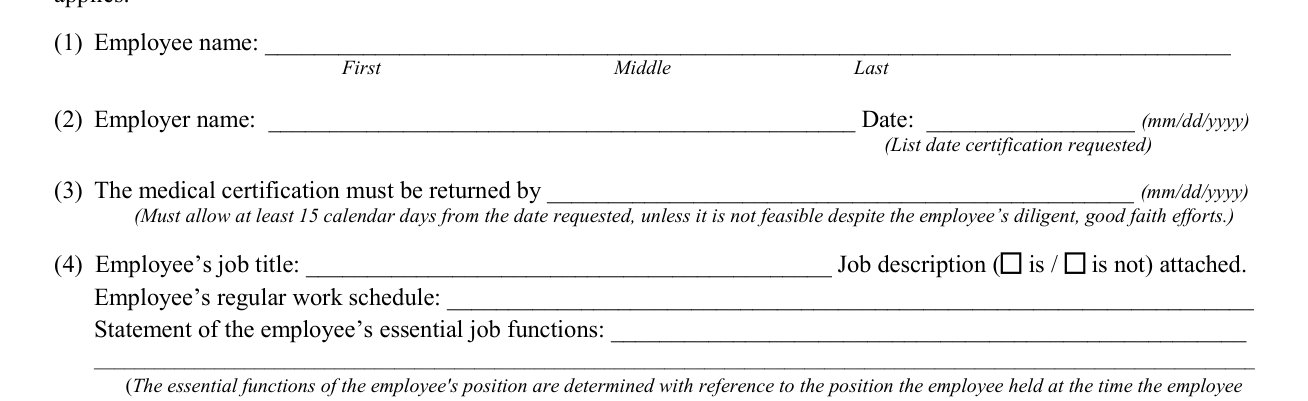
In (1) Employee name, write the employee's name as First, Middle and Last.
In (2) Employer name, write the employer name, and in Date list the date certification requested as mm/dd/yyyy.
In (3), enter the date as mm/dd/yyyy by which the medical certification must be returned, which must allow at least 15 calendar days from the date requested, unless it is not feasible despite the employee's diligent, good faith efforts.
In (4), write the employee's job title, mark the job description as is or is not attached, and write the employee's regular work schedule and the statement of the employee's essential job functions.
Health Care Provider's name, business address, type of practice, telephone, fax and e-mail

Write the Health Care Provider's name (Print), business address, type of practice / medical specialty, telephone, fax and e-mail.
You may, but are not required to, provide other appropriate medical facts including symptoms, diagnosis, or any regimen of continuing treatment such as the use of specialized equipment.
In Part A, limit your response to the medical condition(s) for which the employee is seeking FMLA leave. After completing Part A, complete Part B to provide information about the amount of leave needed.
(1) Approximate date the condition started and (2) how long it lasted

In (1), state the approximate date the condition started or will start, as mm/dd/yyyy.
In (2), provide your best estimate of how long the condition lasted or will last.
(3) Check the box(es) for the questions below, as applicable

In (3), check the box(es) for the questions as applicable; for all box(es) checked, the amount of leave needed must be provided in Part B.
Inpatient Care: the patient has been or is expected to be admitted for an overnight stay in a hospital, hospice, or residential medical care facility on the following date(s).
Incapacity plus Treatment: (e.g. outpatient surgery, strep throat) due to the condition, the patient has been or is expected to be incapacitated for more than three consecutive, full calendar days from mm/dd/yyyy to mm/dd/yyyy.
List the date(s) the patient was or will be seen; mark one: the condition has or has not also resulted in a course of continuing treatment under the supervision of a health care provider.
Pregnancy: if the condition is pregnancy, list the expected delivery date as mm/dd/yyyy.
Chronic Conditions: (e.g. asthma, migraine headaches) check this box when, due to the condition, it is medically necessary for the patient to have treatment visits at least twice per year.
Permanent or Long Term Conditions: check this box when, due to the condition, incapacity is permanent or long term and requires the continuing supervision of a health care provider, even if active treatment is not being provided.
Conditions requiring Multiple Treatments: (e.g. chemotherapy treatments, restorative surgery) check this box when, due to the condition, it is medically necessary for the patient to receive multiple treatments.
If none of the above condition(s) were checked, (i.e., inpatient care, pregnancy) no additional information is needed; go to page 4 to sign and date the form.
PART B: Amount of Leave Needed

In Part B, for the medical condition(s) checked in Part A, complete all that apply. Your answer should be your best estimate based upon your medical knowledge, experience, and examination of the patient. Be as specific as you can; terms such as “lifetime,” “unknown,” or “indeterminate” may not be sufficient to determine FMLA coverage.
In (4), if needed, briefly describe other appropriate medical facts related to the condition(s) for which the employee seeks FMLA leave, such as use of nebulizer or dialysis.
In (5), due to the condition, the patient had or will have planned medical treatment(s) (scheduled medical visits) (e.g. psychotherapy, prenatal appointments) on the following date(s).
In (6), due to the condition, the patient was or will be referred to other health care provider(s) for evaluation or treatment(s). State the nature of such treatments (e.g. cardiologist, physical therapy). Provide your best estimate of the beginning date and end date as mm/dd/yyyy. Provide your best estimate of the duration of the treatment(s), including any period(s) of recovery (e.g. 3 days/week).
In (7), due to the condition, it is medically necessary for the employee to work a reduced schedule. Provide your best estimate of the reduced schedule the employee is able to work, from and to mm/dd/yyyy (e.g., 5 hours/day, up to 25 hours a week).
In (8), due to the condition, the patient was or will be incapacitated for a continuous period of time, including any time for treatment(s) and/or recovery, and provide your best estimate of the beginning date and end date for the period of incapacity as mm/dd/yyyy.
In (9), due to the condition, it was, is or will be medically necessary for the employee to be absent from work on an intermittent basis (periodically), including for any episodes of incapacity. Provide your best estimate of how often (frequency) and how long (duration) the episodes of incapacity will likely last. Over the next 6 months, episodes of incapacity are estimated to occur the entered number of times per day, week or month and are likely to last approximately the entered number of hours or days per episode.
PART C: Essential Job Functions and SIGN

In Part C, if provided, the information in Section I question #4 may be used to answer this question.
In (10), due to the condition the employee was not able, is not able or will not be able to perform one or more of the essential job function(s), and identify at least one essential job function the employee is not able to perform.
The health care provider signs on the Signature of Health Care Provider line and writes the Date as mm/dd/yyyy.
If your situation is different
Incapacity Plus Treatment: a period of incapacity of more than three consecutive, full calendar days
Incapacity Plus Treatment is a period of incapacity of more than three consecutive, full calendar days, and any subsequent treatment or period of incapacity relating to the same condition, that also involves either: two or more in-person visits to a health care provider for treatment within 30 days of the first day of incapacity unless extenuating circumstances exist. The first visit must be within seven days of the first day of incapacity. Or, at least one in-person visit to a health care provider for treatment within seven days of the first day of incapacity, which results in a regimen of continuing treatment under the supervision of the health care provider.
Common questions about Form WH-380-E
Where do I file it?
Do not send the completed form to the Department of Labor; return it to the patient.
When is this form not the right one?
Either the employee or the employer may complete Section I. While use of this form is optional, this form asks the health care provider for the information necessary for a complete and sufficient medical certification, which is set out at 29 C.F.R. § 825.306. You may not ask the employee to provide more information than allowed under the FMLA regulations, 29 C.F.R. §§ 825.306-825.308. Additionally, you may not request a certification for FMLA leave to bond with a healthy newborn child or a child placed for adoption or foster care.
Sources
[1] Form WH-380-E (Revised June 2020), Certification of Health Care Provider for Employee's Serious Health Condition, U.S. Department of Labor Wage and Hour Division (the Official source link on this page).