


Form WH-380-F at a glance
What it is: This form is the Certification of Health Care Provider for Family Member's Serious Health Condition under the Family and Medical Leave Act of the U.S. Department of Labor Wage and Hour Division.
Who signs: Sign on the Employee Signature line and enter the Date in mm/dd/yyyy. Sign on the Signature of Health Care Provider line and enter the Date in mm/dd/yyyy.
The Family and Medical Leave Act (FMLA) provides that an employer may require an employee seeking FMLA leave to care for a family member with a serious health condition to submit a medical certification issued by the family member's health care provider.
A filled-in Form WH-380-F example: an employee completes Section II

How to fill out Form WH-380-F, box by box
Section I: employee name, employer name, date and return date

Either the employee or the employer may complete Section I. While use of this form is optional, this form asks the health care provider for the information necessary for a complete and sufficient medical certification, which is set out at 29 C.F.R. § 825.306. You may not ask the employee to provide more information than allowed under the FMLA regulations, 29 C.F.R. §§ 825.306-825.308. Additionally, you may not request a certification for FMLA leave to bond with a healthy newborn child or a child placed for adoption or foster care.
Enter the employee name as First, Middle and Last.
Enter the employer name and the date, in mm/dd/yyyy, the certification was requested.
Enter the date the medical certification must be returned by, in mm/dd/yyyy. It must allow at least 15 calendar days from the date requested, unless it is not feasible despite the employee's diligent, good faith efforts.
Section II: family member and relationship
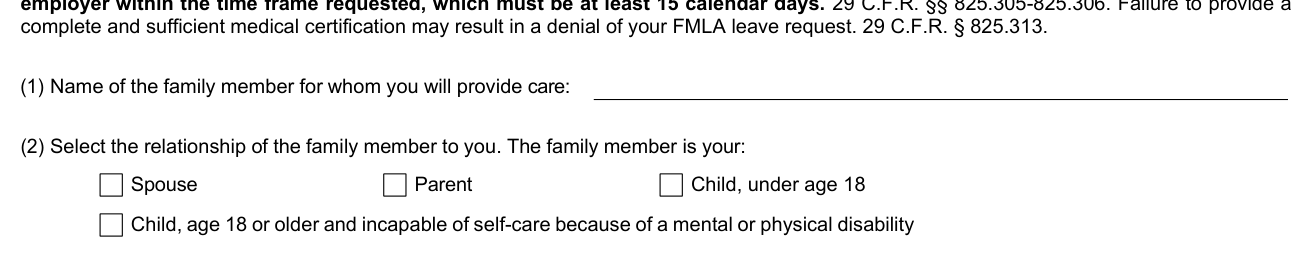
Enter the name of the family member for whom you will provide care.
Select the relationship of the family member to you: Spouse, Parent, Child, under age 18, or Child, age 18 or older and incapable of self-care because of a mental or physical disability.
Care you will provide

Check all that apply to briefly describe the care you will provide to your family member: Assistance with basic medical, hygienic, nutritional, or safety needs, Transportation, Physical Care, Psychological Comfort, or Other.
Amount of leave needed

Give your best estimate of the amount of leave needed to provide the care described.
Reduced work schedule
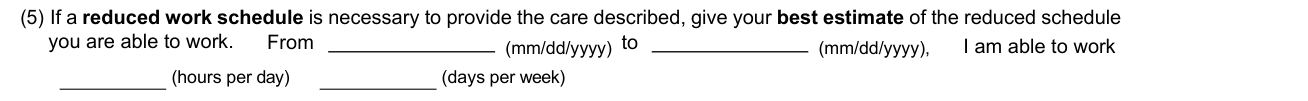
If a reduced work schedule is necessary to provide the care described, give your best estimate of the reduced schedule you are able to work, from (mm/dd/yyyy) to (mm/dd/yyyy), in hours per day and days per week.
Employee signature and date

Sign on the Employee Signature line and enter the Date in mm/dd/yyyy.
Section III: health care provider information
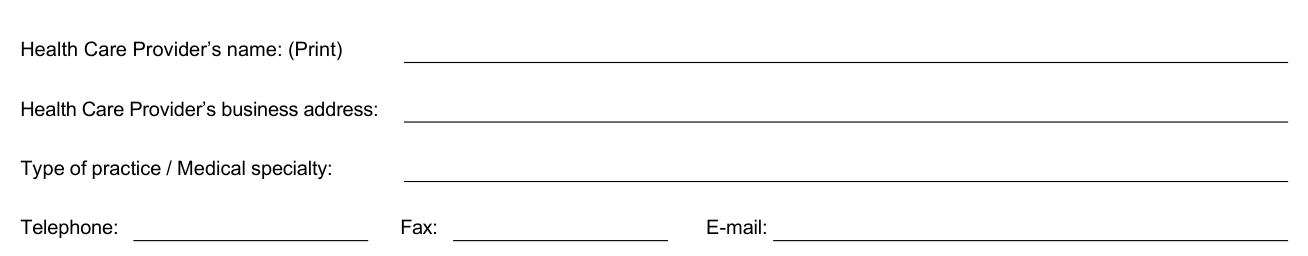
Provide your contact information, complete all relevant parts of this Section, and sign the form.
Enter the Health Care Provider's name (Print), business address, type of practice / medical specialty, telephone, fax and e-mail.
Part A: patient and condition

Limit your response to the medical condition for which the employee is seeking FMLA leave. Your answers should be your best estimate based upon your medical knowledge, experience, and examination of the patient.
(1) Patient's Name: (2) State the approximate date the condition started or will start: (mm/dd/yyyy) (3) Provide your best estimate of how long the condition lasted or will last:
(4) For FMLA to apply, care of the patient must be medically necessary. Briefly describe the type of care needed by the patient (e.g., assistance with basic medical, hygienic, nutritional, safety, transportation needs, physical care, or psychological comfort).
Part A: check the box that applies
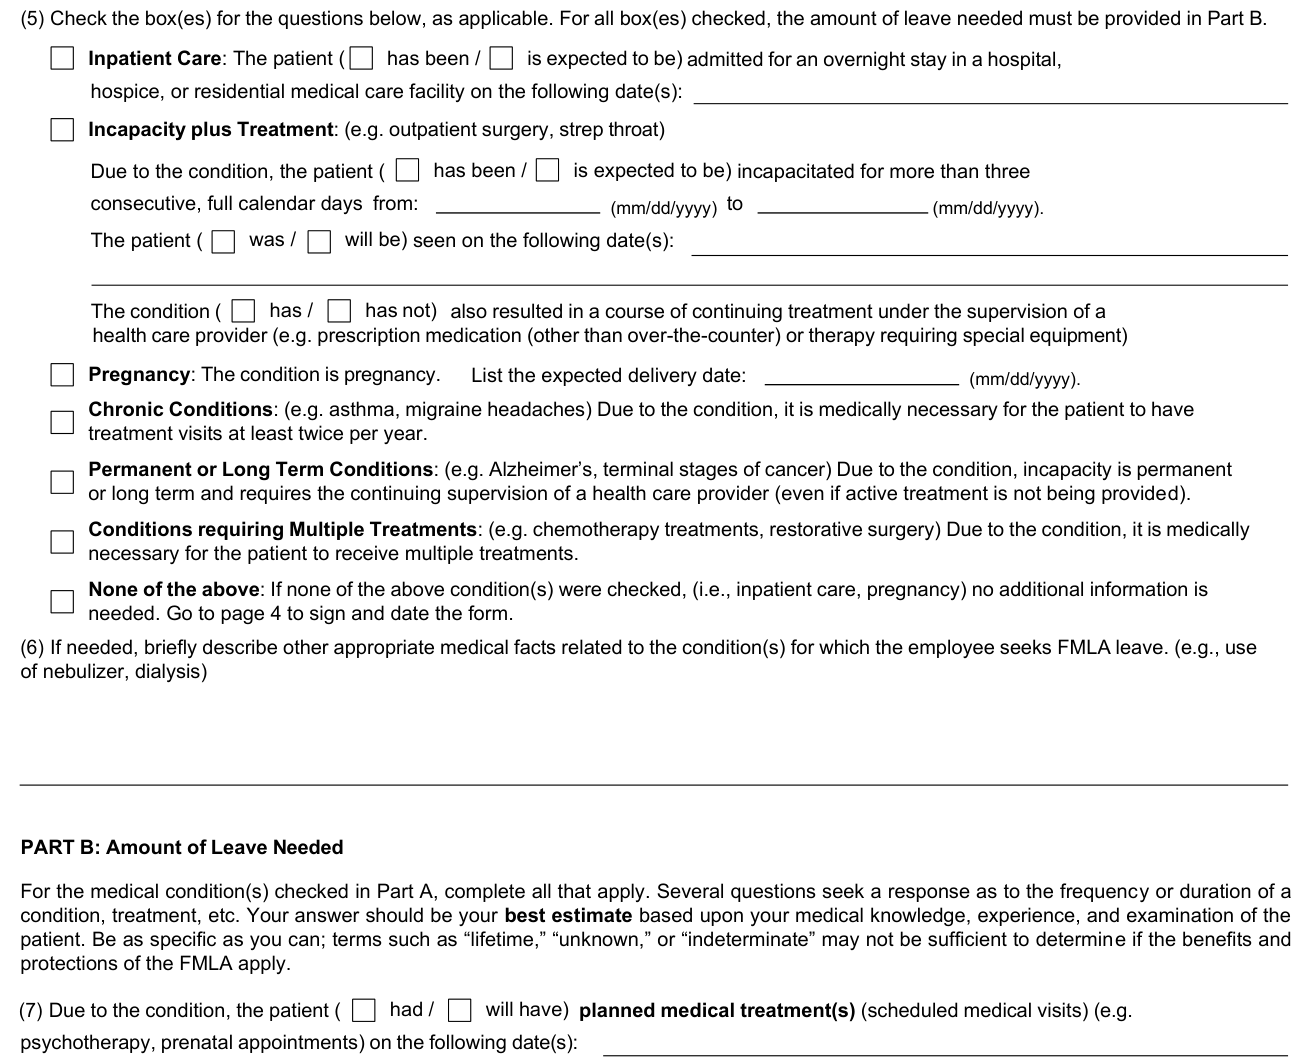
(5) Check the box(es) for the questions, as applicable. For all box(es) checked, the amount of leave needed must be provided in Part B.
Inpatient Care: The patient ( has been / is expected to be) admitted for an overnight stay in a hospital, hospice, or residential medical care facility on the following date(s):
Incapacity plus Treatment: (e.g. outpatient surgery, strep throat) Due to the condition, the patient ( has been / is expected to be) incapacitated for more than three consecutive, full calendar days from: (mm/dd/yyyy) to (mm/dd/yyyy). The patient ( was / will be) seen on the following date(s): The condition ( has / has not) also resulted in a course of continuing treatment under the supervision of a health care provider (e.g. prescription medication (other than over-the-counter) or therapy requiring special equipment)
Pregnancy: The condition is pregnancy. List the expected delivery date: (mm/dd/yyyy).
Chronic Conditions: (e.g. asthma, migraine headaches) Due to the condition, it is medically necessary for the patient to have treatment visits at least twice per year.
Permanent or Long Term Conditions: (e.g. Alzheimer's, terminal stages of cancer) Due to the condition, incapacity is permanent or long term and requires the continuing supervision of a health care provider (even if active treatment is not being provided).
Conditions requiring Multiple Treatments: (e.g. chemotherapy treatments, restorative surgery) Due to the condition, it is medically necessary for the patient to receive multiple treatments.
None of the boxes: If none of the condition(s) were checked, (i.e., inpatient care, pregnancy) no additional information is needed. Go to page 4 to sign and date the form.
(6) If needed, briefly describe other appropriate medical facts related to the condition(s) for which the employee seeks FMLA leave. (e.g., use of nebulizer, dialysis)
Signature of Health Care Provider

Sign on the Signature of Health Care Provider line and enter the Date in mm/dd/yyyy.
More rules for Form WH-380-F
Employers must generally maintain records and documents relating to medical information, medical certifications, recertifications, or medical histories of employees or employees' family members created for FMLA purposes as confidential medical records in separate files/records from the usual personnel files and in accordance with 29 C.F.R. § 1630.14(c)(1), if the Americans with Disabilities Act applies, and in accordance with 29 C.F.R. § 1635.9, if the Genetic Information Nondiscrimination Act applies.
For FMLA purposes, a “serious health condition” means an illness, injury, impairment, or physical or mental condition that involves inpatient care or continuing treatment by a health care provider.
Some state or local laws may not allow disclosure of private medical information about the patient's serious health condition, such as providing the diagnosis and/or course of treatment.
Common questions about Form WH-380-F
What is a WH-380-F form?
This form is the Certification of Health Care Provider for Family Member's Serious Health Condition under the Family and Medical Leave Act of the U.S. Department of Labor Wage and Hour Division. A family member of your patient has requested leave under the FMLA to care for your patient.
Is there a deadline?
The employer must give the employee at least 15 calendar days to provide the certification.
Where do I file it?
Do not send the completed form to the Department of Labor. Return it to the patient. Please complete and sign Section II before providing this form to your family member or your family member's health care provider. The FMLA allows an employer to require that you submit a timely, complete, and sufficient medical certification to support a request for FMLA leave due to the serious health condition of your family member. If requested by your employer, your response is required to obtain or retain the benefit of the FMLA protections. 29 U.S.C. §§ 2613, 2614(c)(3). You are responsible for making sure the medical certification is provided to your employer within the time frame requested, which must be at least 15 calendar days. 29 C.F.R. §§ 825.305-825.306. Failure to provide a complete and sufficient medical certification may result in a denial of your FMLA leave request. 29 C.F.R. § 825.313.
Sources
[1] Form WH-380-F (Revised June 2020), Certification of Health Care Provider for Family Member's Serious Health Condition under the Family and Medical Leave Act, U.S. Department of Labor Wage and Hour Division (the Official source link on this page).