


Forma MA-34 at a glance
What it is: MA-34 Revisada: octubre/2023 is the CERTIFICACIÓN DE GASTOS DE MEDICAMENTOS PARA USO CONTINUO of the DEPARTAMENTO DE SALUD PROGRAMA MEDICAID.
Who signs: The solicitante, beneficiario or representante signs at "FIRMA DEL SOLICITANTE/BENEFICIARIO/O REPRESENTANTE:". The médico and the farmaceútico each sign at FIRMA.
A filled-in Forma MA-34 example: a physician and a pharmacist certify two medicines
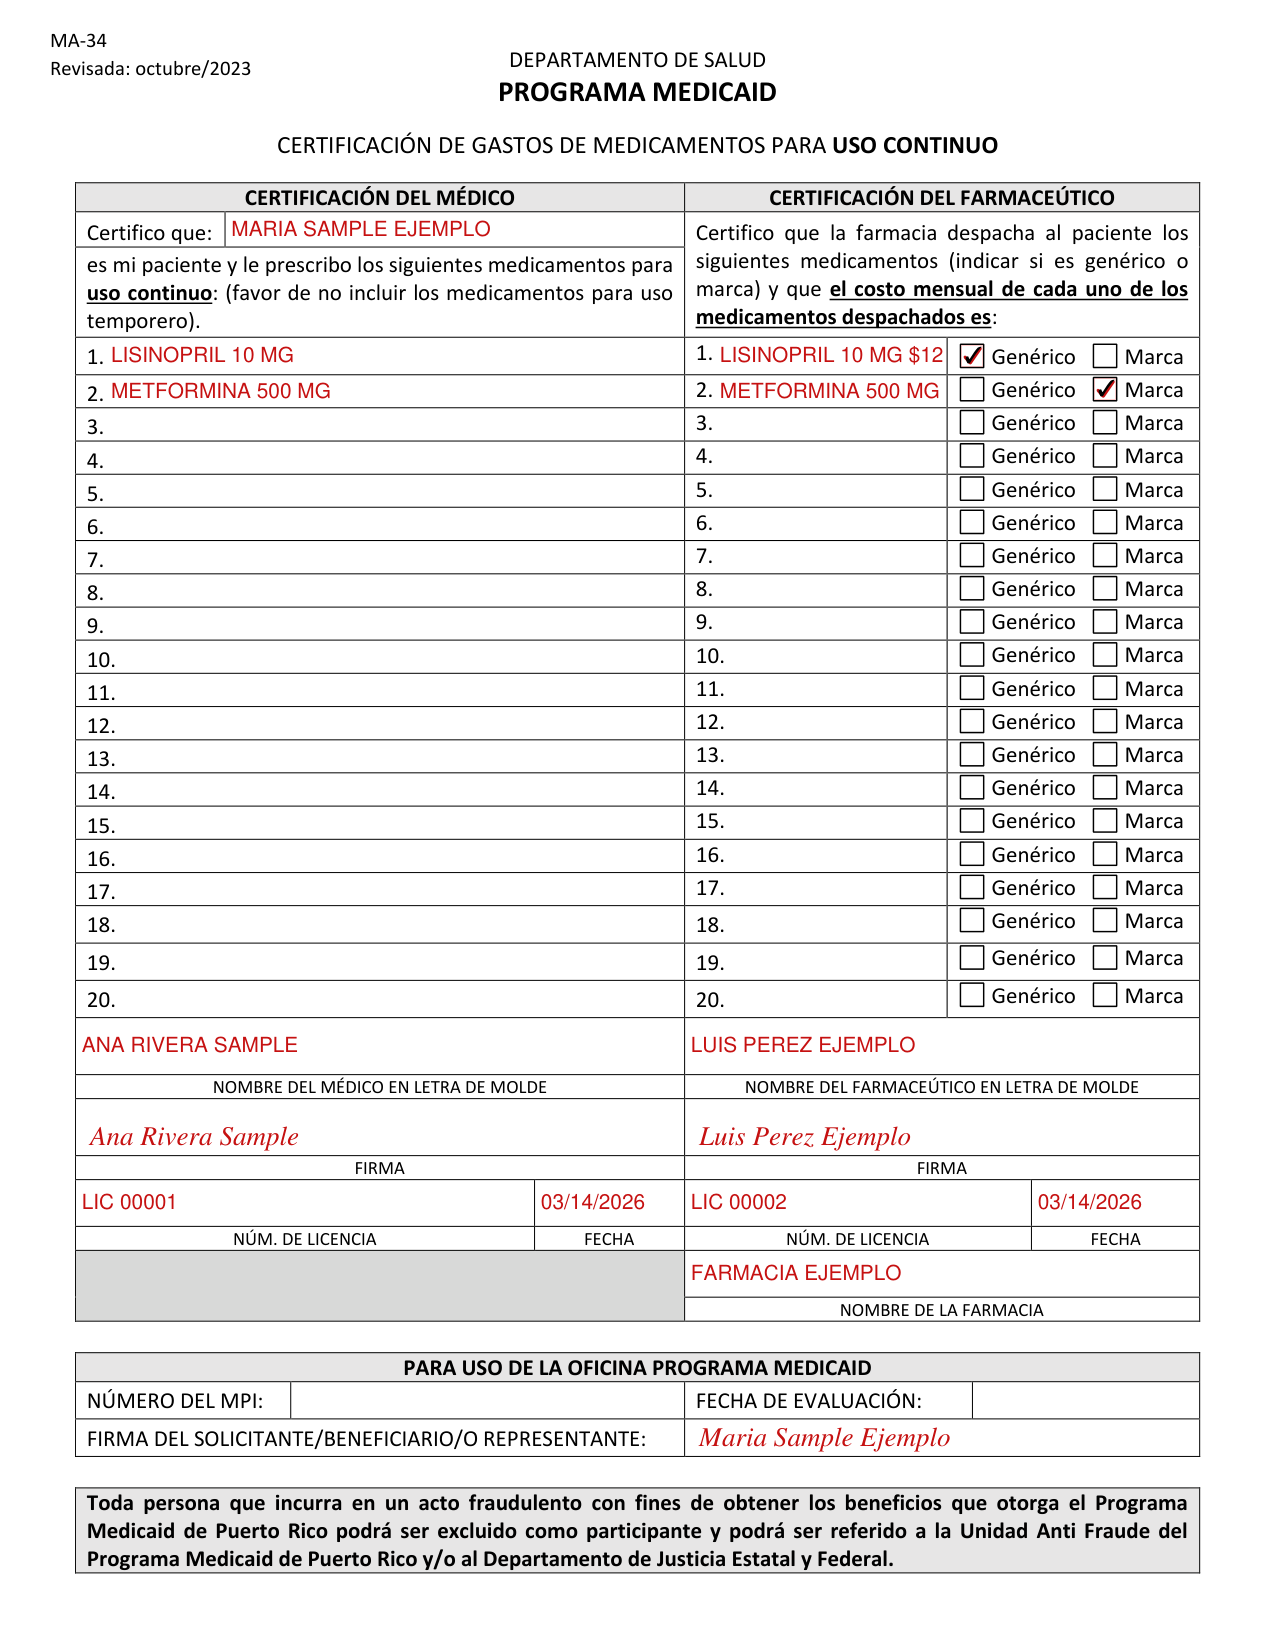
How to fill out Forma MA-34, box by box
CERTIFICACIÓN DEL MÉDICO
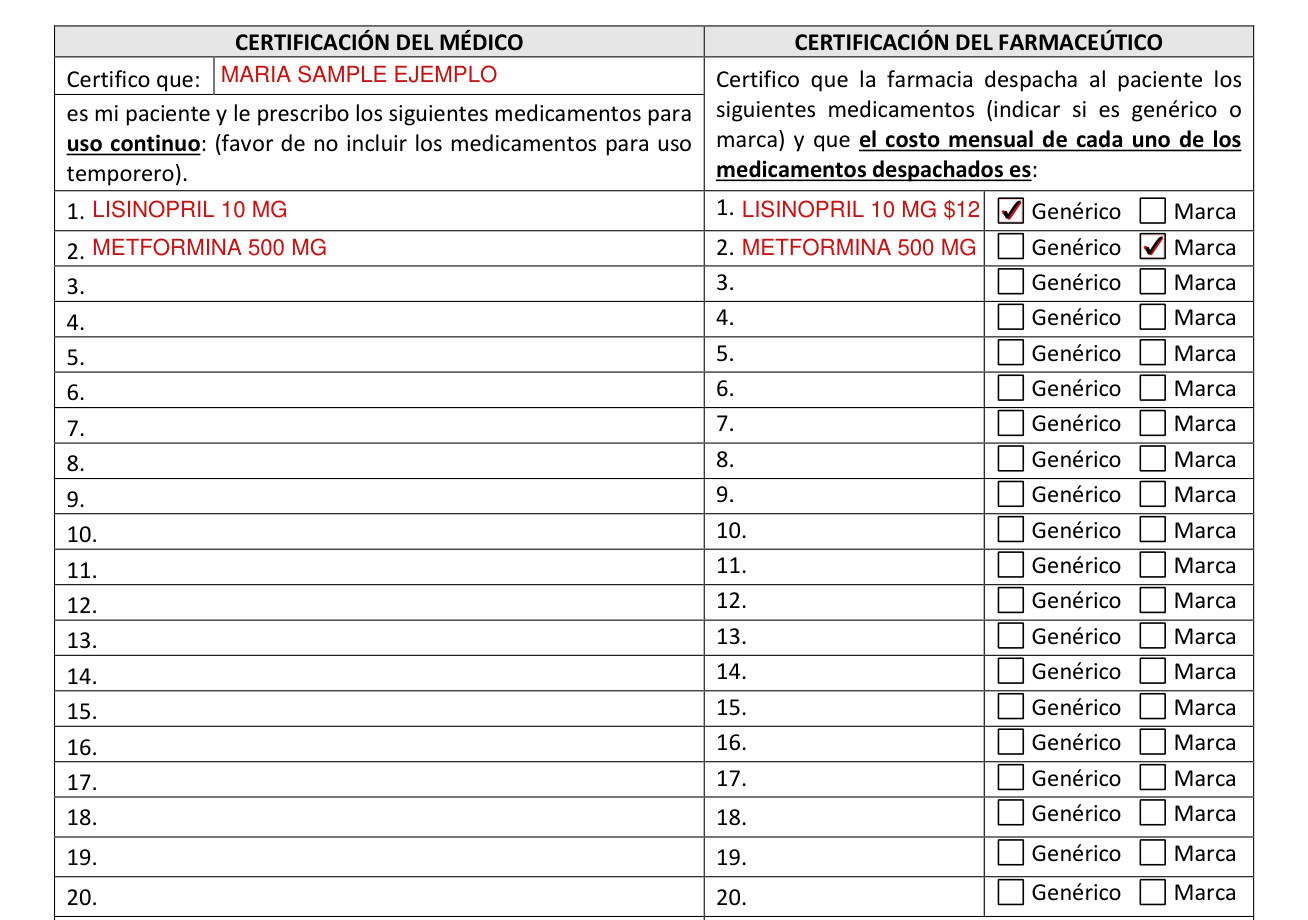
Next to "Certifico que:", write the paciente who "es mi paciente y le prescribo los siguientes medicamentos para uso continuo: (favor de no incluir los medicamentos para uso temporero)".
Write the medicamentos on lines 1 to 20.
CERTIFICACIÓN DEL FARMACEÚTICO
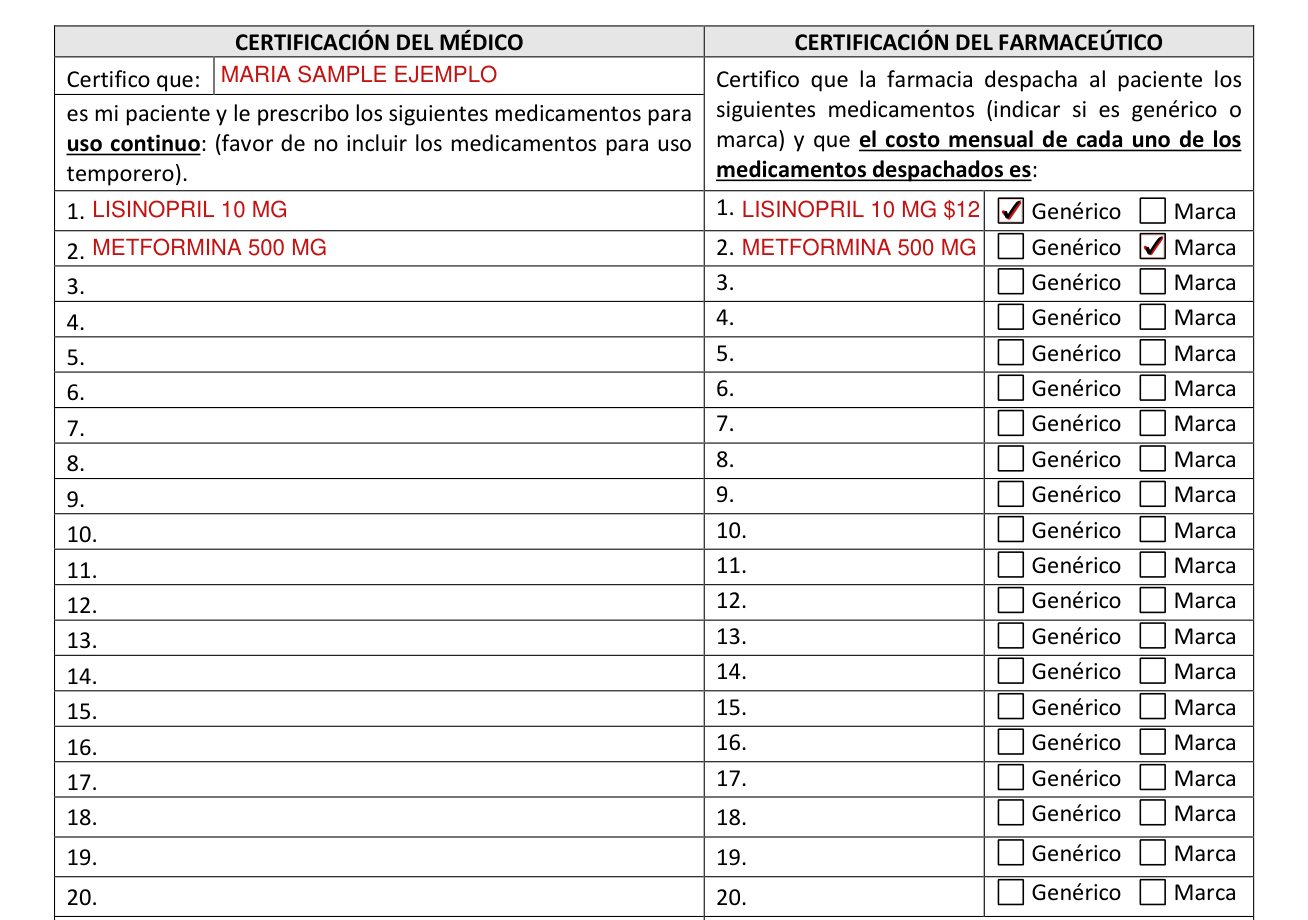
Under "Certifico que la farmacia despacha al paciente los siguientes medicamentos (indicar si es genérico o marca) y que el costo mensual de cada unode los medicamentos despachados es:", write on lines 1 to 20 each of the medicamentos despachados and its costo mensual.
On each of lines 1 to 20, "indicar si es genérico o marca" by marking "Genérico" or "Marca".
NOMBRE, FIRMA, NÚM. DE LICENCIA, FECHA

Write the NOMBRE DEL MÉDICO EN LETRA DE MOLDE and the NOMBRE DEL FARMACEÚTICO EN LETRA DE MOLDE; then enter FIRMA, NÚM. DE LICENCIA and FECHA.
Enter the NOMBRE DE LA FARMACIA.
Common questions about Forma MA-34
¿Qué es la MA 34?
MA-34 Revisada: octubre/2023 is the CERTIFICACIÓN DE GASTOS DE MEDICAMENTOS PARA USO CONTINUO of the DEPARTAMENTO DE SALUD PROGRAMA MEDICAID. The form has the CERTIFICACIÓN DEL MÉDICO and the CERTIFICACIÓN DEL FARMACEÚTICO.
Is there a penalty?
Any person who "incurra en un acto fraudulento con fines de obtener los beneficios que otorga el Programa Medicaid de Puerto Rico" "podrá ser excluido como participante y podrá ser referido a la Unidad Anti Fraude del Programa Medicaid de Puerto Rico y/o al Departamento de Justicia Estatal y Federal".
Sources
[1] Forma MA-34 Revisada octubre/2023, Certificación de Gastos de Medicamentos para Uso Continuo, Departamento de Salud Programa Medicaid (the Official source link on this page).