

How to Fill Out Form HFS 1409

Form HFS 1409 at a glance

What it is: HFS 1409 (R-11-15) is the Prior Approval Request Form of the Illinois Department of Healthcare and Family Services.

Who signs: Box 22 is Approving Authority Signature. In box 23, Provider Signature Date, sign and write the date.

A filled-in Form HFS 1409 example: a provider asks for prior approval

Form HFS 1409 example filled out, example: a provider asks for prior approval
Sample Supply Co., the provider, fills out HFS 1409. It asks for prior approval of one procedure in box 16, with Qty 1 and one diagnosis. The picture shows the provider's boxes; every value in it is made up. Dr. Alex Q. Sample is the physician. Jamie Q. Sample is the recipient. Boxes 17 to 20 stay empty, because the request has one procedure. Box 13 stays empty, because the request has one diagnosis. Cat. Serv, Pur/Rent and Mod stay empty, because the form gives no values for them. Approved HFS Amt and Approving Authority Signature stay empty, because the form is a request for approval. Sam Q. Sample signs for the provider on 10/20/2026.

How to fill out Form HFS 1409, box by box

Recipient Name, Birthdate, Provider NPI and Provider Telephone

Form HFS 1409 example filled out, recipient Name, Birthdate, Provider NPI and Provider Telephone

Enter 1. Recipient #, 2. Recipient Name and 3. Birthdate.

Enter 4. Provider /NPI # and 5. Provider Telephone #.

Provider and Physician Name, Street Address, City, State and Zip Code
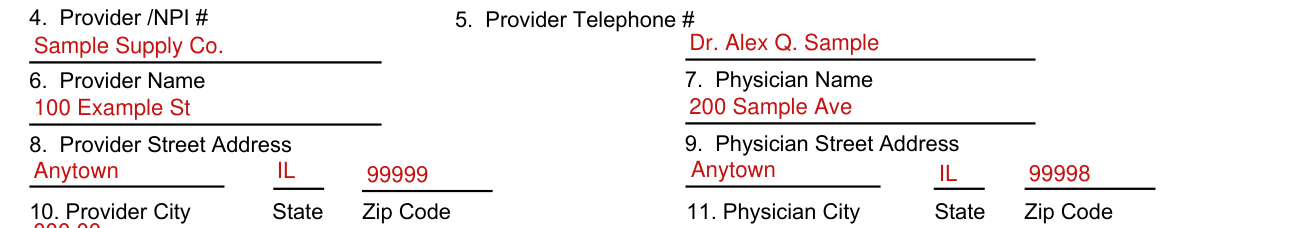
Form HFS 1409 example filled out, provider and Physician Name, Street Address, City, State and Zip Code

Enter 6. Provider Name and 7. Physician Name.

Enter 8. Provider Street Address and 9. Physician Street Address.

Enter 10. Provider City, State and Zip Code, and 11. Physician City, State and Zip Code.

Diagnosis Code, Additional Diagnosis, Diagnosis Description and Patient Height / Weight

Form HFS 1409 example filled out, diagnosis Code, Additional Diagnosis, Diagnosis Description and Patient Height / Weight

Enter 12. Diagnosis Code and 13. Additional Diagnosis.

Enter 14. Diagnosis Description and 15. Patient Height / Weight.

Procedure Code, Description, Qty, Cat. Serv, Begin Date and End Date
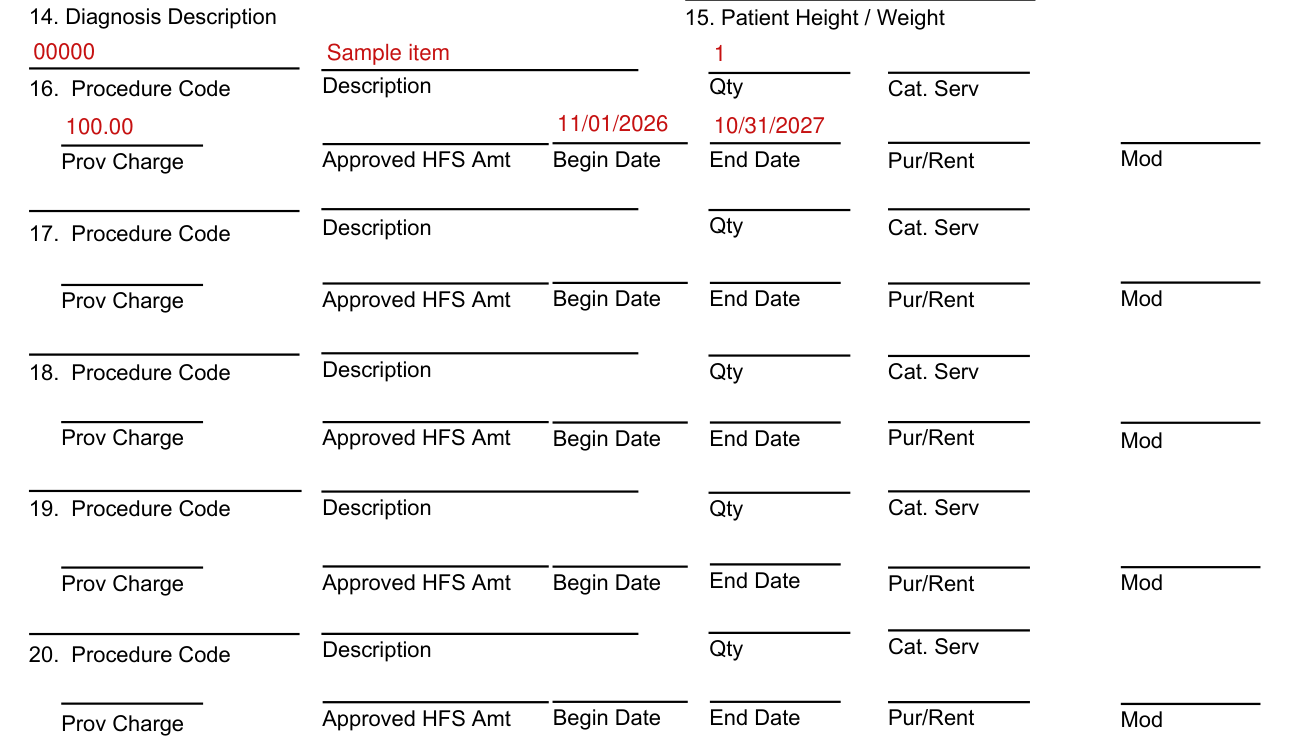
Form HFS 1409 example filled out, procedure Code, Description, Qty, Cat. Serv, Begin Date and End Date

Each of boxes 16, 17, 18, 19 and 20 has Procedure Code, Description, Qty, Cat. Serv, Prov Charge, Approved HFS Amt, Begin Date, End Date, Pur/Rent and Mod.

Additional Medical Necessity

Form HFS 1409 example filled out, additional Medical Necessity

Enter 21. Additional Medical Necessity.

Approving Authority Signature and Provider Signature Date

Form HFS 1409 example filled out, approving Authority Signature and Provider Signature Date

The form certifies that the information is true, accurate, and complete.

Box 22 is Approving Authority Signature.

In box 23, Provider Signature Date, sign and write the date.

Sources

[1] Form HFS 1409 (R-11-15), Prior Approval Request Form, Illinois Department of Healthcare and Family Services (the Official source link on this page).

HFS 1409 Form PDF Details

Form HFS 1409 lists the recipient, provider, physician and diagnosis, then the procedures.

Recipient: Recipient #, Recipient Name and Birthdate.

Provider: Provider /NPI #, Provider Telephone #, Provider Name, Provider Street Address and Provider City, State and Zip Code.

Physician: Physician Name, Physician Street Address and Physician City.

Diagnosis: Diagnosis Code, Additional Diagnosis, Diagnosis Description and Patient Height / Weight.

Each procedure line (boxes 16 to 20): Procedure Code, Description, Qty, Cat. Serv, Prov Charge, Approved HFS Amt, Begin Date, End Date, Pur/Rent and Mod.

Signatures: box 22, Approving Authority Signature, and box 23, Provider Signature and Date.

QuestionAnswer
Form NameHFS 1409 Form
Form Length1 page
Fillable?Yes
Fillable fields73
Avg. time to fill out13 min
EditionR-11-15
Other namesHFS 1409, Form 1409, HFS 1409 Prior Approval Request Form
Official sourceForm HFS 1409 (R-11-15)