

Enrollment/Waiver Form ENR-129 at a glance
What it is: This is the enrollment/waiver form: complete this application in its entirety in blue or black ink, and do not use pencil or highlighter.
Where and when to file: For New Group Business, send all new business materials (Small Group Business Application, Enrollment/Waiver Forms and supporting documentation) to Highmark Attn: Producer Affairs P.O. Box 890089 Camp Hill, PA 17089-0089.
A filled-in Enrollment/Waiver Form ENR-129 example: an employee enrolls alone
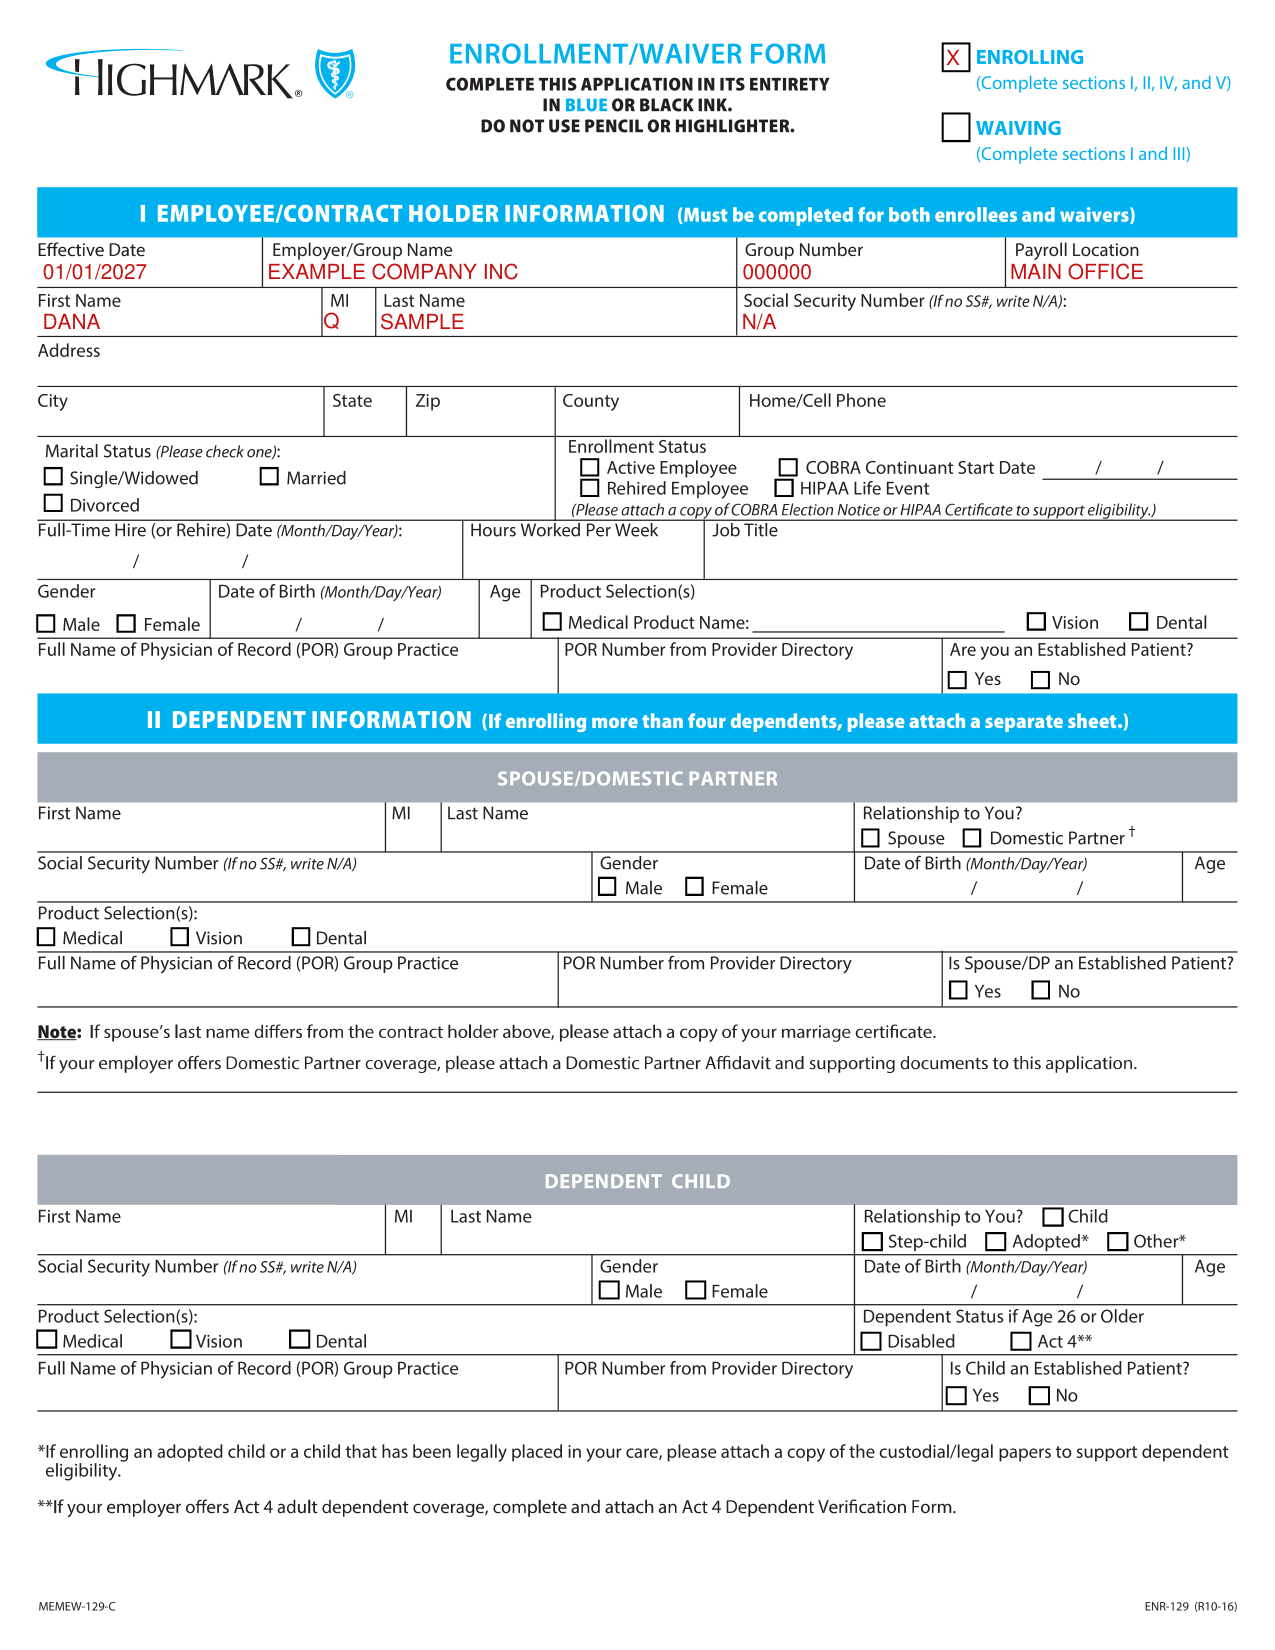
How to fill out Enrollment/Waiver Form ENR-129, box by box
Employee/Contract Holder Information
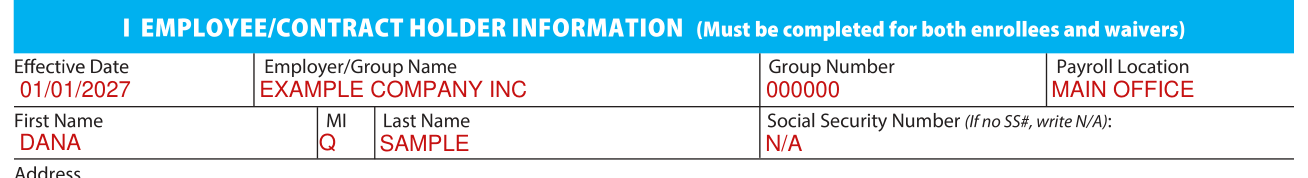
Complete the Employee/Contract Holder Information for both enrollees and waivers: Effective Date, Employer/Group Name, Group Number, Payroll Location, First Name, MI, Last Name and Social Security Number (If no write N/A).
If your situation is different
Dependent Information
If enrolling more than four dependents, attach a separate sheet.
If spouse's last name differs from the contract holder, attach a copy of your marriage certificate.
If enrolling an adopted child or a child that has been legally placed in your care, attach a copy of the custodial/legal papers to support dependent eligibility.
Waiver of Coverage
Complete the Waiver of Coverage section ONLY if you are declining coverage(s) offered to you AND/OR your family members.
Sign only if you are waiving coverage.
If you are declining enrollment for yourself or your dependents (including your spouse) because of other health insurance or group health plan coverage, you may in the future be able to enroll yourself and your dependents in this plan, provided that you request enrollment within 31 days after you and your other coverage ends, or not later than 60 days if the other plan coverage was through Medicaid or a state Children's Health Insurance Program (CHIP).
If you have a new eligible dependent as a result of marriage, birth, adoption or placement for adoption, you may be able to enroll yourself and your eligible dependents, provided that you request enrollment within 30 days after the marriage, birth, adoption or placement for adoption.
To request special enrollment or obtain more information, contact your employer or call the toll-free Highmark Member Service number: 1-800-345-3806 (TTY/TDD: Dial 711).
Medicare Coverage
Under Medicare Coverage, list any family member that is eligible for Medicare Benefits.
Common questions about Enrollment/Waiver Form ENR-129
Where do I file it?
For Ongoing Enrollment, when adding new employees/contract holders or dependents to an existing group, fax Enrollment/Waiver Forms to Fax (800) 290-3301 or send them to Membership Department P.O. Box 890172 Camp Hill, PA 17089-0172.
Is there a penalty?
Any person who knowingly and with intent to defraud any insurance company or other person files an application for insurance or statement of claim containing any materially false information commits a fraudulent insurance act, which is a crime and subjects such person to criminal and civil penalties.
Sources
[1] Enrollment/Waiver Form ENR-129 (R10-16), Highmark (the Official source link on this page).
