Hospital Admit Form PDF Details

Navigating the paperwork for hospital admission can often feel overwhelming, but understanding the elements of the Hospital Admit Form can simplify the process. This comprehensive document collects essential information ranging from the type of service required—be it general surgery, maternity, or day surgery—to the patient's personal details like name, birth date, and social security number. It addresses patient-specific queries like the expected date of admission, diagnosis or symptoms, and even the date of the last menstrual period for maternity cases. The form doesn't just stop at medical details; it extends to logistical concerns, ensuring the hospital is equipped to provide a personalized and efficient healthcare experience. By requesting information on insurance details, it prompts patients to verify coverage beforehand, aiming to streamline the financial aspect of the hospital stay. It also delves into whether the patient is self-paying or covered under workman's compensation, requiring further details if applicable. Additionally, for those eligible, it inquires about military service and Alaska Native benefits. This form signifies more than just a registration necessity; it reflects the hospital's commitment to patient care and the importance of preparing both the patient and the facility for the upcoming medical service. The Providence Hospital Pre-Admission Form, deeply rooted in the ethos of ensuring equitable access to health care, underscores the community's sustained commitment to serve, a principle championed by the Sisters of Providence since their inception.

QuestionAnswer
Form NameHospital Admit Form
Form Length2 pages
Fillable?No
Fillable fields0
Avg. time to fill out30 sec
Other namestemplate of admission and discharge forms in the maternity ward, hospital discharge paper, hospital admission slip and discharge papers, hospital admitting papers

How to Fill Out Providence Hospital Pre-Admission Form

Providence Hospital Pre-Admission Form at a glance

What it is: Providence Hospital Pre-Admission Form: procedure information required for registration.

Where and when to file: Admitting Department, Providence Alaska Medical Center, PO Box 196604, Anchorage AK 99519-6604; place postage stamp here.

A filled-in Providence Hospital Pre-Admission Form example: a day surgery pre-admission

Providence Hospital Pre-Admission Form example filled out, example: a day surgery pre-admission
Sam Q. Sample fills out the Providence pre-admission form for day surgery. Sam is the patient and has one insurance, so Responsible party and Insurance 2 stay empty. Emergency contact, Facility directory, Military, VA, Alaska Native benefits and U.S. citizen, and Self pay and workman's compensation are left blank because Sam answers them at registration. The picture shows the filled form, and none of its entries is real.

How to fill out Providence Hospital Pre-Admission Form, box by box

Procedure information, required for registration
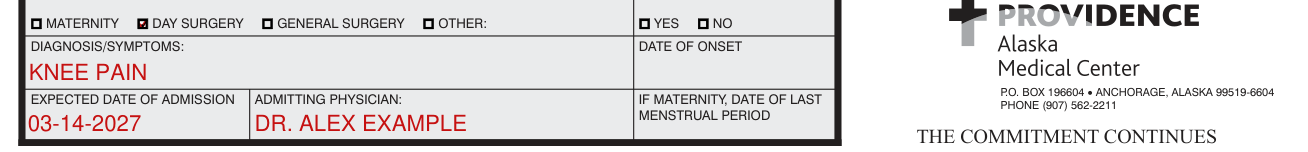
Providence Hospital Pre-Admission Form example filled out, procedure information, required for registration

Under What type of service are you registering for, check Maternity, Day Surgery, General Surgery or Other.

Enter the Diagnosis/Symptoms, the Date of Onset, the Admitting Physician and the Expected Date of Admission.

If maternity, enter the Date of Last Menstrual Period.

Facility directory

Providence Hospital Pre-Admission Form example filled out, facility directory

Under Facility Directory, check Yes or No.

Patient information
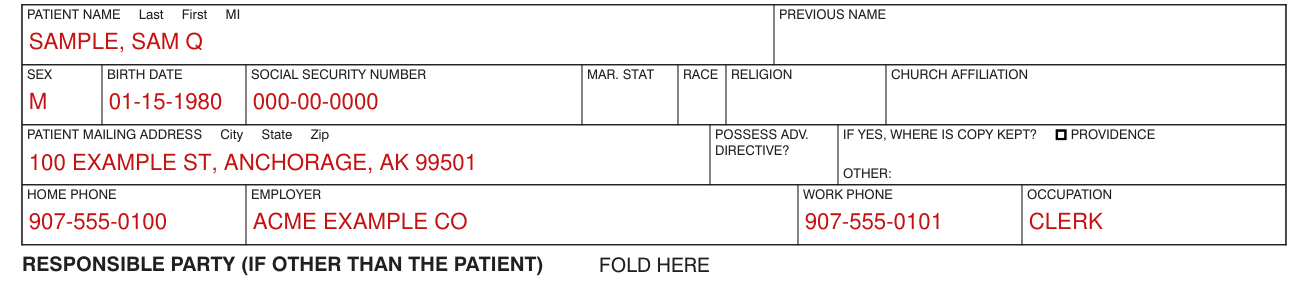
Providence Hospital Pre-Admission Form example filled out, patient information

Enter the Patient Name (Last, First, MI), Previous Name, Sex, Birth Date, Social Security Number, Mar. Stat, Race, Religion and Church Affiliation.

Enter the Patient Mailing Address (City, State, Zip), Home Phone, Employer, Work Phone and Occupation.

Under Possess Adv. Directive, if yes, state where the copy is kept: Providence or Other.

Responsible party (if other than the patient)
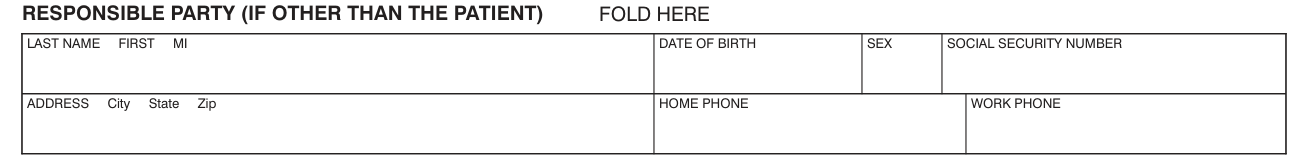
Providence Hospital Pre-Admission Form example filled out, responsible party (if other than the patient)

Under Responsible Party (if other than the patient), enter the Last Name, First, MI, Date of Birth, Sex, Social Security Number, Address (City, State, Zip), Home Phone and Work Phone.

Emergency contact
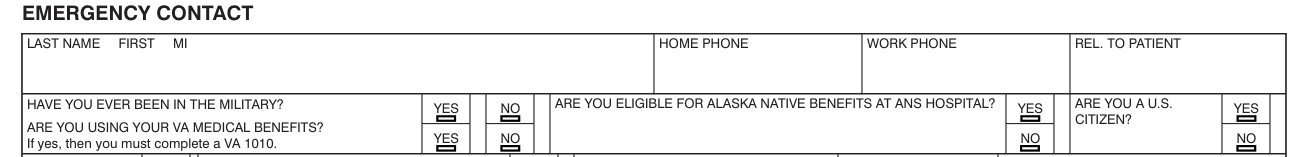
Providence Hospital Pre-Admission Form example filled out, emergency contact

Under Emergency Contact, enter the Last Name, First, MI, Home Phone, Work Phone and Rel. to Patient.

Military, VA, Alaska Native benefits and U.S. citizen

Providence Hospital Pre-Admission Form example filled out, military, VA, Alaska Native benefits and U.S. citizen

Check Yes or No: Have you ever been in the military?

Check Yes or No: Are you using your VA medical benefits? If yes, then you must complete a VA 1010.

Check Yes or No: Are you eligible for Alaska Native benefits at ANS Hospital? Are you a U.S. citizen?

Self pay and workman's compensation

Providence Hospital Pre-Admission Form example filled out, self pay and workman's compensation

Check Yes or No: Self pay? Workman's Compensation? If yes, please complete next four blocks: Claim Number, Date of Injury and Workman's Comp. Carrier.

Insurance 1, Insurance 2 and Insurance 3
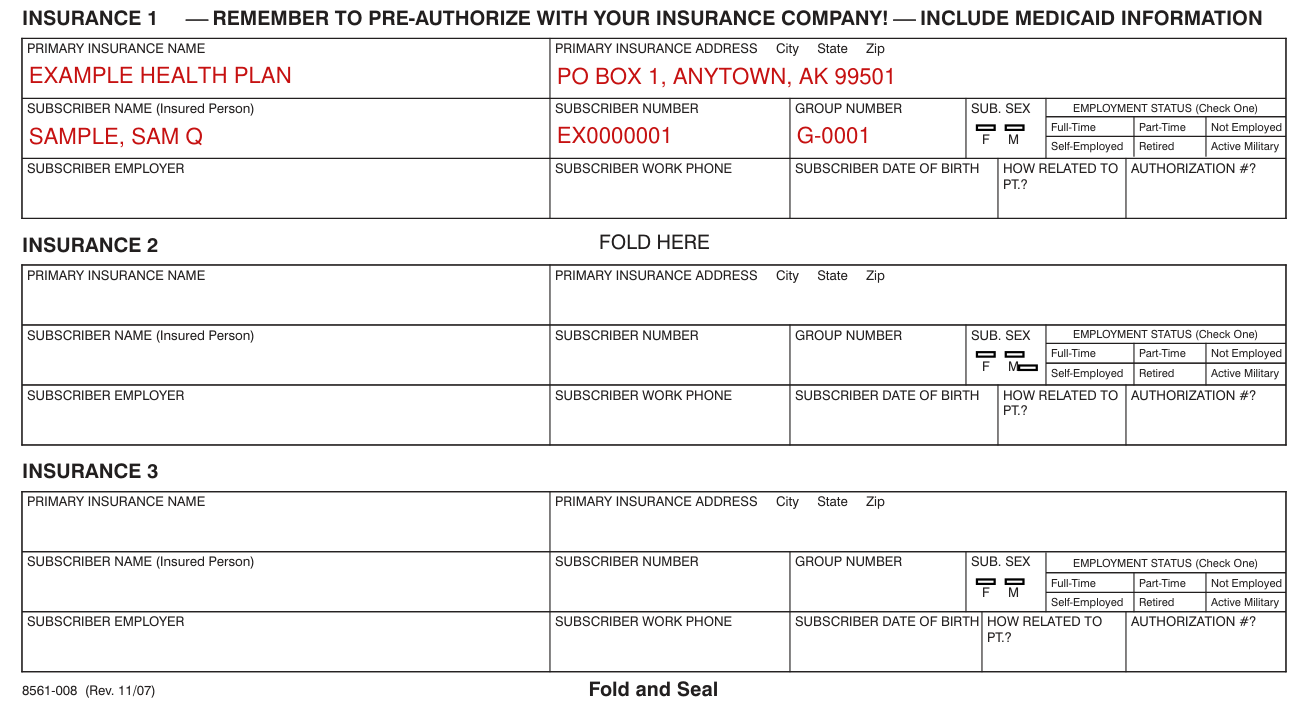
Providence Hospital Pre-Admission Form example filled out, insurance 1, Insurance 2 and Insurance 3

Under Insurance 1, remember to pre-authorize with your insurance company and include Medicaid information; enter the Primary Insurance Name and Primary Insurance Address (City, State, Zip).

Enter the Subscriber Name (Insured Person), Subscriber Number, Group Number, Sub. Sex, Subscriber Employer, Subscriber Work Phone, Subscriber Date of Birth, How Related to Pt. and Authorization #.

Insurance 2 and Insurance 3 each have their own Primary Insurance Name.

More rules for Providence Hospital Pre-Admission Form

Elective inpatient and outpatient cosmetic surgeries require payment in full at time of registration.

If your insurance has determined that this is a covered service and a payment authorization is obtained prior to registration, the balance due at point of registration will be the expected balance remaining after insurance.

Common questions about Providence Hospital Pre-Admission Form

Where do I file it?

Admitting Department, Providence Alaska Medical Center, PO Box 196604, Anchorage AK 99519-6604; place postage stamp here.

Sources

[1] Providence Hospital Pre-Admission Form (Rev. 11/07), Providence Alaska Medical Center (the Official source link on this page).

Please rate Hospital Admit Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .