

HS 215A at a glance
What it is: HS 215A (Rev. 7/2023) is the Applicant Individual Information form of the California Department of Public Health Licensing and Certification.
Who signs: The signature and date of this form should be within the last three months and must contain the signature of the individual whom this form is regarding.
The Applicant Individual Information (HS 215A) form is intended for any individual with five (5) percent or more (direct or indirect) ownership interest and/or control interest in the applicant facility or any individual involved (now or in the past) with any health care facility, agency, clinic, or community care facility. Refer to the Instructions for assistance.
The HS 215A form is required as part of a health care facility, agency, or clinic's application packet for state licensing and/or federal certification, including when changes are reported regarding officers, directors, purchase of stock, etc., even though no change in legal ownership has or is occurring.
What to bring and attach to HS 215A
Submit a copy of the individual's driver's license or state-issued identification card and title as: “Section B.4 - Driver's License or State-Issued Identification Card”.
Submit all supplemental paperwork and supporting documents to complete the Applicant Individual Information (HS 215A) Form.
A filled-in HS 215A example: a Director of Nursing applies for a new hospice agency

How to fill out HS 215A, box by box
A. Applicant Facility Information
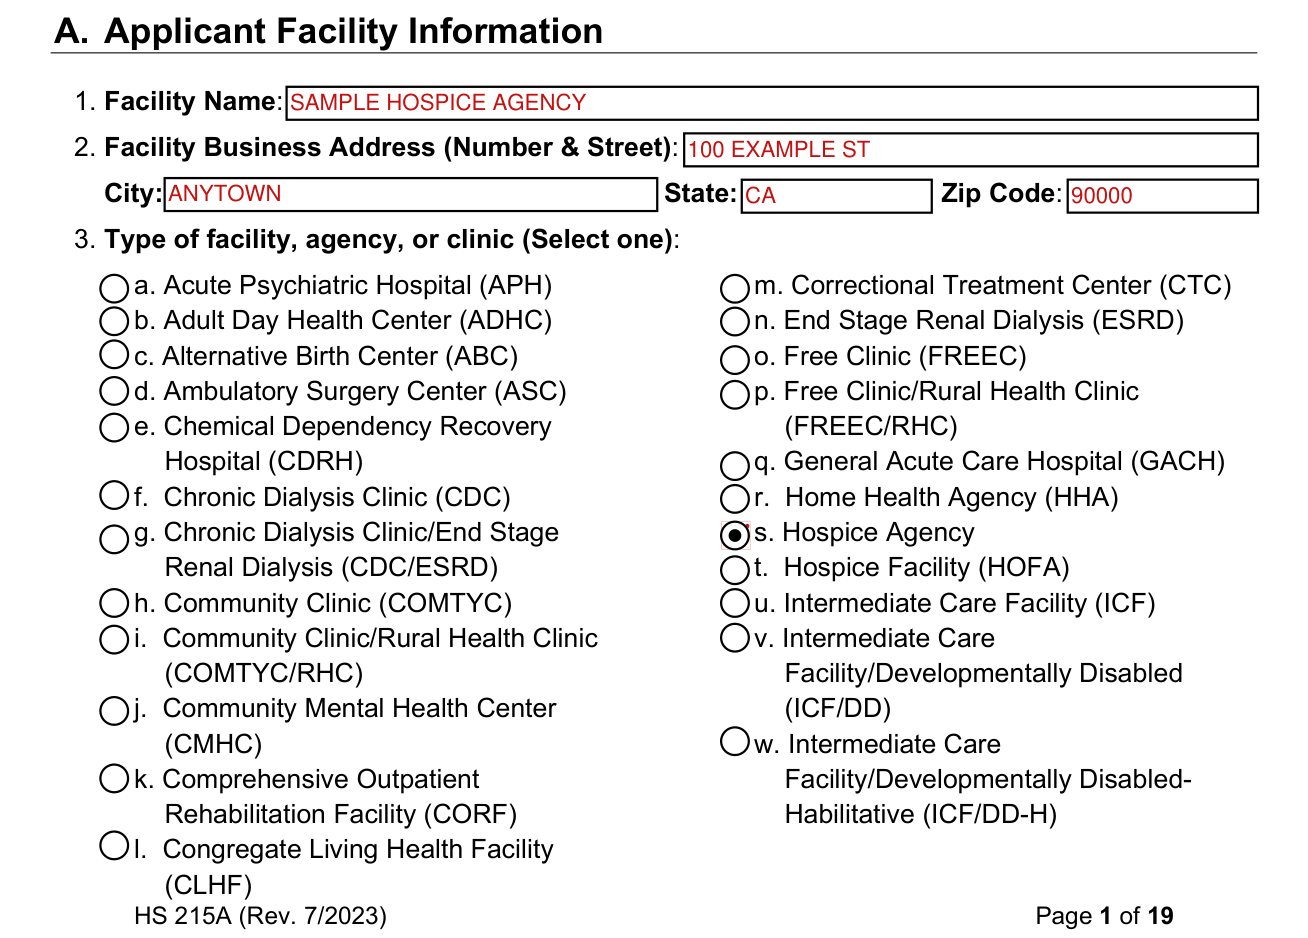
Facility Name: Enter the name of the facility, agency, or clinic.
Facility Business Address: Enter the address where the facility, agency, or clinic provides services.
3. Type of facility, agency, or clinic (Select one): Type of Facility: Select the type of facility, agency, or clinic you are involved with identified in Section A.1 and A.2.
4. Type of Application (Check one): Type of Application: Select the type of application you are submitting.
B. Applicant Individual Information
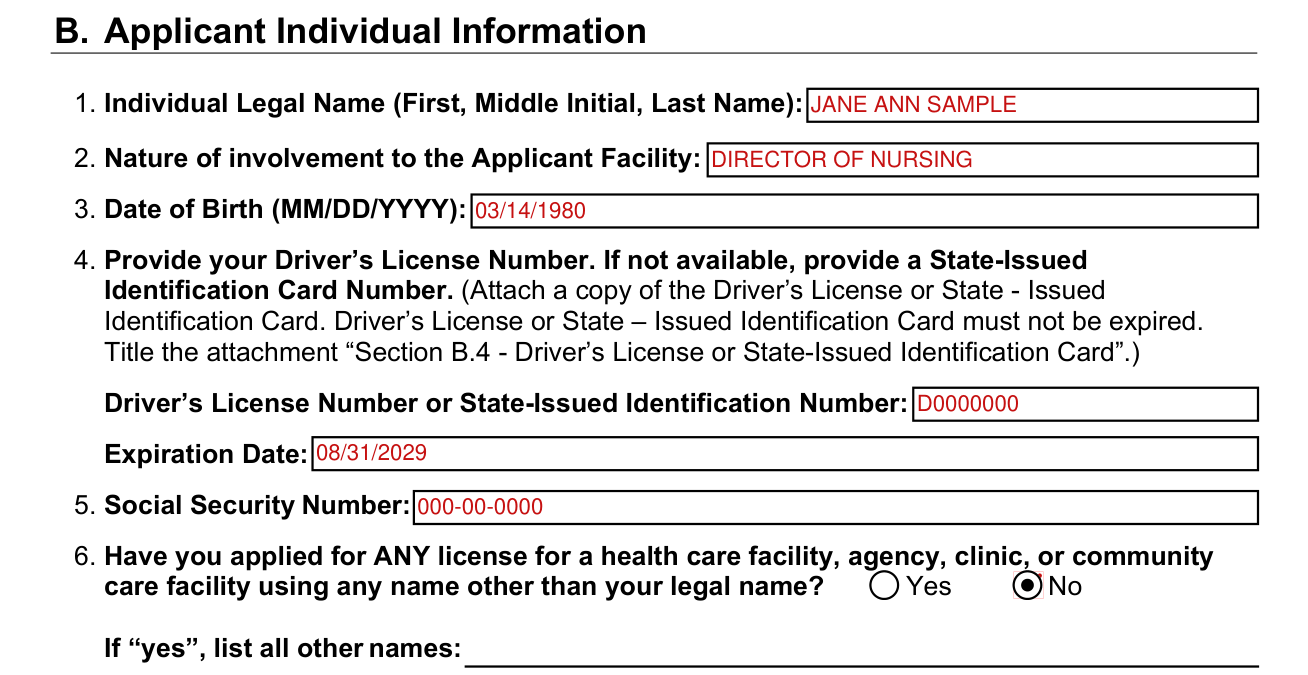
1. Individual Legal Name (First, Middle Initial, Last Name): Applicant Name: Enter the name of the individual filling out this form.
2. Nature of involvement to the Applicant Facility: Nature of involvement to this Facility: Enter the title of the relationship the individual has with this facility.
Date of Birth (MM/DD/YYYY): Enter the individual's date of birth in numerical format with two digits for the month, two digits for the date, and four digits for the year.
Provide your Driver's License Number. If not available, provide a State-Issued Identification Card Number.
(Attach a copy of the Driver's License or State - Issued Identification Card. Driver's License or State - Issued Identification Card must not be expired. Title the attachment “Section B.4 - Driver's License or State-Issued Identification Card”.)
Social Security Number: Applicant must provide this information as required per Title 42 Code of Federal Regulations (CFR) Section 455.104(b)(1).
Select “yes” or “no” if you applied for any license for health care facility or community care facility using any other name than your legal name: If “yes” is selected, list the names used in the space provided.
7. Administrator
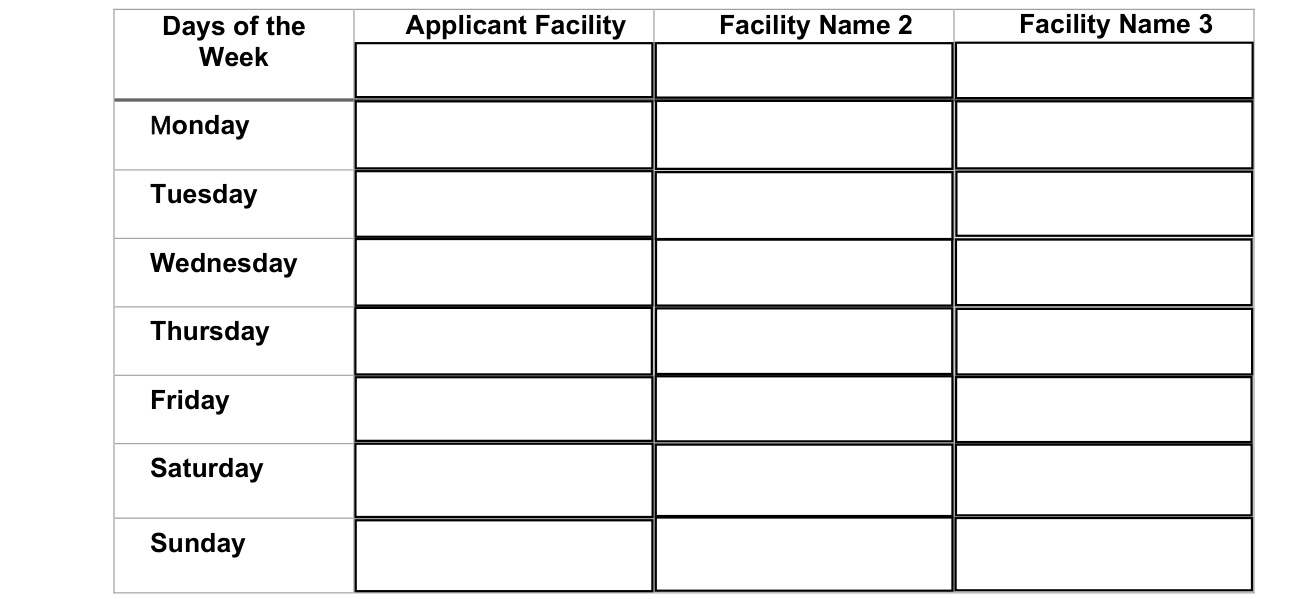
Administrator: If you have an Administrator role at the applicant facility, agency or clinic named in Section A, list the number of hours that you will spend at the facility each week. If you are an Administrator at more than one licensed and/or certified facility list the name of each facility and the number of hours spent in each facility per week.
(Attach additional pages if necessary. Title pages: “Section B.7 - Administrator Schedule of Multiple Facilities”.)
C. Criminal Record

1. Have you ever been convicted of an offense that is still on your record, whether a misdemeanor or felony? Yes No
2. Has there been a judgment against you for Medicare or Medicaid (Medi-Cal) fraud? Yes No
Select “yes” or “no” if there has been a judgment against you by a health care professional/technical licensing entity.
If “yes” to any of the questions in Section C, provide conviction information, dates of misdemeanor and/or felony, and any supporting documents (Attach additional pages if necessary. Title pages: “Section C - Criminal Record”.)
D. Professional Licenses/Certificates
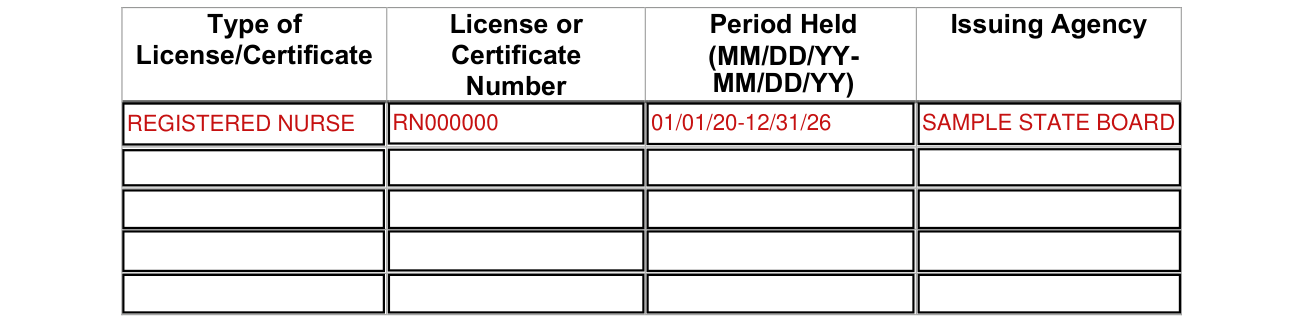
If a professional license or certificate is required for your role in association with the applicant facility, agency, or clinic (as identified in Section B.2.), provide the information in the table.
Enter the Period Held as MM/DD/YY to MM/DD/YY.
E. Employment History
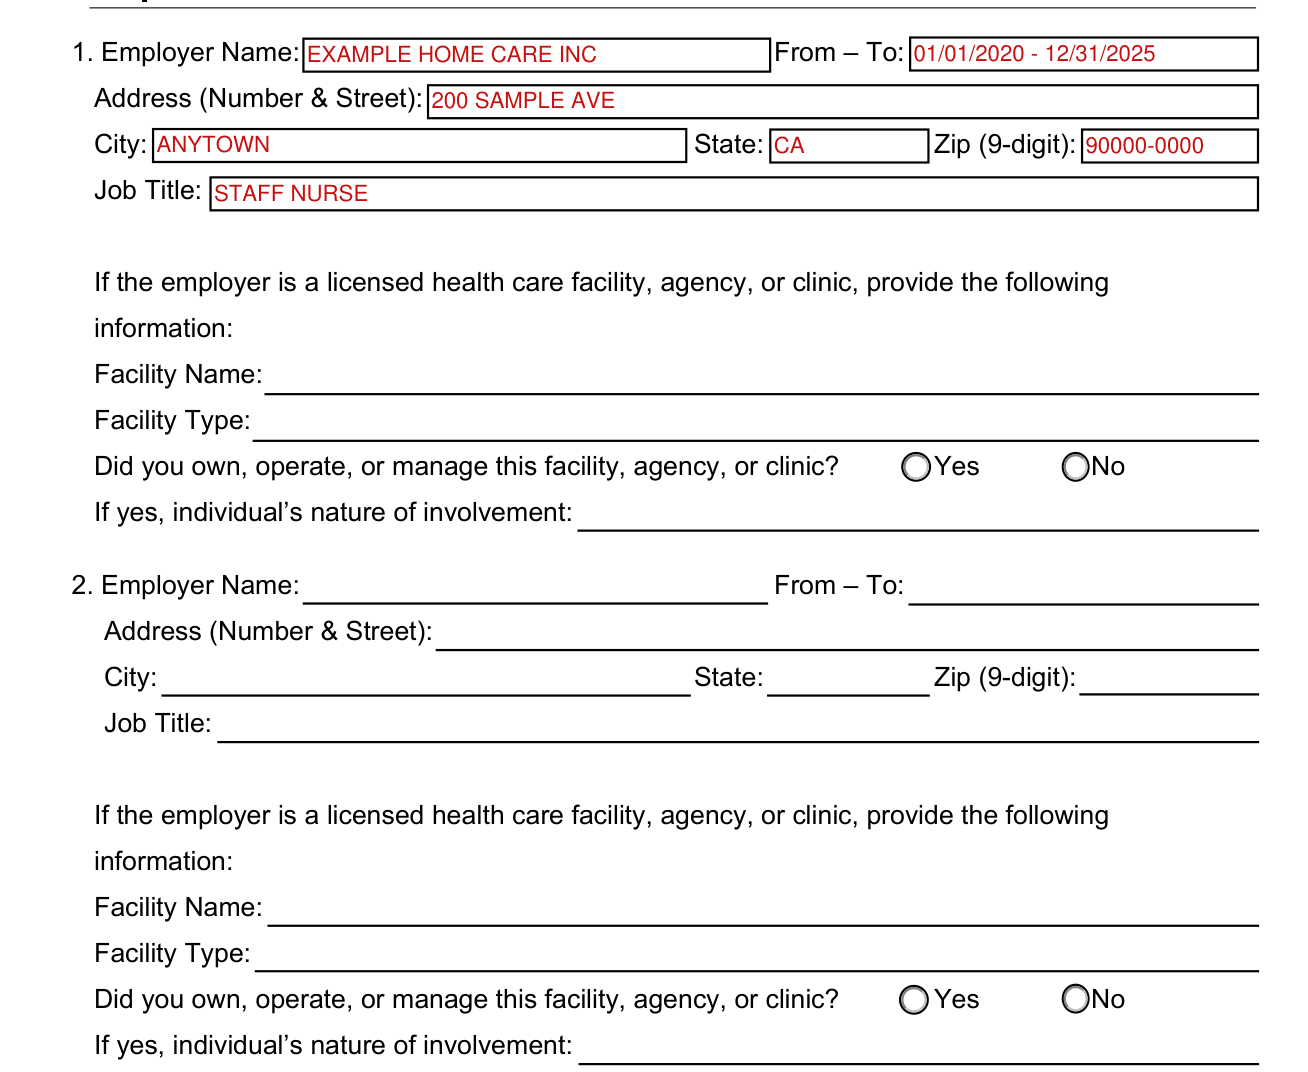
Please list your complete employment history for the past 10 years. In addition, any additional experience that qualifies you for the nature of your involvement in this facility, agency, or clinic. Begin with your most recent job.
You may submit a resume in lieu of completing this section, include all pertinent information as requested.
If the employer is a licensed health care facility, agency, or clinic, provide the Facility Name and the Facility Type. Did you own, operate, or manage this facility, agency, or clinic? Yes No. If yes, provide the individual's nature of involvement.
F. Facility, Agency, Clinic Involvement

1. Have you ever been involved with a business entity that owned, operated, or managed a health care facility, agency, or clinic? Yes No
2. Have you ever held a five (5) percent or more beneficial (direct or indirect) ownership interest and/or control interest in any health care facility, agency, or clinic? Yes No
If “yes” to any of the questions in Section F, complete Section H, Facility Information Sheet.
G. Adverse Actions

Select “yes” or “no” if the applicant has ever been affiliated with any facility, either past or present, that has been identified as having one or more of the listed adverse actions.
If “yes”, check ALL applicable: include facility name/address, provide dates, and findings. (Attach additional pages. Title pages: “Section G - Adverse Action”.)
Check ALL that apply: Action Resolved by settlement, Bankruptcy, Foreclosures, Judgments, License Revocation action filed, License Revoked (Whether stayed or not), License Involuntarily Suspended, Medicaid (Medi-Cal) decertification, Medicare decertification, Placed on any form of probation, Receiver Appointed, Temporary Manager appointed, Other: (Specify).
H. Facility Information Sheet
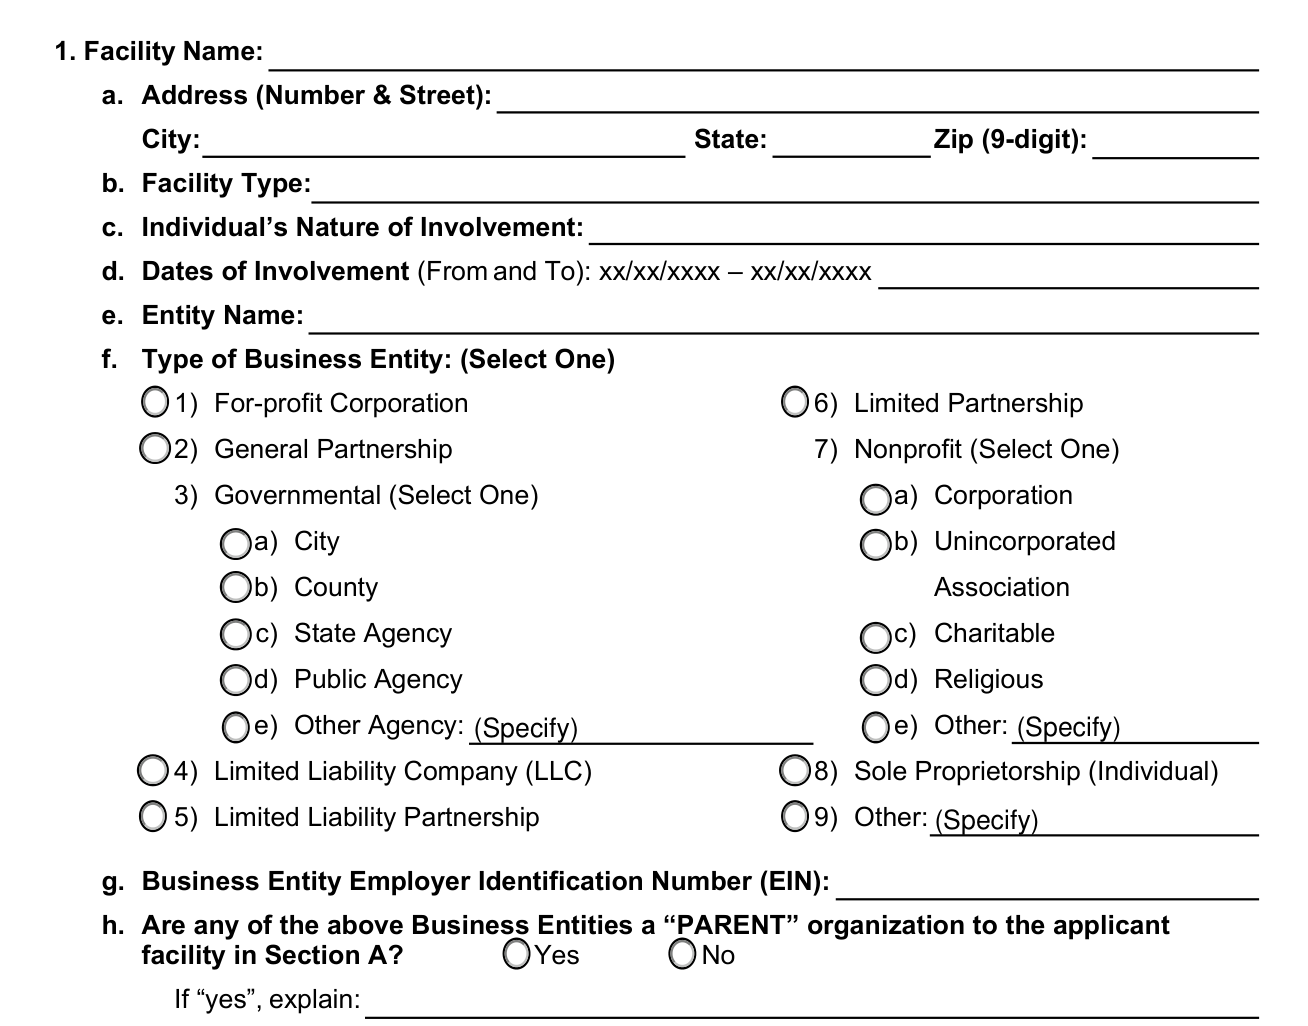
You are required to complete the following for each facility (including all facilities in all business entities) with which you have a current relationship or have had a past relationship (going back 5 years for SNFs and 3 years for all other facility types).
1. Facility Name: Facility Name (questions 1 - 6): Enter the name of the facility.
If “Stockholder” is selected, then the applicant must enter the amount of ownership percentage held. If “other” is selected, the applicant must list the type of involvement.
Dates of Involvement: Enter the start and finish date of involvement. If this relationship is still ongoing indicate the start date to “Current”.
Type of Business Entity: (Select One) Business Entity Type: Select an option provided. If “other” is selected, the applicant must indicate the type of entity.
Business Entity Employer Identification Number (EIN): Business Entity Employment Identification Number (EIN): Enter the businesses EIN number.
If any of the Business entities are a “Parent” organization to the applicant facility in Section A, select “yes”; if “yes” is selected, explain in the space provided.
Applicant Release

“I declare under penalty of perjury under the laws of the State of California that the statements on this application and on the accompanying attachments are correct to the best of my knowledge.”
Applicant Signature: Date: Applicant Release Application must be signed by the individual applicant whom it is about. Provide signature and date.
Type your full legal name in Applicant Printed Name, and add your Title.
Failure to provide the information as requested or misrepresentation of a material fact may result in denial of an application, non-issuance of a license, or license revocation.
More rules for HS 215A
Complete all applicable questions. Do not leave items blank. Mark N/A, if not applicable.
The information provided on this form is mandatory and is necessary for licensure approval.
The information is considered public information and will be made available to the public upon request.
Common questions about HS 215A
Is there a deadline?
Any changes must be provided to the state department within 10 days of the change.
Sources
[1] Form HS 215A (Rev. 7/2023), Applicant Individual Information, California Department of Public Health (the Official source link on this page).
