

Form HSMV 72190 at a glance
What it is: The Medical Referral Form of the State of Florida Department of Highway Safety and Motor Vehicles is for reporting an individual whose driving ability is questionable due to some physical or mental deficit or disorder.
Where and when to file: Mail this Completed Form to: Bureau of Motorist Compliance, Medical Review Program, Neil Kirkman Building, MS 86, Tallahassee, Florida 32399-0500.
A filled-in Form HSMV 72190 example: a friend reports a driver who had a stroke

How to fill out Form HSMV 72190, box by box
The driver
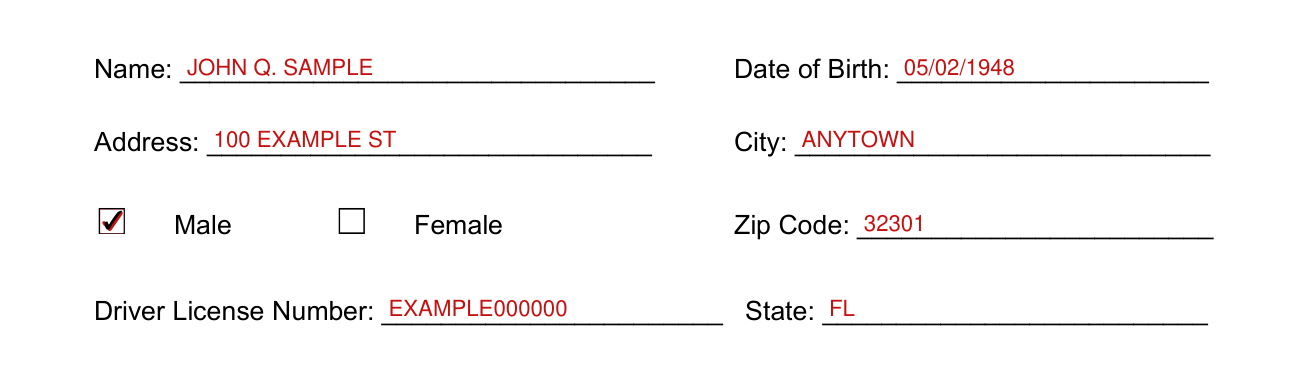
Complete as much of the information on the form as possible.
Enter the Name, Date of Birth, Address, City, Driver License Number and State.
Mark Male or Female, and enter the Zip Code.
Physical or Mental Deficit or Disorder Noted

Under Physical or Mental Deficit or Disorder Noted, mark Seizures, Severe Cardiac Condition, Stroke, Loss of Consciousness, Uncontrollable Diabetes, Dementia/Memory Deficits, Psychiatric Disturbance, Drug/Alcohol Addiction, Severe Visual Deficit, Sleep Disorder or Other.
Explain each area that was marked

Explain each area that was marked.
Indicate how you know this individual (friend, family member, patient, etc.).
The reporting person
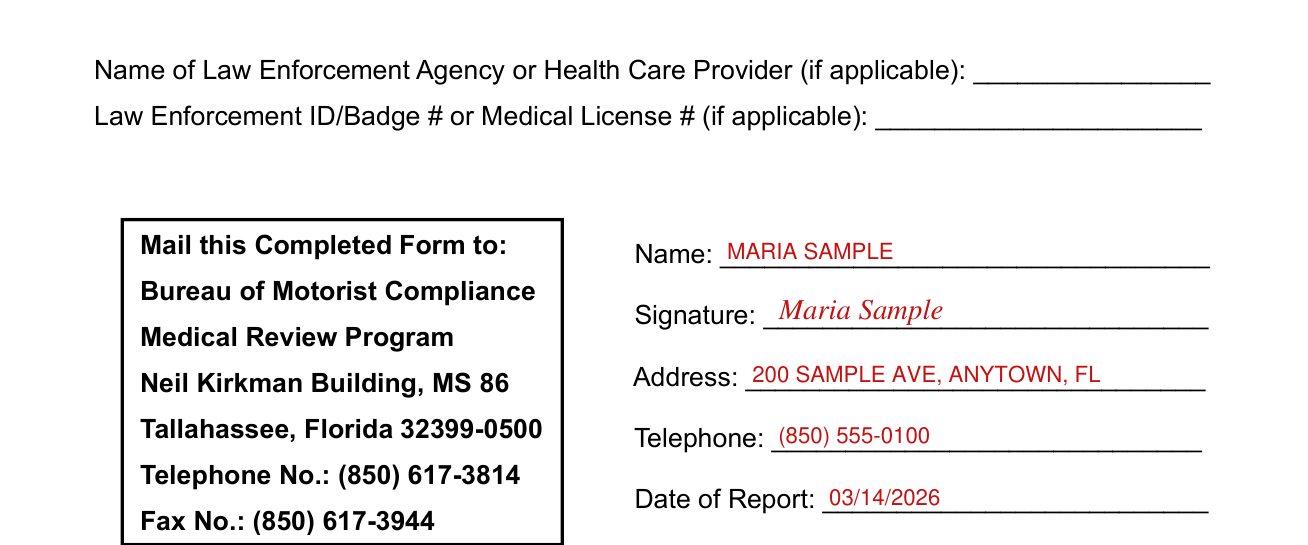
The name and signature of the reporting person is required to investigate the report.
The reporting person enters the Name, Signature, Address, Telephone and Date of Report.
If applicable, enter the Name of Law Enforcement Agency or Health Care Provider and the Law Enforcement ID/Badge # or Medical License #.
More rules for Form HSMV 72190
Under Sections 322.126(2) and (3), Florida Statutes, any physician, person, or agency having knowledge of any licensed driver's or applicant's mental or physical disability to drive is authorized to report such knowledge to the Department of Highway Safety and Motor Vehicles. The reports authorized by this section shall be confidential. No civil or criminal action may be brought against any physician, person, or agency who provides the information herein.
The Medical Review Program prints Telephone No.: (850) 617-3814 and Fax No.: (850) 617-3944.
Medical reviews are initiated based on medical conditions or symptoms that could affect the safe operation of a motor vehicle and not the age of the driver.
Common questions about Form HSMV 72190
Where do I file it?
Mail this Completed Form to: Bureau of Motorist Compliance, Medical Review Program, Neil Kirkman Building, MS 86, Tallahassee, Florida 32399-0500.
Sources
[1] Form HSMV 72190, Medical Referral Form, Florida Department of Highway Safety and Motor Vehicles (the Official source link on this page).