

Health Care Worker Waiver Application at a glance
What it is: Health Care Worker Waiver Application: all information requested must be provided before you will be considered for a waiver; All Fields must be completed or application will not be processed.
Where and when to file: Mail this completed form, along with all supporting documents, to Illinois Department of Public Health, Health Care Worker Registry, 525 W. Jefferson St., Springfield, IL 62761.
What to bring and attach to Health Care Worker Waiver Application
A copy, of the following items may be submitted with this application but are not required. (This material will not be returned to you.)
1. A current or recent employment reference. 2. A character reference. 3. Other evidence demonstrating the ability of the applicant to perform the employment responsibilities competently and evidence that the applicant does not pose as a threat to the health or safety of residents, patients or clients.
A filled-in Health Care Worker Waiver Application example: an applicant fills out page one

How to fill out Health Care Worker Waiver Application, box by box
Name, Today's Date, Address, Maiden Name, Email Address, Phone Number and Social Security Number

Enter your Name (First, Full Middle, and Last) and Today's Date.
Enter your Address (Street, Apartment #, P. 0. Box, City, State, ZIP Code).
Enter your Maiden Name (or other name(s) used) and Email Address.
Enter your Phone Number and Social Security Number (REQUIRED).
Male, Female, Race, Height, Weight, Hair Color, Eye Color, Date of Birth and Place of Birth

Mark Male or Female. Under Race, enter a letter from the list. Enter your Height, Weight, Hair Color and Eye Color.
A Chinese, Japanese, Filipino, Korean, Polynesian, Indian, Indonesian, Asian Indian, Samoan, or any other Pacific Islander. B Black or African American (Not Hispanic or Latino). H Hispanic or Latino (Mexican, Puerto Rican, Cuban, Central or South American, or other Spanish culture or origin). I American Indian, Eskimo, or Alaskan native, or a person having origins in any of the 48 contiguous states of the United States or Alaska who maintains cultural identification through tribal affiliation or community recognition. U Of undetermined race or of untold mixture. W Caucasian (not Hispanic or Latino).
Enter your Date of Birth and Place of Birth.
Work History: Employer, Start Date, Separation Date and Employer's Address

If you have previously been employed, you must provide an entire work history or attach a complete resume. Start with your current employer. Attach addition pages if necessary.
Enter the Employer, Start Date and Separation Date, and the Employer's Address (City, State, ZIP Code).
Other states where you have lived or worked

Enter the other states where you have lived or worked.
Rehabilitation program

If the use of alcohol or other drugs was involved in your offense, were you ordered to participate in a rehabilitation program as part of the judgment? Mark Yes or No. If yes, you must provide proof of successful completion of the rehabilitation program.
Fine in connection to a disqualifying offense, probation, mandatory supervised release, or parole

Were you required to pay a fine in connection to a disqualifying offense? If yes, you must provide proof of having paid all fines unless you are on a payment schedule. If on a payment schedule, you must provide proof that you are up-to-date on the schedule.
If you were released on probation, mandatory supervised release, or parole, you must provide proof of having successfully completed it.
Certified as a nurse aide/assistant in another state and Name used when certified
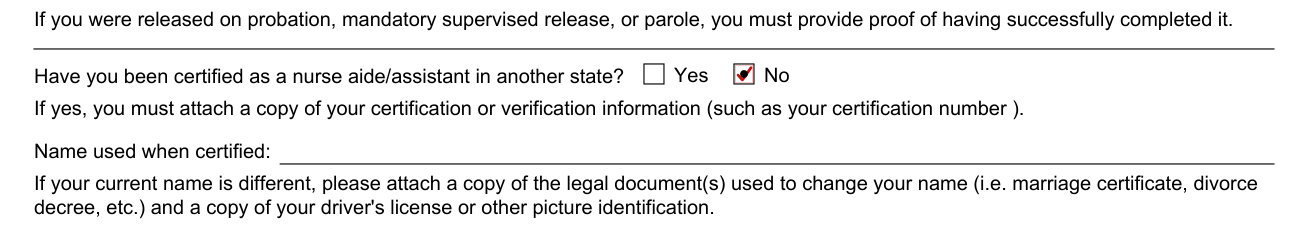
Have you been certified as a nurse aide/assistant in another state? If yes, you must attach a copy of your certification or verification information (such as your certification number).
Name used when certified: If your current name is different, please attach a copy of the legal document(s) used to change your name (i.e. marriage certificate, divorce decree, etc.) and a copy of your driver's license or other picture identification.
Administrative Finding of Abuse, Neglect, and/or Theft

Have you ever had an Administrative Finding of Abuse, Neglect, and/or Theft issued by the Illinois Department of Public Health or the Illinois Department of Human Services? Mark Yes or No. If "Yes," indicate in what state this finding was issued.
Convicted of a criminal offense, other than a minor traffic violation
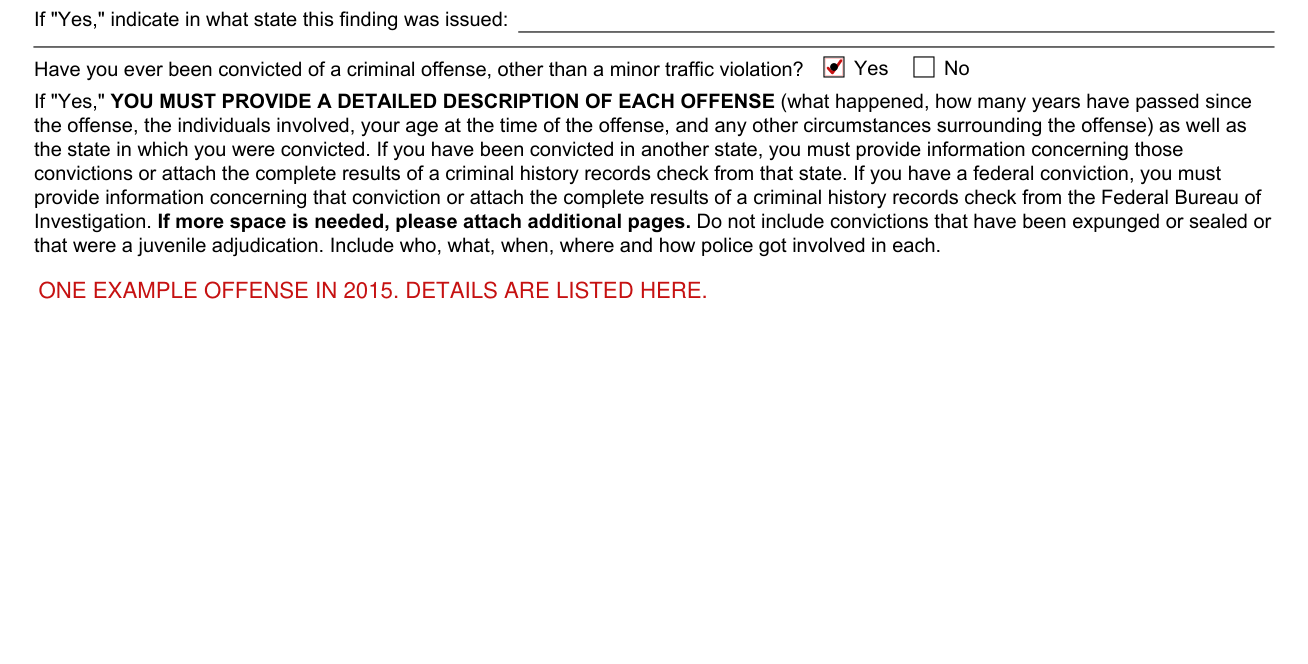
Have you ever been convicted of a criminal offense, other than a minor traffic violation? If "Yes," YOU MUST PROVIDE A DETAILED DESCRIPTION OF EACH OFFENSE (what happened, how many years have passed since the offense, the individuals involved, your age at the time of the offense, and any other circumstances surrounding the offense) as well as the state in which you were convicted.
If you have been convicted in another state, you must provide information concerning those convictions or attach the complete results of a criminal history records check from that state.
If you have a federal conviction, you must provide information concerning that conviction or attach the complete results of a criminal history records check from the Federal Bureau of Investigation.
If more space is needed, please attach additional pages.
Do not include convictions that have been expunged or sealed or that were a juvenile adjudication. Include who, what, when, where and how police got involved in each.
SIGN: Signature and Date

By signing you certify that the form is true and correct and give your consent for your name to appear on the Department's Health care Worker Registry with the results of your criminal history records check. Sign on the Signature line and enter the Date.
SIGN: parent or guardian Signature and Date

As the parent or guardian of the named individual, who is younger than the age of 17, you give your consent for this named individual to appear on the Department's Health Care Worker Registry with the results of his/her criminal history records check. The parent or guardian signs and dates the second Signature line.
More rules for Health Care Worker Waiver Application
The information requested for sex, race, height, weight, eye color, and date of birth is for the sole purpose of identification, the gathering of the mentioned information and the processing of this waiver application. This information will not be used to discriminate against you in violation of the law. The provision of your Social Security number is required by law. A facsimile or photographic copy of this authorization will be as valid as the original.
Before you go
Before a waiver can be granted, there must be a record of your criminal history background check listed on the Health Care Worker Registry. If there is not one, you must be fingerprinted by a Livescan fingerprint vendor authorized by the Illinois Department of Public Health (IDPH) and undergo a fingerprint-based criminal history records check. No other background check will be accepted for purposes of a waiver. IDPH will not initiate a Livescan request for you to be fingerprinted. The Department's designee that trains or tests health care workers, a staffing agency, a health care employer, a workforce intermediary, or an organization providing pro bono legal services must initiate the Livescan request and ask you to report for fingerprints. A health care employer shall not be liable for the failure to hire or retain an applicant or employee who has been convicted of committing or attempting to commit one or more of the offenses stated in the Health care Worker Background Check Act [225 ILCS 46/25].
Common questions about Health Care Worker Waiver Application
Where do I file it?
Alternatively, you may fax this form and supporting documents to (217) 524-3479 or scan (as a PDF document) and e-mail this form and supporting documents to DPH.HCWR@illinois.gov.
Sources
[1] Health Care Worker Waiver Application (2/26 IOCI 26-1136), Illinois Department of Public Health (the Official source link on this page).
