

Form IMM-75 at a glance
What it is: The Immunization Record lists the Vaccine, Date Given and Next Dose Due, and TB Tests/Risk Assessment.
Where and when to file: Parents: Your child must meet California's immunization requirements to be enrolled in school and child care.
A filled-in Form IMM-75 example: a clinic records the first Hepatitis B dose
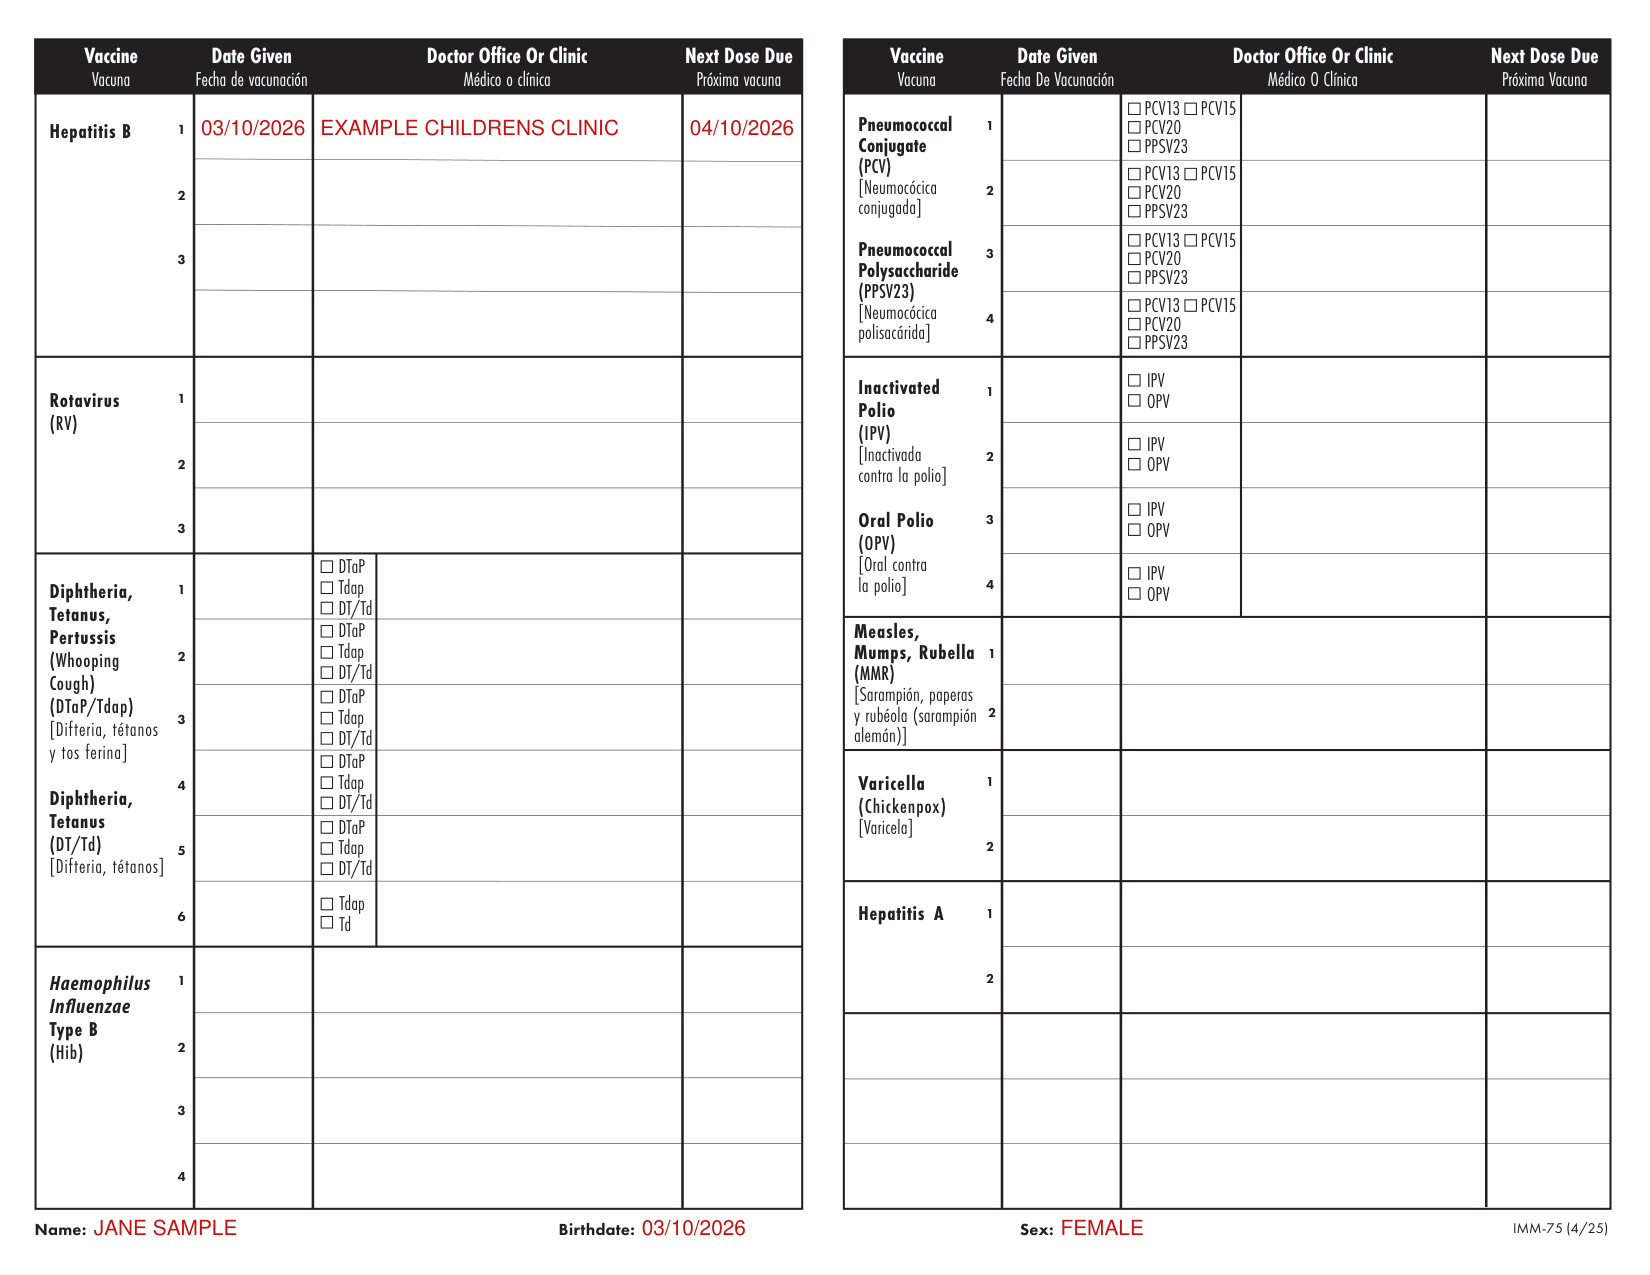
How to fill out Form IMM-75, box by box
Name, Birthdate and Sex

Enter the Name, the Birthdate and the Sex.
Enter the Name, the Birthdate and the Sex on page 2 too.
Allergies and Vaccine Reactions

Enter the Allergies and the Vaccine Reactions.
Vaccine, Date Given, Doctor Office Or Clinic and Next Dose Due
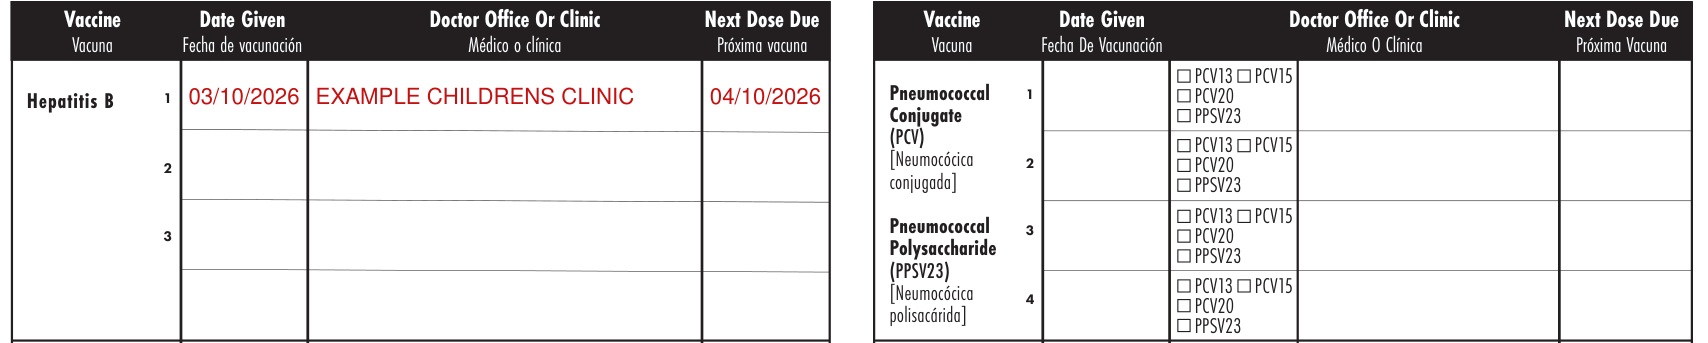
For each Vaccine, enter the Date Given, the Doctor Office Or Clinic and the Next Dose Due.
Vaccines listed: Human Papillomavirus; Meningococcal Conjugate; Serogroup B Meningococcal (Men B); Inactivated Influenza; Nasal Spray Influenza (LAIV); COVID-19 (Coronavirus); Respiratory Syncytial Virus (RSV); Pneumococcal Conjugate (PCV); Pneumococcal Polysaccharide (PPSV23); Inactivated Polio (IPV); Oral Polio (OPV); Rotavirus (RV); Diphtheria, Tetanus, Pertussis (Whooping Cough); Diphtheria, Tetanus; Measles, Mumps, Rubella (MMR); Varicella (Chickenpox); Hepatitis A; Hepatitis B; and Haemophilus Influenzae Type B (Hib).
COVID-19 (Coronavirus) prints Moderna, Pfizer, Novavax and Other.
Respiratory Syncytial Virus (RSV) prints Mom and Infant.
TB Tests/Risk Assessment
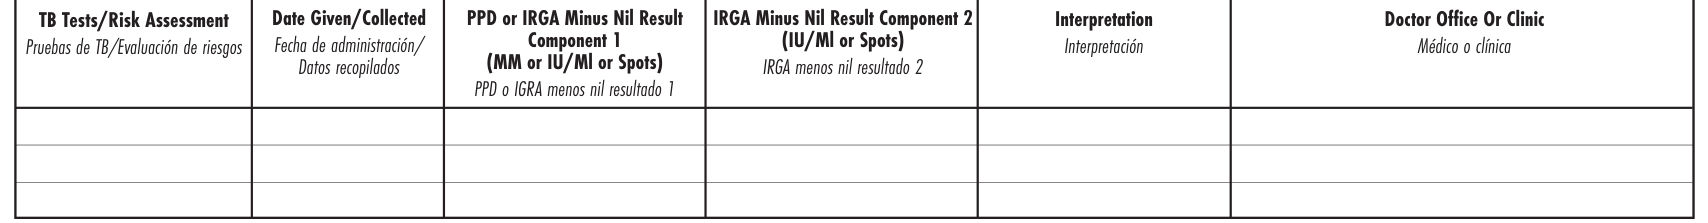
For TB Tests/Risk Assessment, enter the Date Given/Collected, the PPD or IRGA Minus Nil Result, the Interpretation and the Doctor Office Or Clinic.
Enter Component 1 in MM or IU/ml or Spots.
Enter IRGA Minus Nil Result Component 2 in IU/ml or Spots.
If your situation is different
You are a parent
Parents: Your child must meet California's immunization requirements to be enrolled in school and child care.
Keep this Record as proof of immunization.
You are a provider using combination vaccines
Providers: If using combination vaccines, remember to record dose in all appropriate spaces.
Sources
[1] Form IMM-75 (4/25), Immunization Record, California Department of Public Health (the Official source link on this page).
