


IMRF Form 5.41 at a glance
What it is: IMRF Form 5.41, the Employer Statement-Disability Claim: by furnishing this information, the employer makes NO representation regarding the validity of the member's claim for disability benefits.
Who signs: The Authorized Agent signs and dates the form (MM/DD/YYYY).
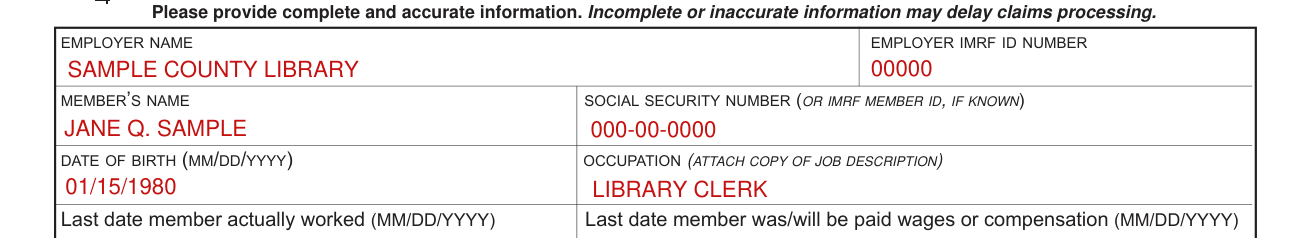
A filled-in IMRF Form 5.41 example: an employer reports a member's disability

How to fill out IMRF Form 5.41, box by box
Complete this form: employer and member
1. Complete this form: a. As soon as the member has stopped working and is expected to remain disabled for thirty (30) days or more. b. Whether the disabling condition is work-related or not. 2. "Last date the member actually worked" refers to the last day the member was physically present at his or her job. This does not include sick or vacation time. 3. "Last date the member was or will be paid" refers to the last day for which the member will receive wages (or compensation), including sick and vacation time. 4. The Authorized Agent's signature is required for all claims. 5. Print the member's Social Security Number (or IMRF Member ID, if known) on all documents you enclose with this form. 6. Do not return this Instruction sheet; return the form only.
Enter the Employer Name and the Employer IMRF ID Number.
Enter the Member's Name and the Social Security Number (or IMRF Member ID, if known).
Enter the Date of Birth (MM/DD/YYYY) and the Occupation, and attach a copy of the job description.
Last date member actually worked, last date paid and off work for the same injury or illness

Enter the last date member actually worked (MM/DD/YYYY), not including sick or vacation days.
Enter the last date member was/will be paid wages or compensation (MM/DD/YYYY), including vacation pay, sick pay, etc., NOT the date of the member's paycheck.
Mark No or Yes: within the past 6 months, has the member been off work for the same injury or illness?
Pre-employment medical examination, Elected Official and the ECO Plan

For members with less than five years of IMRF service credit, mark No or Yes: did the member undergo a pre-employment medical examination? If yes, attach a copy of doctor's report to this form and print the member's Social Security number or IMRF Member ID, if known on the report.
Mark No or Yes: is the member an Elected Official?
If yes, mark No or Yes: does the member participate in the ECO Plan? If yes, complete the section to be completed for ECO members only.
For ECO members only, enter the dates for the ECO member's term of office; if the member is not currently in office, provide dates for the last elected county office held, FROM (MM/DD/YYYY) TO (MM/DD/YYYY).
For ECO members only, enter the member's final annual salary and the member's annual stipend(s) earned as a member of the ECO Plan.
Seasonal employee, returned to work and terminated
Mark No or Yes: is the member a seasonal employee? If yes, mark No or Yes: did the member elect to be paid over 12 months?
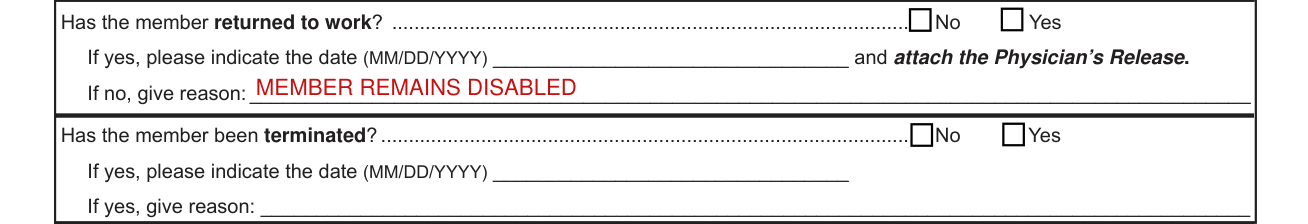
Mark No or Yes: has the member returned to work? If yes, indicate the date (MM/DD/YYYY) and attach the Physician's Release.
If the member has not returned to work, give the reason.
Mark No or Yes: has the member been terminated? If yes, indicate the date (MM/DD/YYYY) and give the reason.
Workers' compensation or occupational disease benefits
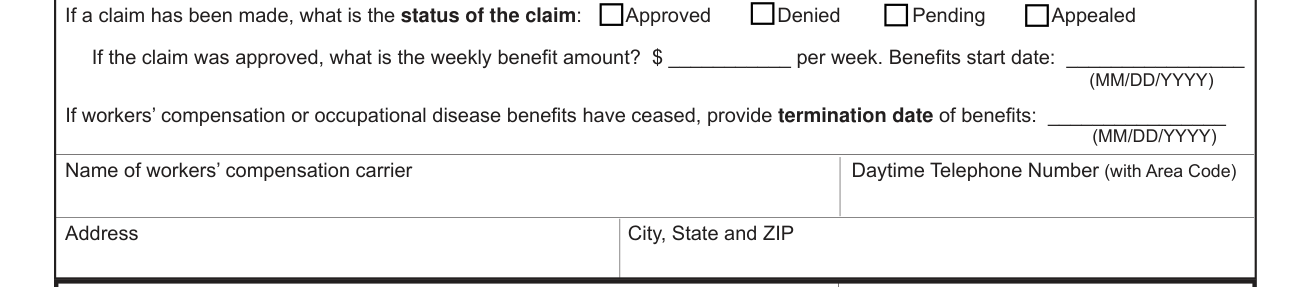
Mark No or Yes: was a claim made for workers' compensation or occupational disease benefits?
If a claim has been made, mark the status of the claim: Approved, Denied, Pending or Appealed. If the claim was approved, enter the weekly benefit amount.
Enter the benefits start date (MM/DD/YYYY). If workers' compensation or occupational disease benefits have ceased, provide the termination date of benefits (MM/DD/YYYY).
If a claim has been made, enter the Name of workers' compensation carrier, its Daytime Telephone Number (with Area Code), Address, and City, State and ZIP.
Authorized Agent's Signature

Sign on the Authorized Agent's Signature line and enter the Date (MM/DD/YYYY). Enter the Daytime Telephone Number (with Area Code) and Email.
More rules for IMRF Form 5.41
Disability benefit payments can be reduced or terminated if the member receives wages (or compensation) in any month he or she is disabled, or resigns. If the member resigns, forward a copy of the resignation letter and supporting documents, and include meeting minutes accepting the resignation.
Provide complete and accurate information: incomplete or inaccurate information may delay claims processing.
Sources
[1] IMRF Form 5.41 (Rev. 02/2013), Employer Statement-Disability Claim, Illinois Municipal Retirement Fund (the Official source link on this page).