


State Form 51654 at a glance
What it is: State Form 51654 is the Qualified Medication Aide (QMA) Record of Annual Inservice Training of the Indiana Department of Health.
Who signs: Sign on the QMA Signature line (typed name is acceptable) and enter the Date (mm/dd/yy).
QMA MUST keep the original form.
A filled-in State Form 51654 example: a QMA lists four inservices
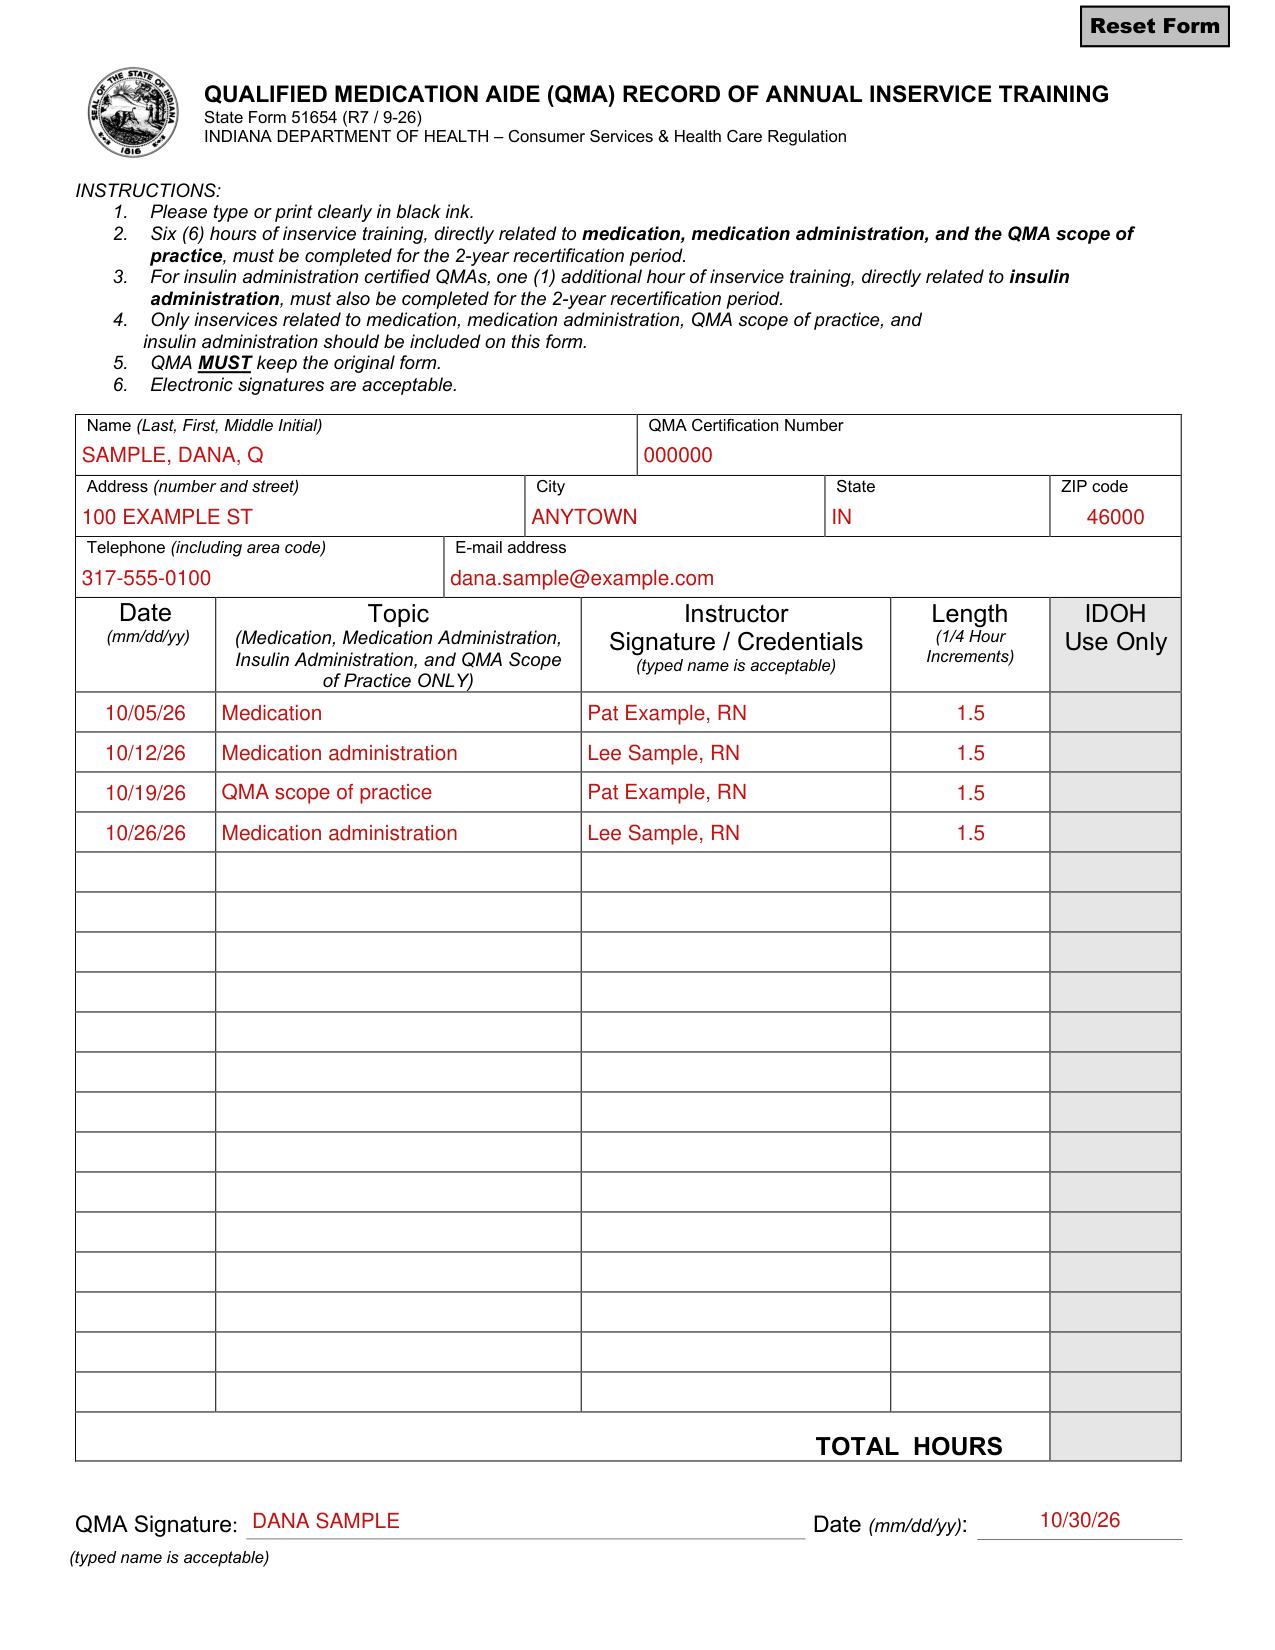
How to fill out State Form 51654, box by box
Name, certification number and address

Enter the Name (Last, First, Middle Initial) and the QMA Certification Number.
Enter the Address (number and street), City, State and ZIP code.
Enter the Telephone (including area code) and the E-mail address.
Date, topic, instructor and length
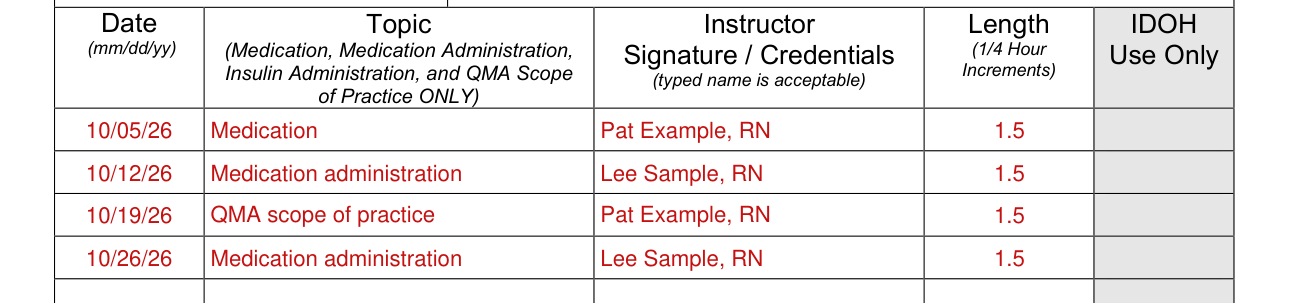
Enter the Date (mm/dd/yy) and the Topic (Medication, Medication Administration, Insulin Administration, and QMA Scope of Practice ONLY).
Enter the Instructor Signature / Credentials (typed name is acceptable).
Enter the Length (1/4 Hour Increments).
QMA signature and date

Sign on the QMA Signature line (typed name is acceptable) and enter the Date (mm/dd/yy).
More rules for State Form 51654
Six (6) hours of inservice training, directly related to medication, medication administration, and the QMA scope of practice, must be completed for the 2-year recertification period.
For insulin administration certified QMAs, one (1) additional hour of inservice training, directly related to insulin administration, must also be completed for the 2-year recertification period.
Only inservices related to medication, medication administration, QMA scope of practice, and insulin administration should be included on this form.
Electronic signatures are acceptable.
Please type or print clearly in black ink.
The IDOH use only boxes and TOTAL HOURS are filled out by IDOH.
Sources
[1] State Form 51654 (R7 / 9-26), Qualified Medication Aide (QMA) Record of Annual Inservice Training, Indiana Department of Health (the Official source link on this page).