

Form F-20445 at a glance
What it is: Form F-20445 (09/2022) is the State of Wisconsin Department of Health Services Individual Service Plan for the Children's Long-Term Support Programs.
Who signs: ISP signatures are required at the time of plan development, review, and recertification.
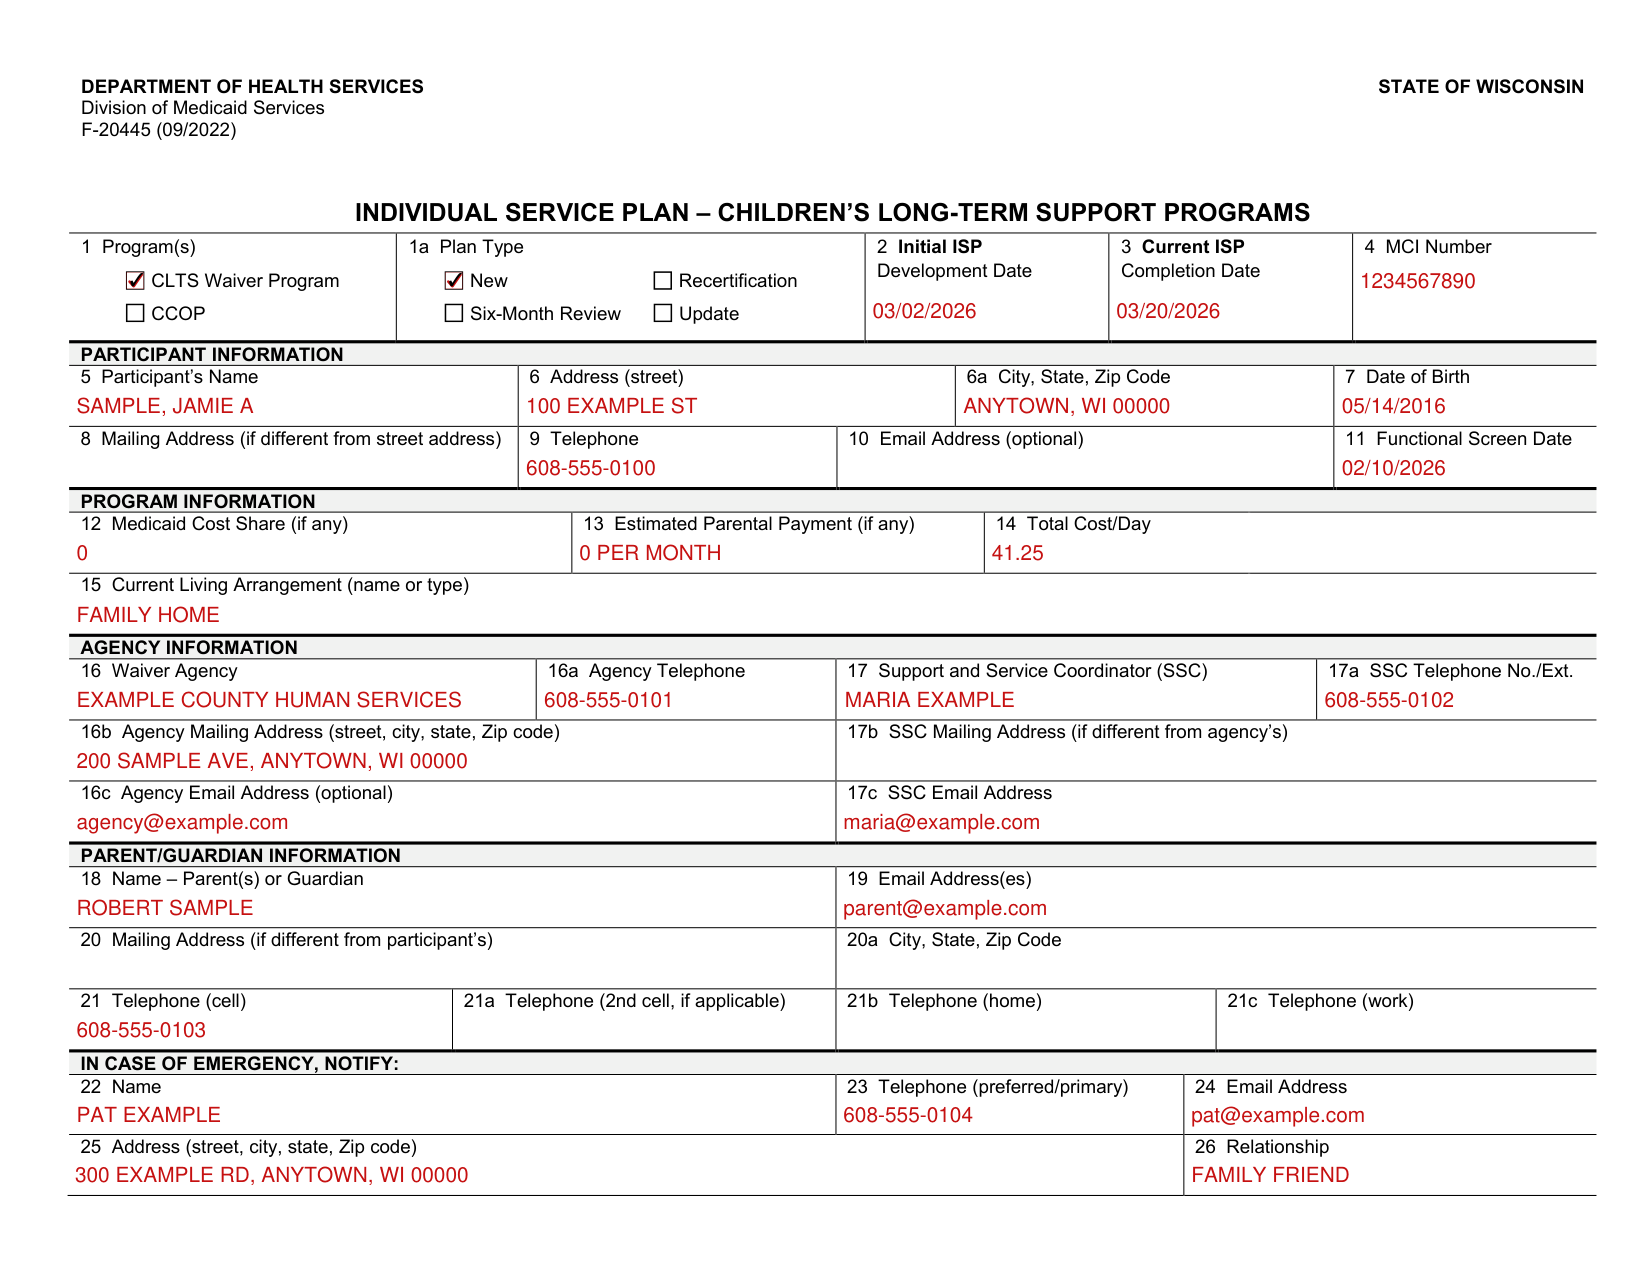
A filled-in Form F-20445 example: a coordinator plans a new waiver enrollment
How to fill out Form F-20445, box by box
Program(s), plan type and dates

Box 1, Program(s): Indicate the program(s) in which the participant is enrolled.
Box 1a, Plan Type: Check “New” when the plan is for a participant who is newly enrolling.
Check “Six-Month Review” when the plan is the result of a required six-month face-to-face review.
Check “Recertification” when the plan is the result of the required annual ISP review and program recertification.
Check “Update” when, at another time of year, the plan replaces an earlier plan and includes a change.
Box 2, Initial ISP Development Date: The date on which the service planning process was first initiated.
Common mistake: The participant's enrollment date must be on or after the date in this field. In other words, the enrollment date cannot be before the initial ISP development date.
Box 3, Current ISP Completion Date: The date on which the current service plan was accepted by all parties involved in its development.
Box 4, MCI Number: The participant's 10-digit MCI (Master Client Index) number, if known.[2]
Participant information

Box 5, Participant's Name: The participant's full legal name: last name, first name, middle initial, and any suffix.
Boxes 6 to 6a, Address, City, State, ZIP Code: The place where the participant resides.
Box 7, Date of Birth. Box 8, Mailing Address: The address where the person receives mail, if different from where they reside.
Box 9, Telephone: The area code and telephone number at the place the person resides.
Box 10, Email Address: The email address of the participant, if they have one they would like to share.
Box 11, Functional Screen Date: The date the most recent Wisconsin Children's Long-Term Support Functional Screen (CLTS FS) eligibility results were determined.[2]
Cost share, parental payment, total cost per day and living arrangement

Box 12, Medicaid Cost Share: Enter any cost share amount as determined on the Medicaid Waiver Eligibility and Cost Sharing Worksheet, F-20919. When a CLTS Waiver Program participant's primary source of Medicaid is HCBW, a cost share based upon the participant's income must be calculated using the F-20919.
Box 13, Estimated Parental Payment: Enter the estimated amount that the parents or legal guardians may be required to contribute to the overall cost of the participant's CLTS and CCOP services.
Indicate if the estimated amount is per month or annually. This amount is calculated using the Worksheet for Determination of Parental Payment Limit, F-01337.
Box 14, Total Cost/Day: Enter the total daily cost of ongoing CLTS- and CCOP-funded services and start-up or one-time costs. To calculate, add the daily costs of CLTS- and CCOP-funded services that are listed in field 34 on the ISP.
Common mistake: Do not include ongoing items or services that are closed or have not yet begun, any program administration costs, or costs for items or services that are covered by the Medicaid card or another funding source in this amount.
Box 15, Current Living Arrangement: The type of residence in which the person lives or is expected to reside when they begin services.[2]
Waiver agency and Support and Service Coordinator

Boxes 16 to 16c, Waiver Agency Contact Information: The name, phone number, physical address, and email address of the county, tribal, or contract agency responsible for authorizing and monitoring the individual's services.
Boxes 17 to 17c, Support and Service Coordinator Contact Information: The name and contact information for the SSC who is working with the family and is responsible for monitoring and updating the plan. Enter the phone number where the SSC can best be reached.[2]
Parent/Guardian information
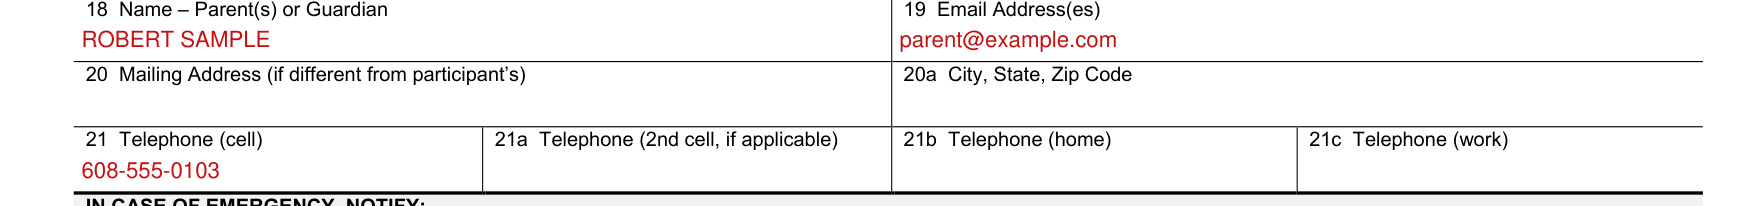
Box 18, Name, Parent(s) or Guardian: For participants who are minors, list the parent(s) or the guardian. For participants who are adults, list the guardian, or enter the word “self” if the person does not have a legal guardian.
Boxes 20 to 20a, Mailing Address, and Boxes 21 to 21c, Telephone Numbers: Include the area codes.[2]
Emergency contact information

Box 22, Name: Name of the person designated as the waiver participant's emergency contact.
Box 23, Telephone (preferred/primary): List the number where the emergency contact can best be reached.
Box 24, Email Address. Box 25, Address. Box 26, Relationship: Word or phrase that describes how the emergency contact is related to the participant.[2]
Service plan, boxes 27 to 35
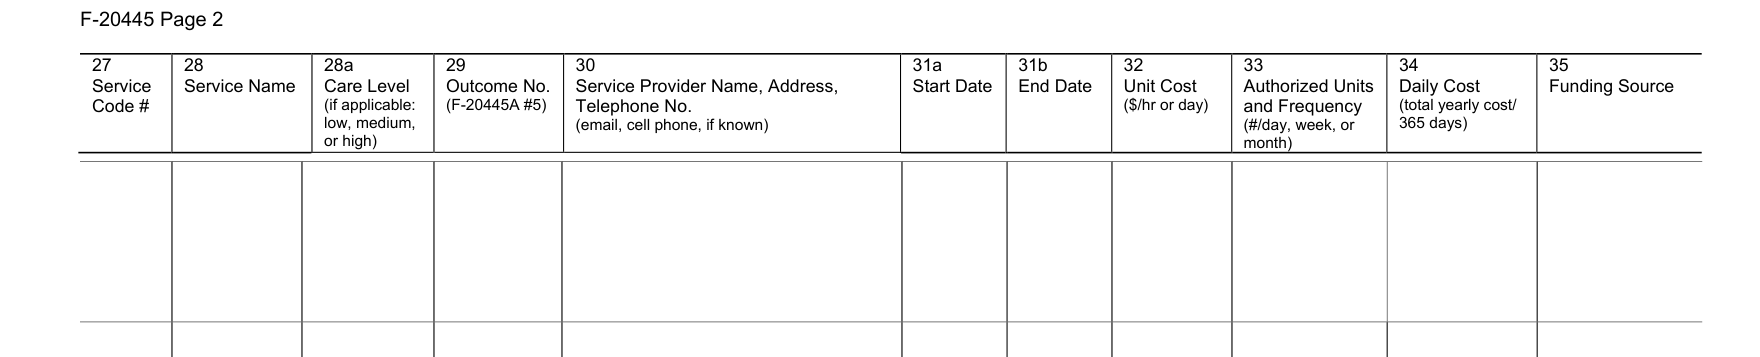
Page 2, Box 27, Service Code Number: The three- or five-digit SPC code assigned to the particular service. This code only applies to services that are covered by the CLTS Waiver Program or CCOP. Medicaid card services and informal supports, for example, do not have an SPC.
Box 28, Service Name: If the service is provided through the CLTS Waiver or CCOP, list the SPC name. If the service is not waiver- or CCOP-funded, use a word or phrase that describes the type of support or service. Include all formal and informal supports.
Common mistake: Box 28a, Care Level: This field is only required for CLTS waiver services that require a care level determination. For those services, indicate a “Low,” “Medium,” or “High” classification based on the CLTS care level guidelines.
Box 29, Outcome Number: From the F-20445A (field 5), enter the number(s) of the outcome(s) the service corresponds to or is being provided to meet.
Box 30, Service Provider Contact Information: The individual/agency name, address, email, and phone number(s) of the service provider.
Box 31a, Start Date: The date on which the service will begin. Box 31b, End Date: The date on which the service will stop, if applicable.
Box 32, Unit Cost: The cost per unit of the CLTS waiver or CCOP service.
Box 33, Authorized Units of Service and Frequency: The number of units of the service the county authorizes for this participant during a specified period of time (e.g., unit/day, week, or month). Only applies to CLTS Waiver and CCOP supports and services.
Box 34, Daily Cost: The total cost of the CLTS Waiver or CCOP-funded service for the year, divided by 365 days.
Box 35, Funding Source: List the source of funding for the service or support.[2]
Outlier rate

Box 36, Outlier Rate: Check this box when any service listed on this ISP uses a DHS-approved outlier rate. Indicate if any unit cost for a service listed on the ISP is an approved DHS-outlier rate.[2]
Participant-informed rights and choice

Box 37, Participant-Informed Rights and Choice: Review REQUIRED at initial plan development and recertification. Topics that must be discussed with the participant and parent(s)/guardian include: Right to choose between institutional services and the waiver program. Right to choose types of services and providers. Notification of participant rights and responsibilities, verbally and in writing. Including the right to request a hearing regarding eligibility determinations and/or denial, reduction, or termination of services. All lines apply to both CLTS Waiver and CCOP, unless otherwise indicated.
Check the box on each line. The line about the RIGHT TO CHOOSE between institutional services and community services and the line “I have chosen to accept community services through a Medicaid HCBS Waiver Program (i.e., the CLTS Waiver Program)” do not apply to CCOP-only plans.[2]
Plan review and update verification

Box 38, Review/Update Verification: Only applies to plan review or ISP update.
Signatures and dates
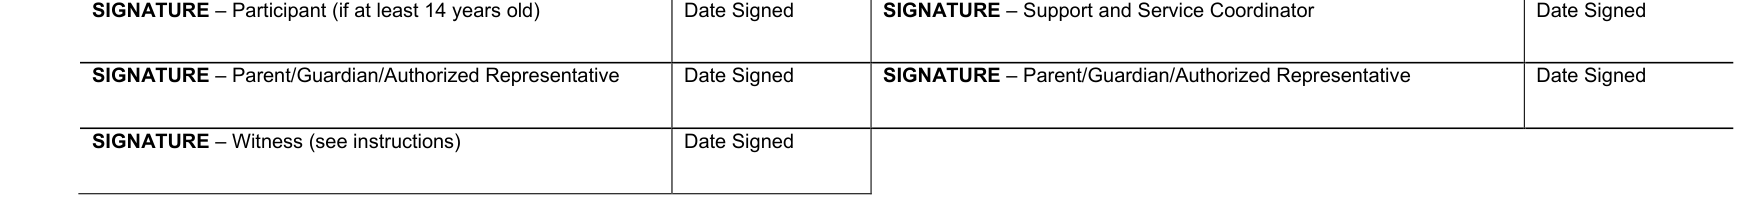
ISP signatures are required at the time of plan development, review, and recertification.
Signatures: Participant (if at least 14 years old), Support and Service Coordinator, Parent/Guardian/Authorized Representative, Parent/Guardian/Authorized Representative, Witness (see instructions), each with a Date Signed.
Participant Signature: A signature is required if the participant is age 14 or older and capable of signing the form. Make a note on the plan if a participant who is 14 or older is unable to sign.
Witness: If a participant who is at least 18 years old and who does not have a legal guardian or authorized representative is only able to sign with an “x” or a mark, have the signature witnessed by someone in addition to the SSC.
Date Signed: Include the date when each individual signs the plan.[2]
Common questions about Form F-20445
Where do I file it?
Distribution: Original, Support and Service Coordinator/Participant File; Copy, Participant/Parent/Guardian/Authorized Representative.
Sources
[1] Form F-20445 (09/2022), Individual Service Plan, Children's Long-Term Support Programs, Wisconsin Department of Health Services (the Official source link on this page).
