

Intrinsic Touch Massage Therapy Client Intake Form at a glance
What it is: Intrinsic Touch - Massage Therapy Client Intake Form.
Who signs: You have completed this client intake form to the best of your knowledge. You understand the massage services are designed to be a health aid and in no way substitute a physician's care when indicated. You understand massage therapists are not qualified to perform spinal adjustments, diagnose, prescribe, or treat any physical or mental illness. If you experience any pain or discomfort during the massage, you will immediately inform the therapist so that pressure/stroke may be adjusted to your comfort. You agree to keep the therapist updated as to any changes in your medical profile and you understand there shall be no liability on the therapist's part if you fail to do so. Sign on the Signature line and enter the Date.
A filled-in Intrinsic Touch Massage Therapy Client Intake Form example: a new client fills out the intake form
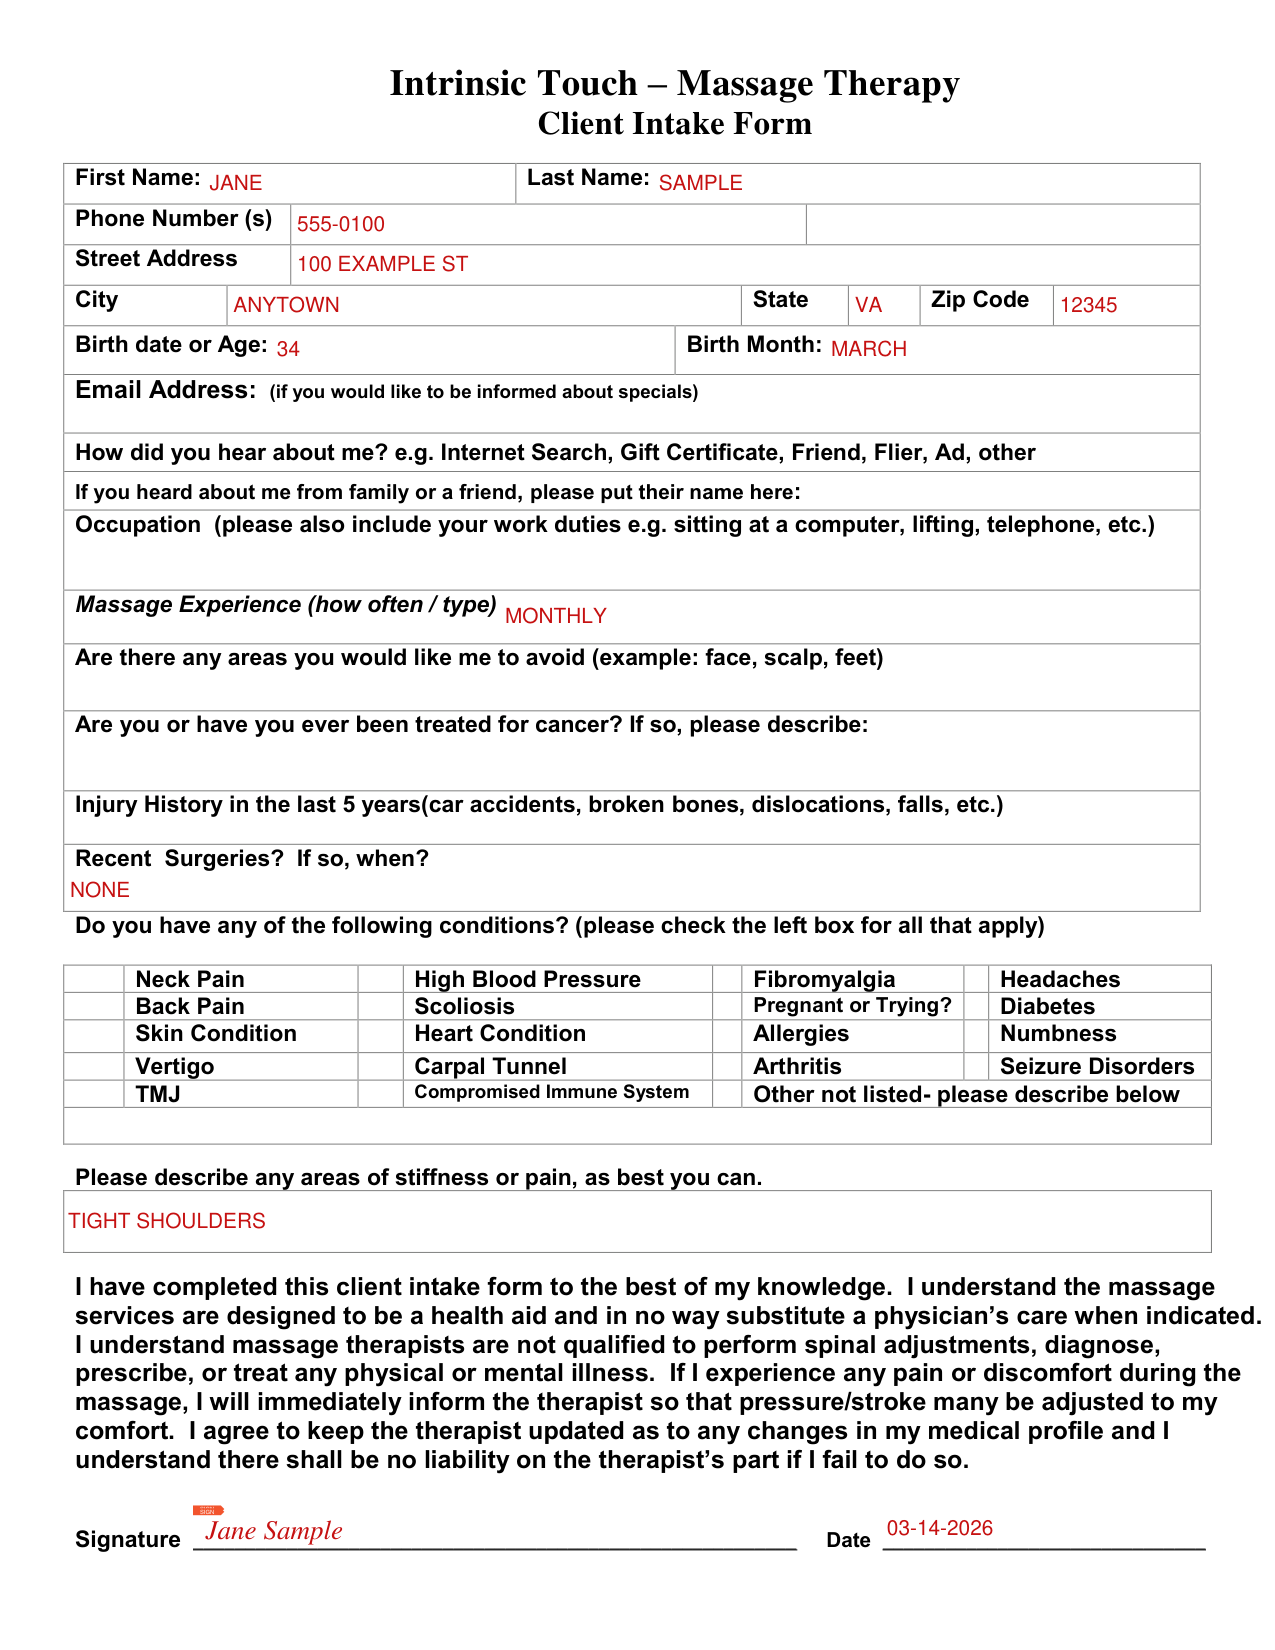
How to fill out Intrinsic Touch Massage Therapy Client Intake Form, box by box
First Name, Last Name, Phone Number, Street Address and Birth date or Age

Enter your First Name and Last Name, your Phone Number (s), your Street Address, and your City, State and Zip Code.
Enter your Birth date or Age and your Birth Month.
Email, how you heard about me, Occupation and Massage Experience
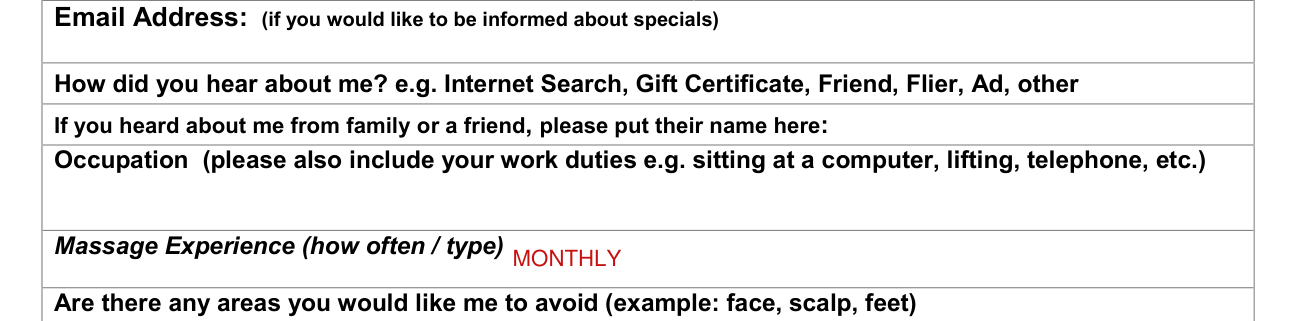
Enter your Email Address if you would like to be informed about specials.
How did you hear about me? e.g. Internet Search, Gift Certificate, Friend, Flier, Ad, other.
If you heard about me from family or a friend, please put their name here.
Enter your Occupation, and please also include your work duties e.g. sitting at a computer, lifting, telephone, etc.
Enter your Massage Experience: how often and type.
Say if there are any areas you would like me to avoid (example: face, scalp, feet).
Cancer, Injury History and Recent Surgeries
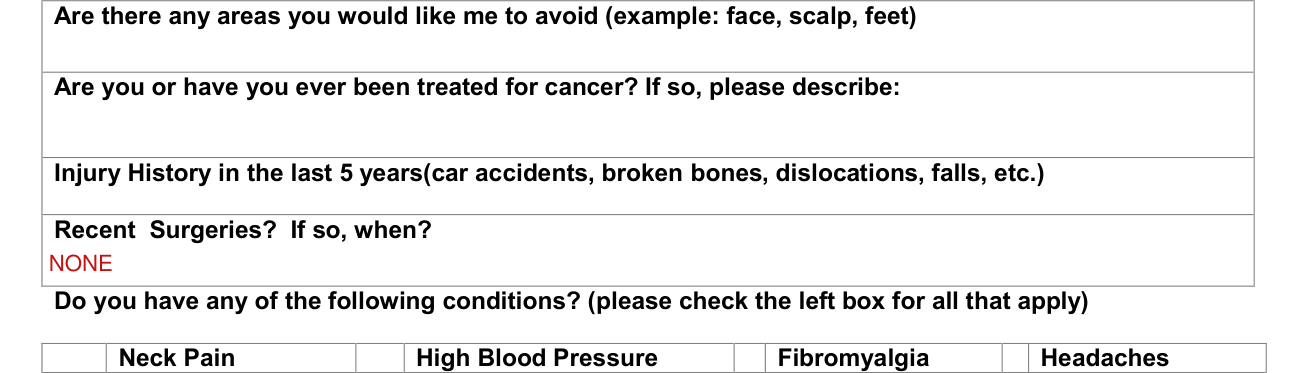
Are you or have you ever been treated for cancer? If so, please describe.
Enter your Injury History in the last 5 years (car accidents, broken bones, dislocations, falls, etc.).
Enter your Recent Surgeries and, if so, when.
Conditions you check
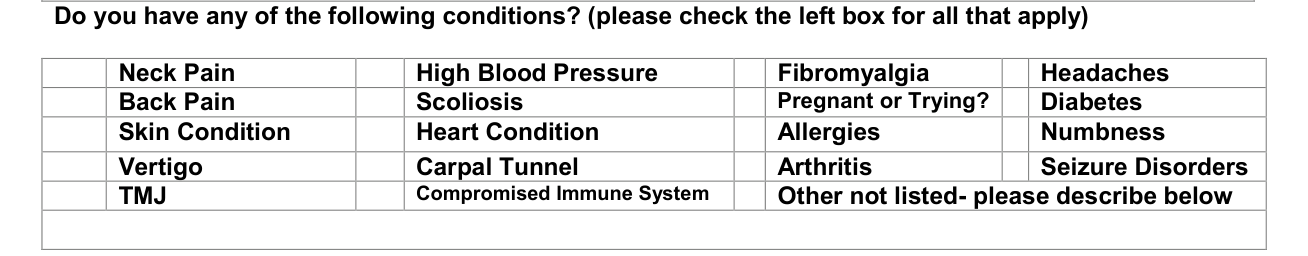
Do you have any of the following conditions? Please check the left box for all that apply.
The conditions are Neck Pain, High Blood Pressure, Fibromyalgia, Headaches, Back Pain, Scoliosis, Pregnant or Trying?, Diabetes, Skin Condition, Heart Condition, Allergies, Numbness, Vertigo, Carpal Tunnel, Arthritis, Seizure Disorders, TMJ and Compromised Immune System.
For Other not listed, please describe.
Areas of stiffness or pain

Please describe any areas of stiffness or pain, as best you can.
Sign

Sign.
Sources
[1] Intrinsic Touch - Massage Therapy Client Intake Form (2025) (the Official source link on this page).
