

Benefit Request Form at a glance
What it is: The Benefit Request Form is submitted to Key Benefit Administrators, Inc., P.O. Box 2050, Fort Mill, SC 27916-2050.
Who signs: In Box 12, the patient or authorized person signs and dates under: I authorize the Release of any Medical Information Necessary to Process this request.
A filled-in Benefit Request Form example: an employee requests benefits for a visit
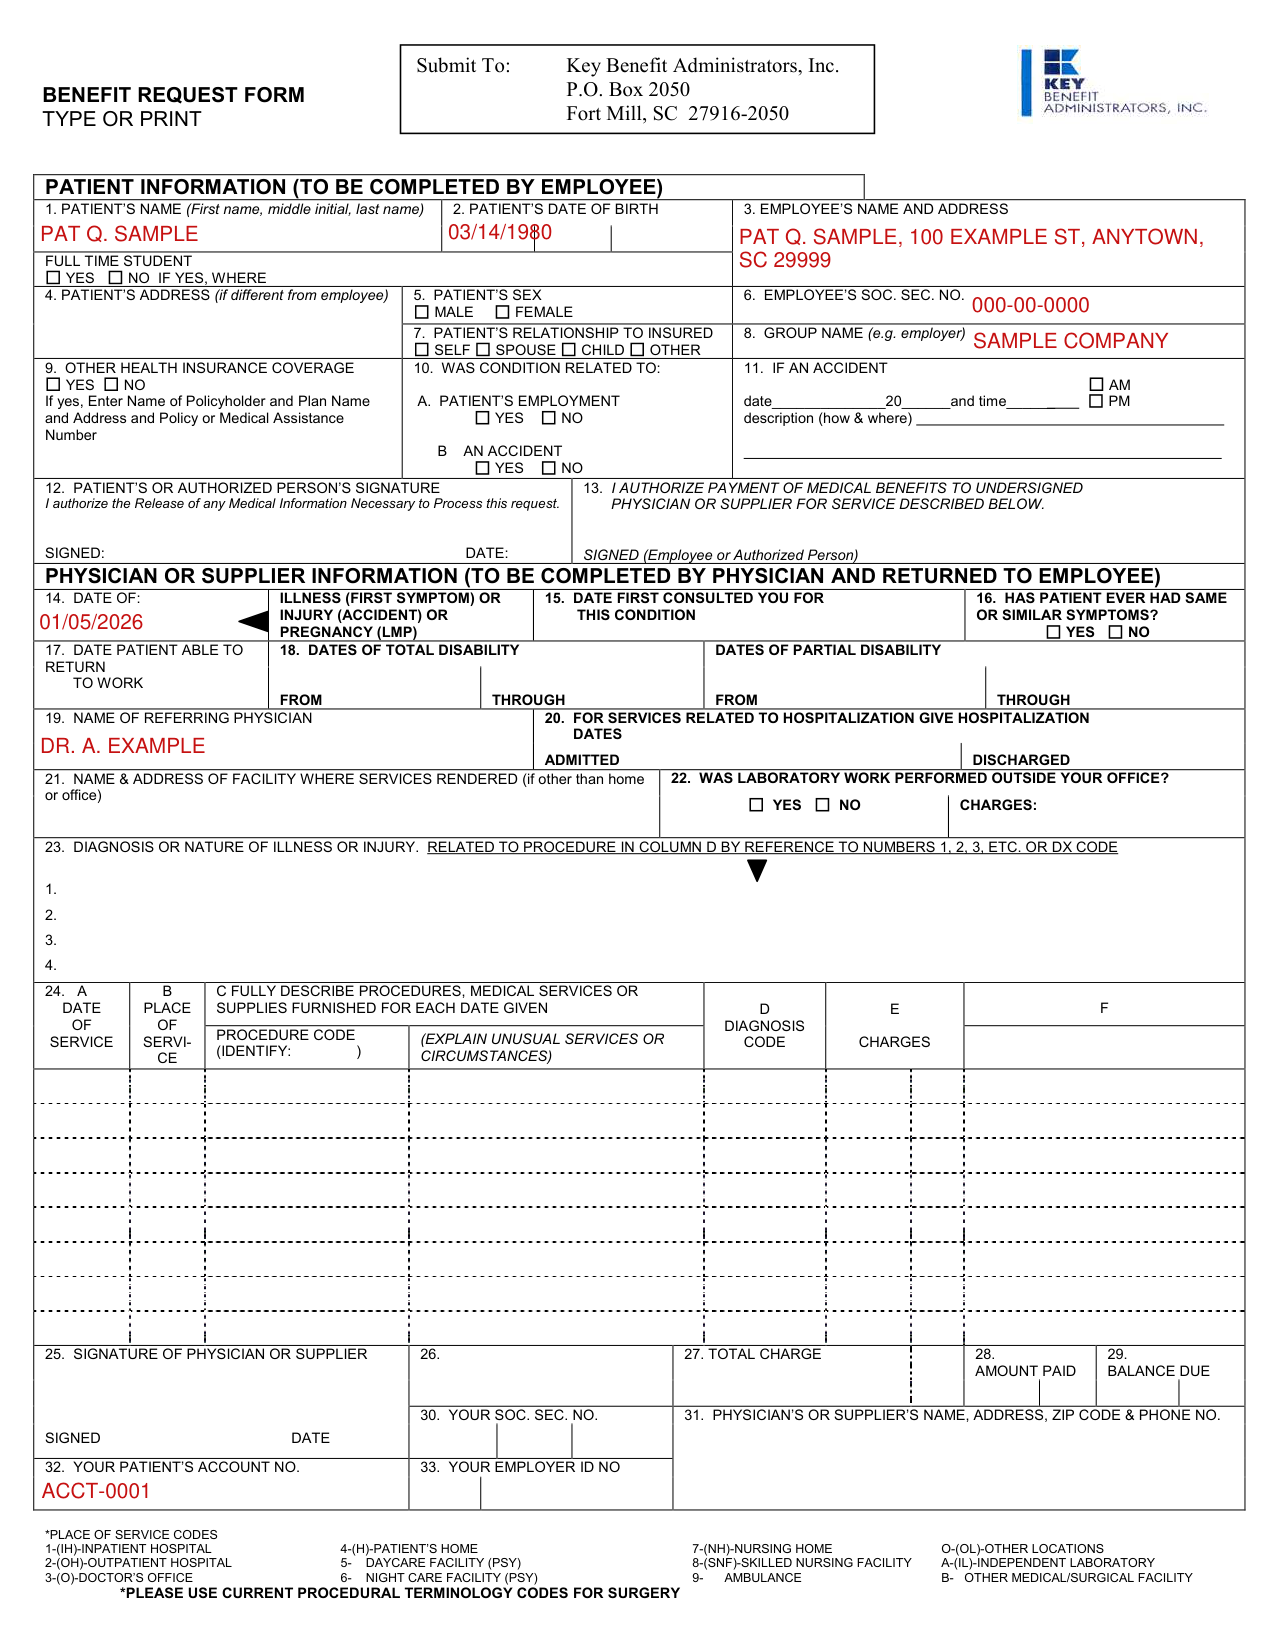
How to fill out Benefit Request Form, box by box
Patient information, completed by the employee
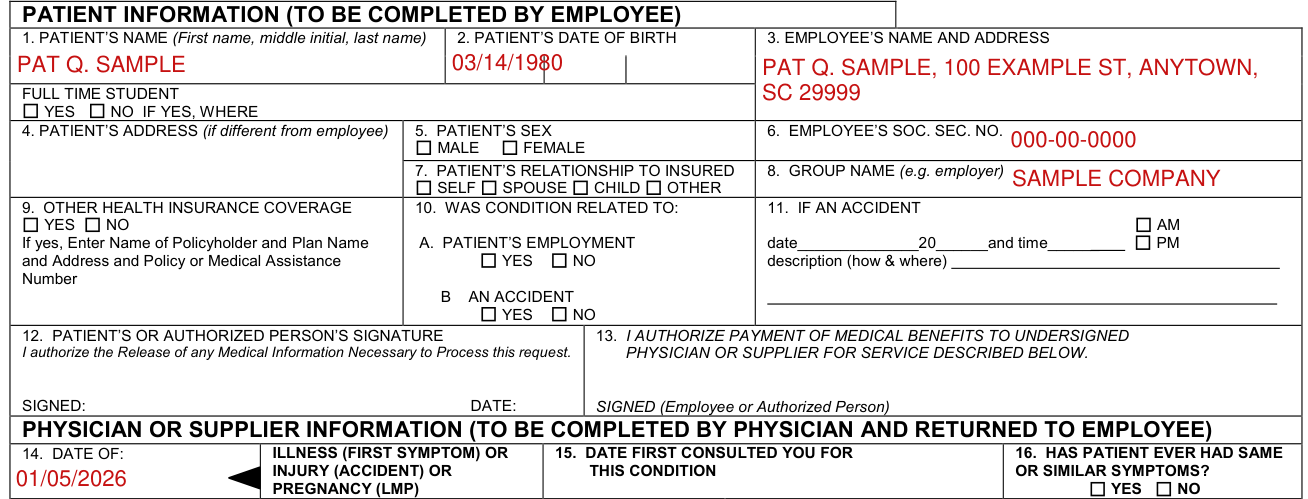
Under PATIENT INFORMATION (TO BE COMPLETED BY EMPLOYEE), enter the Patient's Name (First name, middle initial, last name), the Patient's Date of Birth and the Employee's Name and Address.
Mark YES or NO for Full Time Student; if YES, write where. Enter the Patient's Address if different from employee.
For the Patient's Sex, mark MALE or FEMALE. Enter the Employee's Soc. Sec. No.
For the Patient's Relationship to Insured, mark SELF, SPOUSE, CHILD or OTHER. Enter the Group Name (e.g. employer).
For Other Health Insurance Coverage, mark YES or NO. If yes, enter the Name of Policyholder and Plan Name and Address and Policy or Medical Assistance Number.
Box 10, Was Condition Related to: A. Patient's Employment, YES or NO; B. An Accident, YES or NO.
In Box 11, if an accident, enter the date, the time (AM or PM) and a description (how & where).
In Box 13, the Employee or Authorized Person signs to authorize payment of medical benefits to the undersigned physician or supplier for service described below. The physician or supplier information is to be completed by the physician and returned to the employee.
Physician or supplier information, completed by the physician
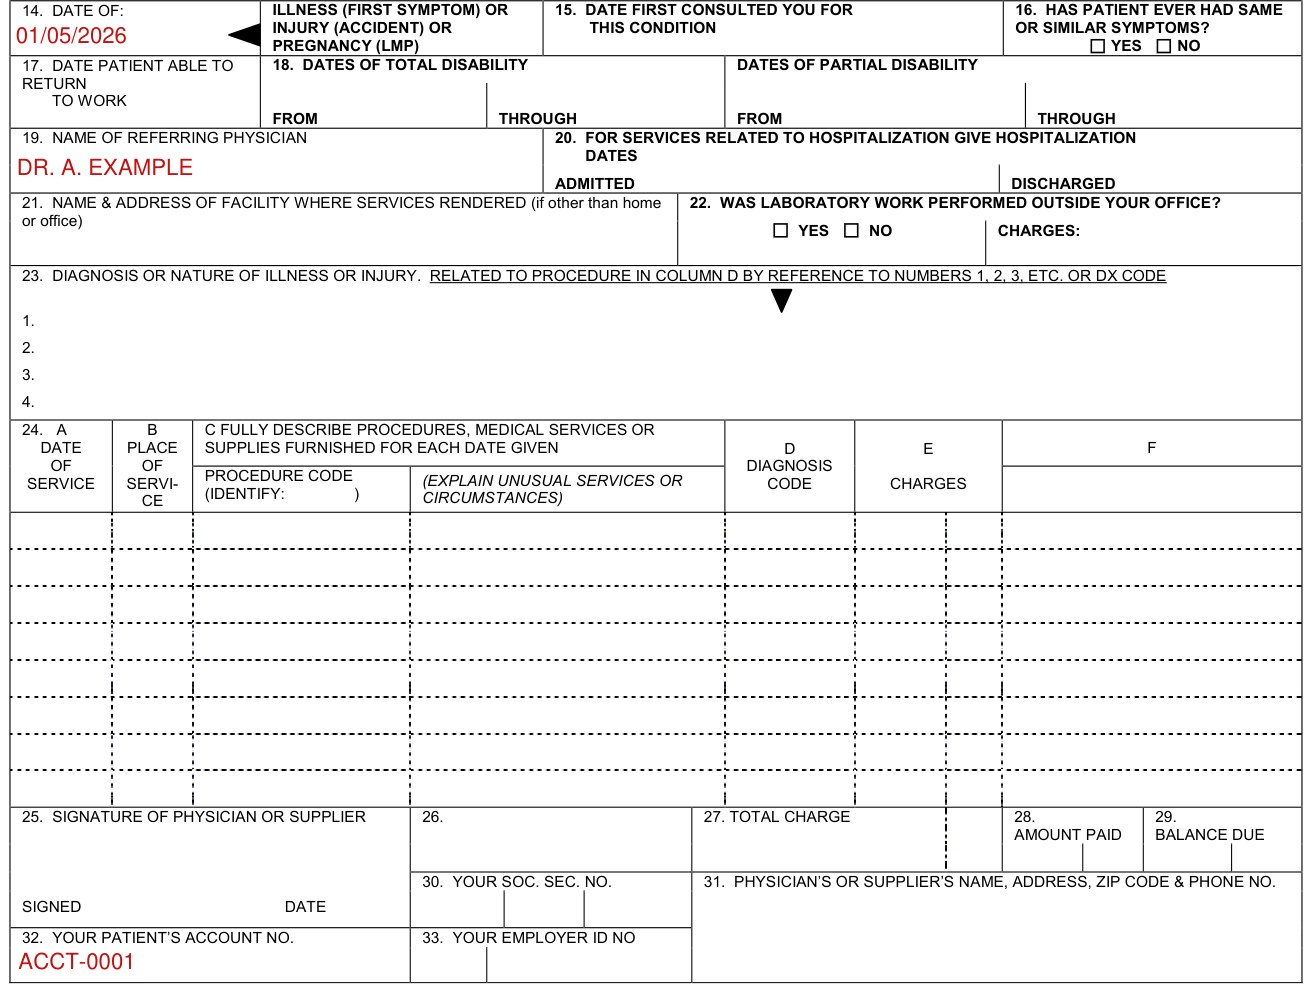
In Box 14, enter the date of illness (first symptom) or injury (accident) or pregnancy (LMP).
In Box 15, enter the Date First Consulted You for This Condition.
In Box 16, mark YES or NO to Has Patient Ever Had Same or Similar Symptoms. In Box 17, enter the Date Patient Able to Return to Work.
In Box 18, enter the dates of total disability and the dates of partial disability, each FROM and THROUGH. In Box 19, enter the name of the referring physician.
In Box 20, for services related to hospitalization, give the hospitalization dates, ADMITTED and DISCHARGED. In Box 21, enter the name and address of the facility where services were rendered (if other than home or office).
In Box 22, mark YES or NO to Was laboratory work performed outside your office, and enter CHARGES.
In Box 23, enter the diagnosis or nature of illness or injury, related to procedure in Column D by reference to numbers 1, 2, 3, etc. or Dx code.
In Box 24, A is Date of Service, B is Place of Service, C is Fully describe procedures, medical services or supplies furnished for each date given (explain unusual services or circumstances) with the Procedure Code (Identify:), and D is Diagnosis Code.
E is Charges.
Place of Service codes: 1 Inpatient Hospital, 2 Outpatient Hospital, 3 Doctor's Office, 4 Patient's Home, 5 Daycare Facility (PSY), 6 Night Care Facility (PSY), 7 Nursing Home, 8 Skilled Nursing Facility, 9 Ambulance, O Other Locations, A Independent Laboratory, B Other Medical/Surgical Facility.
In Box 25, the physician or supplier signs and dates the Signature of Physician or Supplier.
Enter the Total Charge in Box 27, the Amount Paid in Box 28 and the Balance Due in Box 29.
Enter Your Soc. Sec. No. in Box 30, the Physician's or Supplier's Name, Address, Zip Code & Phone No. in Box 31, Your Patient's Account No. in Box 32 and Your Employer ID No in Box 33.
Common questions about Benefit Request Form
Where do I file it?
The Benefit Request Form is submitted to Key Benefit Administrators, Inc., P.O. Box 2050, Fort Mill, SC 27916-2050.
Sources
[1] Benefit Request Form (the served file; no issuer file found) (the Official source link on this page).
