

Lab 1513 at a glance
What it is: Disclosure of Ownership and Control Interest Statement, a State of California Health and Human Services Agency, California Department of Public Health form.
Who signs: Enter the Name of authorized representative (typed) and Title.
A filled-in Lab 1513 example: a sole owner answers No to every question

How to fill out Lab 1513, box by box
I. Identifying Information
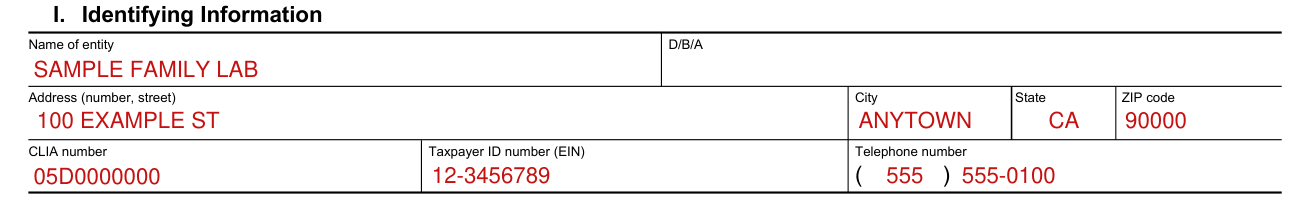
Under I. Identifying Information, enter the Name of entity, D/B/A, Address (number, street), City, State, ZIP code, CLIA number, Taxpayer ID number (EIN) and Telephone number.
II. Answer the following questions by checking Yes or No

Answer the following questions by checking “Yes” or “No.” If any of the questions are answered “Yes,” list names and addresses of individuals or corporations under “Remarks” on page 2. Identify each item number to be continued.
II. A. Are there any individuals or organizations having a direct or indirect ownership or control interest of five percent or more in the institution, organizations, or agency that have been convicted of a criminal offense related to the involvement of such persons or organizations in any of the programs established by Titles XVIII, XIX, or XX?
II. B. Are there any directors, officers, agents, or managing employees of the institution, agency, or organization who have ever been convicted of a criminal offense related to their involvement in such programs established by Titles XVIII, XIX, or XX?
II. C. Are there any individuals currently employed by the institution, agency, or organization in a managerial, accounting, auditing, or similar capacity who were employed by the institution's, organization's, or agency's fiscal intermediary or carrier within the previous 12 months? (Title XVIII providers only)
III. A. Names, addresses and EIN of owners

III. A. List names, addresses for individuals, or the EIN for organizations having direct or indirect ownership or a controlling interest in the entity under NAME, ADDRESS and EIN. List any additional names and addresses under “Remarks” on page 2. If more than one individual is reported and any of these persons are related to each other, this must be reported under “Remarks.”
III. B. Type of entity

III. B. Type of entity: Sole proprietorship, Partnership, Corporation, Unincorporated Associations or Other (specify).
III. C. If the disclosing entity is a corporation, list names, addresses of the directors, and EINs for corporations under “Remarks.”
III. D. Other Medicare/Medicaid facilities
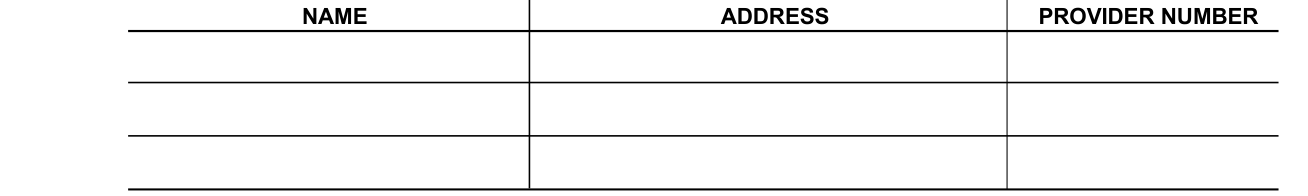
III. D. Are any owners of the disclosing entity also owners of other Medicare/Medicaid facilities? If yes, list names, addresses of individuals, and provider numbers under NAME, ADDRESS and PROVIDER NUMBER.
IV. Change in ownership, control or bankruptcy

IV. A. Has there been a change in ownership or control within the last year? If yes, give date.
IV. B. Do you anticipate any change of ownership or control within the year? If yes, when?
IV. C. Do you anticipate filing for bankruptcy within the year? If yes, when?
V. to VII. Management company, Administrator and chain affiliated
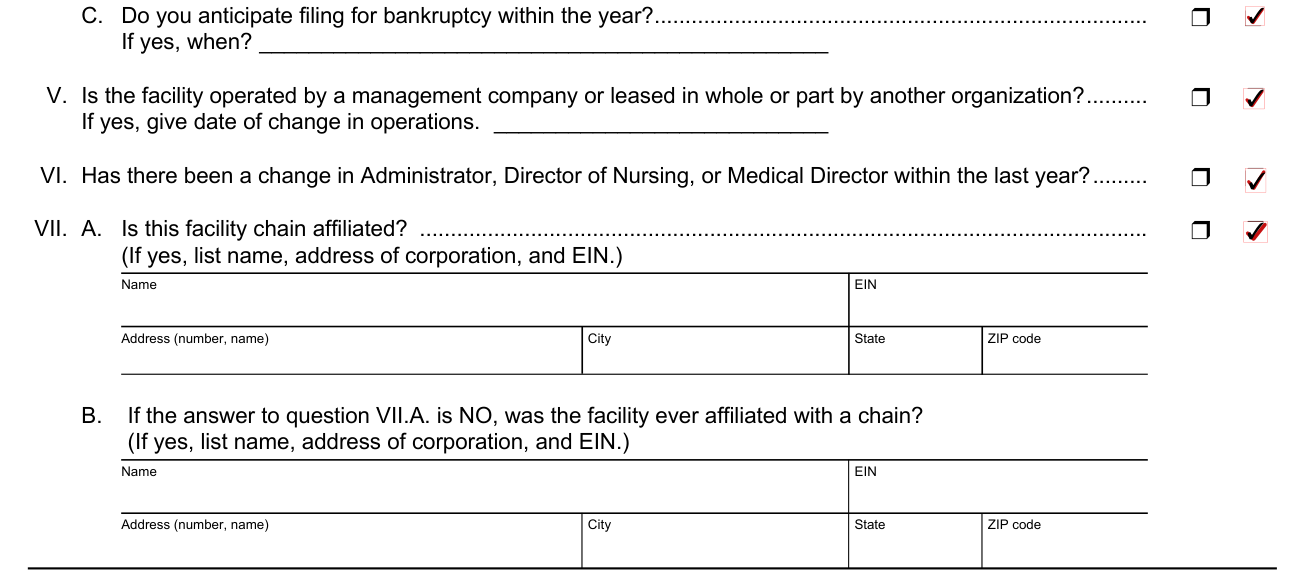
V. Is the facility operated by a management company or leased in whole or part by another organization? If yes, give date of change in operations.
VI. Has there been a change in Administrator, Director of Nursing, or Medical Director within the last year?
VII. A. Is this facility chain affiliated? VII. B. If the answer to question VII.A. is NO, was the facility ever affiliated with a chain? For each, if yes, list name, address of corporation, and EIN, under Name, EIN, Address (number, name), City, State and ZIP code.
Signature and false statement

Sign on the Signature line and enter the Date.
Whoever knowingly and willfully makes or causes to be made a false statement or representation of this statement, may be prosecuted under applicable federal or state laws.
In addition, knowingly and willfully failing to fully and accurately disclose the information requested may result in denial of a request to participate or where the entity already participates, a termination of its agreement or contract with the state agency or the secretary, as appropriate.
Sources
[1] Lab 1513 (7/07), Disclosure of Ownership and Control Interest Statement, California Department of Public Health (the Official source link on this page).