

Form LIC 602A at a glance
What it is: This is the California Department of Social Services Medical Assessment for Residential Care Facilities for the Elderly.
Who signs: Sign on the SIGNATURE OF PROSPECTIVE RESIDENT/RESIDENT OR PROSPECTIVE RESIDENT'S/RESIDENT'S LEGAL REPRESENTATIVE line. Sign on the LICENSED MEDICAL PROFESSIONAL SIGNATURE line and enter the DATE.
Note to licensed medical professional: The person/patient named is either a prospective resident or resident of a Residential Care Facility for the Elderly (RCFE) licensed by the Department of Social Services. The information that you provide about this person/patient is required by law to assist in determining whether the person/patient is appropriate for care in this non-medical facility [California Code of Regulations (CCR), Title 22, Section 87458, Medical Assessment]. These facilities cannot provide skilled nursing care.
A filled-in Form LIC 602A example: a prospective resident, nonambulatory but not bedridden
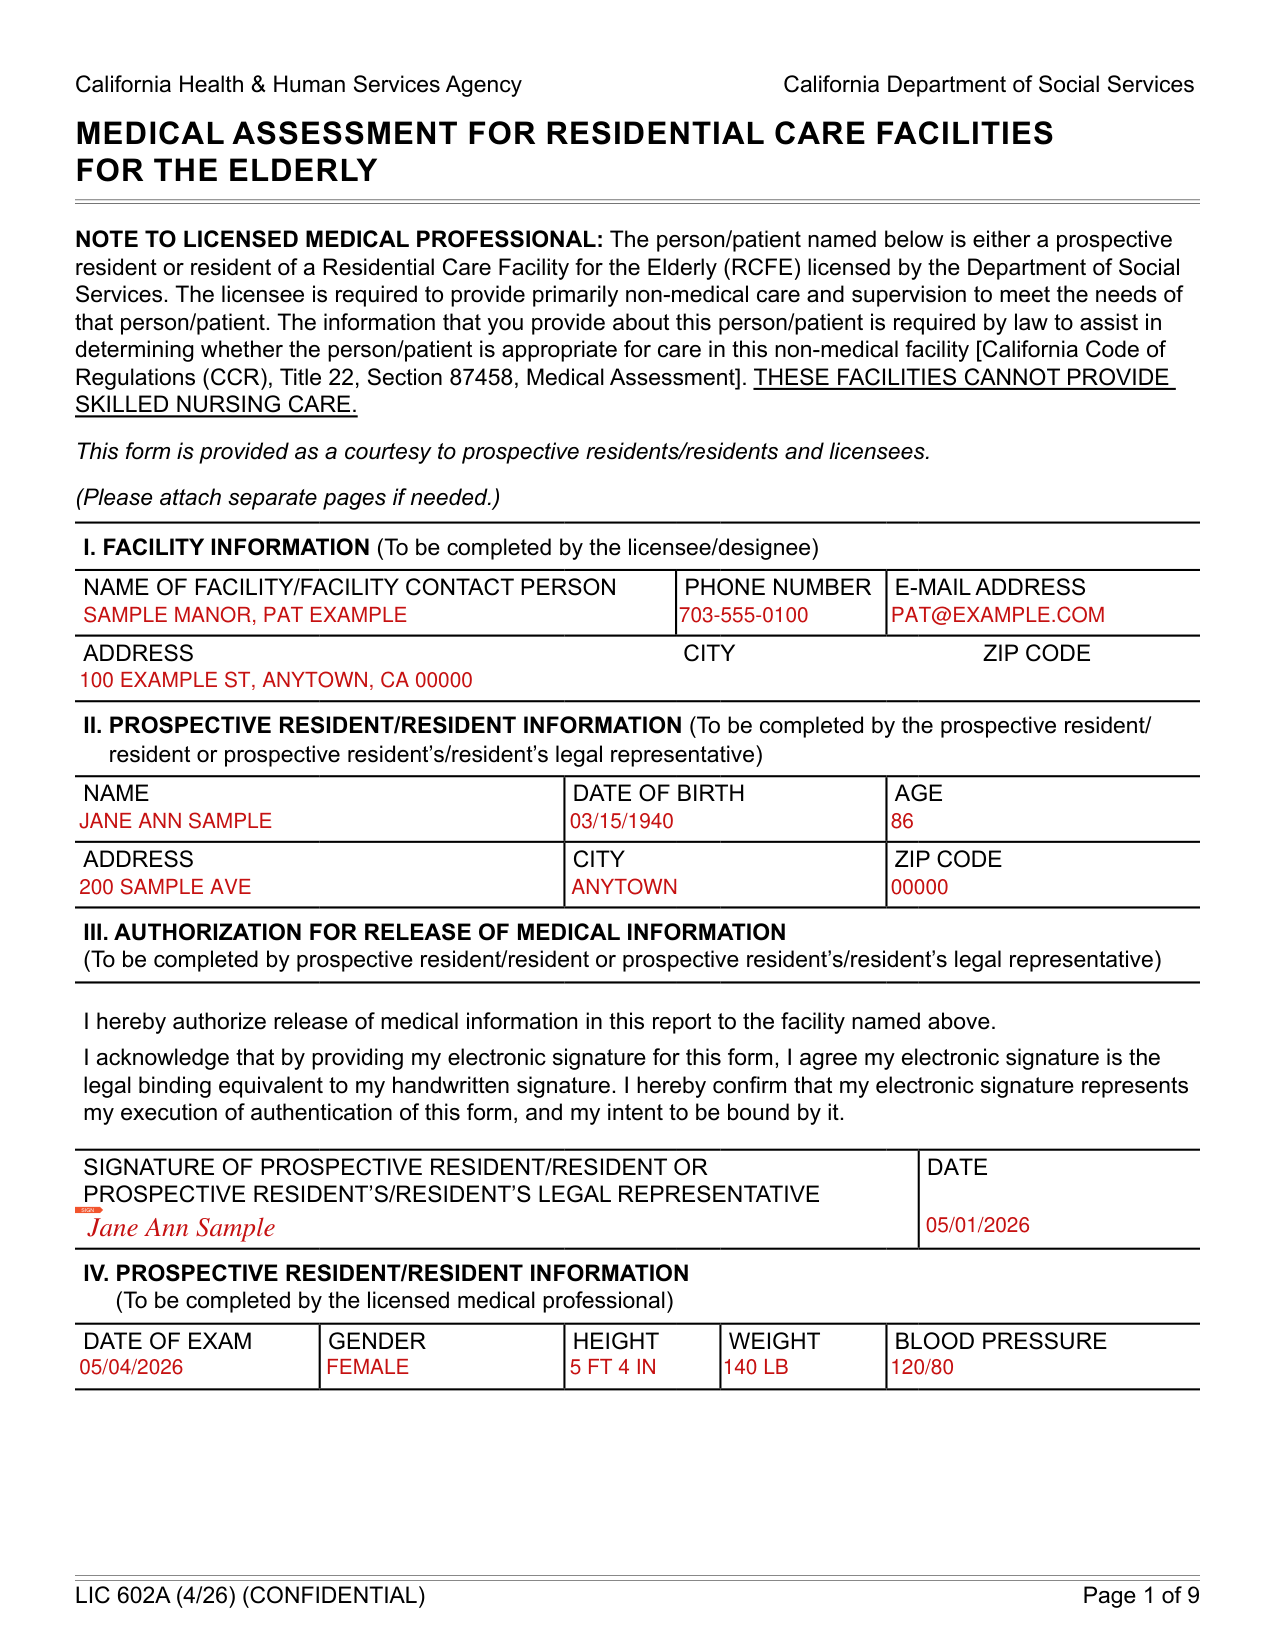
How to fill out Form LIC 602A, box by box
I. FACILITY INFORMATION

I. FACILITY INFORMATION is to be completed by the licensee/designee.
Enter the Name of Facility/Facility Contact Person, Phone Number and E-mail Address, then the Address, City and Zip Code.
II. PROSPECTIVE RESIDENT/RESIDENT INFORMATION
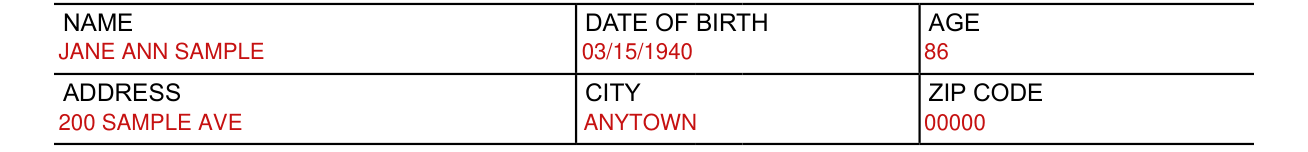
II. PROSPECTIVE RESIDENT/RESIDENT INFORMATION is to be completed by the prospective resident/resident or prospective resident's/resident's legal representative.
Enter the Name, Date of Birth, Age, Address, City and Zip Code.
III. AUTHORIZATION FOR RELEASE OF MEDICAL INFORMATION

III. AUTHORIZATION FOR RELEASE OF MEDICAL INFORMATION is to be completed by the prospective resident/resident or prospective resident's/resident's legal representative, who authorizes release of medical information in this report to the facility named.
By providing your electronic signature for this form, you agree your electronic signature is the legal binding equivalent to your handwritten signature.
Sign on the SIGNATURE OF PROSPECTIVE RESIDENT/RESIDENT OR PROSPECTIVE RESIDENT'S/RESIDENT'S LEGAL REPRESENTATIVE line.
Enter the DATE.
IV. PROSPECTIVE RESIDENT/RESIDENT INFORMATION (To be completed by the licensed medical professional)

IV. PROSPECTIVE RESIDENT/RESIDENT INFORMATION is to be completed by the licensed medical professional.
Enter the Date of Exam, Gender, Height, Weight and Blood Pressure.
DIAGNOSIS/DIAGNOSES
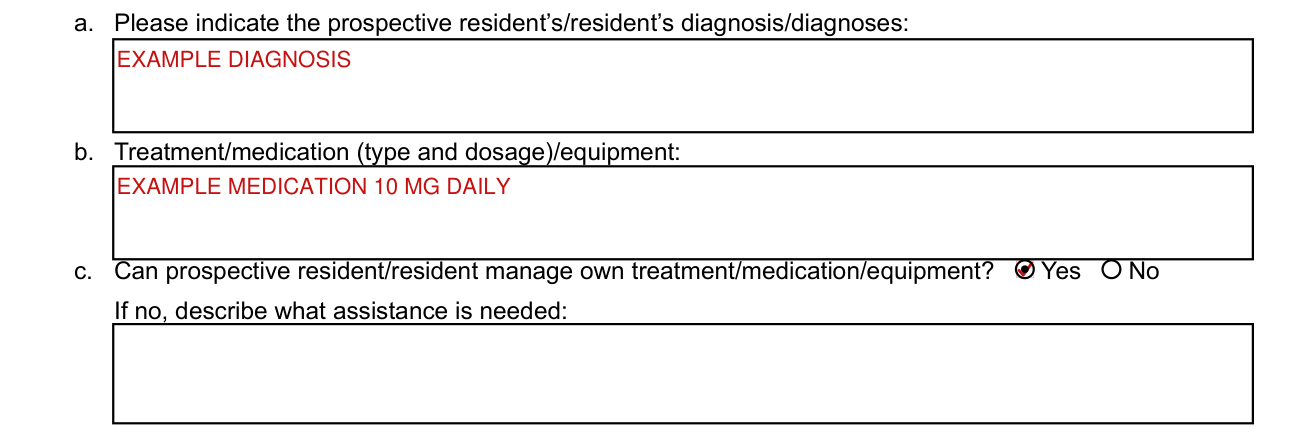
For DIAGNOSIS/DIAGNOSES, please indicate the prospective resident's/resident's diagnosis/diagnoses.
For DIAGNOSIS/DIAGNOSES, enter the Treatment/medication (type and dosage)/equipment; mark Yes or No for: can prospective resident/resident manage own treatment/medication/equipment?; if no, describe what assistance is needed.
COGNITIVE CONDITIONS

For COGNITIVE CONDITIONS, mark Yes or No: Does prospective resident/resident have any cognitive conditions? If yes, please indicate cognitive condition(s).
For COGNITIVE CONDITIONS, enter the Treatment/medication (type and dosage)/equipment; mark Yes or No for: can prospective resident/resident manage own treatment/medication/equipment?; if no, describe what assistance is needed.
RESULTS OF EXAM FOR COMMUNICABLE TUBERCULOSIS (TB)
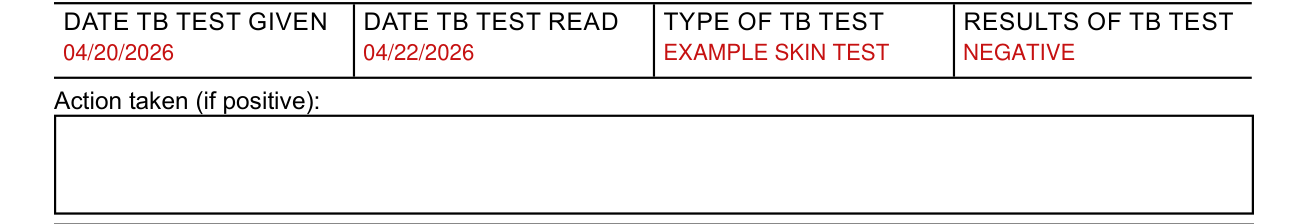
For RESULTS OF EXAM FOR COMMUNICABLE TUBERCULOSIS (TB), enter the DATE TB TEST GIVEN, DATE TB TEST READ, TYPE OF TB TEST and RESULTS OF TB TEST, then the Action taken (if positive).
RESULTS OF EXAM FOR INFECTIOUS DISEASES
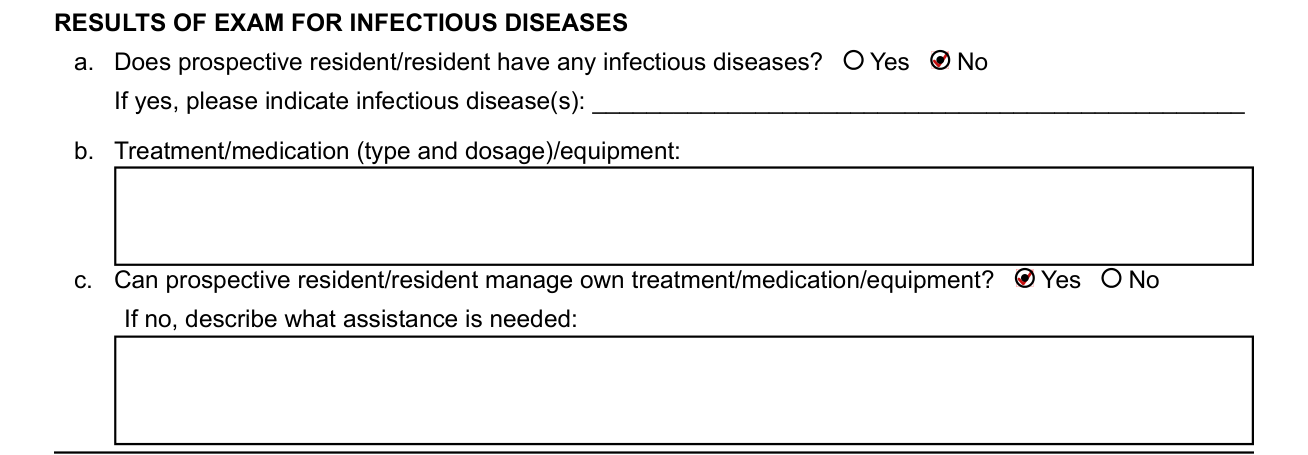
For RESULTS OF EXAM FOR INFECTIOUS DISEASES, mark Yes or No: Does prospective resident/resident have any infectious diseases? If yes, please indicate infectious disease(s).
For RESULTS OF EXAM FOR INFECTIOUS DISEASES, enter the Treatment/medication (type and dosage)/equipment; mark Yes or No for: can prospective resident/resident manage own treatment/medication/equipment?; if no, describe what assistance is needed.
RESULTS OF EXAM FOR CONTAGIOUS DISEASES
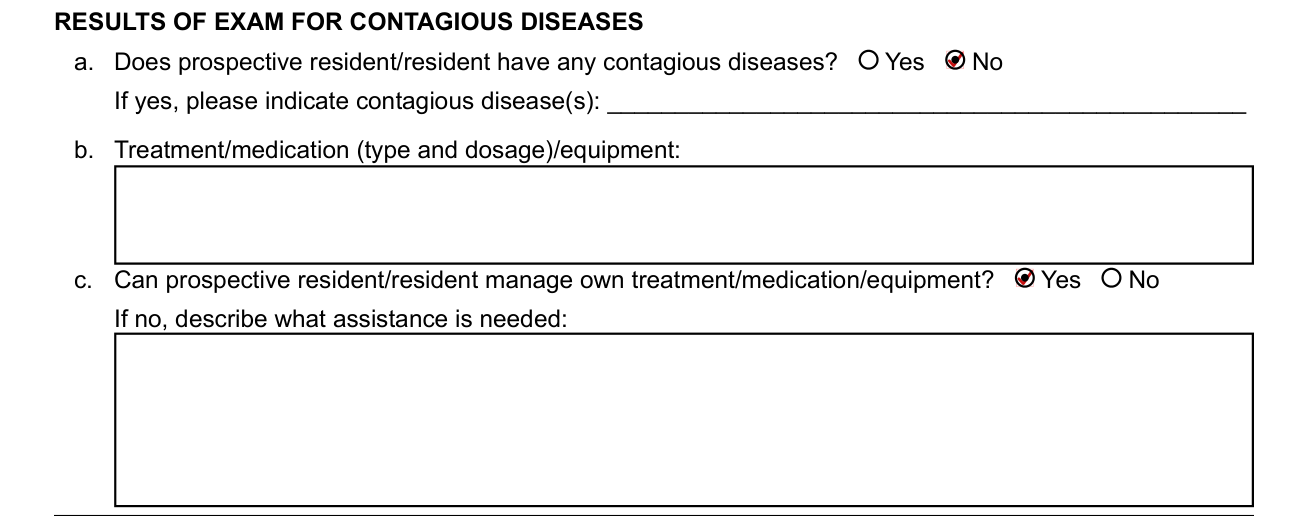
For RESULTS OF EXAM FOR CONTAGIOUS DISEASES, mark Yes or No: Does prospective resident/resident have any contagious diseases? If yes, please indicate contagious disease(s).
For RESULTS OF EXAM FOR CONTAGIOUS DISEASES, enter the Treatment/medication (type and dosage)/equipment; mark Yes or No for: can prospective resident/resident manage own treatment/medication/equipment?; if no, describe what assistance is needed.
RESULTS OF EXAM FOR OTHER MEDICAL CONDITIONS
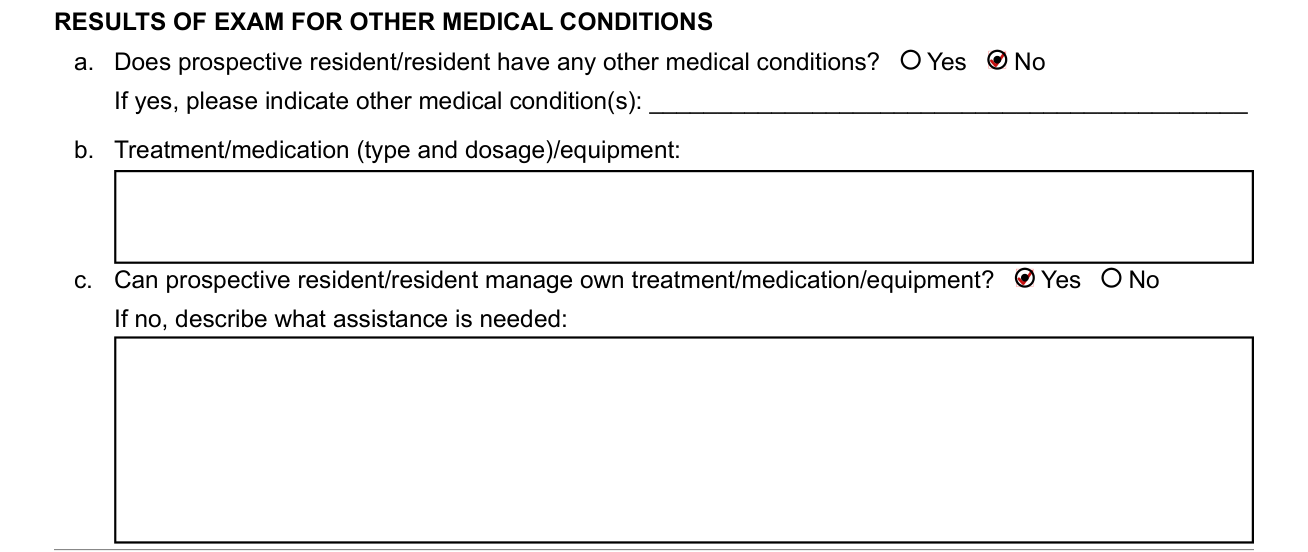
For RESULTS OF EXAM FOR OTHER MEDICAL CONDITIONS, mark Yes or No: Does prospective resident/resident have any other medical conditions? If yes, please indicate other medical condition(s).
For RESULTS OF EXAM FOR OTHER MEDICAL CONDITIONS, enter the Treatment/medication (type and dosage)/equipment; mark Yes or No for: can prospective resident/resident manage own treatment/medication/equipment?; if no, describe what assistance is needed.
ALLERGIES

For ALLERGIES, mark Yes or No: Does prospective resident/resident have any allergies (e.g., seasonal, food, medication, dander)? If yes, please indicate allergy(ies).
For ALLERGIES, enter the Treatment/medication (type and dosage)/equipment; mark Yes or No for: can prospective resident/resident manage own treatment/medication/equipment?; if no, describe what assistance is needed.
1. OVERALL PHYSICAL HEALTH
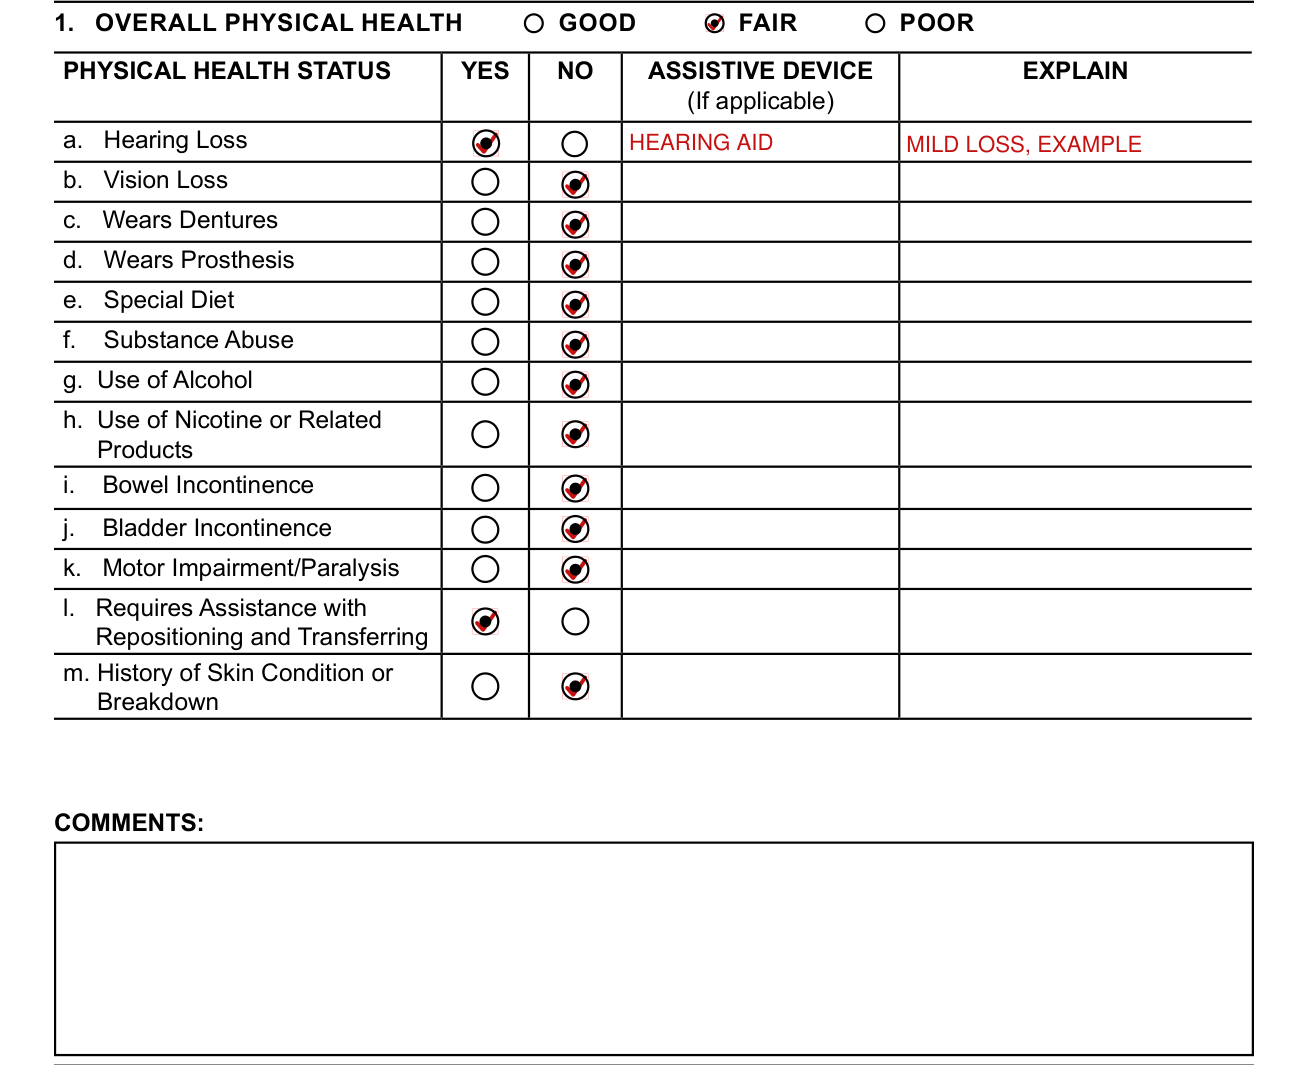
Mark GOOD, FAIR or POOR for 1. OVERALL PHYSICAL HEALTH. For PHYSICAL HEALTH STATUS, mark YES or NO and enter the ASSISTIVE DEVICE and EXPLAIN (If applicable) for Hearing Loss, Vision Loss, Wears Dentures, Wears Prosthesis, Special Diet, Substance Abuse, Use of Alcohol, Use of Nicotine or Related Products, Bowel Incontinence, Bladder Incontinence, Motor Impairment/Paralysis, Requires Assistance with Repositioning and Transferring, and History of Skin Condition or Breakdown.
2. CAPACITY FOR SELF-CARE
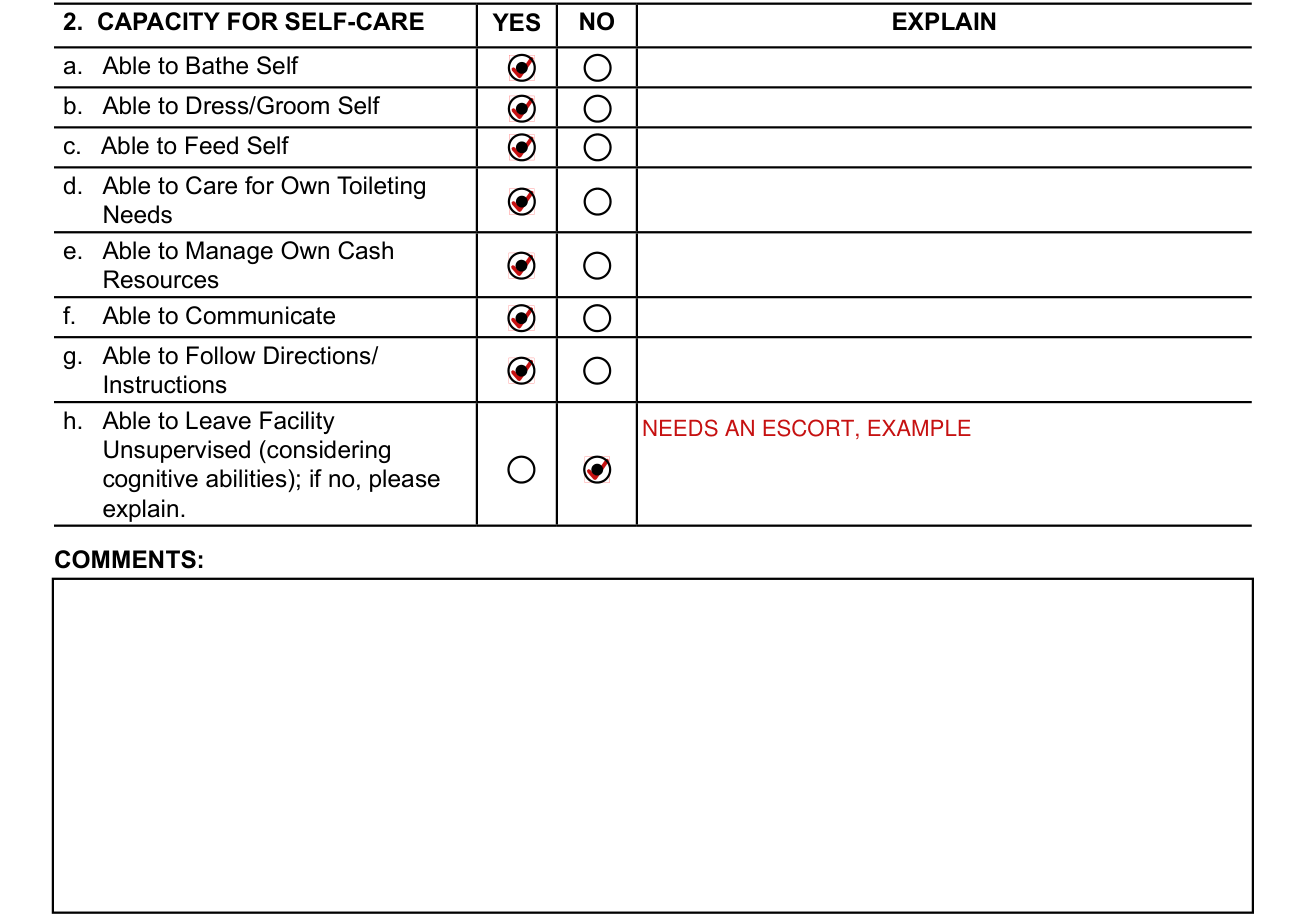
For 2. CAPACITY FOR SELF-CARE, mark YES or NO and EXPLAIN for Able to Bathe Self, Able to Dress/Groom Self, Able to Feed Self, Able to Care for Own Toileting Needs, Able to Manage Own Cash Resources, Able to Communicate, Able to Follow Directions/Instructions and Able to Leave Facility Unsupervised (considering cognitive abilities); if no, please explain.
3. OVERALL MENTAL HEALTH
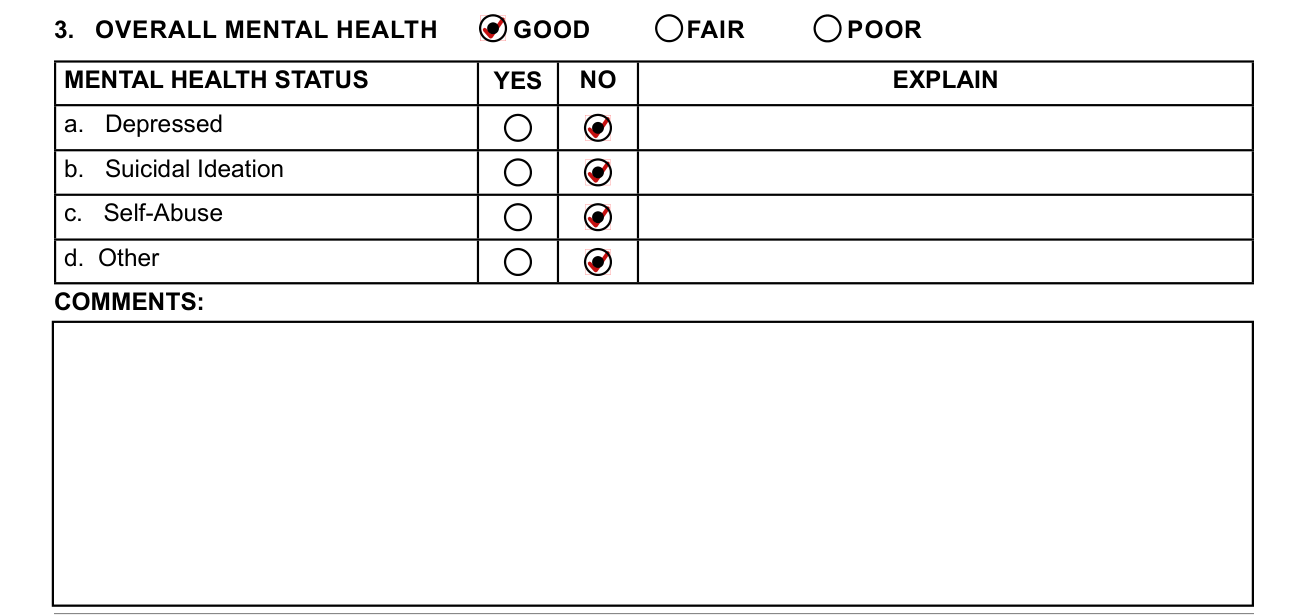
Mark GOOD, FAIR or POOR for 3. OVERALL MENTAL HEALTH. For MENTAL HEALTH STATUS, mark YES or NO and EXPLAIN for Depressed, Suicidal Ideation, Self-Abuse and Other.
4. BEHAVIORAL EXPRESSIONS

For 4. BEHAVIORAL EXPRESSIONS, mark YES or NO and EXPLAIN for Disorientation, Lack of Hazard Awareness, Lack of Impulse Control, Unsafe Wandering, Elopement, Expressions of Frustration, Hallucinations and Other.
5. ACCESS TO ITEMS
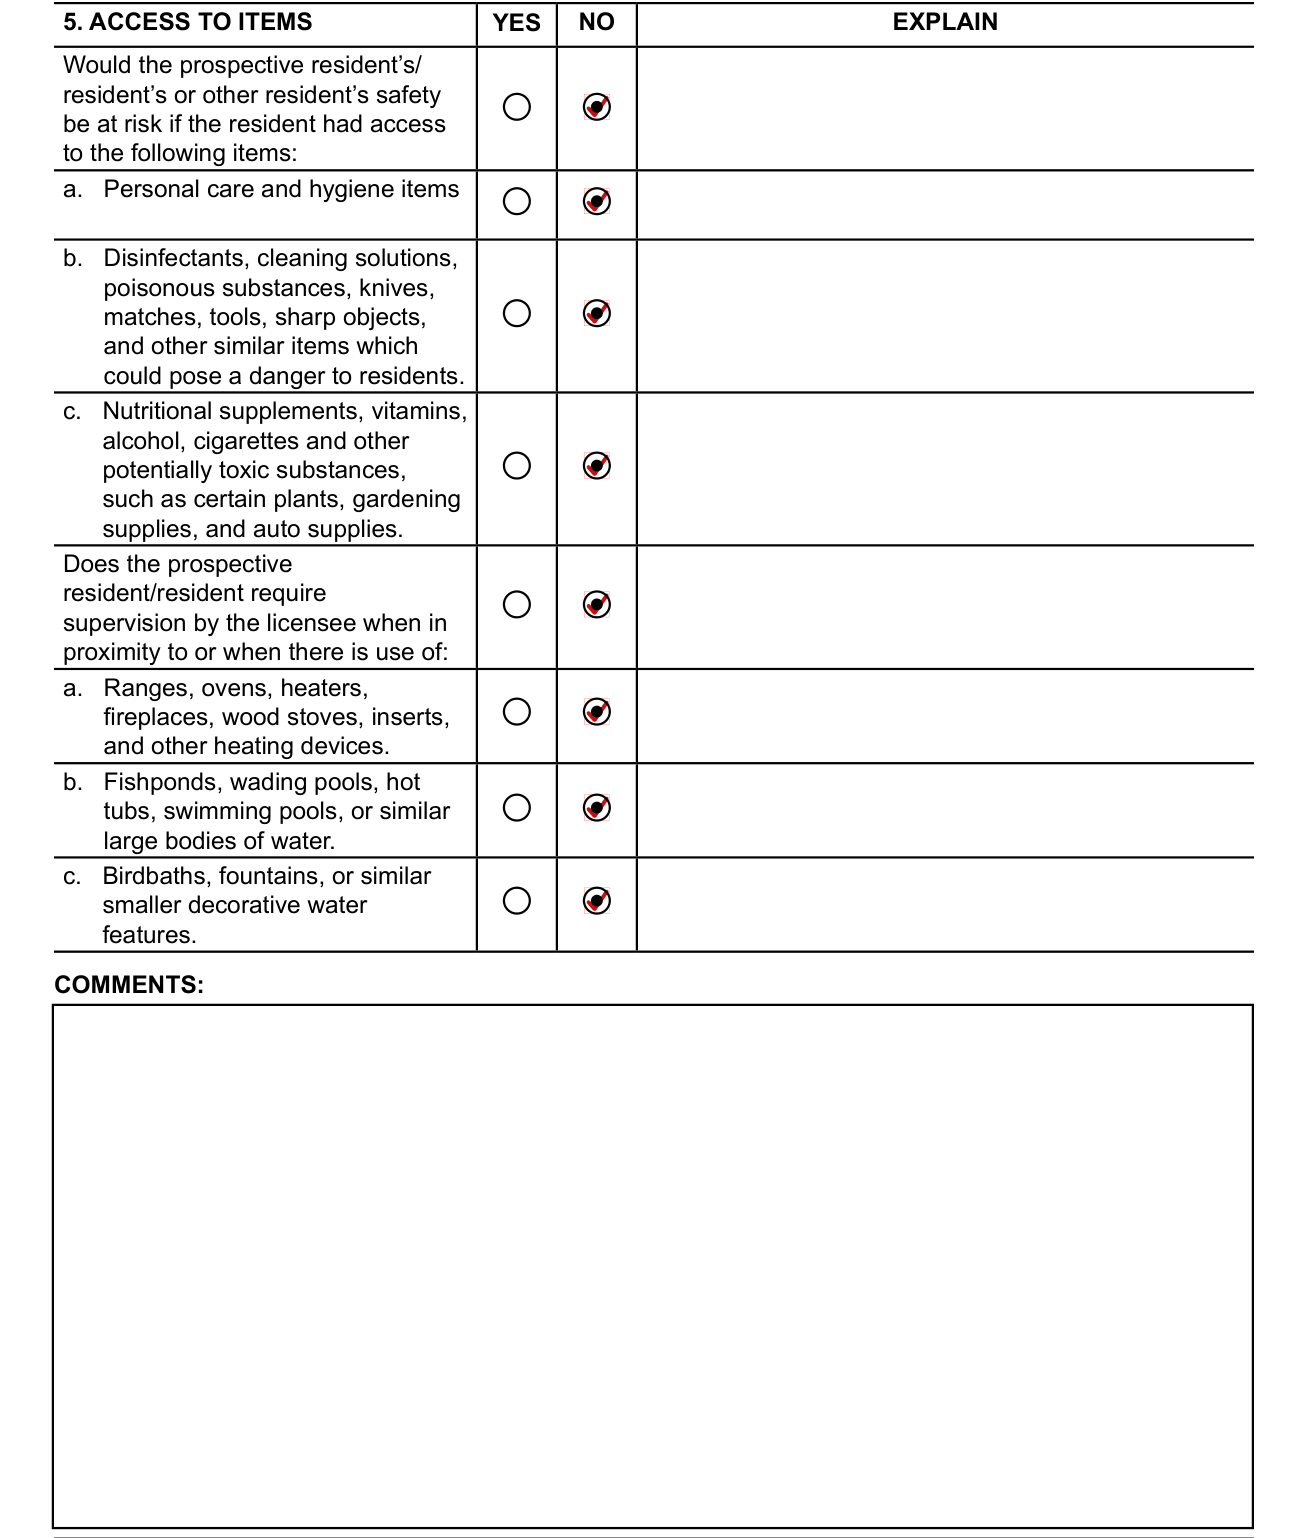
For 5. ACCESS TO ITEMS, mark YES or NO and EXPLAIN. Would the prospective resident's/resident's or other resident's safety be at risk if the resident had access to the following items: personal care and hygiene items; disinfectants, cleaning solutions, poisonous substances, knives, matches, tools and sharp objects; or nutritional supplements, vitamins, alcohol and cigarettes?
Does the prospective resident/resident require supervision by the licensee when in proximity to or when there is use of ranges, ovens, heaters and fireplaces; fishponds, wading pools, hot tubs and swimming pools; or birdbaths and fountains?
6. MEDICATION MANAGEMENT
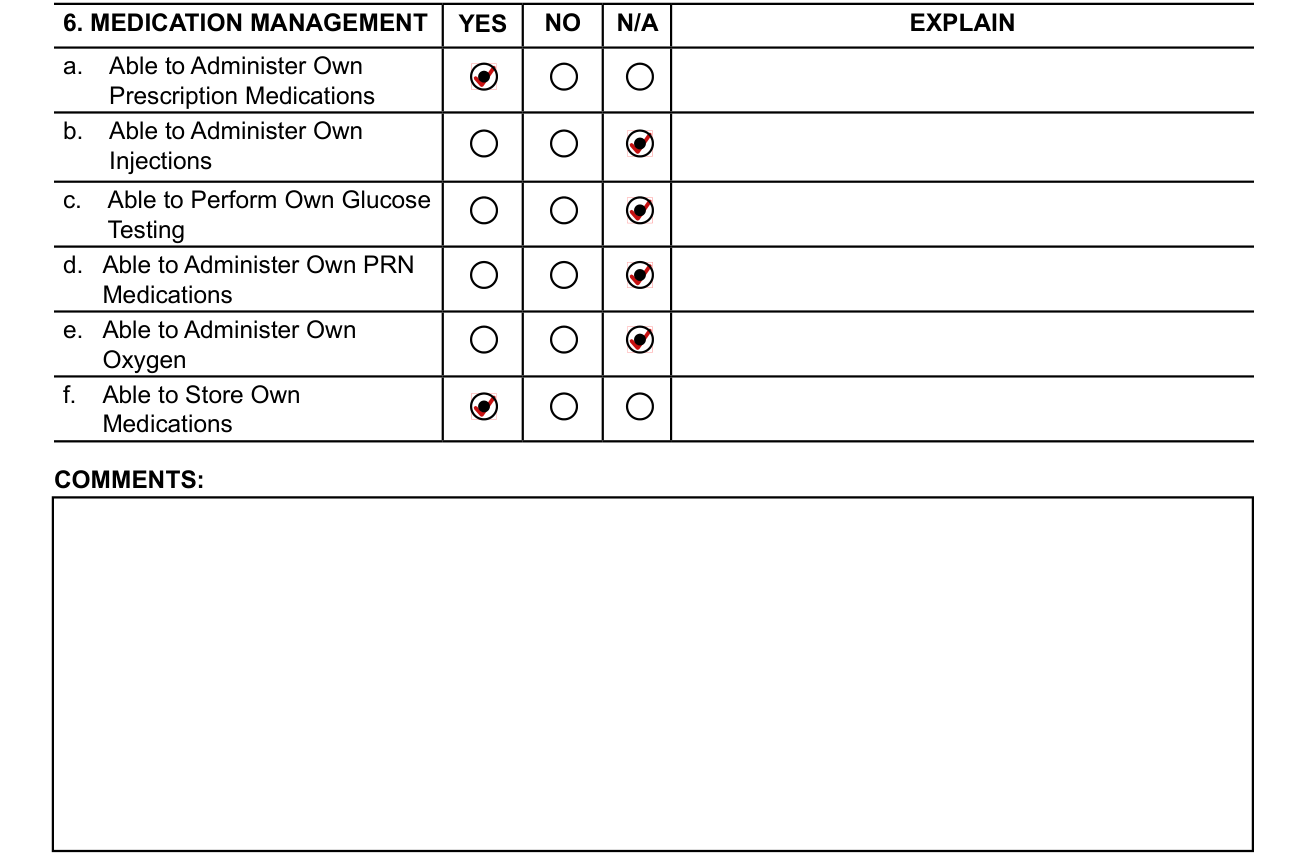
For 6. MEDICATION MANAGEMENT, mark YES, NO or N/A and EXPLAIN for Able to Administer Own Prescription Medications, Able to Administer Own Injections, Able to Perform Own Glucose Testing, Able to Administer Own PRN Medications, Able to Administer Own Oxygen and Able to Store Own Medications.
AMBULATORY STATUS

For AMBULATORY STATUS, mark Yes or No: the prospective resident/resident is able to independently transfer to and from bed.
For purposes of a fire clearance, mark Ambulatory, Nonambulatory or Bedridden for this prospective resident/resident.
Nonambulatory: The prospective resident/resident is unable to leave a building unassisted under emergency conditions.
A prospective resident/resident who is unable to independently transfer to and from bed, but who does not need assistance to turn or reposition in bed, shall be considered non-ambulatory for the purposes of a fire clearance.
Bedridden: For the purpose of a fire clearance, this means a prospective resident/resident who requires assistance with turning or repositioning in bed.
If prospective resident/resident is nonambulatory, this status is based upon: mark Physical Condition, Mental Condition or Both Physical and Mental Condition.
Illness, Recovery from Surgery, Other

If a prospective resident/resident is bedridden, check one or more of Illness, Recovery from Surgery and Other, and describe the nature of the illness, surgery or other cause.
An illness or recovery is considered temporary if it will last 14 days or less.
How long is bedridden status expected to persist?

If a prospective resident/resident is bedridden, enter how long bedridden status is expected to persist.
Enter the number of days and the estimated date illness or recovery is expected to end or when prospective resident/resident will no longer be confined to bed.
If illness or recovery is permanent, please explain.
Is prospective resident/resident receiving hospice care?

Mark No or Yes: Is prospective resident/resident receiving hospice care? If yes, specify the terminal illness.
V. LICENSED MEDICAL PROFESSIONAL INFORMATION
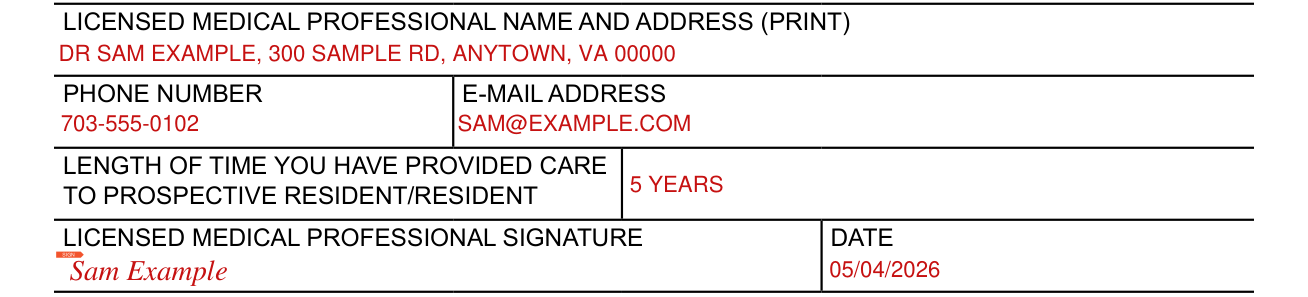
For V. LICENSED MEDICAL PROFESSIONAL INFORMATION, print the licensed medical professional name and address, phone number, e-mail address and length of time you have provided care to prospective resident/resident.
More rules for Form LIC 602A
Please attach separate pages if needed.
Common questions about Form LIC 602A
What is lic 602A?
This is the California Department of Social Services Medical Assessment for Residential Care Facilities for the Elderly. This form is provided as a courtesy to prospective residents/residents and licensees.
Sources
[1] Form LIC 602A (4/26), Medical Assessment for Residential Care Facilities for the Elderly, California Department of Social Services (the Official source link on this page).
