

Form LIC 603 at a glance
What it is: Form LIC 603 (6/22) is the Preplacement Appraisal Information for Admission to Residential Care Facilities, from the California Department of Social Services.
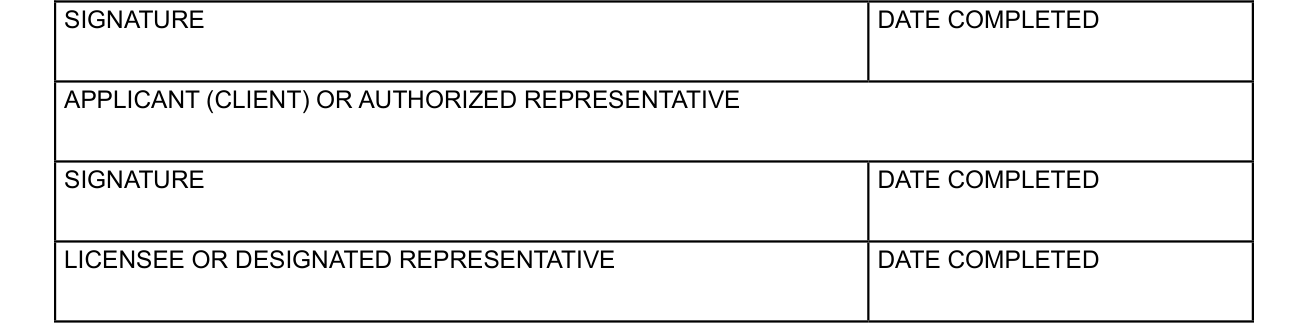
Who signs: Under SIGNATURE and DATE COMPLETED, the APPLICANT (CLIENT) OR AUTHORIZED REPRESENTATIVE signs and enters the date. Under SIGNATURE and DATE COMPLETED, the LICENSEE OR DESIGNATED REPRESENTATIVE signs and enters the date.
This information may be obtained from the applicant, or his/her authorized representative. Relatives, social agency, hospital or physician may assist the applicant in completing this form.
A filled-in Form LIC 603 example: a daughter fills it out for her father

How to fill out Form LIC 603, box by box
Applicant name and age

Enter the APPLICANT NAME and the AGE.
Health, physical disabilities and mental condition
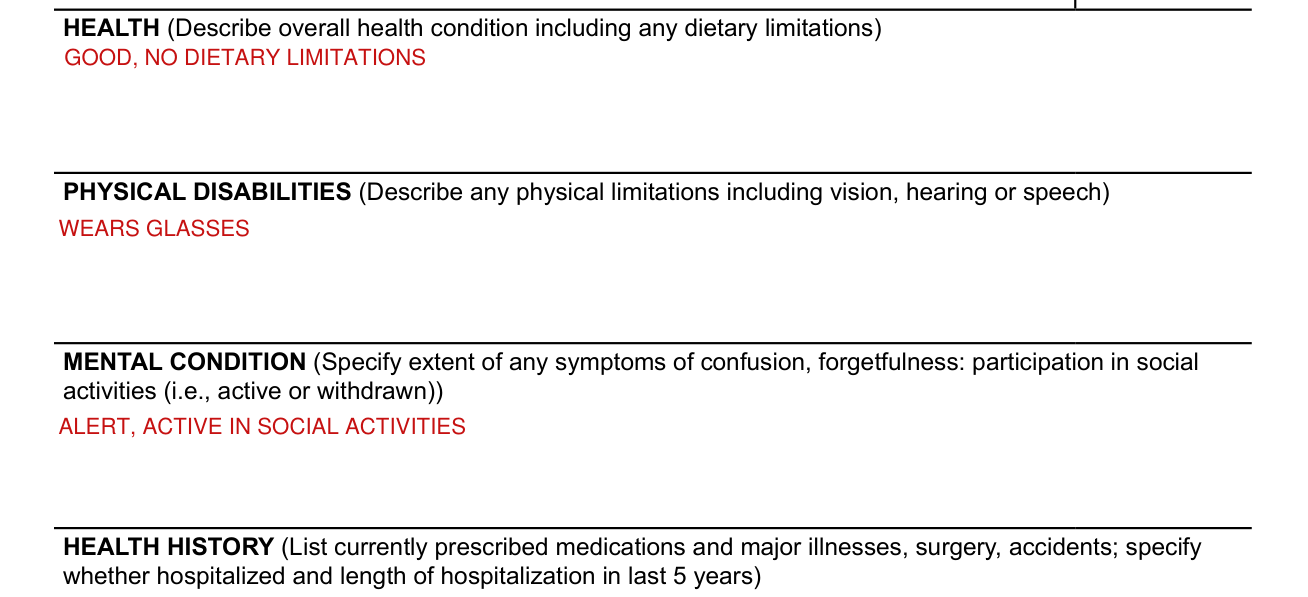
Under HEALTH, describe overall health condition including any dietary limitations.
Under PHYSICAL DISABILITIES, describe any physical limitations including vision, hearing or speech.
Under MENTAL CONDITION, specify extent of any symptoms of confusion, forgetfulness: participation in social activities (i.e., active or withdrawn).
Health history and social factors
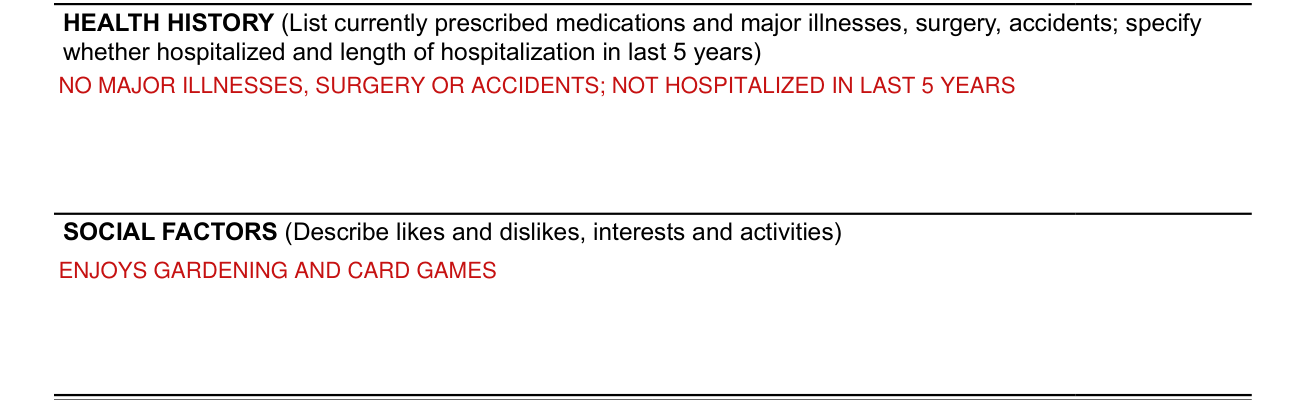
Under HEALTH HISTORY, list currently prescribed medications and major illnesses, surgery, accidents; specify whether hospitalized and length of hospitalization in last 5 years.
Under SOCIAL FACTORS, describe likes and dislikes, interests and activities.
Bed status

BED STATUS lists OUT OF BED ALL DAY, IN BED ALL OR MOST OF THE TIME and IN BED PART OF THE TIME. Write a COMMENT.
Tuberculosis information
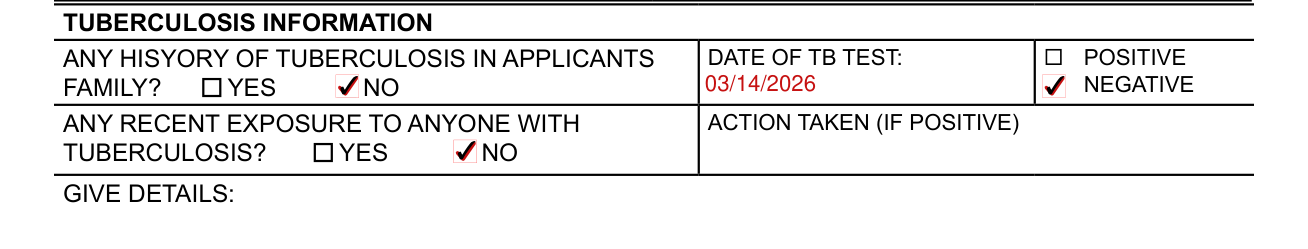
Under TUBERCULOSIS INFORMATION, mark YES or NO for ANY HISYORY OF TUBERCULOSIS IN APPLICANTS FAMILY, as the form prints it.
Enter the DATE OF TB TEST and mark POSITIVE or NEGATIVE.
Mark YES or NO for ANY RECENT EXPOSURE TO ANYONE WITH TUBERCULOSIS.
Write the ACTION TAKEN (IF POSITIVE) and GIVE DETAILS.
Ambulatory status

For AMBULATORY STATUS, mark ambulatory or nonambulatory. Ambulatory means able to demonstrate the mental and physical ability to leave a building without the assistance of a person or the use of a mechanical device.
An ambulatory person must be able to do the following:
Mark YES or NO for each: Able to walk without any physical assistance (e.g., walker, crutches, other person), or able to walk with a cane. Mentally and physically able to follow signals and instructions for evacuation. Able to use evacuation routes including stairs if necessary. Able to evacuate reasonably quickly (e.g., walk directly the route without hesitation).
Functional capabilities

FUNCTIONAL CAPABILITIES: Check all items in this FUNCTIONAL CAPABILITIES list, YES or NO. Active, requires no personal help of any kind, able to go up and down stairs easily. Active, but has difficulty climbing or descending stairs. Uses brace or crutch. Feeble or slow.
Uses walker. If Yes, can get in and out unassisted? Yes or No. Uses wheelchair. If Yes, can get in and out unassisted? Yes or No. Requires grab bars in bathroom.
For Other, describe.
Services needed

SERVICES NEEDED: Check items and explain. Help in transferring in and out of bed and dressing. Help with bathing, hair care, personal hygiene. Does client desire and is client capable of doing own personal laundry and other household tasks (specify).
Help with moving about the facility. Help with eating (need for adaptive devices or assistance from another person). Special diet/observation of food intake. Toileting, including assistance equipment, or assistance of another person.
Continence, bowel or bladder control. Are assistive devices such as a catheter required?
Services needed, second part

SERVICES NEEDED: Check items and explain. Help with medication. Needs special observation/night supervision (due to confusion, forgetfulness, wandering). Help in managing own cash resources. Help in participating in activity programs.
Special medical attention. Assistance in incidental health and medical care. Other “Services Needed” not identified in the Services Needed list.
Additional information

Is there any additional information which would assist the facility in determining applicant’s suitability for admission? Mark Yes or No. If Yes, please attach comments on separate sheet.
Skilled nursing care and signatures
By the signatures, the form prints: To the best of my knowledge; I do not need skilled nursing care.
Under SIGNATURE and DATE COMPLETED, the APPLICANT (CLIENT) OR AUTHORIZED REPRESENTATIVE signs and enters the date.
Under SIGNATURE and DATE COMPLETED, the LICENSEE OR DESIGNATED REPRESENTATIVE signs and enters the date.
Common questions about Form LIC 603
When is this form not the right one?
This form is not a substitute for the Physician’s Report (LIC 602).
Sources
[1] Form LIC 603 (6/22), California Department of Social Services (the Official source link on this page).
