

LIC 625 at a glance
What it is: LIC 625 is the Appraisal/Needs and Services Plan of the California Department of Social Services.
Who signs: The form has a licensee(s) signature line, a line for the client's/resident's authorized representative(s)/facility social worker/physician/ other appropriate consultant signature, and a client's/resident's or authorized representative(s) signature line.
Licensing regulations require that an appraisal of needs or a needs and services plan be completed for clients/residents to identify individual needs or to develop a service plan for meeting client/resident needs.
This form is provided as a courtesy to licensees.
A filled-in LIC 625 example: a care home completes the plan for a new resident

How to fill out LIC 625, box by box
Client's/resident's name, date of birth, age, sex and date

Enter the CLIENT'S/RESIDENT'S NAME, DATE OF BIRTH and AGE, check MALE or FEMALE under SEX, and enter the DATE.
Facility name, address and type of needs and services plan

Enter the FACILITY NAME and ADDRESS. Check the TYPE OF NEEDS AND SERVICES PLAN: ADMISSION or UPDATE.
Person(s) or agency(ies) referring client/resident, facility license number and telephone number

Enter the PERSON(S) OR AGENCY(IES) REFERRING CLIENT/RESIDENT FOR PLACEMENT.
Enter the FACILITY LICENSE NUMBER and the TELEPHONE NUMBER.
Background information

Enter a brief description of client's/resident's medical history/emotional, behavioral, and physical conditions; functional limitations; physical and mental; functional capabilities; ability to handle personal cash resources and perform simple homemaking tasks; client's/resident's likes and dislikes.
Other information
For facilities serving children, the OTHER INFORMATION section may be used for other information required in an appraisal/needs and services plan, which may include, but is not limited to, family reunification or permanency plan, special dietary needs or practices, and history of infections or contagious diseases.
Refer to category-specific licensing requirements.
Needs, objective/plan, time frame, person(s) responsible and method of evaluating: socialization and emotional
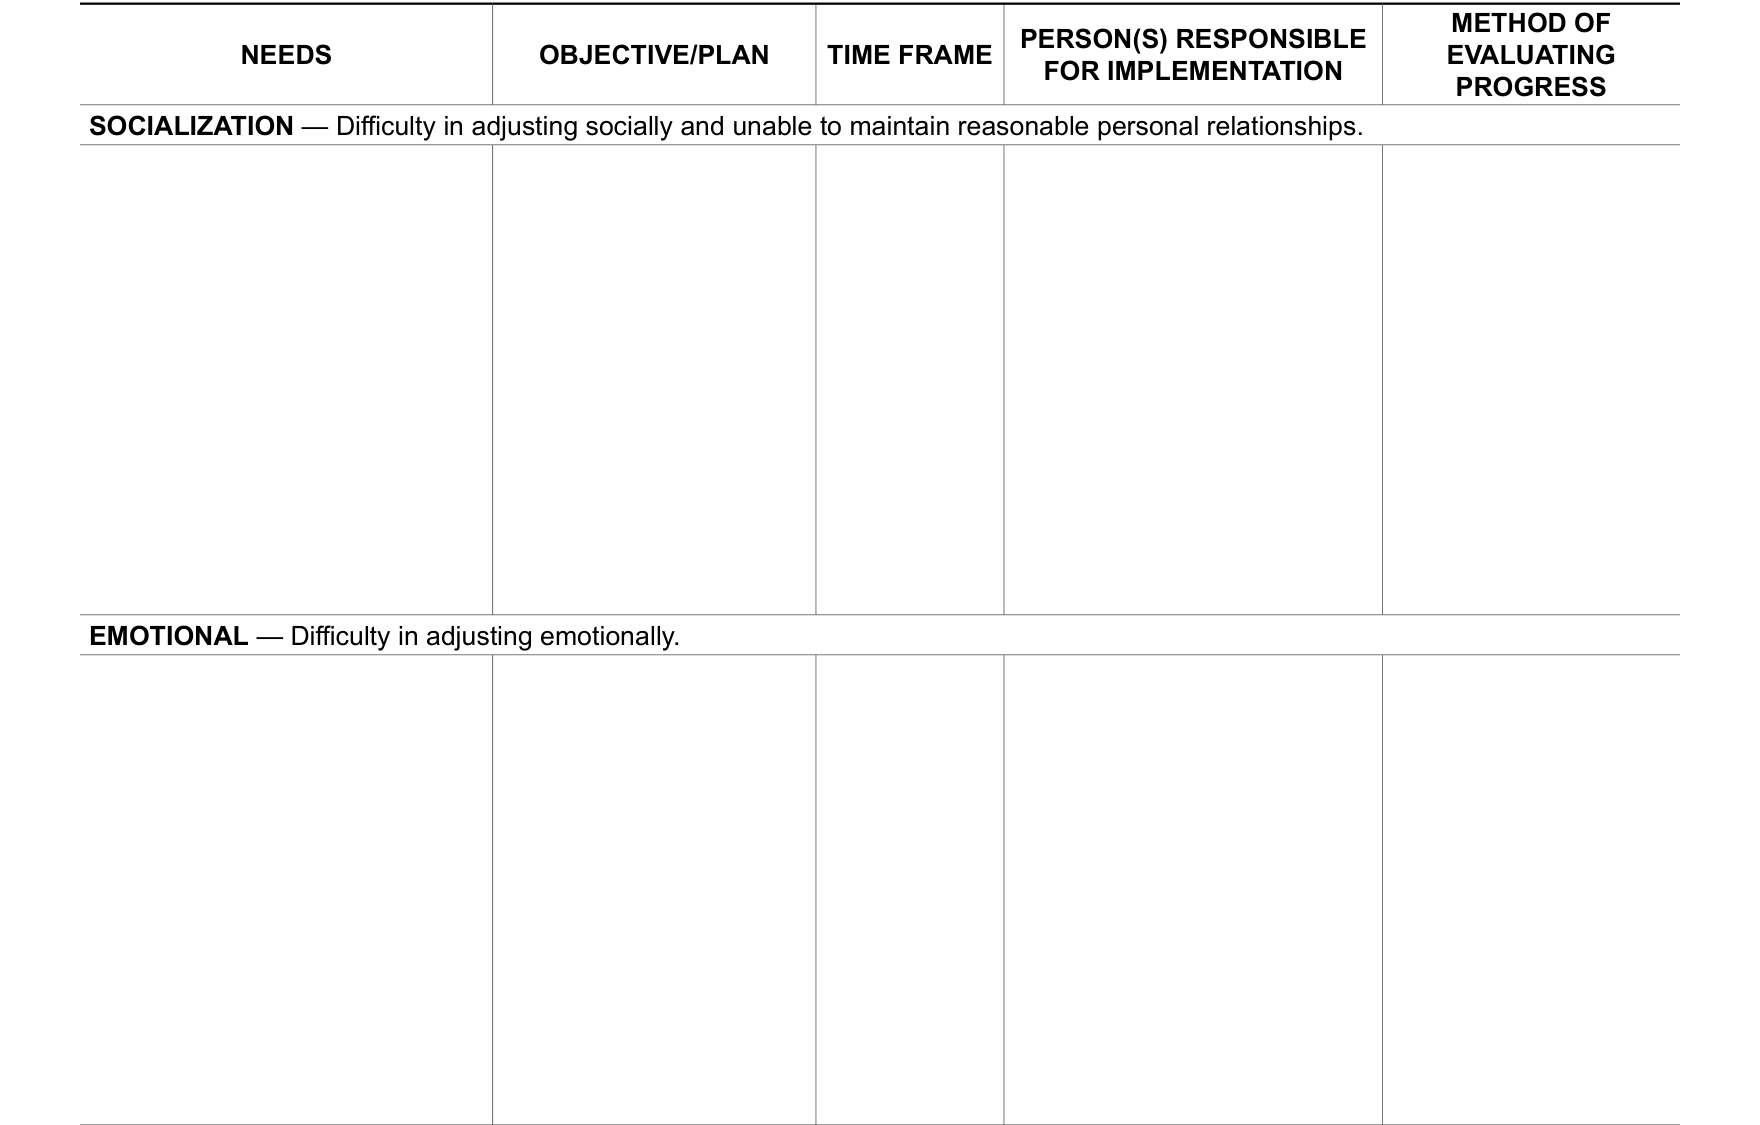
On each line, fill in the needs, objective/plan, time frame for implementation, person(s) responsible and method of evaluating progress boxes.
On the SOCIALIZATION line, fill in the boxes for difficulty in adjusting socially and unable to maintain reasonable personal relationships.
On the EMOTIONAL line, fill in the boxes for difficulty in adjusting emotionally.
Needs, objective/plan, time frame, person(s) responsible and method of evaluating: mental and physical/health
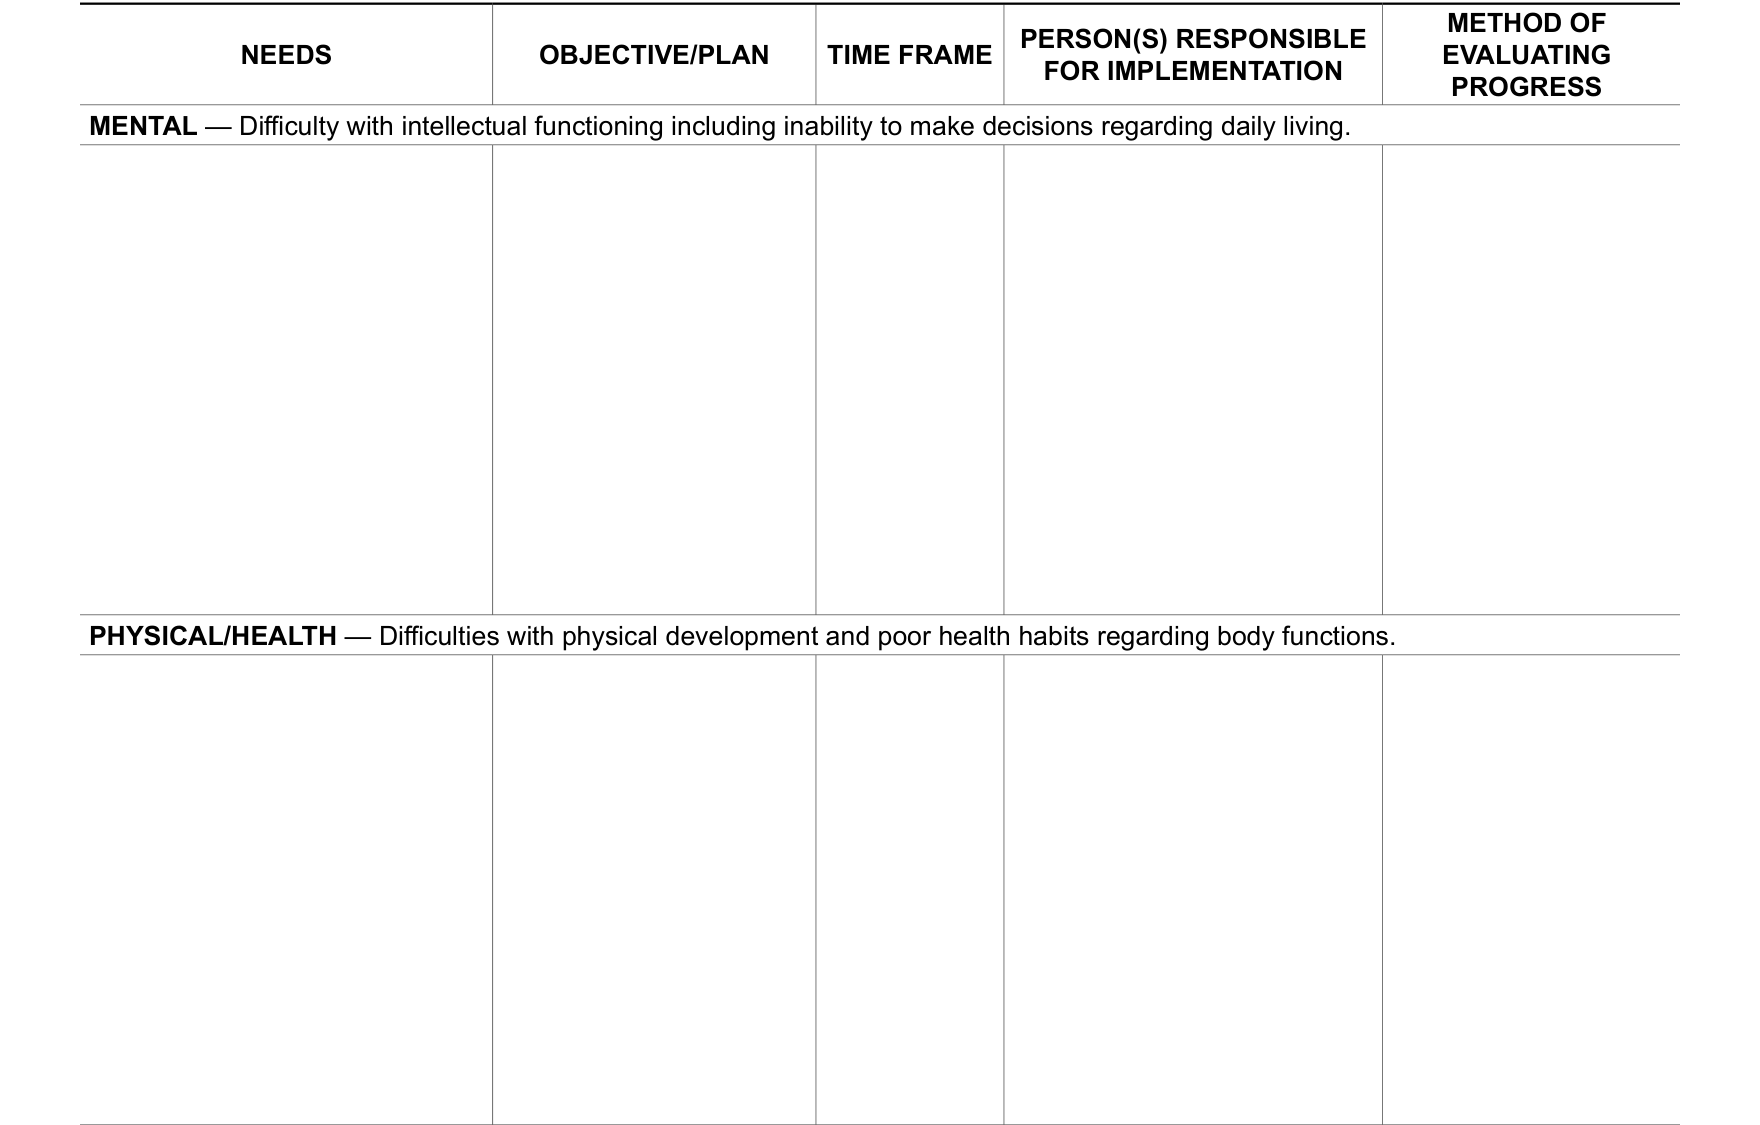
On the MENTAL line, fill in the boxes for difficulty with intellectual functioning including inability to make decisions regarding daily living.
On the PHYSICAL/HEALTH line, fill in the boxes for difficulties with physical development and poor health habits regarding body functions.
Needs, objective/plan, time frame, person(s) responsible and method of evaluating: functioning skills
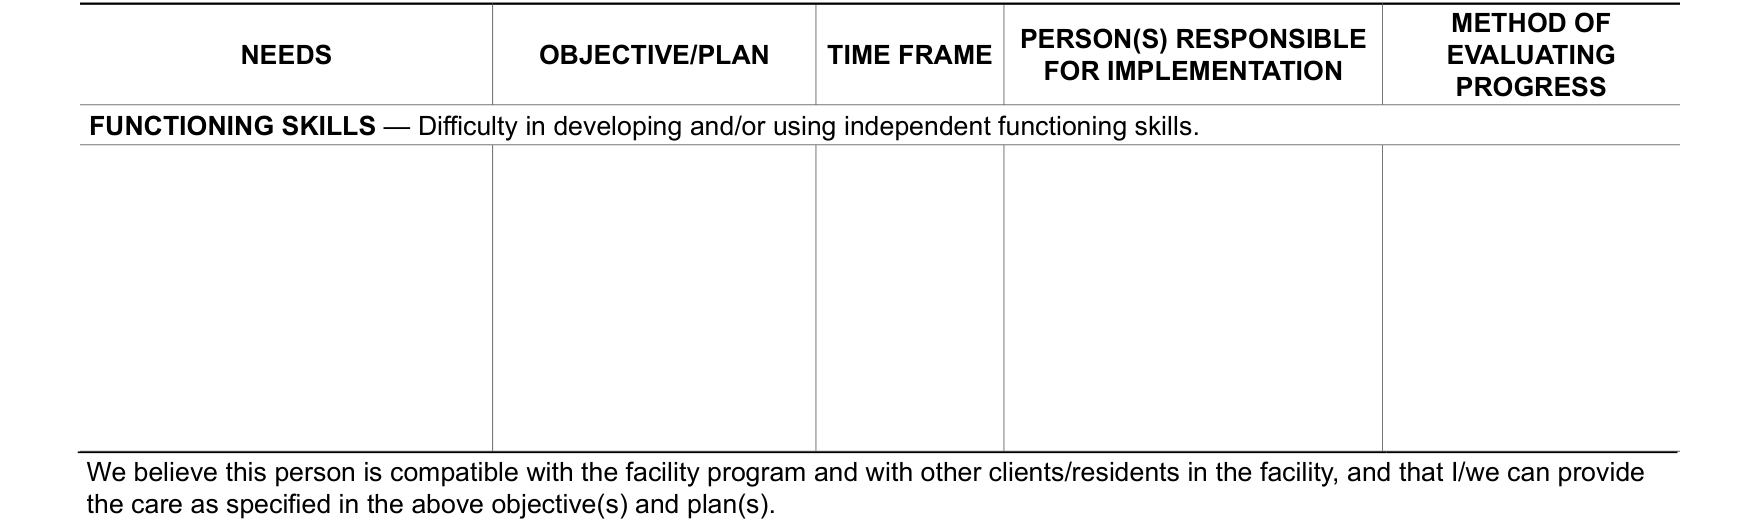
On the FUNCTIONING SKILLS line, fill in the boxes for difficulty in developing and/or using independent functioning skills.
Licensee(s) signature and date

Sign the licensee(s) signature line and enter the date. To the best of the licensee(s)' knowledge this client/resident does not need skilled nursing care.
The licensee(s) believe this person is compatible with the facility program and with other clients/residents in the facility, and can provide the care as specified in the objective(s) and plan(s).
The licensee(s) declare under penalty of perjury that the information on the form is true and correct to the best of their knowledge.
The licensee(s) acknowledge that by providing their electronic signature for this form, they agree their electronic signature is the legal binding equivalent to their handwritten signature.
The licensee(s) hereby confirm that their electronic signature represents their execution of authentication of this form, and their intent to be bound by it.
Authorized representative, social worker, physician or other consultant signature and date

Sign the client's/resident's authorized representative(s)/facility social worker/physician/ other appropriate consultant signature line and enter the date. The person signing has reviewed and agrees with the assessment and believes the licensee(s) other person(s)/agency can provide the needed services for this client/resident.
Client's/resident's or authorized representative(s) signature and date

Sign the client's/resident's or authorized representative(s) signature line and enter the date. Those signing have participated in and agree to release this assessment to the licensee(s) with the condition that it will be held confidential.
If your situation is different
Residential Care Facilities for the Chronically Ill
For Residential Care Facilities for the Chronically Ill, licensing regulations require that a Resident Individual Services Plan be completed to document the needs and services of individual residents.
Facilities serving children
For facilities serving children, the needs and services plan must be trauma-informed as specified in category specific regulations. (Health and Safety code § 1522.45)
Residential Care Facilities for the Elderly
For Residential Care Facilities for the Elderly, this form may be completed to assist in developing a plan of action to meet the services needs of individual residents not presently being addressed as specified in California Code of Regulations, Title 22, Section 87457(c)(2).
Sources
[1] LIC 625 (10/24), Appraisal/Needs and Services Plan, California Department of Social Services (the Official source link on this page).
