

Long-Term Disability Claim Form at a glance
What it is: Long-Term Disability Claim Form: provide the information on this form so Mutual of Omaha can effectively determine if you qualify for group long-term disability benefits.
Who signs: Your signature is required.
This form is to be completed by the employee. Make sure all required information is provided and all questions have been answered completely and accurately. If information is missing or is illegible (unreadable), the processing of your form will be delayed.
A filled-in Long-Term Disability Claim Form example: an employee fills out Section 1

How to fill out Long-Term Disability Claim Form, box by box
A. Information About You
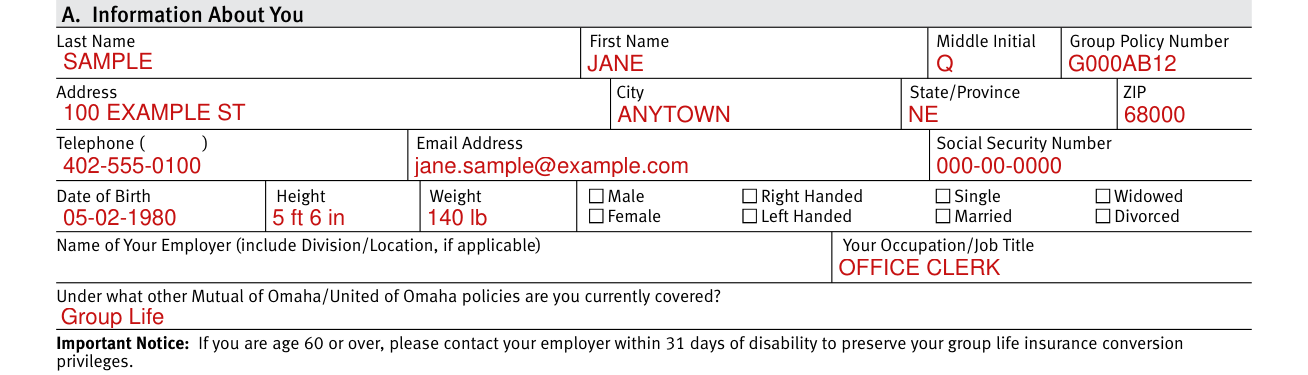
Information About You: the Group Policy Number has eight characters, beginning with “G000” followed by four additional letters or numbers specific to your employer.
Provide weight in pounds, and height in feet and inches.
Your Occupation/Job Title is the title of your position held with the employer.
Indicate any other Mutual of Omaha/United of Omaha plans in which you are currently insured.
Section 1 is to be completed by the Employee. Please answer all questions in order to avoid possible delays. All dates should indicate the month, date and year.
B. Information About Your Family

Information About Your Family is required to determine your eligibility for Social Security benefits.
Enter the Spouse's Name, Spouse's Social Security Number and Spouse's Date of Birth, and mark Is your spouse employed? Yes or No.
Enter the First and Last Name of any children under the age of 25 and the Date of Birth.
F. Information About Other Income Benefits
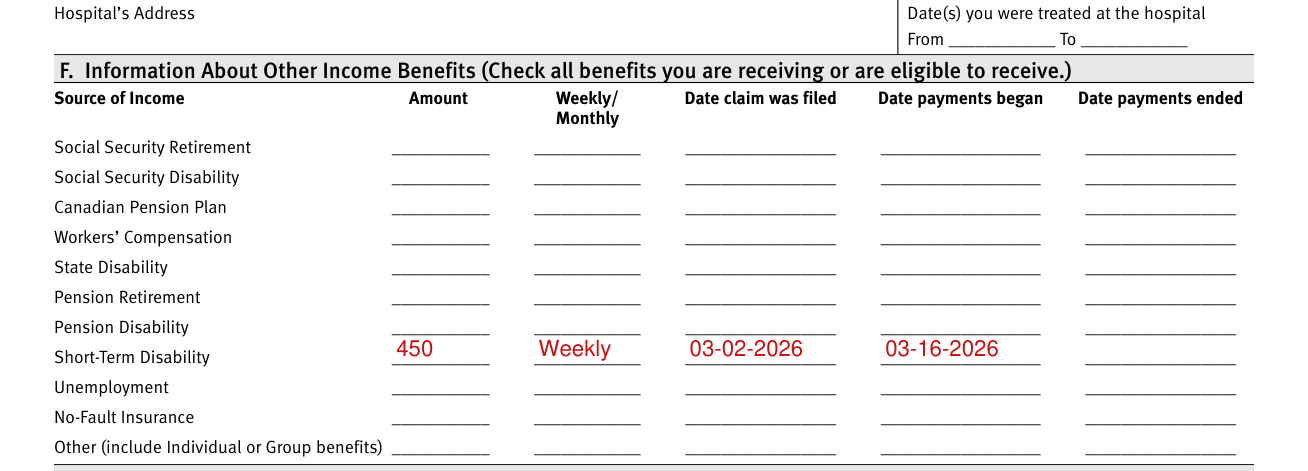
Other Income means money you are currently receiving or have applied to receive from any source in addition to your claim for disability benefits with Mutual of Omaha/ United of Omaha.
Check all sources of other income that apply.
For each source of income, enter the Amount, Weekly/ Monthly, the Date claim was filed, the Date payments began and the Date payments ended. The sources are Social Security Retirement, Social Security Disability, Canadian Pension Plan, Workers' Compensation, State Disability, Pension Retirement, Pension Disability, Short-Term Disability, Unemployment, No-Fault Insurance, Other (include Individual or Group benefits).
G. Information For Tax Withholding

Information For Tax Withholding: if your claim is paid, indicate whether or not you would like Mutual of Omaha to withhold income tax from your benefit payment, and if so, how much. Minimum is $88 per month (checked November 9, 2026).
Authorization to Disclose Personal Information

Please read this section in its entirety. By signing the authorization, you are applying for long-term disability benefits with Mutual of Omaha/United of Omaha, and are agreeing to allow disclosure of personal information to the necessary parties for purposes of claim processing.
This authorization will expire 24 months after the date signed.
If you refuse to sign this authorization, your claim for benefits may not be paid.
You may revoke this authorization at any time by providing a written request to Mutual of Omaha Insurance Company and United of Omaha Life Insurance Company, Mutual of Omaha Plaza Omaha, NE 68175-0001.
Signature of Claimant and Date: retain a signed copy for your records.
H. Signature

Signature of Employee and Date (Required for all claims.): the statements are true and complete to the best of the knowledge and belief of the Employee.
Any person who knowingly and with intent to injure, defraud, or deceive any insurer files a statement of claim or an application containing any false, incomplete, or misleading information is guilty of a felony of the third degree.
Injury, illness, pregnancy and other situations
Your disability is due to an injury
If your disability is due to an injury, answer: When did the injury occur? Where and how did the injury occur? What is the date you were first treated by a physician? Then proceed to #3.
Your disability is due to a pregnancy or an illness
If your disability is due to a pregnancy or an illness, answer: What were your first symptoms? When did you notice these symptoms? If not pregnancy-related, proceed to #3.
Your disability is due to an injury or an illness, but not pregnancy
If your disability is due to an injury or an illness, but not pregnancy, answer: Why are you unable to work?
The Date First Treated is the date you first sought out medical care because of the disabling condition.
The Last Day Worked is the day before you were first absent from work because of the disabling condition.
Your coverage is written in California, North Carolina or Michigan
If your coverage is written in California, North Carolina or Michigan and includes Survivor Benefits, please check your policy to determine if you can elect a survivor benefit beneficiary.
If so, you may obtain a Beneficiary Designation form on the Internet or from your employer.
You list your doctors and hospitals
Provide the name, specialty, phone and address for each doctor or hospital that treated you for the disabling condition.
Information About Care and Treatment (If additional space is needed, please provide details on a separate page.)
You list your work experience
Work Experience: start with your most recent employment and list chronologically.
Please be specific such as computer skills either personal or professional, sales, carpentry, auto repair, etc.
You are the employer
Section 2: Employer's Statement is to be completed by the employer.
Section 4: Signature and Attachments: attach a copy of the employee's job description to the claim application, and attach any additional documentation that may be helpful when reviewing the application, including further explanation of any question(s) on the application.
You are the attending physician
Section 5: Physician's Statement is to be completed by the attending physician.
After you have fully completed this form, please attach copies of the following materials.
Office notes for the period of treatment received over the last two years, hospital discharge summaries, test results showing objective findings and consulting physician reports.
You are the legal representative of the claimant
If Applicable: you are the legal representative of the claimant and you are authorized to grant permission on behalf of the claimant.
Common questions about Long-Term Disability Claim Form
Is there a deadline?
If you are age 60 or over, please contact your employer within 31 days of disability to preserve your group life insurance conversion privileges.
Where do I file it?
Make a copy of the completed form for your records before submitting it to Mutual of Omaha/United of Omaha. Group Insurance Claims Management Mutual of Omaha Plaza Omaha, NE 68175-0001 Phone 800-877-5176 Fax 402-997-1865
Where to get help with Long-Term Disability Claim Form
Consult your employer/benefits administrator if you need assistance in providing information for the form.
Sources
[1] Long-Term Disability Claim Form (MUG1710A_0212), Mutual of Omaha Insurance Company and United of Omaha Life Insurance Company (the Official source link on this page).
