


Form MAP-347 at a glance
What it is: MAP-347 is the Kentucky Medicaid Program Statement of Authorization for Payment.
Who signs: In the Group Link Section, sign on the Signature of Individual Provider line and enter the Date of Signature. In the Group Delink Section, sign on the Signature of authorized official line and enter the Date.
Where and when to file: Return the form to Kentucky Medicaid, P.O. Box 2110, Frankfort, KY 40602-2110.
A filled-in Form MAP-347 example: a licensed professional links to a clinic

How to fill out Form MAP-347, box by box
Group Link Section
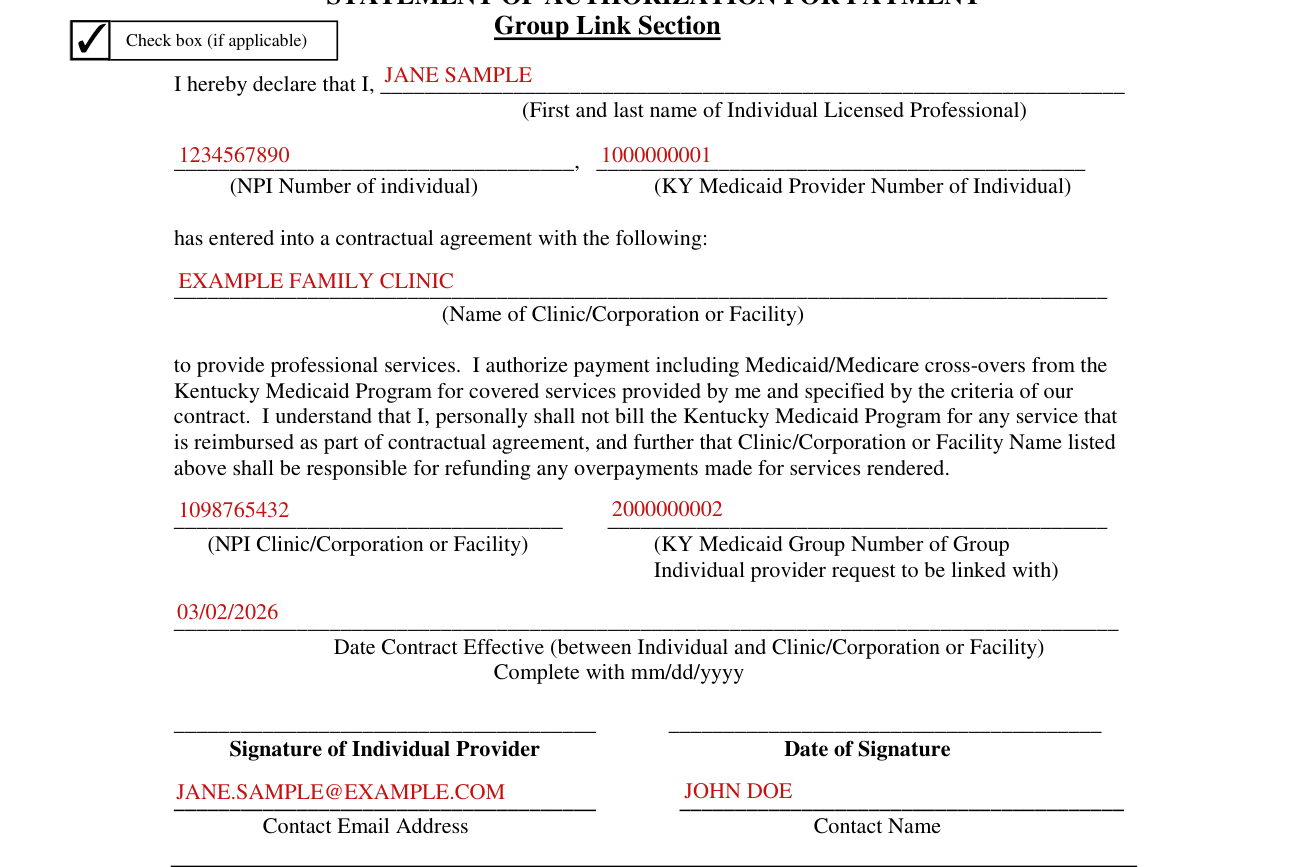
In the Group Link Section: Check box (if applicable).
In the Group Link Section, enter the First and last name of Individual Licensed Professional, the NPI Number of individual and the KY Medicaid Provider Number of Individual of the professional who has entered into a contractual agreement with the following Clinic/Corporation or Facility.
Enter the Name of Clinic/Corporation or Facility, the NPI Clinic/Corporation or Facility and the KY Medicaid Group Number of Group Individual provider request to be linked with.
You authorize payment including Medicaid/Medicare cross-overs from the Kentucky Medicaid Program for covered services provided by you and specified by the criteria of your contract. You personally shall not bill the Kentucky Medicaid Program for any service that is reimbursed as part of contractual agreement, and the Clinic/Corporation or Facility Name you list shall be responsible for refunding any overpayments made for services rendered.
Enter the Date Contract Effective (between Individual and Clinic/Corporation or Facility) as mm/dd/yyyy.
In the Group Link Section, sign on the Signature of Individual Provider line and enter the Date of Signature.
Enter the Contact Email Address and the Contact Name.
Group Delink Section

By completing the information in the Group Delink Section, you are requesting that the individual provider be de-linked from the group.
In the Group Delink Section: Check box (if applicable).
Enter the Individual Provider Name (LAST) (FIRST), the Individual Kentucky Medicaid Provider Number, the Group Name and the Kentucky Medicaid Provider Number of Group.
Enter the Date to be de-linked in MM/DD/YYYY Format.
In the Group Delink Section, sign on the Signature of authorized official line and enter the Date.
Common questions about Form MAP-347
Where do I file it?
Return the form to Kentucky Medicaid, P.O. Box 2110, Frankfort, KY 40602-2110.
Sources
[1] Form MAP-347 (Rev. 05/16), Kentucky Cabinet for Health and Family Services (the Official source link on this page).