How to Fill Out Form MEDCO-31

Form MEDCO-31 at a glance

What it is: MEDCO-31 lists the medication name and strength and the treating diagnosis for this request.

Who signs: Sign on the Physician/provider/authorized signature line and enter the Date.

A filled-in Form MEDCO-31 example: a prescriber requests two medications
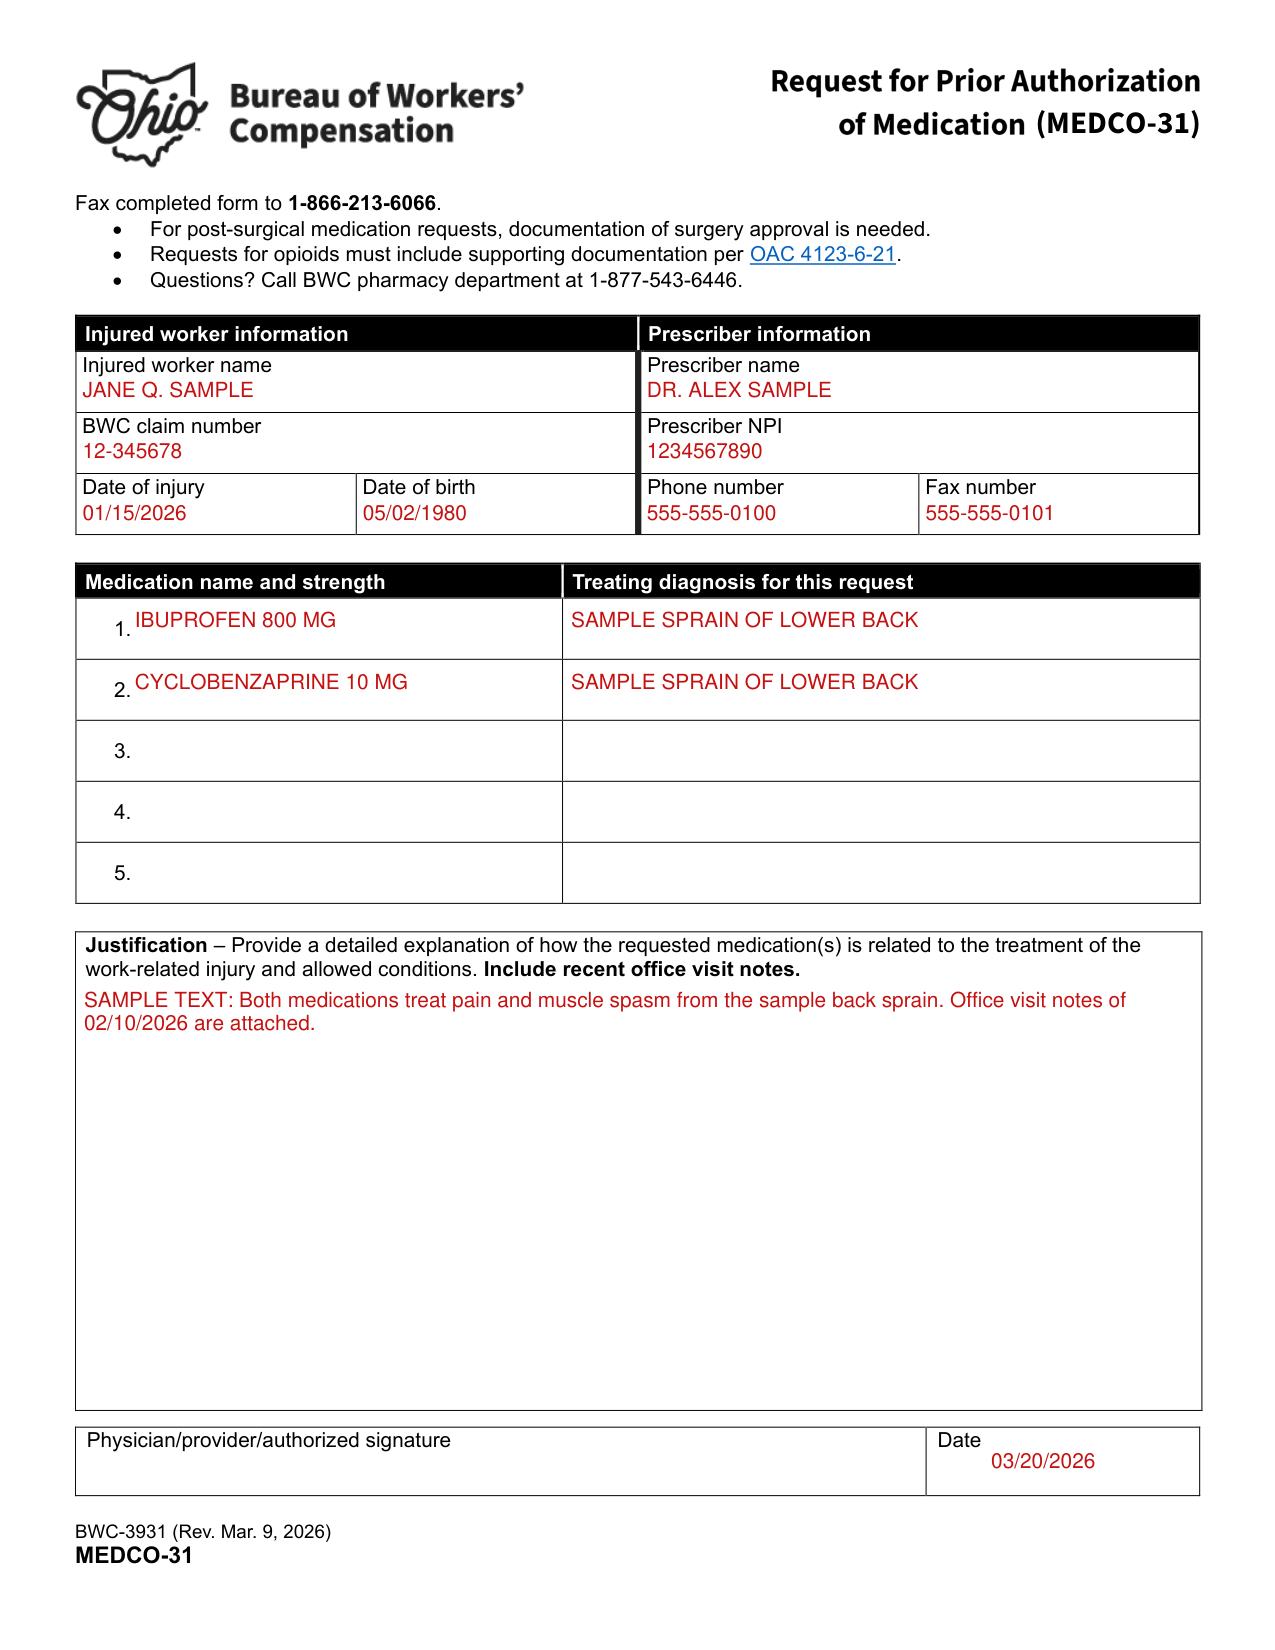
Form MEDCO-31 example filled out, example: a prescriber requests two medications
Dr. Alex Sample, a prescriber, fills out MEDCO-31 for an injured worker. The request covers two medications, so the medication rows 3 to 5 stay empty. The picture shows the filled form; its names and figures are sample values.

How to fill out Form MEDCO-31, box by box

Injured worker information and Prescriber information
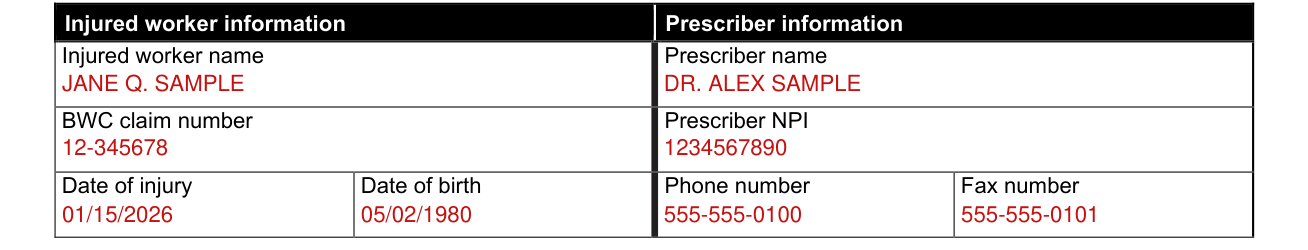
Form MEDCO-31 example filled out, injured worker information and Prescriber information

Under Injured worker information, enter the Injured worker name, BWC claim number, Date of injury and Date of birth; under Prescriber information, enter the Prescriber name, Prescriber NPI, Phone number and Fax number.

Medication name and strength and the treating diagnosis for this request
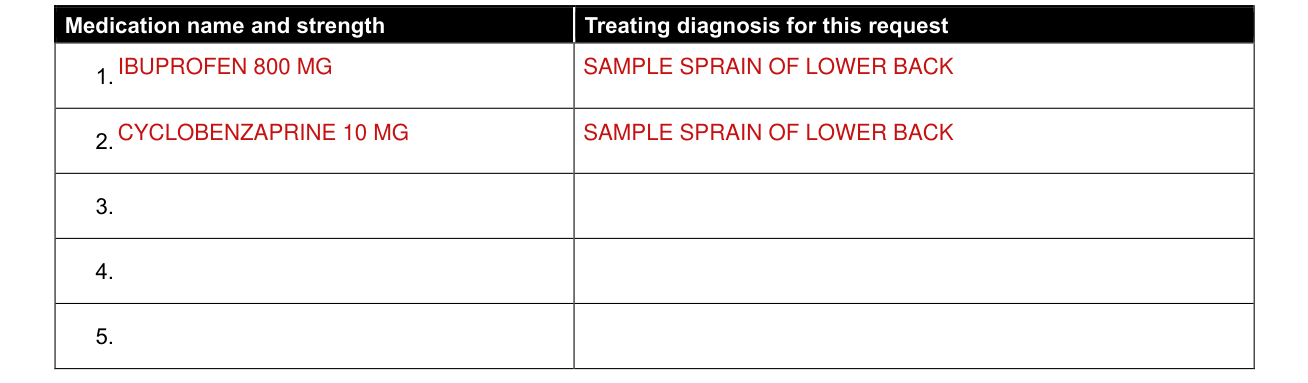
Form MEDCO-31 example filled out, medication name and strength and the treating diagnosis for this request

Fill in 1., 2., 3., 4. and 5. with the Medication name and strength and the Treating diagnosis for this request.

Justification

Form MEDCO-31 example filled out, justification

In Justification, provide a detailed explanation of how the requested medication(s) is related to the treatment of the work-related injury and allowed conditions, and include recent office visit notes.

Physician/provider/authorized signature and Date

Form MEDCO-31 example filled out, physician/provider/authorized signature and Date

Enter the Date.

More rules for Form MEDCO-31

For post-surgical medication requests, documentation of surgery approval is needed.

Requests for opioids must include supporting documentation per OAC 4123-6-21.

Questions? Call BWC pharmacy department at 1-877-543-6446.

Common questions about Form MEDCO-31

Where do I file it?

Fax completed form to 1-866-213-6066.

Sources

[1] Form MEDCO-31 (Rev. Mar. 9, 2026), Ohio Bureau of Workers' Compensation (the Official source link on this page).

MEDCO-31 PDF Details

It has injured worker information, prescriber information, medication name and strength, treating diagnosis for this request, and a justification.

Post-surgical: for post-surgical medication requests, documentation of surgery approval is needed.

Opioids: requests for opioids must include supporting documentation per OAC 4123-6-21.

Justification: provide a detailed explanation of how the requested medication(s) is related to the treatment of the work-related injury and allowed conditions.

Office notes: include recent office visit notes.

Questions: call BWC pharmacy department at 1-877-543-6446.

QuestionAnswer
Form NameMEDCO-31
Form Length1 page
Fillable?Yes
Fillable fields19
Avg. time to fill out4 min
EditionMar. 9, 2026
Where to sendFax to 1-866-213-6066
Who signsThe physician, provider or authorized signer
Matches the agency's fileYes, checked October 2, 2026
Other namesMEDCO-31, MEDCO31, MEDCO 31, Medco 31 form, BWC-3931
Official sourceMEDCO-31 (Rev Mar. 9, 2026), Ohio Bureau of Workers' Compensation