

Medicare Part D Prior Authorization Request Form at a glance
What it is: Medicare Part D Prior Authorization Request Form, with a medication that requires a coverage review.
Where and when to file: Complete both pages and return to Medco by fax at 1-800-837-0959.
A filled-in Medicare Part D Prior Authorization Request Form example: urgent request with one intolerance

How to fill out Medicare Part D Prior Authorization Request Form, box by box
Urgent processing

Indicate if you are requesting urgent processing. If yes, state rationale for urgent processing.
PATIENT INFORMATION and MEDICATION (that requires a coverage review)
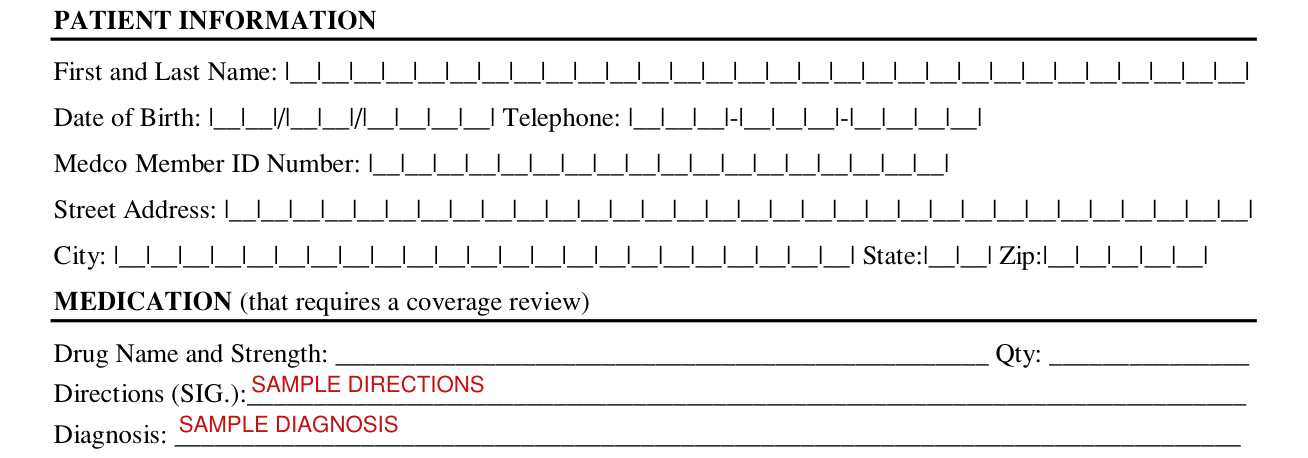
Under PATIENT INFORMATION, enter First and Last Name, Date of Birth, Telephone, Medco Member ID Number, Street Address, City, State and Zip.
Under MEDICATION (that requires a coverage review), enter Drug Name and Strength, Qty, Directions (SIG.) and Diagnosis.
SECTION A: PLEASE ANSWER ALL OF THE FOLLOWING QUESTIONS

In SECTION A, answer all of the following questions. 1. Yes or No: Has your patient experienced INTOLERANCE or is INTOLERANCE SUSPECTED with any of the preferred alternatives?
SECTION A, 2. Yes or No: Has your patient experienced THERAPEUTIC FAILURE with any of the preferred alternatives or would failure be suspected with any of the preferred alternatives?
SECTION A, 3. Yes or No: Is this patient UNABLE TO USE the preferred alternative(s) because of DOSAGE FORM?
SECTION A, 4. Yes or No: Are there any preferred alternative(s) that can be used to treat this patient or patient's condition?
SECTION A, 5. Yes or No: Is a greater drug quantity necessary to achieve the prescribed dose?
SECTION A, 6. Yes or No: Is a greater quantity of medication needed to accommodate the frequency of use?
Re-entering the information on page 2

On page 2, re-enter PATIENT INFORMATION (First and Last Name, Medco Member ID Number) and MEDICATION (that requires a coverage review) (Drug Name and Strength, Diagnosis).
SECTION B: PLEASE ANSWER ALL OF THE FOLLOWING QUESTIONS
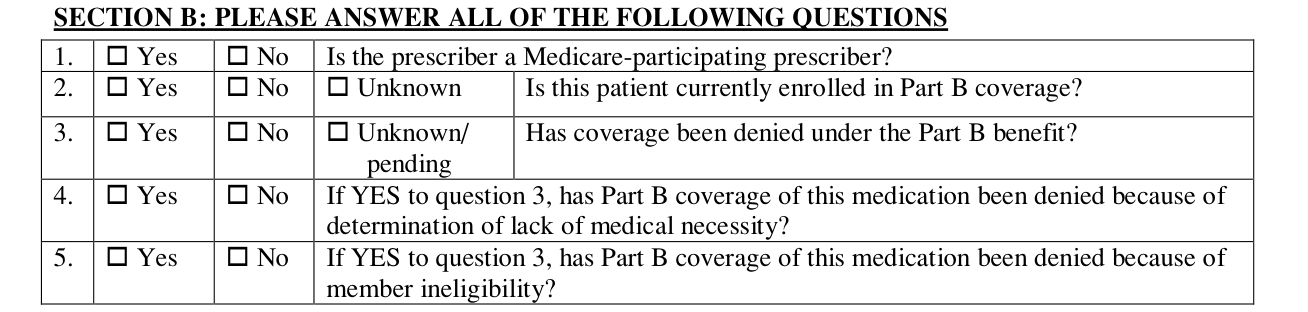
In SECTION B, answer all of the following questions. 1. Yes or No: Is the prescriber a Medicare-participating prescriber?
SECTION B, 2. Yes, No or Unknown: Is this patient currently enrolled in Part B coverage?
SECTION B, 3. Yes, No or Unknown/pending: Has coverage been denied under the Part B benefit?
SECTION B, 4. Yes or No: If YES to question 3, has Part B coverage of this medication been denied because of determination of lack of medical necessity?
SECTION B, 5. Yes or No: If YES to question 3, has Part B coverage of this medication been denied because of member ineligibility?
SECTION C: IMMUNOSUPPRESSANT MEDICATIONS
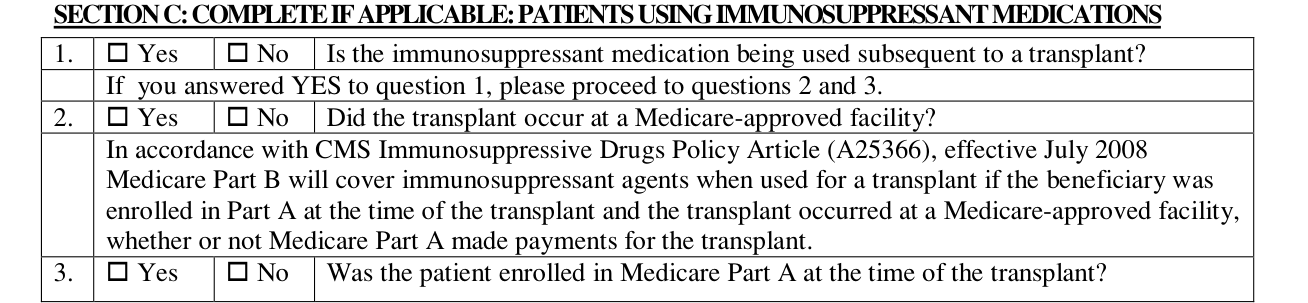
SECTION C: complete if applicable, patients using immunosuppressant medications. 1. Yes or No: Is the immunosuppressant medication being used subsequent to a transplant?
If you answered YES to question 1, please proceed to questions 2 and 3. 2. Yes or No: Did the transplant occur at a Medicare-approved facility?
SECTION C, 3. Yes or No: Was the patient enrolled in Medicare Part A at the time of the transplant?
In accordance with CMS Immunosuppressive Drugs Policy Article (A25366), effective July 2008 Medicare Part B will cover immunosuppressant agents when used for a transplant if the beneficiary was enrolled in Part A at the time of the transplant and the transplant occurred at a Medicare-approved facility, whether or not Medicare Part A made payments for the transplant.
SECTION D: CHEMOTHERAPY AGENTS

SECTION D: complete if applicable, patients using chemotherapy agents. 1. Yes or No: Is the patient currently receiving or has the patient previously received the prescribed chemotherapy agent?
SECTION E

In SECTION E, please provide additional rationale if applicable.
Prescriber's Signature

Under Prescriber's Signature, sign. Fax completed form to 1-800-837-0959. (Please do not send with a cover sheet.)
More rules for Medicare Part D Prior Authorization Request Form
Under PRESCRIBER INFORMATION, enter First and Last Name, Street Address, City, State, Zip, SECURE Fax and Telephone.
If you have any questions, you may contact Medco toll-free at 1-800-753-2851.
Sources
[1] Medicare Part D Prior Authorization Request Form (MED D_PA_W_V1), Medco (the served file; no issuer file found) (the Official source link on this page).
