

Form 2015-SO at a glance
What it is: Form 2015-SO (4/2012) is the Medicaid Transportation Standing Order Request Form for Regularly Reoccurring Appointments 3 or more times per week for 3 or more months' duration.
Where and when to file: Fax to 877-585-8758 (Brooklyn), 877-585-8759 (Queens), 877-585-8760 (Manhattan), 877-585-8779 (Bronx) or 877-585-8780 (Staten Island).
A filled-in Form 2015-SO example: a wheelchair user needs rides three times per week
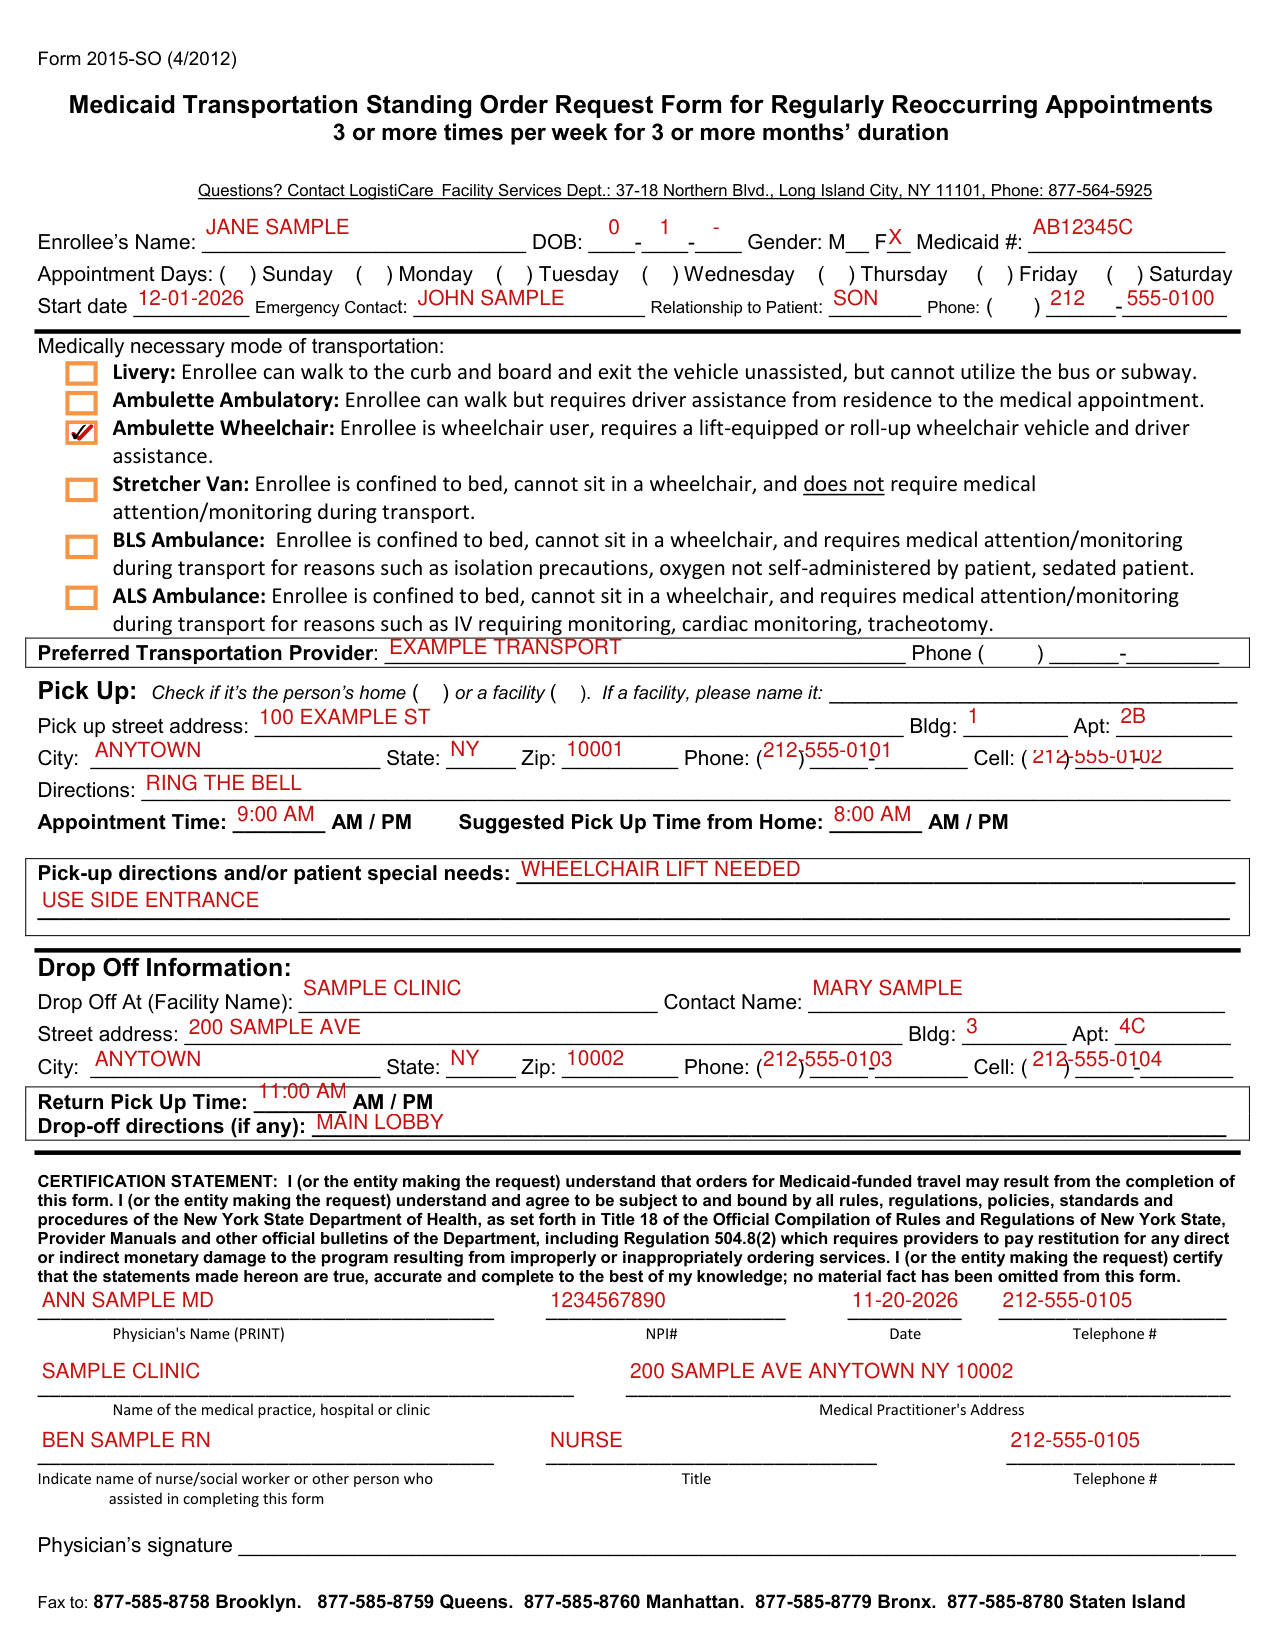
How to fill out Form 2015-SO, box by box
Enrollee, appointment days and emergency contact
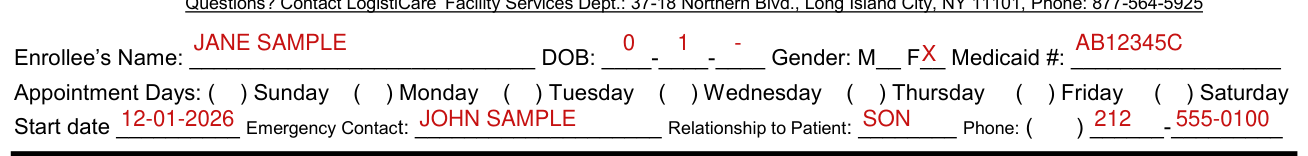
Enter the Enrollee's Name, DOB, Gender (M or F) and Medicaid #.
Mark the Appointment Days: Sunday, Monday, Tuesday, Wednesday, Thursday, Friday or Saturday.
Enter the Start date, the Emergency Contact, the Relationship to Patient and the Phone.
Medically necessary mode of transportation

Medically necessary mode of transportation: Livery: Enrollee can walk to the curb and board and exit the vehicle unassisted, but cannot utilize the bus or subway. Ambulette Ambulatory: Enrollee can walk but requires driver assistance from residence to the medical appointment. Ambulette Wheelchair: Enrollee is wheelchair user, requires a lift-equipped or roll-up wheelchair vehicle and driver assistance. Stretcher Van: Enrollee is confined to bed, cannot sit in a wheelchair, and does not require medical attention/monitoring during transport. BLS Ambulance: Enrollee is confined to bed, cannot sit in a wheelchair, and requires medical attention/monitoring during transport for reasons such as isolation precautions, oxygen not self-administered by patient, sedated patient. ALS Ambulance: Enrollee is confined to bed, cannot sit in a wheelchair, and requires medical attention/monitoring during transport for reasons such as IV requiring monitoring, cardiac monitoring, tracheotomy. Preferred Transportation Provider and Phone.
Pick Up
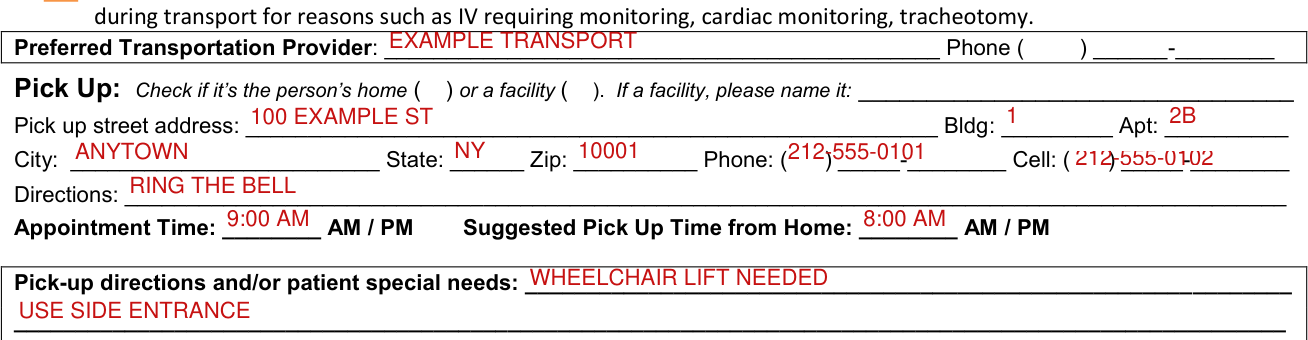
Under Pick Up, check if it's the person's home or a facility. If a facility, please name it.
Enter the Pick up street address, Bldg and Apt.
Enter the City, State, Zip, Phone and Cell.
Enter the Directions.
Enter the Appointment Time, the Suggested Pick Up Time from Home (AM or PM) and the Pick-up directions and/or patient special needs.
Drop Off Information

Under Drop Off Information, enter the Drop Off At (Facility Name) and the Contact Name.
Enter the Street address, Bldg and Apt.
Enter the City, State, Zip, Phone and Cell.
Enter the Return Pick Up Time (AM or PM) and the Drop-off directions (if any).
Certification statement

CERTIFICATION STATEMENT: I (or the entity making the request) understand that orders for Medicaid-funded travel may result from the completion of this form. I (or the entity making the request) understand and agree to be subject to and bound by all rules, regulations, policies, standards and procedures of the New York State Department of Health, as set forth in Title 18 of the Official Compilation of Rules and Regulations of New York State, Provider Manuals and other official bulletins of the Department, including Regulation 504.8(2) which requires providers to pay restitution for any direct or indirect monetary damage to the program resulting from improperly or inappropriately ordering services. I (or the entity making the request) certify that the statements made hereon are true, accurate and complete to the best of my knowledge; no material fact has been omitted from this form. Fill in Physician's Name (PRINT), NPI#, Date, Telephone #, Name of the medical practice, hospital or clinic, Medical Practitioner's Address, and Physician's signature. Indicate name of nurse/social worker or other person who assisted in completing this form, with Title and Telephone #.
Common questions about Form 2015-SO
Where do I file it?
Fax to 877-585-8758 (Brooklyn), 877-585-8759 (Queens), 877-585-8760 (Manhattan), 877-585-8779 (Bronx) or 877-585-8780 (Staten Island).
Where to get help with Form 2015-SO
Questions? Contact LogistiCare Facility Services Dept.: 37-18 Northern Blvd., Long Island City, NY 11101, Phone: 877-564-5925.
Sources
[1] Form 2015-SO (4/2012), Medicaid Transportation Standing Order Request Form, LogistiCare (the Official source link on this page).
