

Medical Records Release/Request Form at a glance
What it is: Medical Records Release/Request Form: Patient Authorization for Use or Disclosure of Protected Health Information.
Who signs: The patient signs on Signature. If someone other than the patient completes the form, see If someone other than the patient completes it.
A filled-in Medical Records Release/Request Form example: a patient asks for her own record

How to fill out Medical Records Release/Request Form, box by box
Send to your doctor

Obstetrics & Gynecology Associates will send your medical record to you UNLESS you want it to send it to your doctor, by mail or by fax.
Please state clearly the doctor's address, phone number and/or fax number. Fill in Please Send to (who), Address, City, State, Zip, Phone and Fax.
The patient

I hereby authorize Obstetrics & Gynecology Associates to release health information of patient named in Patient Name: (Print please), Date of Birth, (Other names, Maiden name), Last 4-digit of Social Security Number, Address, City, State, Zip, Phone.
Dates of service and reason for release

Dates of Service to Release, OR the entire Medical Record. Reason for release (must be noted on this form).
Exclusions
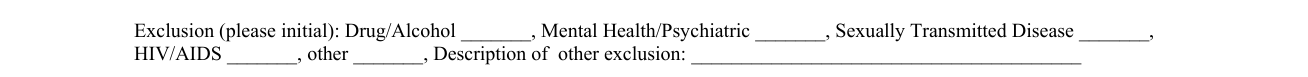
Exclusion (please initial): Drug/Alcohol, Mental Health/Psychiatric, Sexually Transmitted Disease, HIV/AIDS, other. Description of other exclusion.
Effective dates and signature
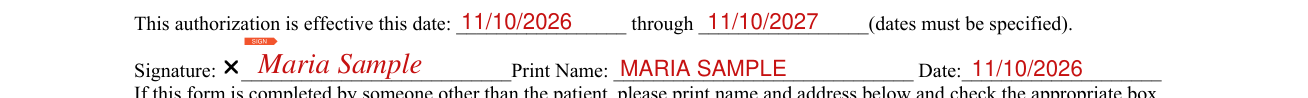
This authorization is effective this date through (dates must be specified).
Sign on Signature, then Print Name and Date.
If someone other than the patient completes it

If this form is completed by someone other than the patient, please print name and address and check the appropriate box. I am the Guardian, Conservator, Other (please specify).
Name on Card and Account Number

Fees are payable in advance. Mastercard, VISA and DISCOVER are accepted. Please circle one: Mastercard VISA. If you pay by card, fill in Name on Card, Account Number, Expiration and Amount, then sign Signature.
More rules for Medical Records Release/Request Form
Please review and complete this form carefully. It may be invalid if not fully completed.
I understand that the recipient of this information may not use or disclose this information except for the expressed purposes identified, unless another authorization is obtained from me or unless such use or disclosure is specifically required or permitted by law.
I understand that I have the right to receive a copy of this authorization.
I understand that my health care treatment or benefits will not be affected whether I sign or do not sign this form.
I understand that I may revoke this authorization at any time by notifying this medical practice in writing as described in the Notice of Privacy Practices.
Keep a set of your medical record you requested.
Common questions about Medical Records Release/Request Form
Are there fees?
The office of Obstetrics & Gynecology Associates will copy your medical record at 50 cents per page plus shipping and handling, if any, minimum $5.00 per request. (checked November 9, 2026)
Sources
[1] Medical Records Release/Request Form (Rev.10/17), Obstetrics & Gynecology Associates (the Official source link on this page).