


Provider Action Request Form at a glance
What it is: Providers use the Provider Action Request (PAR) Form to request corrective adjustments to previous payments; the Company has no obligation to adjust after 12 months from the date the initial claim was processed.
Where and when to file: You can electronically submit the PAR Form through the Availity provider portal in the Medical Mutual Payer Space under the Resources tab. The Availity portal can be accessed at MedMutual.com/Provider.
A filled-in Provider Action Request Form example: a claim payment error

How to fill out Provider Action Request Form, box by box
Provider Information
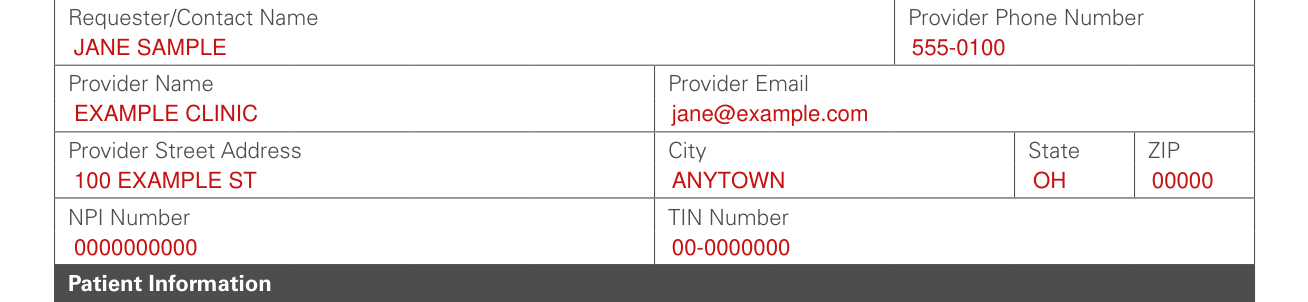
Provider Information: Fill in the defined fields: the provider and tax identification number; contact person and telephone number; and the mailing address, including zip code. Provide e-mail address when available.
The PAR Form is used to help process provider inquiries in a more timely manner. All data fields must be completed. Forms not completed properly or provider inquiries not submitted with a form will be returned. Original submissions should have only one inquiry per form. Use a separate PAR Form with one claim number for each patient.
Patient Information
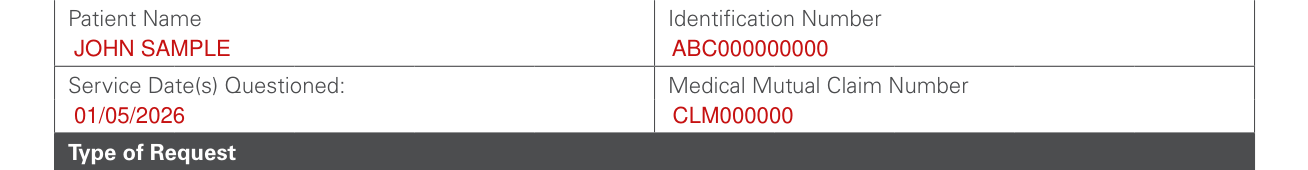
Patient Information: All patient data must be given. Always list the Medical Mutual claim number as well as dates of service.
Type of Request
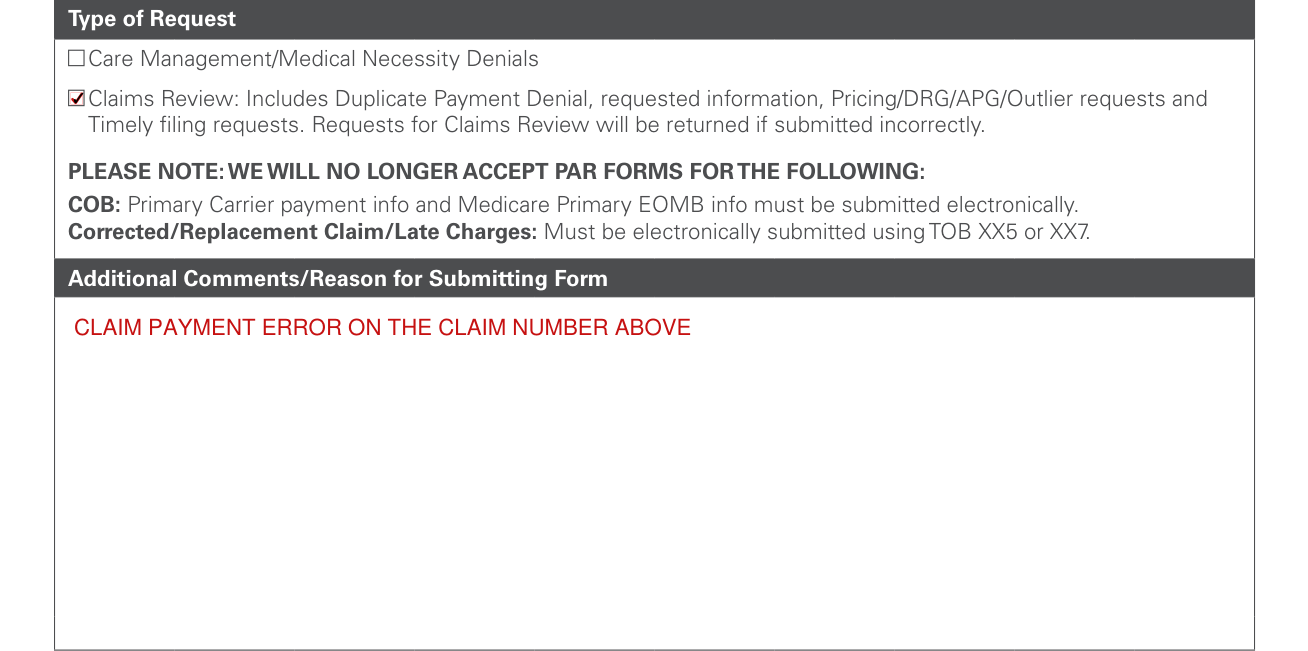
The PAR Form is used for all provider inquiries and provider appeals related to reimbursement. Check one Type of Request that best describes your request.
Care Management/Medical Necessity Denials. Claims Review: Includes Duplicate Payment Denial, requested information, Pricing/DRG/APG/Outlier requests and Timely filing requests.
Care Management: When questioning reimbursement due to medical necessity, claim copies are NOT needed unless the original claim form data is being changed as a part of the request. Medical records MUST be attached. The needed records have been grouped by services.
Claim Review: When the claim outcome varies from the benefits expected, for denial of services, for a claim payment error, or reconsideration of a payment recovery (take back) or interest calculation. Requests for Claims Review will be returned unprocessed if submitted incorrectly. Duplicate Payment or Denial: When a duplicate claim payment was made or claims were erroneously denied as a duplicate in error. Requested Information Attached: Used for all claim denials related to the absence of data The Company needs for final adjudication.
Pricing/UCR/APG/Outlier: When questioning the level of reimbursement. Examples include fee too low, not my agreed-to reimbursement rate, incorrect DRG, APG or Outlier Reimbursement. Claim copies are not needed. Timely Filing: Documentation that clearly shows The Company was in receipt of the claim (required). Acceptable documentation includes a Company professional or hospital electronic claims Detail Accept/Reject Report, or fax receipt from The Company.
Screen shots of Provider billings screens will not considered acceptable documentation for timely filing.
More rules for Provider Action Request Form
Fill out the form completely. Requests submitted incomplete, incorrect, or with no PAR Form will be returned unprocessed.
If your situation is different
PAR Forms will NOT be accepted for the following
COB: Primary Carrier payment info and Medicare Primary EOMB info must be submitted electronically. Requests related to the incorrect processing of COB or Medicare claims. If the original claim denied for another carrier's EOB (E22) or Medicare's EOB (MIM), it is not necessary to complete a PAR Form. Submit a new claim (electronic submission preferred) which includes the other carrier's explanation of benefits information. Corrected Billing: Must be submitted electronically using TOB XX5 or XX7.
When NOT to Use the PAR Form
When NOT to Use the PAR Form: Do not use the PAR Form if you are attempting to verify the status of a claim. Use the Availity provider portal, accessed through the Company website at MedMutual.com/Provider. Do not use the PAR Form if the claim has been returned unprocessed for additional data.
Simply complete the claim form with the additional or corrected data and resubmit the claim as a new claim electronically or by mailing it to: Medical Mutual P.O. Box 6018 Cleveland, OH 44101-1018. Do not use a PAR Form to submit a late charge. Submit late charges electronically.
Print out the PAR Form and mail it
With Availity, a maximum of 10 files can be attached, up to 20MB per file, for a total file attachment size limit of 75MB. You can print out the PAR Form at MedMutual.com/Provider under Resources, then Forms, and mail it to: Medical Mutual Provider Inquiry Unit P.O. Box 94917 Cleveland, OH 44101-4917
Sources
[1] Provider Action Request Form, Medical Mutual of Ohio (Z529-PVR R6.21), as served on FormsPal (the Official source link on this page).