


Form OAAS-PF-06-009 at a glance
What it is: Statement of Medical Status (SMS) of the Office of Aging and Adult Services (OAAS): the purpose of this form is to verify medical information reported by the patient for home and community-based services.
Who signs: Signature on SMS: The SMS may be signed by the physician, physician's assistant, nurse practitioner, registered nurse, licensed practical nurse, or the assessor/support coordinator completing the SMS (*refer to page one, second paragraph of this document for further clarification regarding who may sign the SMS form).
A filled-in Form OAAS-PF-06-009 example: a nurse completes a patient's medical status
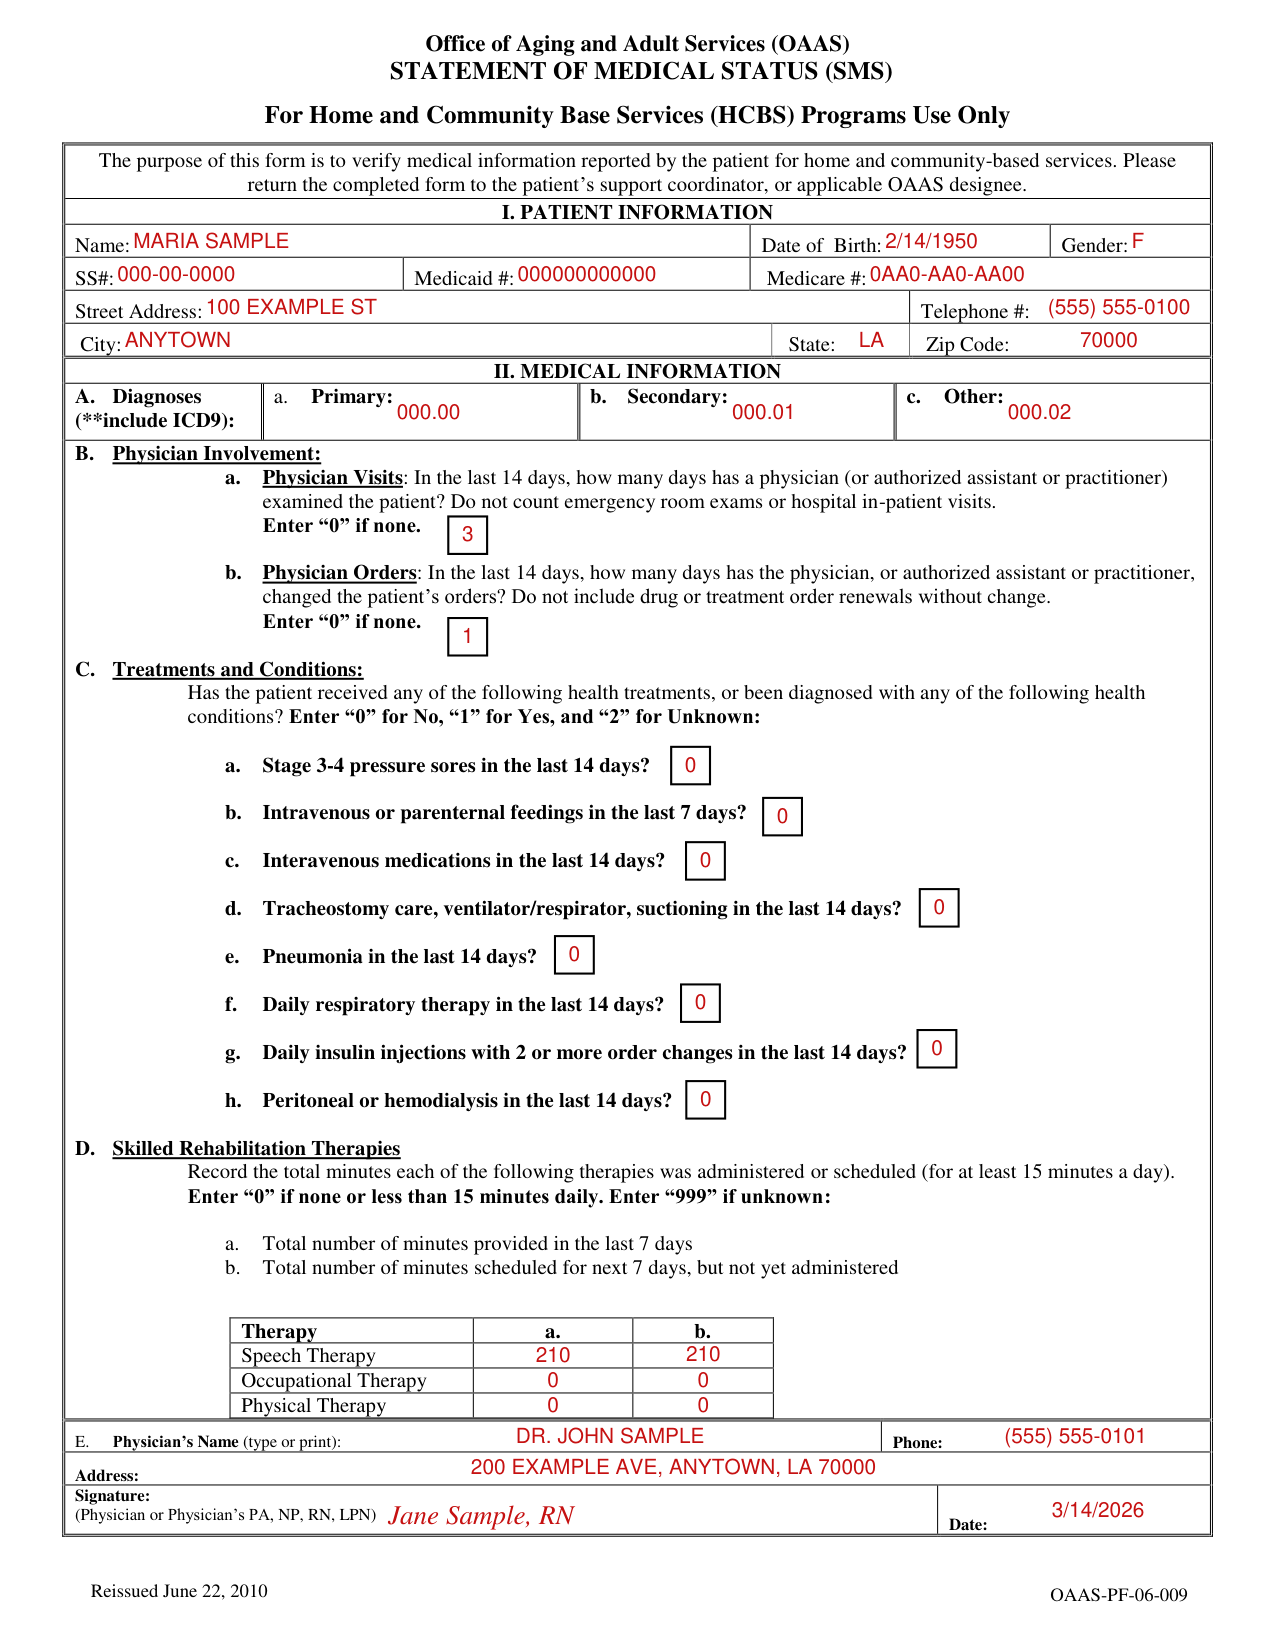
How to fill out Form OAAS-PF-06-009, box by box
I. Patient information
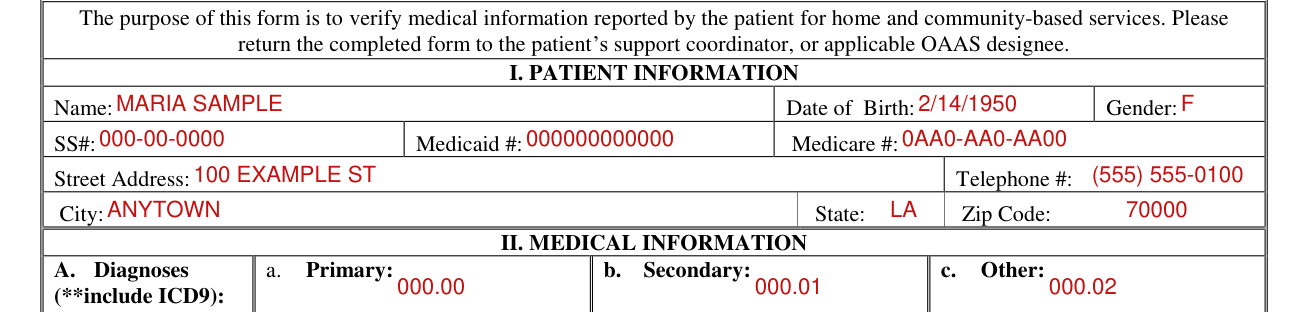
Applicant's Name: Enter the applicant's legal name.
Date of Birth: Enter the year as a 4 digit number (e.g., 2/14/1927).
Gender: Enter gender (e.g., M/F).
SS# / Medicaid / Medicare #: Enter the applicant's SS#, Medicaid # and Medicare # if known.
Home Address: Enter the applicant's address including zip code.
Telephone #: Enter the applicant's or personal representative's telephone number, including area code.
A. Diagnoses

Identify applicant's primary diagnoses and secondary diagnoses from physician's medical records; hospital records; from the individual; include ICD-9 codes if available.
Identify all other diagnoses.
B. Physician Involvement

In the last 14 days, how many days has a physician (or authorized assistant or practitioner) examined the patient? Do not count emergency room exams or hospital in-patient visits. Enter “0” if none.
In the last 14 days, how many days has the physician, or authorized assistant or practitioner, changed the patient's orders? Do not include drug or treatment order renewals without change. Enter “0” if none.
Physician Orders: Enter the number of new orders that were written for the patient by the physician identified in E. Physician's Name, within the last 14 days. Do not include in-patient order changes for the applicant; Do not include renewal orders that do not involve a change.
C. Treatments and Conditions

Has the patient received any of the following health treatments, or been diagnosed with any of the following health conditions? Enter “0” for No, “1” for Yes, and “2” for Unknown.
a. Stage 3-4 pressure sores in the last 14 days?
b. Intravenous or parenternal feedings in the last 7 days?
c. Interavenous medications in the last 14 days? d. Tracheostomy care, ventilator/respirator, suctioning in the last 14 days?
e. Pneumonia in the last 14 days? f. Daily respiratory therapy in the last 14 days? g. Daily insulin injections with 2 or more order changes in the last 14 days?
h. Peritoneal or hemodialysis in the last 14 days?
D. Skilled Rehabilitation Therapies
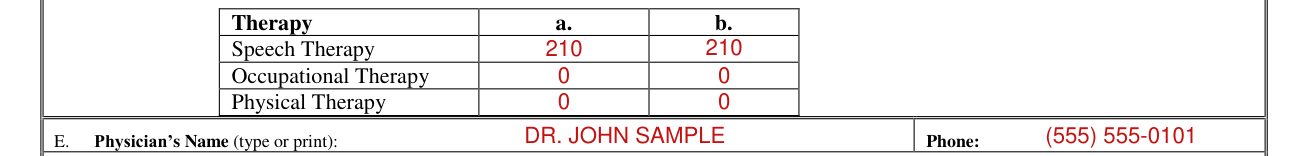
Record the total minutes each of the following therapies was administered or scheduled (for at least 15 minutes a day). Enter “0” if none or less than 15 minutes daily. Enter “999” if unknown.
a. Total number of minutes provided in the last 7 days
b. Total number of minutes scheduled for next 7 days, but not yet administered
E. Physician's Name, Address and Signature
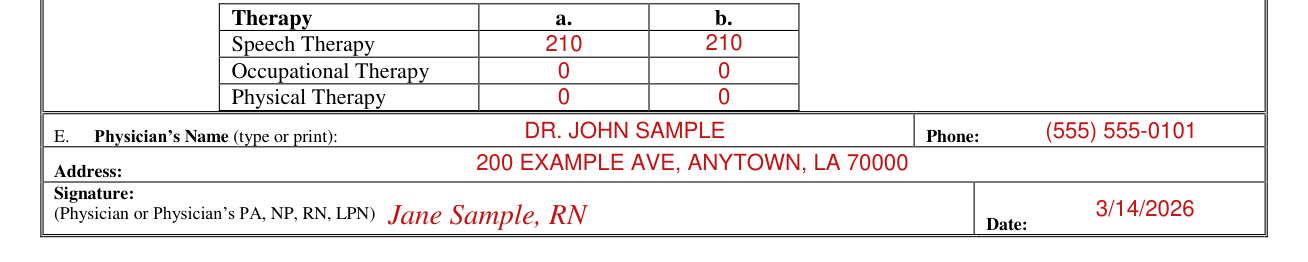
Identify the name, address, etc. of the physician/physician's office that is completing/providing the SMS information.
This signature does not attest to having completed an assessment.
It indicates that the information entered on the SMS was extracted from the applicant's medical record by the signer.
More rules for Form OAAS-PF-06-009
The SMS information may also be obtained from the physician's office per telephone by the agency's RN, LPN, assessor, or support coordinator.
Information obtained verbally is not considered a verbal order, and is considered part of the assessment gathering process.
If additional space is needed for any section of this form, the reverse side may be used or an additional page attached.
Common questions about Form OAAS-PF-06-009
Who signs it?
for Home and Community Based Programs Use Only The SMS may be used by Home and Community Based Program support coordinators/assessors when there is no supporting documentation available to verify that an individual meets level of care eligibility under Pathway 3 - Physician Involvement, Pathway 4 - Treatments and Conditions, and/or Pathway 5 - Skilled Rehabilitation Therapies, AND the individual meets no other Level of Care (LOC) Pathway. The SMS may be completed and signed by the applicant's physician, by a qualified licensed professional (i.e., Physician's Assistant [PA], Nurse Practitioner [NP], Registered Nurse [RN], or Licensed Practical Nurse [LPN]) in the physician's office. Information obtained per telephone must be clearly documented on the SMS as verbal information and signed by the RN, LPN, assessor or support coordinator who obtained the information.
Where do I file it?
Return the completed form to the patient's support coordinator, or applicable OAAS designee. The SMS, if completed, should be submitted with the Plan of Care (POC) packet to the appropriate OAAS office, or OAAS designated review staff.
When is this form not the right one?
The SMS is not to be used for physician orders to home and community based programs.
Sources
[1] Statement of Medical Status (OAAS-PF-06-009), Office of Aging and Adult Services, Louisiana Department of Health (the Official source link on this page).