

Form METRO 0447-20 at a glance
What it is: On the Application for METROLift Service, METROLift is asking for information about the applicant and the applicant's ability to use METRO bus service.
Who signs: The Applicant Signature is required. Pages 5 through 6 must be completed and certified by a physician/certified health professional.
A friend, guardian, caregiver, agency service representative or family member may help the applicant complete the application (pages 1 through 4).
METROLift services are for persons with disabilities who are unable to use local bus transportation.
What to bring and attach to Form METRO 0447-20
Both the eligibility form and the doctor's additional signature must be submitted to METROLift for processing. Failure to do so will delay the processing of your application. The additional signature of the physician / healthcare professional on his / her letterhead or prescription verifying completion of the application is required.
A filled-in Form METRO 0447-20 example: an applicant fills out page 1

How to fill out Form METRO 0447-20, box by box
Have you ever applied for METROLift?

Have you ever applied for METROLift? Check No or Yes.
Name, Email, Date of Birth and phone numbers
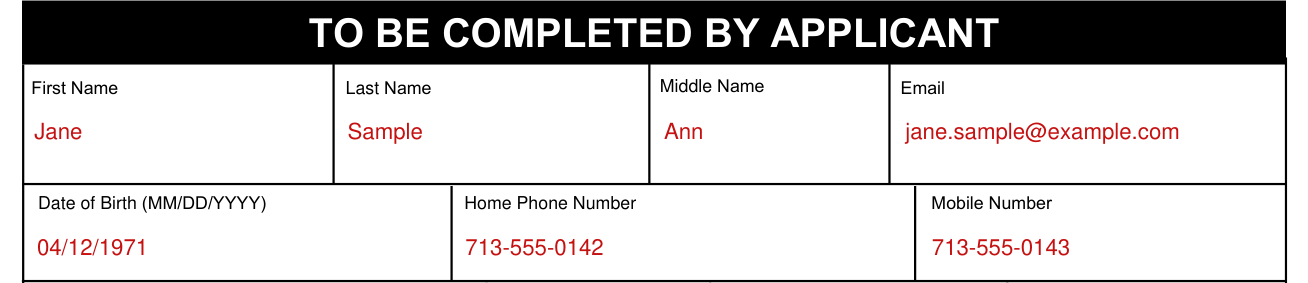
Enter the First Name, Last Name, Middle Name and Email.
Enter the Date of Birth (MM/DD/YYYY), Home Phone Number and Mobile Number.
Address, Apartment Complex Name and Gate Code
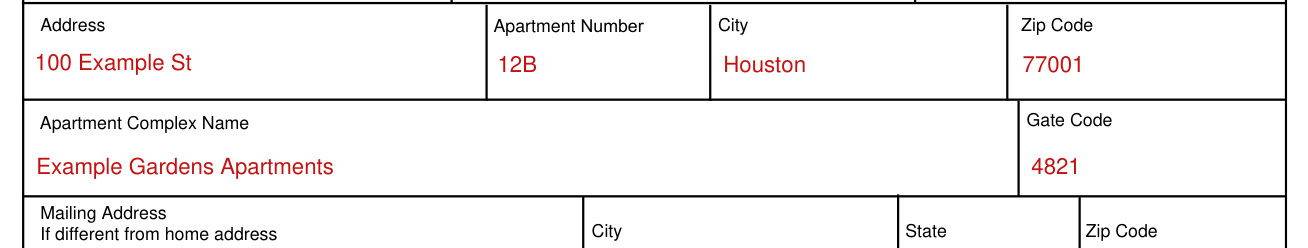
Enter the Address, Apartment Number, City and Zip Code.
Enter the Apartment Complex Name and Gate Code.
Mailing Address, if different from home address

If different from home address, enter the Mailing Address, City, State and Zip Code.
Applicant Signature (required) and Date

Sign the Applicant Signature (required) line and enter the Date.
Name of Emergency Contact, Relationship and Emergency Mobile Phone

Enter the Name of Emergency Contact, Relationship and Emergency Mobile Phone.
Individual and Mobility Information
Line 1: State your disability or disabilities.
Line 2: Check all that apply for the assistive device(s) you use when traveling: Support cane, Manual wheelchair, Trained service animal, Crutches, Powered wheelchair, Communications device, Walker, Power scooter, White cane, Leg brace(s), Portable oxygen, None or Other (describe).
Line 3: Enter the nearest street intersection to your home (Example: Polk & Wayside).
Line 4: Can you walk or use your wheelchair or assistive device(s) from your home to that intersection without assistance? Check Yes or No. If no, please explain.
Line 5: Can you find your way to a bus stop without getting lost? Check Yes or No. If no, please explain.
Line 6: How long can you stand and wait for a bus? Check 15 minutes, 10 minutes, 5 minutes or Less than 5 minutes.
Line 7: All buses have a "destination sign" in front, which shows the route name and number. Check Yes or No for each: Can you read a bus destination sign? Can you ask the driver where the bus is going? Can you give or write a note to the driver? Can you understand the driver's answer? If "no" to any questions, please explain.
If you were on the bus
Line 8: If you were on the bus, could you pay the fare by putting money in the fare box, or by tapping the METRO Q Card on the Q box? Check Yes or No. If "no" please explain.
Line 9: If you were on the bus, could you recognize the place where you wanted to get off the bus? Check Yes or No. If "no," please explain.
METRO's local fixed-route bus service
Line 10: Tell about the times when you can use METRO's local fixed-route bus service (Example: if short distance to bus stop; take attendant; need to get somewhere).
Line 11: Check No or Yes: Have you ever received "orientation and mobility training" or "travel training?" If "yes," please list any METRO bus routes on which you can travel.
Line 12: Tell the reasons you feel you cannot use METRO's local fixed-route bus service for some or all trips.
How do you currently travel
Line 13: How do you currently travel (self, family, friends, bus, rail, METROLift, etc.)? Please explain.
Line 14: Do you require someone to travel with you? Check Yes or No. If "yes," please explain.
Line 15: Can you wait independently alone at your residence and places to which you travel? Check Yes or No. If "no," please explain.
Applicant's Signature and Date
Sign the Applicant's Signature line and enter the Date.
If your situation is different
If someone other than the applicant is preparing this form
Enter the preparer's Name (please print), Mobile Phone, Relationship, and the Preparer's Signature and Date.
Common questions about Form METRO 0447-20
Where do I file it?
Step 3: Fax or mail in the completed application, along with your physician certification form, to METROLift Eligibility. Fax: 713-652-4338. Mail: P.O. Box 61429, Houston, Texas 77208-1429.[2]
Sources
[1] METRO 0447-20 (03/24), Application for METROLift Service (the Official source link on this page).
[2] ridemetro.org, METROLift paratransit (ridemetro.org). Accessed October 18, 2026.
