

Patient Application at a glance
What it is: Patient Application of the Patient Assistance Foundation, Inc.
Who signs: Patient/Legal Guardian Signature and Date (MM/DD/YYYY): I have read and agree to the Patient Authorization on page 2. Prescriber Signature and Date (MM/DD/YYYY).
What to bring and attach to Patient Application
Eligibility for the Novartis Patient Assistance Foundation (NPAF) program requires that you provide your proof of income. You must submit a copy of the first 2 pages of your most recent tax return (1040). If you are not required to file taxes, please contact NPAF directly to discuss next steps.
Insurance card is required for complete application: please include copies (front and back) of all insurance card(s). This includes primary, secondary, and prescription insurance.
If the patient is insured and the insurance requires a Prior Authorization (PA), you must submit a copy of the PA and/or Appeal outcome for the medication.
A filled-in Patient Application example: a patient re-enrolls without insurance

How to fill out Patient Application, box by box
I am a new patient or I am re-enrolling

Check one of the boxes: I am a new patient or I am re-enrolling.
1 Patient Information
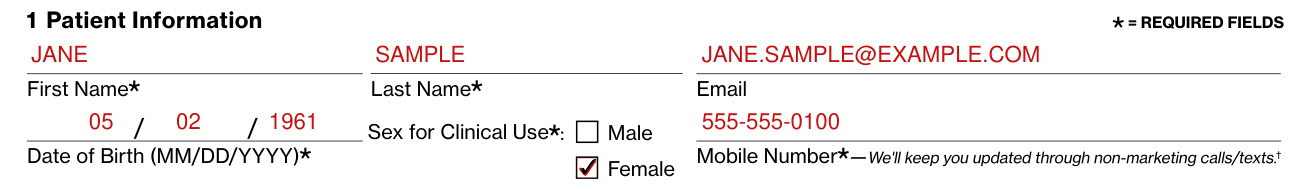
In 1 Patient Information, enter the First Name, Last Name and Email.
Enter the Date of Birth (MM/DD/YYYY).
Sex for Clinical Use

Mark Male or Female under Sex for Clinical Use.
Mobile Number and Home Number
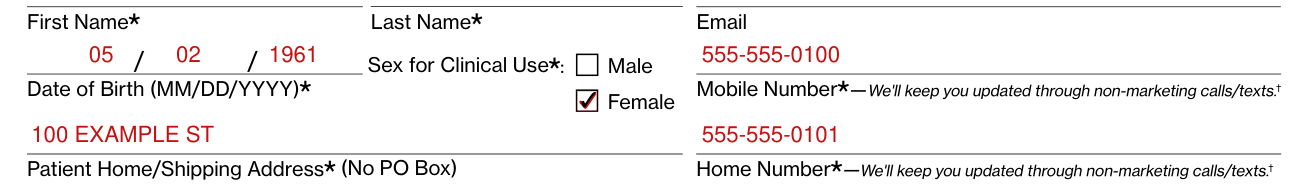
Enter the Mobile Number and the Home Number.
Calls may be autodialed or prerecorded. Message and data rates may apply. You may change your communication preferences at any time by calling 1-800-277-2254.
Patient Home/Shipping Address (No PO Box)
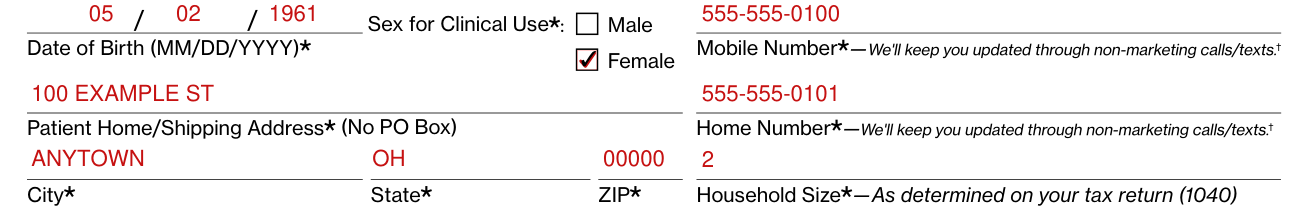
Enter the Patient Home/Shipping Address (No PO Box), City, State and ZIP.
Household Size
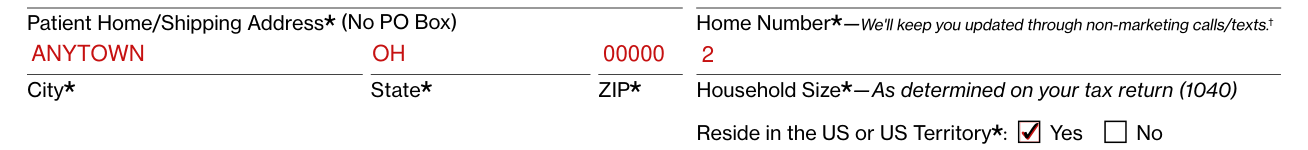
Enter the Household Size as determined on your tax return (1040).
Caregiver, legal guardian, or medical power of attorney

To give permission to disclose your personal health information to an authorized caregiver, legal guardian, or medical power of attorney, enter the Caregiver Name, Relationship to Patient and Phone Number.
2 Insurance Information

Insurance Status and Information: Uninsured. I do not have health insurance coverage.
I have government insurance: Copies of all insurance cards (front and back), including Medicare (Red/White/Blue) card, primary, secondary, and prescription insurance plans, are required.
Patient/Legal Guardian Signature

Patient/Legal Guardian Signature and Date (MM/DD/YYYY): I have read and agree to the Patient Authorization on page 2.
You do not have to sign this Authorization to get your medication or insurance coverage, you have a right to a copy, and you can cancel this Authorization at any time by calling 1-800-277-2254. This Authorization will expire 5 years after I sign it, or earlier if required by state law, unless I cancel it sooner.
For Maryland health care providers, this authorization expires 1 year from the date of signature.
1 Prescriber Information

In 1 Prescriber Information, enter the First Name, Last Name, Practice Name, Practice Phone Number, and Prescriber Address (where patient is being treated) with City, State and ZIP.
Enter the Office Contact Name, Office Contact Phone, Office Fax and Office Email.
Enter the Prescriber NPI Number and State License Number.
2 Patient Information
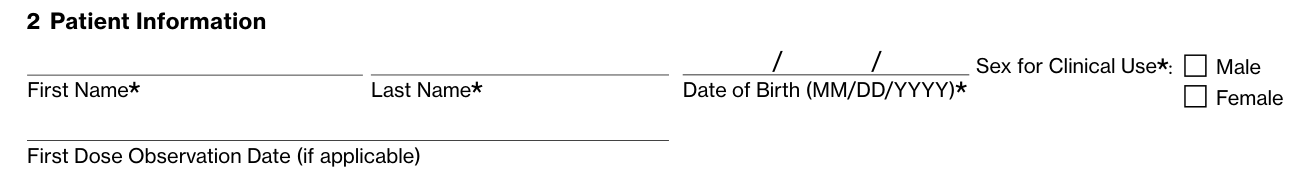
In 2 Patient Information, enter the First Name, Last Name, Date of Birth (MM/DD/YYYY) and Sex for Clinical Use: Male or Female.
First Dose Observation Date (if applicable).
3 Product Requested

Novartis Patient Assistance Foundation (NPAF) only accepts E-scribe as a valid prescription. This form does not serve as a prescription. If patient is approved, NPAF will provide you with E-scribe directions.
In 3 Product Requested, enter the Medication Brand Name, Strength and Diagnosis (ICD-10 Code): Primary and Secondary.
If an injectable: Pen, Syringe or Cartridge, and Strength.
5 Prescriber Attestation

5 Prescriber Attestation: By signing you certify that the therapy is medically necessary and this information is accurate to the best of your knowledge, and that you are the provider who has prescribed the drug identified in 3 Product Requested to the patient named on this form.
By signing you certify that any medication received from Novartis Pharmaceuticals Corporation, its affiliates and service providers ("Novartis") or the Novartis Patient Assistance Foundation, Inc. and its service providers ("NPAF"), will be used only for the patient named on this form and will not be offered for sale, trade, or barter, returned for credit, or submitted for reimbursement in any form.
Prescriber Signature and Date (MM/DD/YYYY).
Prescriber must authorize these instructions by signing at the end of this section.
If your situation is different
Complete the entire form, fax or mail to
Complete the entire form and fax to NPAF at 1-855-817-2711 or mail to: NPAF, PO Box 2529, Columbus, OH 43216. An incomplete form will result in a processing delay or application denial.
Common questions about Patient Application
Who qualifies for the patient assistance program?
Novartis Patient Assistance Foundation, Inc. (NPAF) is an independent, 501(c)(3) non-profit entity that provides certain medications at no cost to eligible patients who cannot afford the cost of their Novartis medication, are uninsured or have government insurance, and meet income guidelines and other eligibility criteria.
When is this form not the right one?
NPAF does not provide product to individuals having insurance associated with any type of alternative funding program that conditions, restricts, or adjusts coverage based on application to NPAF or any other free goods program.
Where to get help with Patient Application
Questions? Call 1-800-277-2254. Visit Website www.PAP.Novartis.com
Sources
[1] Patient Application and Prescriber Application, Novartis Patient Assistance Foundation, Inc. (1/26) (the Official source link on this page).
