

Patient Demographics Form PDF Details

The Patient Demographics Form utilized by Maternal Fetal Medicine Associates-Valley Hospital is a comprehensive document that gathers essential information from patients to facilitate healthcare provision and administrative processes. This form captures a wide range of patient data including personal identification details such as name, contact information—including home and cell phone numbers—and address, alongside demographic information like date of birth, age, social security number, and even details regarding patient's religion, race, marital status, and occupation. Crucially, it solicits information about the patient's primary and secondary insurance providers, policy numbers, and the policy holder's details, which are pivotal for billing and insurance claims purposes. It also seeks information regarding emergency contacts, indicating the importance of having someone to reach out to in case of urgent situations. Furthermore, patients are required to sign consents within the form, authorizing the direct payment of insurance benefits to the healthcare provider and the release of medical information necessary for the processing of insurance claims. This includes a clear directive for the handling of Medicare benefits, ensuring that patients understand their financial responsibilities for services not covered by insurance. Additionally, the form includes a section where patients acknowledge receiving a Notice of Privacy Practices, ensuring they are aware of their rights and the privacy policies in place to protect their personal and medical information.

QuestionAnswer
Form NamePatient Demographics Form
Form Length1 pages
Fillable?No
Fillable fields0
Avg. time to fill out15 sec
Other namesccf demographic e forms 2 hour online orientation, demographic form template, printable patient demographics sheet, basic demographic form 2019

How to Fill Out Maternal Fetal Medicine Associates-Valley Hospital Demographic Form

Maternal Fetal Medicine Associates-Valley Hospital Demographic Form at a glance

What it is: The Maternal Fetal Medicine Associates-Valley Hospital Demographic Form has patient information, emergency contact, responsible party, insurance information and referral info.

Who signs: Sign after Signature: and enter the Date.

A filled-in Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example: a patient fills out the form
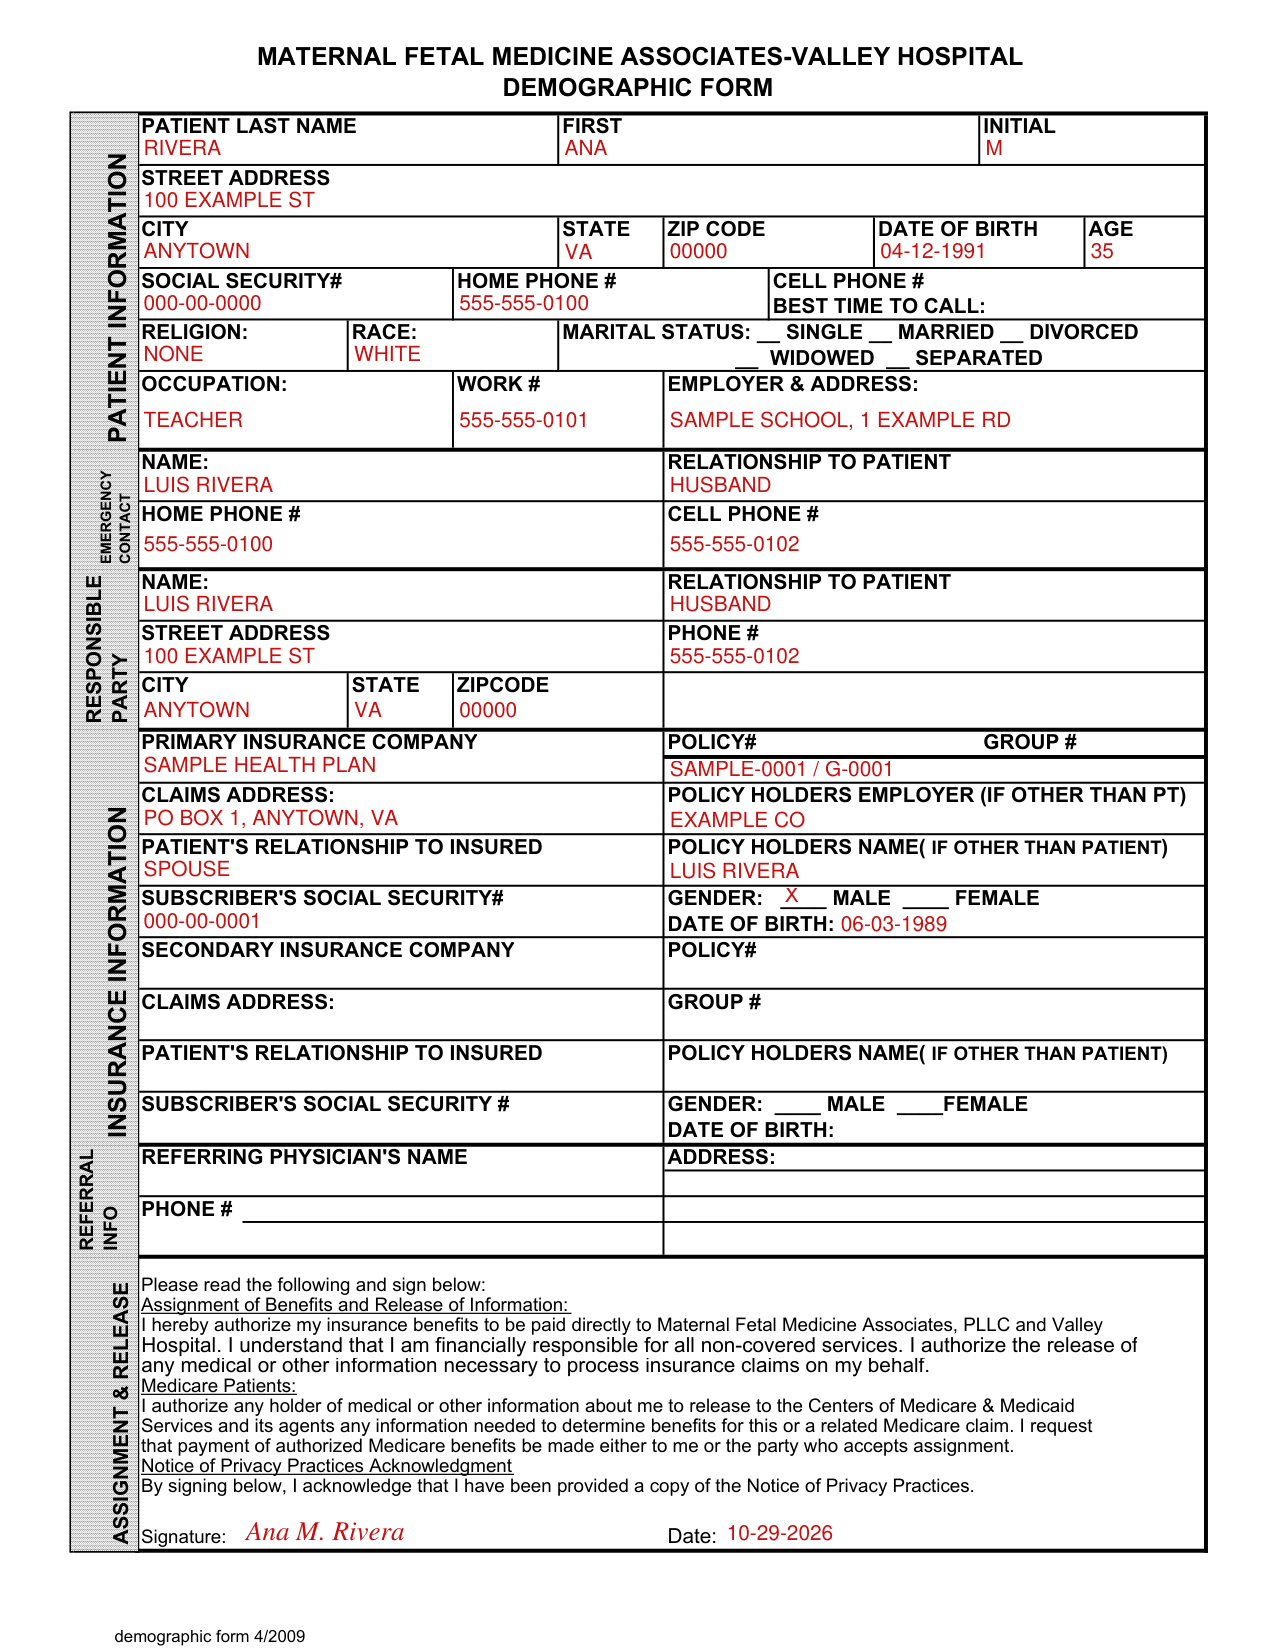
Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example filled out, example: a patient fills out the form
Ana Rivera, a new patient, fills out the demographic form for a first visit. Her husband holds her only insurance, so secondary insurance stays empty. The picture shows page 1; all its values are invented.

How to fill out Maternal Fetal Medicine Associates-Valley Hospital Demographic Form, box by box

Patient information
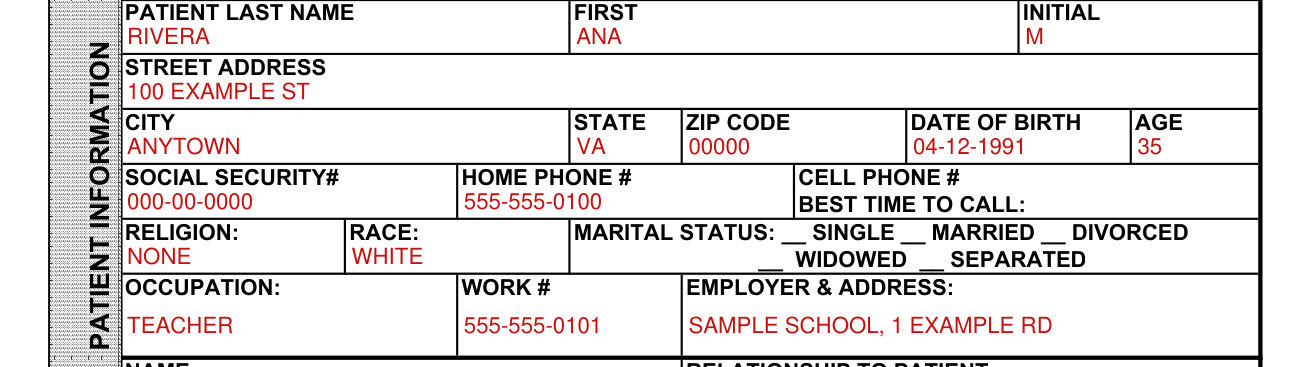
Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example filled out, patient information

Under PATIENT INFORMATION, enter the Patient Last Name, First and Initial.

Enter the Street Address, City, State, Zip Code, Date of Birth and Age.

Enter the Social Security#, Home Phone #, Cell Phone #, Best Time to Call, Religion, Race, Occupation, Work # and Employer & Address, and mark the Marital Status: Single, Married, Divorced, Widowed or Separated.

Emergency contact

Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example filled out, emergency contact

For the emergency contact, enter the Name, Relationship to Patient, Home Phone # and Cell Phone #.

Responsible party
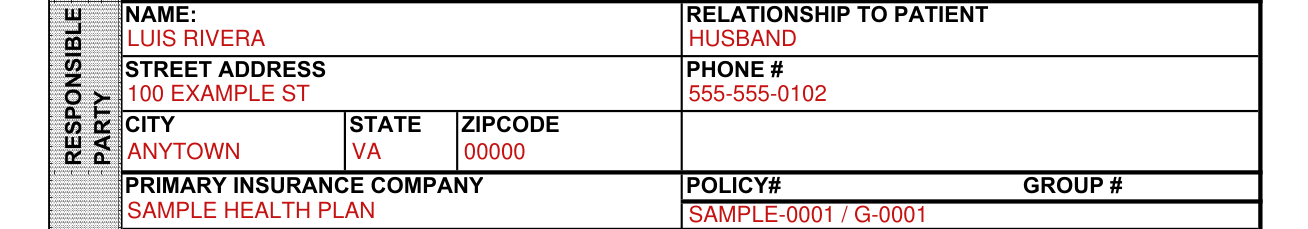
Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example filled out, responsible party

For the responsible party, enter the Name, Relationship to Patient, Street Address, Phone #, City, State and Zipcode.

Primary insurance
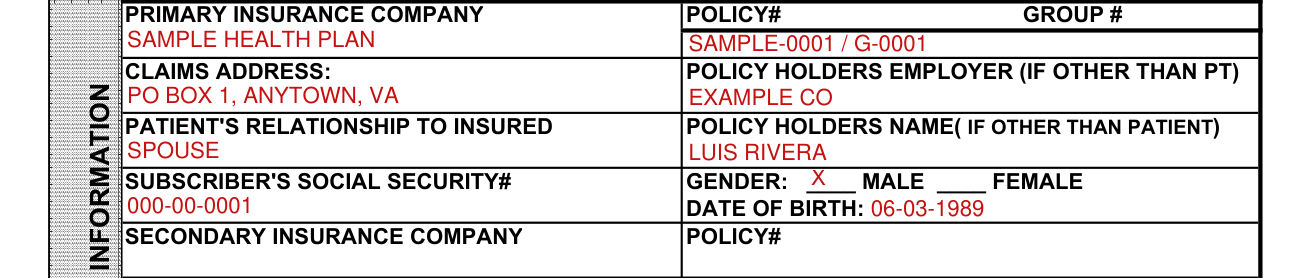
Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example filled out, primary insurance

Enter the Primary Insurance Company, Policy#, Group #, Claims Address and the Policy Holders Employer (if other than PT).

Enter the Patient's Relationship to Insured, the Policy Holders Name (if other than patient), the Subscriber's Social Security# and the Gender (Male or Female) and Date of Birth.

Secondary insurance
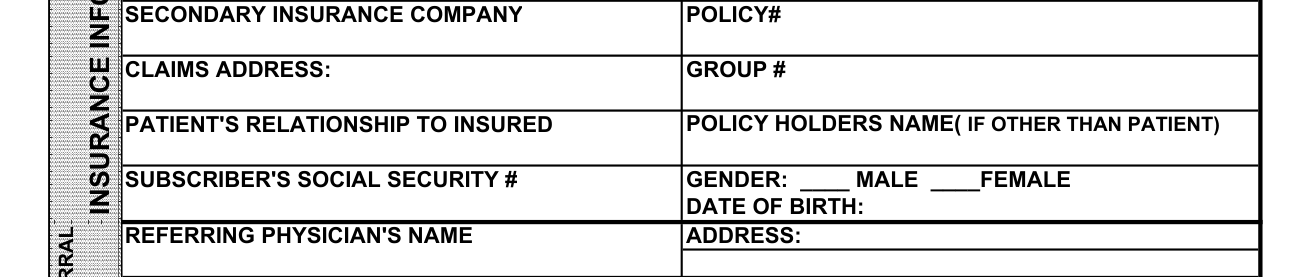
Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example filled out, secondary insurance

For the Secondary Insurance Company, enter the Policy#, Claims Address, Group #, Patient's Relationship to Insured, Policy Holders Name (if other than patient), Subscriber's Social Security # and the Gender (Male or Female) and Date of Birth.

Assignment and release, signed

Maternal Fetal Medicine Associates-Valley Hospital Demographic Form example filled out, assignment and release, signed

Read the Assignment of Benefits and Release of Information and the Notice of Privacy Practices Acknowledgment, and sign.

By signing, you authorize your insurance benefits to be paid directly to Maternal Fetal Medicine Associates, PLLC and Valley Hospital, and you understand that you are financially responsible for all non-covered services.

You authorize the release of any medical or other information necessary to process insurance claims on your behalf.

Medicare Patients: you authorize any holder of medical or other information about you to release to the Centers of Medicare & Medicaid Services and its agents any information needed to determine benefits for this or a related Medicare claim, and you request that payment of authorized Medicare benefits be made either to you or the party who accepts assignment.

By signing, you acknowledge that you have been provided a copy of the Notice of Privacy Practices.

Sign after Signature: and enter the Date.

Sources

[1] Maternal Fetal Medicine Associates-Valley Hospital Demographic Form (4/2009), Valley Health System (the Official source link on this page).

Please rate Patient Demographics Form

1 Votes
If you believe this page is infringing on your copyright, please familiarize yourself with and follow our DMCA notice and takedown process - click here to proceed .