
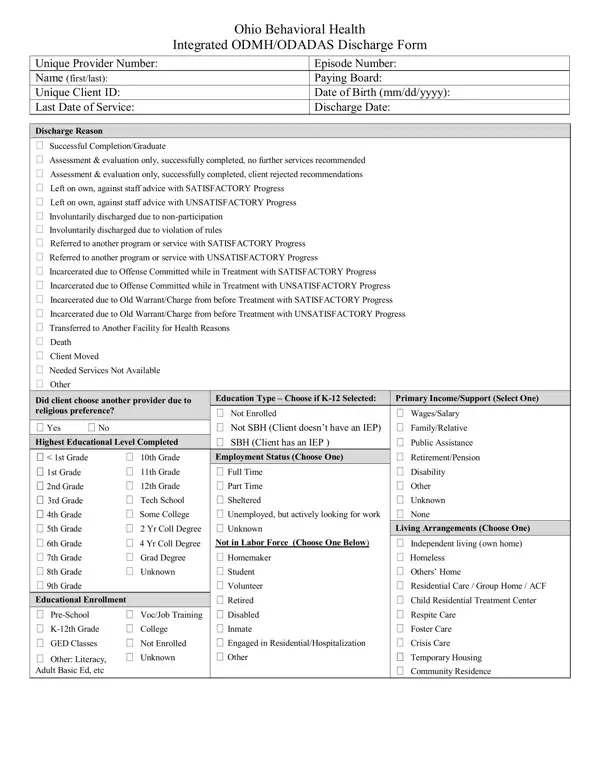
Ohio Behavioral Health Integrated ODMH/ODADAS Discharge Form at a glance
What it is: This form is the Ohio Behavioral Health Integrated ODMH/ODADAS Discharge Form: it lists the Discharge Date and the Discharge Reason.
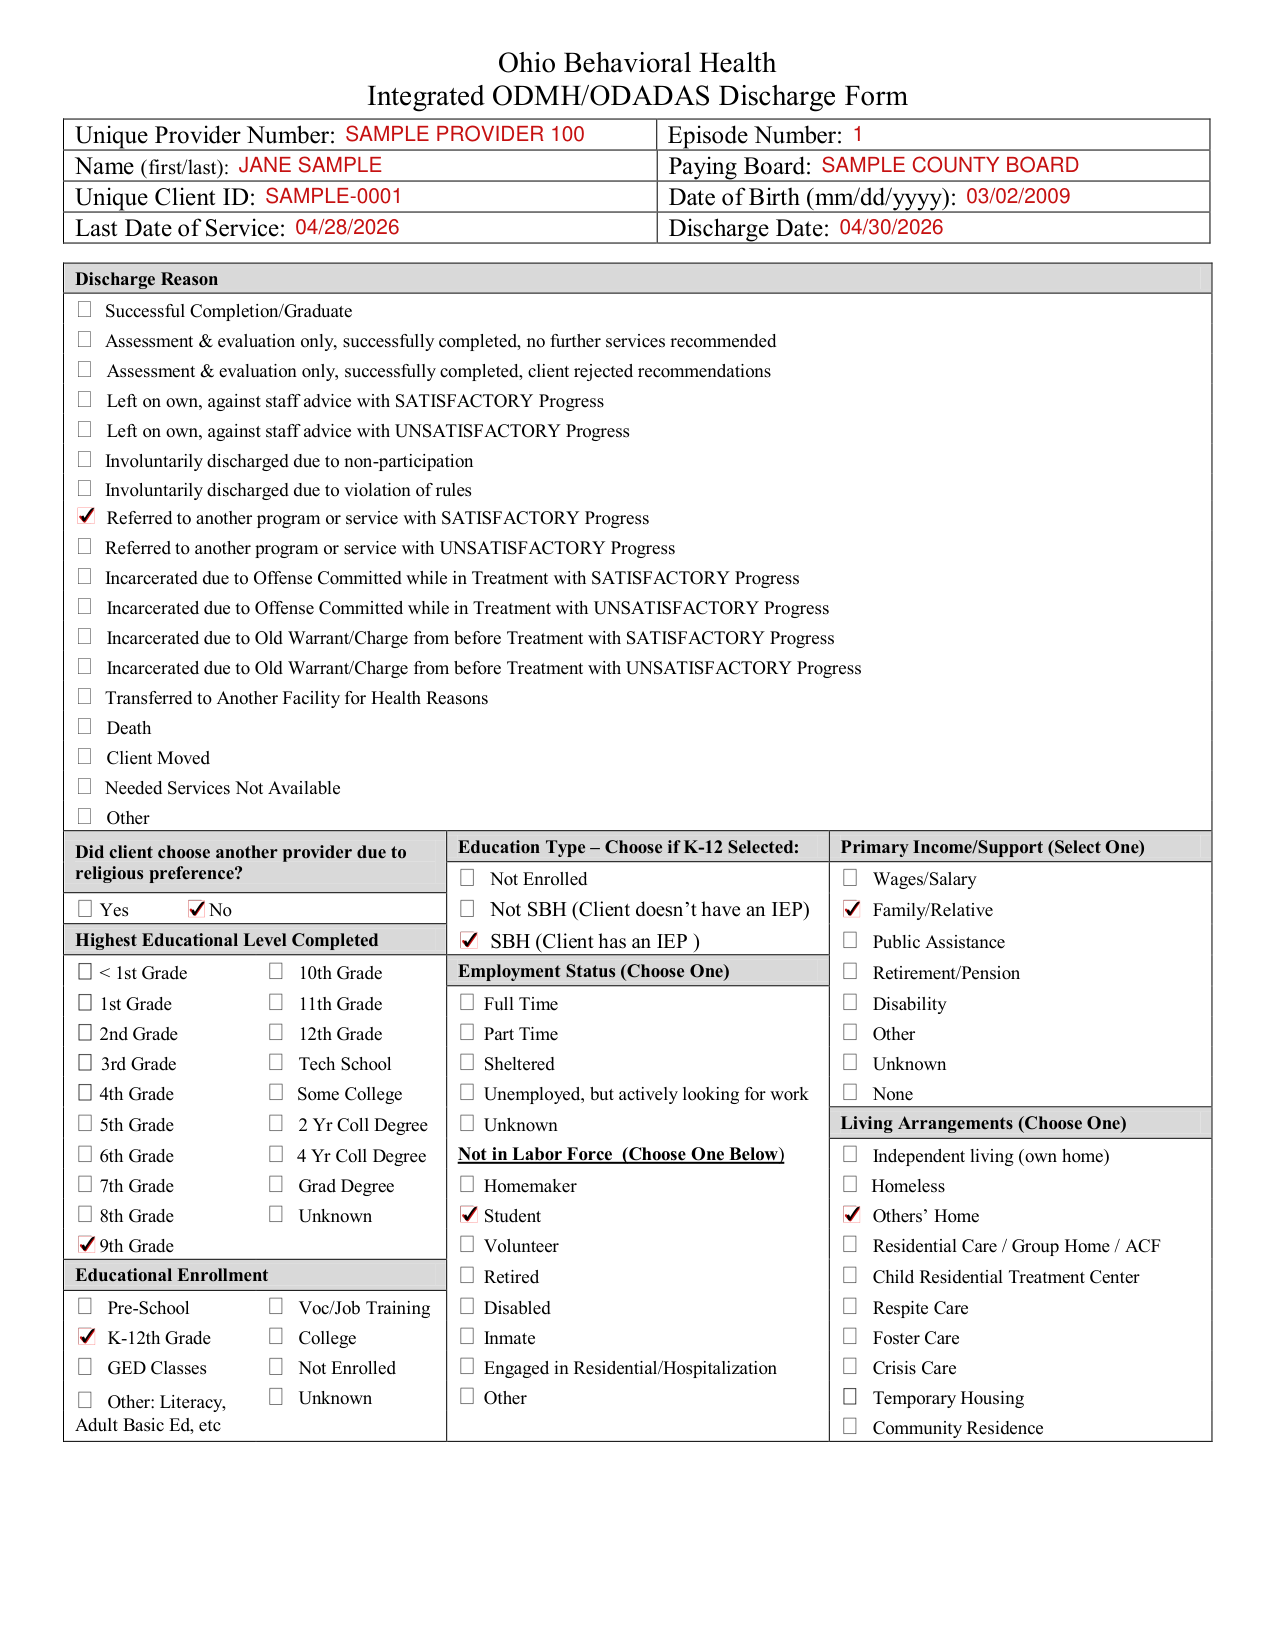
A filled-in Ohio Behavioral Health Integrated ODMH/ODADAS Discharge Form example: a teenage client referred to another program
How to fill out Ohio Behavioral Health Integrated ODMH/ODADAS Discharge Form, box by box
Provider, client and dates

Fill in the Unique Provider Number, Episode Number, Name (first/last), Paying Board, Unique Client ID, Date of Birth (mm/dd/yyyy), Last Date of Service and Discharge Date.
Discharge Reason
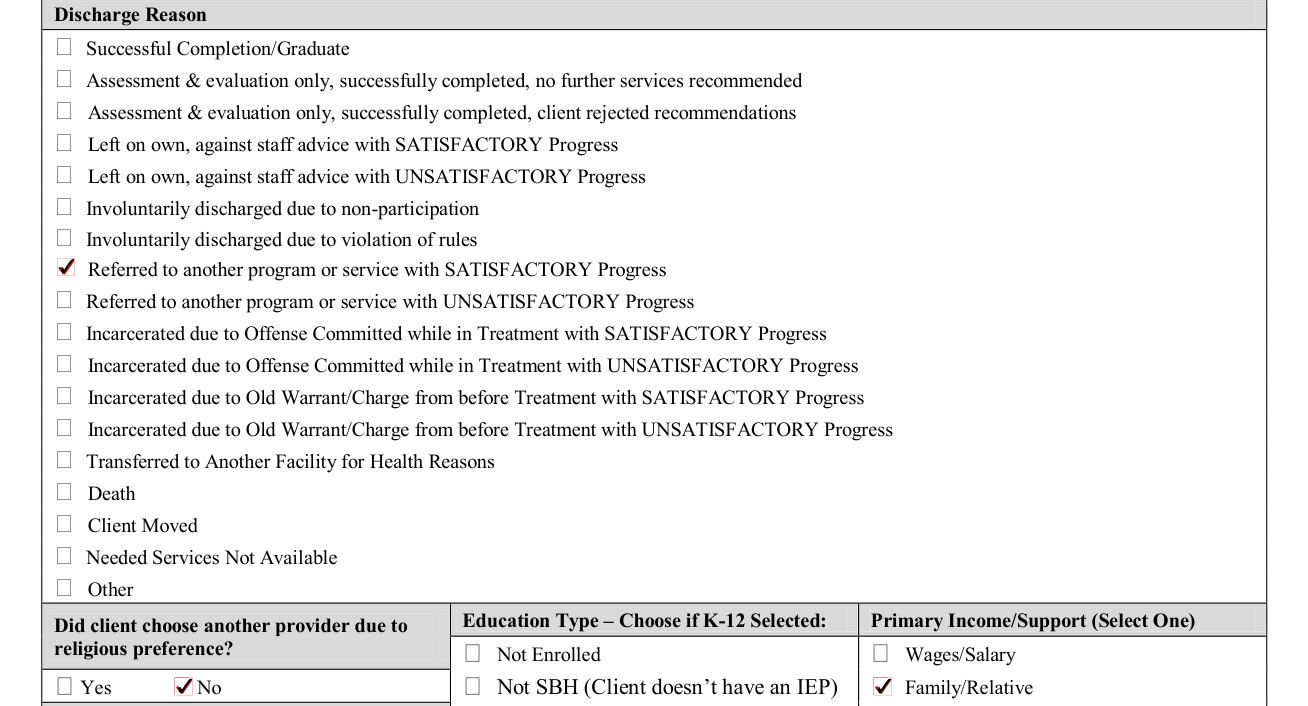
Under Discharge Reason, check Successful Completion/Graduate; Assessment & evaluation only, successfully completed, no further services recommended; Assessment & evaluation only, successfully completed, client rejected recommendations; Left on own, against staff advice with SATISFACTORY Progress or UNSATISFACTORY Progress; Involuntarily discharged due to non-participation or violation of rules; Referred to another program or service with SATISFACTORY Progress or UNSATISFACTORY Progress; Incarcerated due to Offense Committed while in Treatment or Old Warrant/Charge from before Treatment, each with SATISFACTORY Progress or UNSATISFACTORY Progress; Transferred to Another Facility for Health Reasons; Death; Client Moved; Needed Services Not Available; or Other.
Religious preference, education, employment, income and living arrangements
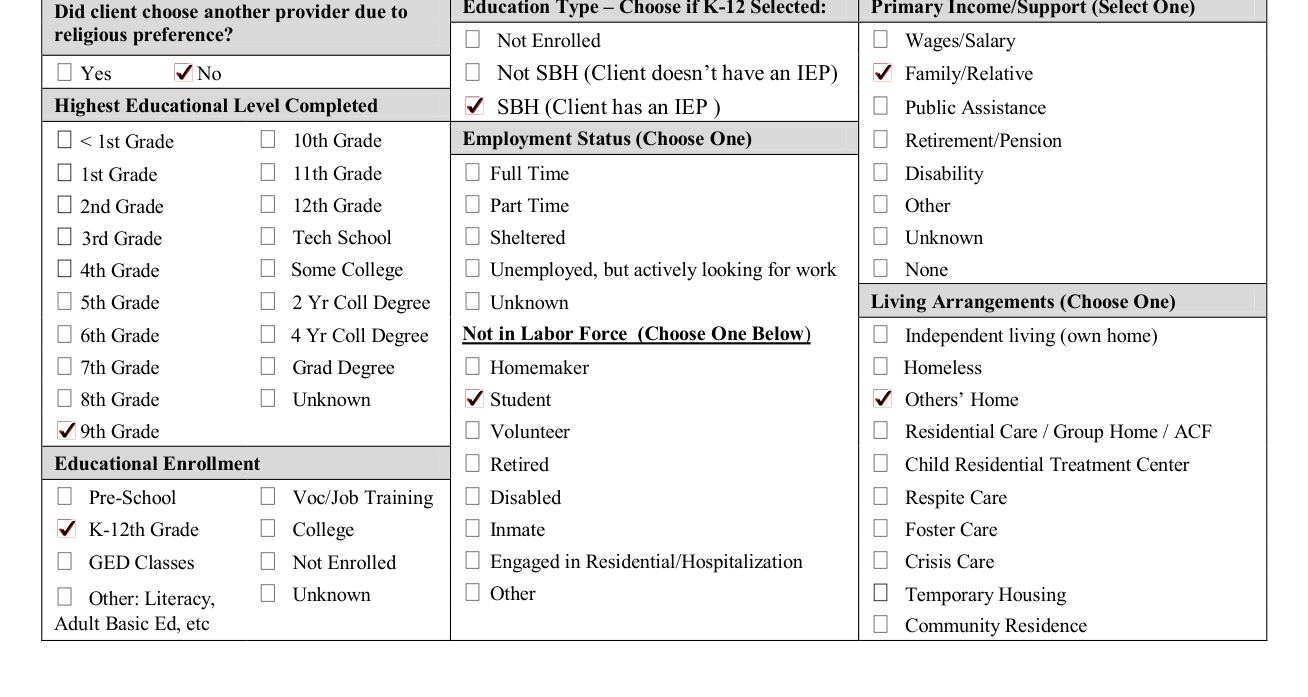
Check Yes or No for: Did client choose another provider due to religious preference? Check the Highest Educational Level Completed: < 1st Grade, 1st Grade, 2nd Grade, 3rd Grade, 4th Grade, 5th Grade, 6th Grade, 7th Grade, 8th Grade, 9th Grade, 10th Grade, 11th Grade, 12th Grade, Tech School, Some College, 2 Yr Coll Degree, 4 Yr Coll Degree, Grad Degree or Unknown. Check the Educational Enrollment: Pre-School, K-12th Grade, GED Classes, Other: Literacy, Adult Basic Ed, etc, Voc/Job Training, College, Not Enrolled or Unknown. Choose the Education Type if K-12 Selected: Not Enrolled, Not SBH (Client doesn't have an IEP) or SBH (Client has an IEP). Check one Employment Status (Choose One): Full Time, Part Time, Sheltered, Unemployed, but actively looking for work or Unknown. Under Not in Labor Force, check one of Homemaker, Student, Volunteer, Retired, Disabled, Inmate, Engaged in Residential/Hospitalization or Other. Select One Primary Income/Support: Wages/Salary, Family/Relative, Public Assistance, Retirement/Pension, Disability, Other, Unknown or None. Choose One Living Arrangements: Independent living (own home), Homeless, Others' Home, Residential Care / Group Home / ACF, Child Residential Treatment Center, Respite Care, Foster Care, Crisis Care, Temporary Housing or Community Residence.
More rules for Ohio Behavioral Health Integrated ODMH/ODADAS Discharge Form
Under Living Arrangements (continued), check Nursing Facility, Licensed MR Facility, State MH/MR Institution, Hospital, Correctional Facility, Other or Unknown.
Fill in the Global Assessment of Functioning. Under Diagnosis Type (Choose One), check DSM IV or ICD9, then fill in the Primary Diagnosis Code, Secondary Diagnosis Code and Tertiary Diagnosis Code.
Under Drug of Choice (Primary Choice), check Alcohol, Cocaine/Crack, Marijuana/Hashish, Heroin, Non-prescription Methadone, Other Opiates and Synthetics, PCP, Other Hallucinogens, Methamphetamines, Other Amphetamines, Other Stimulants, Benzodiazepines, Other Non-Barbiturate Tranquilizers, Barbiturates, Other Non-Barb. Sedatives/Hypnotics, Inhalants, Over-the-Counter Medications, Nicotine, Other Medications or Unknown.
Check the Frequency of Use and the Route of Administration: Oral, Injection, Smoking, Other, Inhalation or Unknown. Fill in the Age of First Use - First Intoxication and the Primary AOD Code.
Select One Primary Reimbursement: Self-Pay, Blue Cross/Blue Shield, Medicare, Medicaid, Other Government Support, Worker's Compensation, Other Private Health Insurance, No Charge or Other Payment Source. Under Special Populations (Select all that Apply), check Language Barriers/English 2nd Lang. where it applies.
Under Health Care Utilization, fill in How frequently (in days) has the client used the following since admission or last update? Hospital Admissions, Emergency Room Visits/Admits (psychiatric or physical health), Outpatient Primary Care Visits (physical health) and Dental Visits.
Fill in the Number of Arrests past 30 days (AOD NOM).
Check Yes, No or Don't Know for: Does the client use tobacco products?
Fill in Drug of Choice (Secondary) and Drug of Choice (Tertiary) with the Frequency of Use, Route of Administration, Age of First Use - First Intoxication, Secondary AOD Code and Tertiary AOD Code.
Sources
[1] Ohio Behavioral Health Integrated ODMH/ODADAS Discharge Form, served PDF (the Official source link on this page).