

Form PA 1671 at a glance
What it is: The Pennsylvania Department of Human Services Health-Sustaining Medication Assessment Form is completed for the applicant/recipient who requires medication that allows the person to be employable or continue with employment.
Who signs: All items in this section must be completed by a licensed prescriber and signed by both the physician and applicant/recipient.
Only the following licensed medical providers may complete the assessment: physician, physician-assistant, certified registered nurse practitioner, or psychologist.
Only the individual who completed the employability assessment may complete and sign the form.
A filled-in Form PA 1671 example: a physician completes the form for an applicant

How to fill out Form PA 1671, box by box
Does the applicant/recipient need health-sustaining medication?
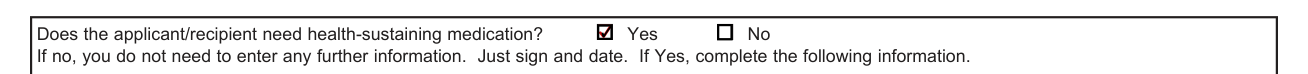
Does the applicant/recipient need health-sustaining medication? If no, you do not need to enter any further information. Just sign and date. If Yes, complete the information.
Diagnosis

Diagnosis: Record your diagnosis of the applicant/recipient's condition. The explanation should indicate whether or not the condition is chronic or temporary.
Attach documentation sufficient to support your decision such as medical records, X-rays, and lab reports. Simply providing a diagnosis is not sufficient. Without this documentation, the client will be determined ineligible for benefits.
Medication(s) needed

Medication Needed: List the medication(s) needed by the applicant/recipient that address his medical condition thus enabling him/her to be able to work.
Explain why the applicant/recipient cannot work

Explain why the APPLICANT/RECIPIENT cannot work in any capacity without this medication. (Please be specific) Explain in detail what the consequences to the applicant/recipient would be if the medication(s) were not available to him/her.
Document in this section whether the medication is for a chronic condition such as diabetes that the person will be required to take for life. Also indicate if the medication will be needed for a limited time period. If that is the case, show the date the person is expected to no longer need the medication.
Medical provider, telephone number and address

Fill in MEDICAL PROVIDER, TELEPHONE NUMBER and ADDRESS.
Signature

Signature or clinic stamps, labels, and other facsimiles are not acceptable. The signature must be original or the form will be invalidated.
The applicant/recipient also signs, on the line marked PUBLIC ASSISTANCE APPLICANT/RECIPIENT. By signing there, the applicant/recipient authorizes all medical providers, individual or facility of whatever type, including mental health and drug or alcohol treatment, to release all medical/clinical information to the Pennsylvania Department of Human Services (DHS) which relates to the applicant/recipient's ability to work.
More rules for Form PA 1671
The information on the form and attachments must be legible. If at all possible, the form and any attachments should be typed.
The inability of county staff to read your material will result in the client's application being delayed and the form being returned to you for clarification. If all questions are not answered fully, the client's application will be delayed and the form returned to you for completion.
Sources
[1] Form PA 1671 (SG) 10/16, Health-Sustaining Medication Assessment Form, Pennsylvania Department of Human Services (the Official source link on this page).
